GABBR2 / Gamma-aminobutyric acid type B receptor subunit 2 · IHC design guide

Design Immunohistochemistry for GABBR2

Plan paraffin-section GABBR2 staining around Purkinje dendrites and cortical neuropil (HPA tissue IHC). Start with the catalog antibody’s 2–5 μg/ml IHC range (datasheet A03830-2), and interpret unexpected staining cautiously because presumed off-target binding was observed (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for GABBR2 (IHC for GABBR2): expected localisation Cell and postsynaptic membranes expected (UniProt), antibody A03830-2, validated IHC image, and IHC protocol steps
Printable GABBR2 IHC protocol sheet — expected localisation Cell and postsynaptic membranes expected (UniProt), antibody A03830-2, controls and protocol steps. Open the full GABBR2 IHC guide →

GABBR2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cell and postsynaptic membranes expected (UniProt)
Staining pattern High in Purkinje dendrites and cortical neuropil (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03830-2)
Positive control ⓘ Cerebellum+2 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent (standard IHC practice; not target-specific)
Caveat Presumed off-target staining was observed (HPA tissue IHC)
Regulation Brain-enriched expression (UniProt)
Isoform / epitope No isoforms annotated; extracellular vs cytoplasmic epitope matters (UniProt)
Section 1

Recommended GABBR2 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet: A03830-2) with two published GABBR2 tissue IHC protocols (PMC10415970; PMC9434366).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human prostate cancer tissue; fixative not specified (datasheet A03830-2)
FixationImage fixative and duration unreported (datasheet A03830-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03830-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03830-2)
Primary antibodyRabbit anti-GABBR2, 2-5 μg/ml (datasheet A03830-2)
Primary incubationOvernight at 4 °C (datasheet A03830-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03830-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultGABBR2-positive staining in purkinje cells - dendrites of cerebellum (HPA tissue IHC: High). HPA tissue profile: Selective expression in CNS. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet: A03830-2). Citrate retrieval is a published alternative (PMC10415970 methods).
Section 2

What Is the Expected GABBR2 Staining Pattern?

GABBR2 is a seven-pass membrane receptor annotated at the cell membrane and postsynaptic cell membrane (UniProt O75899 topology and subcellular location). In paraffin-section IHC, expect selective CNS staining, strongest in cerebellar Purkinje-cell dendrites and cerebral-cortex neuropil (HPA: High in both). HPA rates tissue staining reliability Enhanced, while reporting medium agreement with RNA and presumed off-target binding that was disregarded (HPA tissue IHC).

What am I looking at on my slide?
Strong staining outlines Purkinje-cell dendrites or follows cortical neuropil, with little nuclear signal.This fits the strongest reported tissue patterns (HPA: High in Purkinje-cell dendrites and cortical neuropil). A membrane-associated distribution is consistent with GABBR2 topology (UniProt O75899). Chromogenic IHC cannot by itself resolve an individual postsynaptic membrane (general IHC practice).
Nuclei dominate the stain, while expected dendritic or neuropil structures remain faint.A predominantly nuclear pattern conflicts with the annotated membrane location (UniProt O75899 subcellular location). Treat it as suspect and compare with a positive tissue and a no-primary control before assigning it to GABBR2 (general IHC practice).
Adipocytes or other cells reported as negative stain strongly.HPA reports GABBR2 as Not detected in adipocytes from adipose tissue (HPA tissue IHC). Staining there raises concern for nonspecific antibody binding or endogenous detection activity; it does not, on its own, identify which source caused the signal (general IHC practice).
Brown signal spreads evenly across tissue, including areas without recognizable cellular detail.Diffuse staining obscures the selective CNS pattern reported by HPA (HPA tissue IHC). Assess no-primary and detection-only controls for reagent background, then review blocking, washing and detection conditions (general IHC practice).
Cerebellar dendrites and cortical neuropil show no detectable stain.Those are strong reference patterns, so a blank result calls for a run-level check (HPA: High in both). Confirm tissue identity, antibody use, antigen retrieval and detection performance before interpreting the specimen as GABBR2-negative (general IHC practice).
💡Expected GABBR2 appearanceCall a result consistent with GABBR2 when strong, structured staining follows Purkinje-cell dendrites or cortical neuropil (HPA: High in both); dominant nuclear stain or equally strong staining of HPA-negative adipocytes is suspect (UniProt O75899 subcellular location; HPA: Not detected in adipocytes).
How each factor affects the staining
Tissue and cell selectionHPA reports High staining in cerebellar Purkinje-cell dendrites and cortical neuropil, Medium in caudate neuronal cells, and Low in hippocampal neuronal cells (HPA tissue IHC). These differences make the first two clearer positive references; a weak hippocampal result alone is less decisive.
Membrane topology and epitopeGABBR2 has seven transmembrane segments, a large extracellular region at residues 42–483 and a cytoplasmic C-terminal region at 742–941 (UniProt O75899 topology). The supplied record does not locate the staining antibody's epitope, so topology alone cannot prescribe retrieval or permeabilisation.
Protein processingUniProt lists a signal peptide at residues 1–41 and a mature chain at 42–941 (UniProt O75899 processing). The record does not establish a shed fragment or a processing-dependent tissue stain; avoid using these annotations to explain an unexpected compartment.
Evidence strengthHPA calls tissue staining reliability Enhanced but notes medium agreement with RNA and presumed off-target binding that was disregarded (HPA tissue IHC). Two listed antibodies have Enhanced IHC status; a third is Approved (HPA antibodies). Interpret an isolated unusual pattern with controls.
IF/ICC Q&A: Is the same pattern established in cultured cells?HPA summarizes the subcellular location as membrane, but provides no ICC-IF image cell lines, no available main location and no ICC validation for the listed antibodies (HPA subcellular; HPA antibodies). Use this page's tissue pattern as context, not as a validated cultured-cell image reference.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive reference tissue is blank.A failed stain run, unsuitable retrieval or weak detection is possible (general IHC practice); the expected strong reference signal comes from HPA (HPA: High in cerebellar dendrites and cortical neuropil).Verify section identity and detection controls, then review antibody preparation and run conditions. If needed, compare retrieval conditions using the same positive reference (general IHC practice); no GABBR2-specific retrieval condition is supplied.
Only a faint hippocampal neuronal signal appears.Hippocampal neuronal staining is reported Low, so faint signal may match that reference rather than indicate a failed run (HPA tissue IHC).Judge the run against cerebellar dendrites or cortical neuropil, where HPA reports High staining (HPA tissue IHC). Compare matched negative controls before scoring a faint cell signal (general IHC practice).
Strong stain appears in HPA-negative adipocytes.The pattern conflicts with Not detected adipocyte staining (HPA tissue IHC). Nonspecific binding or endogenous detection activity could account for it (general IHC practice).Compare no-primary and detection-only controls; review blocking and detection chemistry if those controls stain (general IHC practice). Recheck cell identification before calling a new positive pattern.
Nuclei stain more strongly than neuronal processes.Dominant nuclear staining disagrees with GABBR2's annotated membrane location (UniProt O75899 subcellular location), although the stain alone cannot identify the cause.Check the no-primary control and compare staining with Purkinje-cell dendrites or cortical neuropil (HPA: High in both; general IHC practice). Do not score nuclear signal as the expected pattern.
The whole section has diffuse chromogenic background.Excess detection signal or inadequate blocking or washing can obscure tissue detail (general IHC practice). HPA describes selective CNS expression rather than uniform tissue staining (HPA tissue IHC).Inspect negative controls, review reagent timing and washing, and reduce background before interpreting cell distribution (general IHC practice).
An IF/ICC result seems inconsistent with tissue IHC.HPA provides a membrane summary but no ICC-IF image cell lines or ICC validation for the listed antibodies (HPA subcellular; HPA antibodies).Assess the IF/ICC result with its own localisation and negative controls (general IF practice). Do not infer that a cultured-cell result has the same validation as the reported tissue IHC pattern (HPA tissue IHC; HPA antibodies).

Sample controls for GABBR2 IHC & IF

🧪Run cerebellum first and look for staining in Purkinje-cell dendrites (HPA: High in cerebellar Purkinje-cell dendrites). Use adipose tissue as the negative tissue (HPA: Not detected in adipocytes); on the cerebellum slide, cells without the expected dendritic pattern should remain at background levels relative to the no-primary control (HPA: Purkinje-cell dendrites; standard IHC practice).
Positive control tissue: Cerebellum (Purkinje cells - dendrites, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for GABBR2; derive a cell-line control from the positive tissue's cell type (Purkinje cells - dendrites) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and a concentration-matched nonimmune rabbit IgG control matched to the primary antibody’s clonality when known (caption: rabbit primary; standard IHC practice). Prefer GABBR2-knockout tissue as a biological negative, or use peptide competition if the immunizing peptide is available; quench endogenous peroxidase before DAB detection in cerebellum and assess tissue autofluorescence separately for IF (standard IHC/IF practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A03830-2 paraffin-section caption does not state a fixative (caption: fixative not stated). The caption describes heat-mediated retrieval in EDTA at pH 8.0 and primary antibody at 2 μg/ml, but does not establish that retrieval is required (caption: EDTA retrieval and antibody concentration). The supplied evidence offers a paraffin IHC starting point but does not establish whether frozen sections or IF are easier; assess cerebellar autofluorescence if using IF (caption: paraffin IHC; standard IF practice).

HPA tissue IHC evidence for GABBR2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Purkinje cells - dendrites High Protein (IHC) HPA →
Cerebral cortex Neuropil High Protein (IHC) HPA →
Caudate Neuronal cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Endocrine cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced GABBR2 IHC Tips

Troubleshoot chromogenic GABBR2 staining in paraffin sections using the catalog antibody’s tissue image, protein topology, and tissue expression evidence.

Which retrieval conditions should I start with for GABBR2 in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA pH 8.0 for paraffin sections (datasheet A03830-2). The selected image used that retrieval before overnight incubation at 4°C with 2 μg/ml catalog antibody (datasheet A03830-2). Keep heating and cooling conditions consistent across sections, because retrieval variation can obscure a comparison of staining intensity (standard IHC practice). If staining is weak, adjust retrieval duration in a controlled series while holding antibody concentration and detection constant (standard IHC practice). Judge the result against a brain positive control and a no-primary control, rather than relying on the pictured prostate cancer section alone (UniProt tissue specificity; datasheet A03830-2; standard IHC practice).
Could fixation explain weak or uneven GABBR2 staining?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not report a fixative (datasheet A03830-2). Record each specimen’s fixative and fixation duration before comparing staining, since inconsistent fixation can change antigen accessibility in routine IHC (standard IHC practice). Compare adjacent sections processed together with the documented EDTA pH 8.0 retrieval and 2 μg/ml antibody condition (datasheet A03830-2; standard IHC practice). Check morphology and section adhesion alongside signal, because poorly preserved or detached areas can give misleading intensity differences (standard IHC practice). Do not assign a GABBR2-specific fixation effect from its tissue distribution or membrane topology (HPA tissue IHC; UniProt O75899 topology).
Where should convincing GABBR2 chromogenic staining appear?
Expect staining associated with neuronal processes and membranes: GABBR2 is annotated at the cell membrane and postsynaptic cell membrane (UniProt O75899 localisation). Strong tissue references include Purkinje-cell dendrites in cerebellum and neuropil in cerebral cortex; caudate neuronal cells show medium staining (HPA tissue IHC). Review these structures at high magnification before calling diffuse nuclear colour positive, since a predominantly nuclear pattern conflicts with the annotated localisation (UniProt O75899 localisation; standard IHC interpretation). The receptor has 7 transmembrane segments, so a process-rich pattern may be easier to recognise than a crisp outline around every neuronal cell body (UniProt O75899 topology; HPA tissue IHC). Record the stained compartment and cell type alongside intensity (standard IHC practice).
How should epitope location affect GABBR2 troubleshooting?
First obtain the antibody’s immunogen or epitope information before assigning a failed stain to epitope masking; none is provided in the selected caption (datasheet A03830-2). GABBR2 has a large extracellular region at residues 42–483 and a cytoplasmic tail at 742–941, separated by 7 transmembrane segments (UniProt O75899 topology). An extracellular epitope and a cytoplasmic epitope may respond differently to processing, but this antibody’s epitope cannot be placed from the supplied evidence (UniProt O75899 topology; datasheet A03830-2). The record lists 5 glycosylation sites and several phosphorylation sites; neither establishes the cause of a staining change without epitope mapping (UniProt O75899 modifications). No isoforms are listed in this record, so avoid attributing regional staining differences to an identified isoform here (UniProt O75899 isoforms).
How would I assess GABBR2 by multiplex IF alongside this IHC guide?
Treat IF as a separate assay: the supplied HPA subcellular record has no ICC/IF image evidence, while the catalog image documents chromogenic IHC in a paraffin section (HPA subcellular; datasheet A03830-2). Pair GABBR2 with a validated neuronal or Purkinje-cell marker when assessing the reported cortical neuropil or cerebellar dendritic pattern (HPA tissue IHC; standard IF practice). Choose fluorophores after checking tissue autofluorescence and include single-label controls to assess spectral spillover (standard IF practice). If the mapped epitope is cytoplasmic, optimise permeabilisation; if extracellular, test accessibility before applying stronger permeabilisation (UniProt O75899 topology; standard IF practice). Interpret apparent overlap at the resolution of the imaging method, rather than treating it alone as evidence of receptor interaction (standard IF practice).
What should I check when GABBR2 DAB staining is widespread?
Start with a no-primary control and inspect whether colour follows tissue edges, folds, or damaged areas (standard IHC practice). Quench endogenous peroxidase for the HRP–DAB workflow, and check that the 10% goat-serum block and washes are applied consistently (standard IHC practice; datasheet A03830-2). The selected image used 2 μg/ml primary antibody overnight at 4°C; titrate from that documented condition if background persists (datasheet A03830-2; standard IHC practice). Compare staining with a CNS positive control and tissue regions expected to be negative, since the HPA profile is selective for CNS (HPA tissue IHC). Widespread colour in negative-control regions warrants resolving detection background before interpreting weak GABBR2 staining (HPA tissue IHC; standard IHC practice).
How should I quantify GABBR2 staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the anatomical region and stained compartment before scoring, because the reported strong signals occur in Purkinje-cell dendrites and cortical neuropil (HPA tissue IHC). For neuronal cell bodies, report the percentage of positive cells with an intensity score or H-score; for process-rich regions, measure positive area or optical density per mm² (standard IHC practice). Normalise to viable tissue area or the relevant counted cell population, and keep section thickness, retrieval, exposure, and DAB development consistent (standard IHC practice). Set thresholds using negative controls and apply the same analysis settings across groups (standard IHC practice). Report regional scores separately, since cerebellar dendrites, cortical neuropil, and caudate neuronal cells have different reference staining levels (HPA tissue IHC).
How can I distinguish true GABBR2 signal from staining artefact?
A plausible positive pattern follows neuronal membranes or processes, with strong reference staining in cerebellar Purkinje-cell dendrites and cortical neuropil (UniProt O75899 localisation; HPA tissue IHC). Question predominantly nuclear staining, uniform colour across unrelated cell types, or signal concentrated at section edges and necrotic areas (UniProt O75899 localisation; standard IHC interpretation). Use a no-primary control and an endogenous-peroxidase check to separate HRP–DAB artefact from antibody-dependent staining (standard IHC practice). The pictured prostate cancer section shows antibody-dependent staining under its reported conditions, but the HPA tissue profile is selective for CNS and flags presumed off-target binding (datasheet A03830-2; HPA tissue IHC). Confirm unexpected sites with independent antibody or orthogonal evidence before assigning them to GABBR2 (standard IHC practice).
Boster reagents

Best GABBR2 / Gamma-aminobutyric acid type B receptor subunit 2 IHC Antibodies

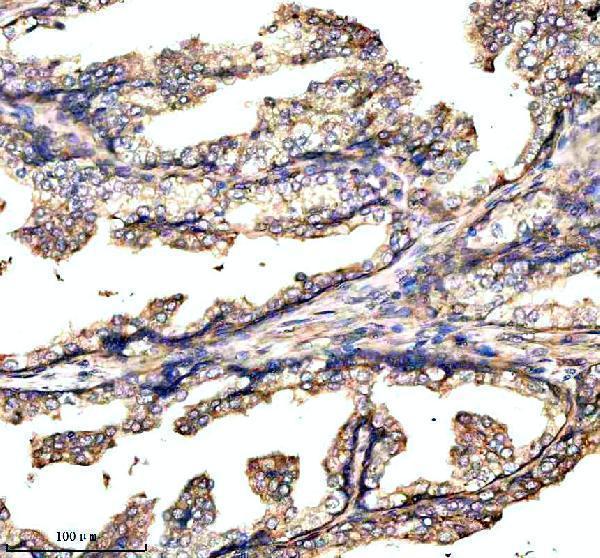
A03830-2 has a human paraffin-section IHC figure (image caption). M03830-2 lists IHC and IF/ICC for human, mouse, and rat, but has no supplied IF figure (catalog applications/reactivity; image alts).

Real IHC data IHC analysis of GABBR2 using anti-GABBR2 antibody (A03830-2). GABBR2 was detected in a paraffin-embedded section of human prostate cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-GABBR2 Antibody (A03830-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-GABBR2 Antibody ®
Cat # A03830-2

A03830-2 will render with an IHC figure from a human prostate cancer paraffin section (image caption). M03830-2 will render with listed IHC and IF/ICC applications and human, mouse, and rat reactivity; no IHC or IF image is supplied (catalog applications/reactivity; image alts).

Which to pick: For tissue IHC, choose A03830-2: its figure documents staining in a human paraffin section, with 2 μg/ml primary antibody and EDTA retrieval at pH 8.0; the fixative is unreported (A03830-2 image caption). For IF/ICC, M03830-2 lists both applications and is a rabbit monoclonal, clone 18G32, though no IF figure is supplied (M03830-2 catalog; image alts). For cross-species work, both list human, mouse, and rat reactivity; the supplied tissue IHC figure documents human tissue only (catalog reactivity; A03830-2 image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O75899 (GABR2_HUMAN, Gamma-aminobutyric acid type B receptor subunit 2).
  2. Human Protein Atlas. GABBR2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. GABBR2 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. GABBR2 antibody validation summary (3 antibodies).
  5. γ-aminobutyric acid B2 receptor: A potential therapeutic target for cholangiocarcinoma in patients with diabetes mellitus. World journal of gastroenterology 2023 — PMC10415970.
  6. miR-31-3p functions as a tumor suppressor by directly targeting GABBR2 in prostate cancer. Frontiers in oncology 2022 — PMC9434366.
  7. PubMed PMID:9872316 — UniProt-cited evidence.
  8. PubMed PMID:10087195 — UniProt-cited evidence.
  9. PubMed PMID:10328880 — UniProt-cited evidence.