This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan GGCX paraffin-section IHC using hepatocyte staining in liver as a positive reference (HPA tissue IHC). The guide covers the catalog antibody’s chromogenic workflow (datasheet A02643-1) and how to interpret cytoplasmic staining in light of GGCX’s ER membrane location (HPA tissue IHC; UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue signal; ER membrane protein (HPA tissue IHC; UniProt) | |
| Staining pattern | Hepatocytes show the strongest cytoplasmic staining (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A02643-1) | |
| Positive control | Liver+4 more · see all | |
| Negative control | Fallopian tube |
| Fixation | Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific) | |
| Caveat | Endogenous biotin may raise liver background with SABC (standard IHC practice; datasheet A02643-1) | |
| Regulation | Liver-enriched expression (HPA tissue RNA; HPA tissue IHC) | |
| Isoform / epitope | 2 isoforms; epitope mapping is needed to assess coverage (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by one published GGCX liver IHC protocol (PMC12084421).
| Sample | Paraffin-embedded human hepatic cancer tissue; fixative not specified (datasheet A02643-1) |
| Fixation | Image fixative and duration unreported (datasheet A02643-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A02643-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A02643-1) |
| Primary antibody | Rabbit anti-GGCX, 2-5 μg/ml (datasheet A02643-1) |
| Primary incubation | Overnight at 4 °C (datasheet A02643-1) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet A02643-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | GGCX-positive staining in hepatocytes of liver (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several different tissue types, most abundant in hepatocytes. No signal in the no-primary control. |
GGCX is an endoplasmic reticulum membrane protein with nine transmembrane segments (UniProt P38435 topology). In paraffin-section IHC, expect cytoplasmic staining, strongest in liver hepatocytes (HPA tissue IHC: High in hepatocytes). HPA also reports Medium staining in several other cell types. Its tissue IHC reliability is Enhanced, with medium consistency between antibody staining and RNA expression (HPA tissue IHC: reliability summary).
| Hepatocytes show prominent cytoplasmic chromogen, while nuclei remain defined by the counterstain. | This is the clearest expected positive pattern: hepatocytes are High and the reported distribution is cytoplasmic (HPA tissue IHC). The ER membrane location explains why GGCX signal is assessed in the cytoplasmic compartment (UniProt P38435 subcellular location). |
| Adrenal or breast glandular cells, bronchial respiratory epithelial cells, or cerebellar Purkinje cells show moderate cytoplasmic staining. | These are plausible positive results; each listed cell population is Medium in the HPA tissue IHC record (HPA tissue IHC). Judge the identified cell population and compartment, rather than requiring every tissue to match hepatocyte intensity. |
| Nuclear staining dominates, or a crisp cell-surface rim replaces the expected cytoplasmic pattern. | Treat this as a compartment mismatch and investigate artefact or nonspecific detection: HPA describes cytoplasmic tissue staining, and UniProt places GGCX in the ER membrane (HPA tissue IHC; UniProt P38435 subcellular location). The slide alone cannot identify the cause. |
| Strong chromogen appears in cells outside the reported pattern, or broadly across unrelated structures. | Consider cross-reactivity or endogenous detection activity and check controls (standard IHC practice). HPA reports specific cell populations, including Not detected in fallopian-tube glandular cells; that reference is a comparison, not proof that every unlisted cell is negative (HPA tissue IHC). |
| Color covers tissue and empty spaces diffusely, or hepatocytes show no discernible signal. | Diffuse background limits localization and warrants detection and wash controls (standard IHC practice). Absent signal in hepatocytes conflicts with their High HPA staining level; first assess section quality, controls, and the IHC workflow before interpreting GGCX as absent (HPA tissue IHC; standard IHC practice). |
| Subcellular topology | GGCX has 9 transmembrane segments and is assigned to the ER membrane (UniProt P38435 topology). Interpret the HPA cytoplasmic IHC profile in that context; paraffin-section chromogen does not itself resolve individual ER membranes (HPA tissue IHC; standard IHC practice). |
| Anatomic comparison | Hepatocytes are High, several listed epithelial or glandular populations and Purkinje cells are Medium, and fallopian-tube glandular cells are Not detected (HPA tissue IHC). Compare matched cell types rather than whole-section darkness (standard IHC practice). |
| Validation and its limit | The listed antibody HPA018284 has Enhanced IHC validation, while tissue IHC has medium antibody-to-RNA consistency (HPA antibodies; HPA tissue IHC reliability). These assessments support a reference pattern but cannot certify each new section or detection run. |
| Molecular annotations | UniProt lists 2 isoforms and four glycosylation sites at 459, 550, 570, and 605 (UniProt P38435). Neither record supplies the IHC antibody epitope, so these annotations cannot predict isoform selectivity, retrieval requirements, or a staining difference. |
| IF/ICC evidence | HPA's ICC-IF summary says Membrane, but gives no main location or cell-line images (HPA subcellular). Use the ER assignment as biological context, without treating that summary as an imaged cell-line staining pattern (UniProt P38435 subcellular location). |
| Situation | Likely cause | Next action |
|---|---|---|
| Hepatocytes are negative despite an otherwise readable section. | This disagrees with their High reference signal (HPA tissue IHC); one slide cannot distinguish technical failure from specimen variation. | Confirm the positive control and counterstained morphology, then review the IHC antibody dilution, retrieval, detection reagents, and run records (standard IHC practice). No GGCX-specific retrieval setting is supplied. |
| The whole section has weak, even brown haze. | Diffuse color can reflect background from detection chemistry, blocking, or washing (standard IHC practice); HPA's cell-specific profile cannot validate a uniform haze (HPA tissue IHC). | Compare a no-primary control, examine background outside cells, and review blocking, reagent handling, and washes (standard IHC practice). Score GGCX only where cellular localization remains interpretable. |
| Unexpected cells stain as strongly as hepatocytes. | Cross-reactivity or endogenous detection activity is possible (standard IHC practice). HPA documents High hepatocytes and Medium or absent signal in specified other populations, not a complete map of every cell (HPA tissue IHC). | Identify the stained cell type on the counterstained section; compare the HPA reference and no-primary control before assigning GGCX positivity (HPA tissue IHC; standard IHC practice). |
| Nuclei or tissue edges dominate the signal. | That distribution conflicts with cytoplasmic IHC staining and ER membrane localization (HPA tissue IHC; UniProt P38435 subcellular location). Artefact is possible, but its mechanism is unresolved. | Inspect morphology and the no-primary control, then review section handling, chromogen development, and counterstain balance (standard IHC practice). Do not score the misplaced signal as the expected GGCX pattern. |
| A fallopian-tube glandular sample appears strongly positive. | HPA reports Not detected for that cell population (HPA tissue IHC). A discrepancy may reflect cell identification, background, or a real sample difference; the supplied record cannot decide which. | Verify glandular-cell identity and compare the staining with a hepatocyte positive control and no-primary control (HPA tissue IHC; standard IHC practice). Report the discrepancy rather than forcing a negative score. |
| What should an IF/ICC result look like? | HPA summarizes the subcellular signal as Membrane but supplies no main location or cell-line images (HPA subcellular); UniProt assigns GGCX to the ER membrane (UniProt P38435 subcellular location). | Interpret a cellular membrane-associated signal cautiously against the ER assignment and appropriate controls (UniProt P38435; standard IF practice). The supplied HPA record does not establish a specific imaged IF/ICC pattern. |
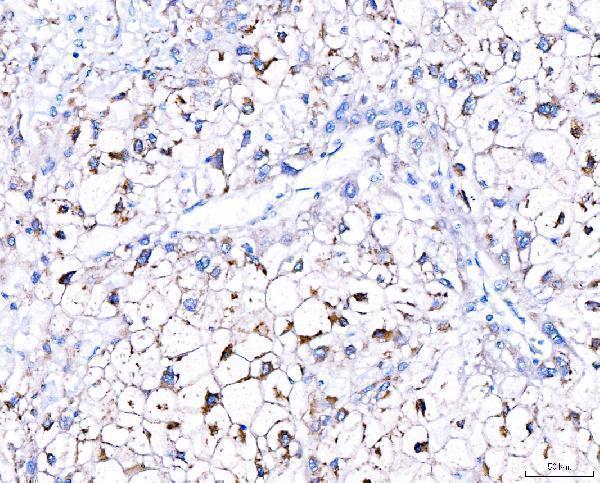
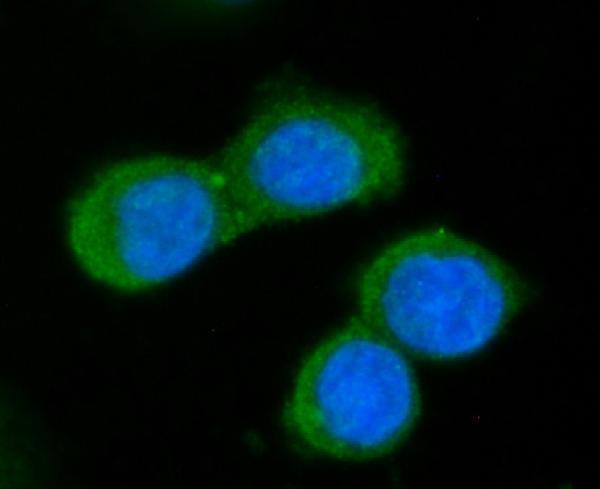


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Liver | Hepatocytes | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Breast | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Fallopian tube | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot GGCX chromogenic IHC in paraffin sections using the catalog antibody’s documented workflow, ER localisation, and tissue expression profile.
A02643-1 has IHC data from a human hepatic cancer paraffin section and IF data from CACO-2 cells (catalog image captions). Its listed reactivity is Human and Mouse (catalog).
A02643-1 will render with an IHC figure from a human hepatic cancer paraffin section (IHC image caption). The same SKU is listed for IHC and IF/ICC, with IF data from CACO-2 cells (catalog applications; IF image caption).
Which to pick: Choose A02643-1 for paraffin-section IHC based on its own human hepatic cancer figure; the fixative is unreported (IHC image caption). Choose A02643-1 for IF/ICC based on its CACO-2 figure (IF image caption). It lists Mouse reactivity, but the supplied IHC and IF figures do not establish mouse-sample performance (catalog reactivity; image captions).