GIPC1 / PDZ domain-containing protein GIPC1 · IHC design guide

Design Immunohistochemistry for GIPC1

Plan chromogenic IHC on paraffin sections using the catalog antibody at 2–5 μg/ml (datasheet A04969-4). Compare cytoplasmic staining with the high signal reported in kidney tubules and hepatocytes, while accounting for low consistency between staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for GIPC1 (IHC for GIPC1): expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody A04969-4, validated IHC image, and IHC protocol steps
Printable GIPC1 IHC protocol sheet — expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody A04969-4, controls and protocol steps. Open the full GIPC1 IHC guide →

GIPC1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC)
Staining pattern Cytoplasmic in most tissues; strong ciliary rootlet staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04969-4)
Positive control ⓘ Bronchus+4 more · see all
Negative control ⓘ Adipose tissue+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining has low consistency with RNA expression (HPA tissue IHC)
Regulation Widely expressed (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended GIPC1 IHC & IF Protocols

The catalog antibody protocol is complemented by published GIPC1 IHC methods for gastric, pancreatic, breast, and ovarian tissues (PMC10765124; PMC6820541; PMC2535783).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver cancer tissue; fixative not specified (datasheet A04969-4)
FixationImage fixative and duration unreported (datasheet A04969-4); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04969-4); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04969-4)
Primary antibodyRabbit anti-GIPC1, 2-5 μg/ml (datasheet A04969-4)
Primary incubationOvernight at 4 °C (datasheet A04969-4)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A04969-4)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultGIPC1-positive staining in ciliated cells (ciliary rootlets) of bronchus (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A04969-4); the gastric study reports heat retrieval without specifying a buffer (PMC10765124).
Section 2

What Is the Expected GIPC1 Staining Pattern?

GIPC1 is reported in the cytoplasm and at membranes, with no transmembrane segment (UniProt O14908 topology; UniProt O14908 subcellular location). In paraffin tissue IHC, expect cytoplasmic staining in many tissues, including high staining in kidney tubule cells, hepatocytes, and glandular cells of the duodenum (HPA tissue IHC). HPA rates the tissue profile Approved but reports low consistency between antibody staining and RNA expression (HPA tissue IHC reliability).

What am I looking at on my slide?
Cytoplasmic signal in kidney tubule cells or hepatocytes, with tissue structure still clear.This fits the reported IHC profile: both cell populations stain at a high level (HPA tissue IHC). Judge the signal in the named cells, since staining elsewhere in the section does not by itself confirm the expected pattern (general IHC practice).
A localized signal at ciliary rootlets in bronchial, fallopian tube, or nasopharyngeal ciliated cells.This is a reported high-staining pattern in those cell types (HPA tissue IHC). Record the cell type and location together; a broad stain over the whole epithelial surface is less specific evidence for the reported rootlet pattern (general IHC practice).
Predominantly nuclear staining in tissue cells, without the expected cytoplasmic pattern.Treat this as discordant with the tissue IHC profile (HPA tissue IHC), then review controls and detection conditions (general IHC practice). HPA reports additional nucleoplasmic localization in ICC-IF, so nuclear signal alone cannot be declared impossible (HPA subcellular ICC-IF).
Strong signal in adipocytes or smooth muscle cells while expected positive cells stain weakly.HPA reports GIPC1 as not detected in those two cell types (HPA tissue IHC). Consider antibody cross-reactivity or endogenous detection activity and compare appropriate controls (general IHC practice); a negative cell type is not a guarantee that its entire tissue section will be blank.
Diffuse color covers cells and surrounding tissue, obscuring cell boundaries.This cannot establish GIPC1 localization against the reported cytoplasmic IHC pattern (HPA tissue IHC). Background may arise from nonspecific binding, detection activity, or excess chromogen development; assess controls and exposure before scoring (general IHC practice).
💡Expected GIPC1 appearanceA convincing positive has discernible cytoplasmic staining in HPA high-staining cells such as kidney tubule cells or hepatocytes (HPA tissue IHC); widespread diffuse color or strong signal confined to HPA-negative adipocytes is suspect (HPA tissue IHC; general IHC practice).
How each factor affects the staining
Tissue and cell choiceHPA reports high staining in kidney tubule cells, hepatocytes, and several glandular populations, but no detection in adipocytes or smooth muscle cells (HPA tissue IHC). Choose comparison cells by identity within the section; an entire organ is not a uniform positive or negative control (general IHC practice).
Assay-specific localizationThe tissue IHC summary is cytoplasmic, while ICC-IF places GIPC1 mainly at plasma membranes and cell junctions, with additional nucleoplasmic localization (HPA tissue IHC; HPA subcellular ICC-IF). Use the tissue profile to judge chromogenic paraffin sections; the IF finding answers a separate localization question.
Antibody evidenceHPA lists rabbit pAb HPA043958 as Approved for IHC and rabbit pAb HPA061786 as Uncertain for ICC (HPA antibodies). The tissue IHC profile itself is Approved with low RNA–staining consistency (HPA tissue IHC reliability); these labels do not establish equivalent performance across assays or antibodies.
Topology and isoformsUniProt describes GIPC1 as cytoplasmic and membrane-associated without a transmembrane segment, and lists two isoforms (UniProt O14908 topology; UniProt O14908 isoforms). These facts do not locate the antibody epitope or predict isoform-specific staining; interpret any claimed selectivity against antibody-specific evidence.
Antigen retrievalFor paraffin IHC, follow the IHC-validated antibody's documented retrieval conditions and check section morphology alongside signal (general IHC practice). No target-specific fixation effect or GIPC1 retrieval preference is established by the supplied UniProt or HPA records.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in a known high-staining population such as kidney tubule cells.The run may have failed, or the tested antibody conditions may be unsuitable (general IHC practice); HPA reports high staining in these cells (HPA tissue IHC).Check a documented positive control and the antibody's IHC conditions, including retrieval, dilution, and detection steps (general IHC practice). Do not infer a GIPC1-specific fixation effect from this result.
Adipocytes or smooth muscle cells stain strongly.These cells are listed as not detected (HPA tissue IHC); nonspecific binding or endogenous detection activity are possible explanations (general IHC practice).Compare a no-primary control and inspect whether the color follows cells or background; review blocking and detection controls (general IHC practice). Score named cell populations rather than the whole tissue.
Color appears across the section with poor cellular definition.Excess background or detection activity can obscure localization (general IHC practice), making comparison with HPA's cytoplasmic pattern unreliable (HPA tissue IHC).Inspect the no-primary control, review blocking and washes, and adjust chromogen development according to the detection system (general IHC practice). Reassess only where cell boundaries remain interpretable.
Staining is mainly nuclear in a paraffin section.This differs from the reported cytoplasmic tissue IHC profile (HPA tissue IHC), although additional nucleoplasmic signal is reported in ICC-IF (HPA subcellular ICC-IF).Check control sections and antibody documentation, then report the observed compartment explicitly (general IHC practice). Do not use the ICC-IF finding alone to validate a nuclear IHC result.
A glandular or ciliated region appears weaker than expected.HPA reports high staining in specified glandular cells and ciliary rootlets, not every cell in those tissues (HPA tissue IHC); the sampled cell population may differ.Confirm cell identity and compare a second HPA high-staining population on the same run before changing IHC conditions (HPA tissue IHC; general IHC practice).
IHC and ICC-IF images appear to disagree on location.HPA summarizes tissue IHC as cytoplasmic but ICC-IF mainly as plasma membrane and cell junction signal, with additional nucleoplasmic signal (HPA tissue IHC; HPA subcellular ICC-IF).Interpret each image within its assay and cell context, and retain the antibody's assay-specific validation status in the report (HPA antibodies; general IHC practice).

Sample controls for GIPC1 IHC & IF

🧪Run bronchus first and look for staining in ciliated cells at the ciliary rootlets (HPA: High in bronchus ciliated cells); run adipose tissue as the negative reference, focusing on adipocytes (HPA: Not detected in adipocytes). On the bronchus slide, cells without ciliary rootlets should lack that rootlet staining pattern, though other staining should be assessed separately (HPA: High in ciliated cells at ciliary rootlets).
Positive control tissue: Bronchus (Ciliated cells (ciliary rootlets), HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show GIPC1 in MCF-7, PC-3, U2OS, with annotated localisation: Plasma membrane (approved), Cell Junctions (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control for the rabbit catalog antibody (selected A04969-4 IHC caption: rabbit primary and anti-rabbit secondary); use GIPC1 knockout material as a biological specificity control where available. Quench endogenous peroxidase before HRP/DAB detection in bronchus sections (selected A04969-4 IHC caption: HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A04969-4 paraffin-section caption does not state its fixative (selected A04969-4 IHC caption: fixative unreported). The caption uses heat retrieval in EDTA at pH 8.0, but does not establish whether retrieval is required; the supplied evidence does not establish that frozen sections or IF are easier (selected A04969-4 IHC caption: EDTA retrieval; HPA: ICC-IF images). In bronchus, section orientation or truncated cilia can complicate scoring of the ciliary-rootlet pattern (HPA: High in bronchus ciliated cells at ciliary rootlets).

HPA tissue IHC evidence for GIPC1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bronchus Ciliated cells (ciliary rootlets) High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Fallopian tube Ciliated cells (ciliary rootlets) High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced GIPC1 IHC Tips

Troubleshoot GIPC1 chromogenic IHC in paraffin sections using the catalog antibody’s tissue protocol, with IF guidance for cross-checking localisation.

What retrieval should I try first when GIPC1 staining is weak in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A04969-4). The selected tissue image used this retrieval before incubation with 2 μg/ml antibody overnight at 4°C, so keep those conditions consistent while troubleshooting (datasheet A04969-4). If staining remains weak, adjust heating duration on matched sections and check morphology and background before testing another retrieval buffer (standard IHC practice). Score epithelial or hepatocyte cytoplasmic staining as well as any membrane pattern, because the reported tissue and subcellular patterns differ (HPA: tissue IHC; HPA: subcellular).
Could fixation explain weak or patchy GIPC1 staining?
Target-specific sensitivity to fixation is unknown: the selected paraffin-section caption does not state a fixative (datasheet A04969-4). Record the fixative, fixation duration, section age and processing history for each specimen, then compare matched sections processed together (standard IHC practice). Begin troubleshooting with the reported EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody overnight at 4°C before changing one processing variable at a time (datasheet A04969-4). Examine whether patchiness follows tissue edges, folds or poorly preserved areas, and avoid assigning those patterns to GIPC1 without a reproducible cellular signal (standard IHC practice).
Should GIPC1 stain cytoplasm or cell membranes in tissue sections?
Expect cytoplasmic staining in many tissue types when reading chromogenic sections (HPA: tissue IHC, cytoplasmic expression in most tissues). GIPC1 is annotated in cytoplasm and at membranes, with no transmembrane segment, so membrane-adjacent staining is plausible but does not alone establish membrane insertion (UniProt O14908: subcellular location and topology). Cell-based IF places it mainly at plasma membranes and cell junctions, with additional nucleoplasmic signal; assess that evidence separately from tissue IHC (HPA: subcellular). Compare staining within intact cells across the same section, using a counterstain to locate nuclei and excluding diffuse extracellular deposit from cellular scoring (standard IHC practice).
Could isoforms or epitope masking change the IHC pattern?
GIPC1 has 2 reported isoforms and a PDZ domain spanning residues 133–213 (UniProt O14908: isoforms and domains). The supplied antibody caption does not identify its epitope, so it cannot establish whether the antibody distinguishes isoforms or whether retrieval exposes a particular domain (datasheet A04969-4). Several phosphorylated residues are annotated, including serines 68 and 222; their effect on this antibody’s staining is unknown (UniProt O14908: modified residues; datasheet A04969-4). If a compartment or specimen gives an unexpected result, compare an independently validated epitope where available and retain the same retrieval and scoring conditions (standard IHC practice).
How can IF help check an unexpected GIPC1 IHC pattern?
Use IF as an independent localisation check, multiplexing GIPC1 with a validated marker for the cell population being assessed, such as ciliated cells when examining bronchus (HPA: high staining in bronchial ciliary rootlets; standard IF practice). Select spectrally separated fluorophores and consider a far-red GIPC1 channel if tissue autofluorescence obscures shorter wavelengths (standard IF practice). Because GIPC1 has no transmembrane segment and the antibody epitope is unspecified, compare permeabilized and nonpermeabilized conditions before interpreting staining on either side of a membrane (UniProt O14908: topology; datasheet A04969-4). Include single-color and secondary-only controls, then compare cellular localisation with the chromogenic section (standard IF practice).
How do I separate nonspecific brown staining from GIPC1 signal?
The selected paraffin-section example used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, a peroxidase-conjugated secondary for 30 minutes at 37°C, and DAB development (datasheet A04969-4). Run a no-primary control and apply a peroxidase block to distinguish endogenous enzyme activity from antibody-dependent staining (standard IHC practice). If background persists, titrate the primary antibody and shorten chromogen development while keeping retrieval and exposure comparable across sections (standard IHC practice). Judge signal within preserved cell boundaries and against the expected cytoplasmic tissue pattern, rather than counting diffuse precipitate or staining at damaged edges (HPA: tissue IHC; standard IHC practice).
What is a defensible way to score GIPC1 IHC across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, then record percent positive cells and an intensity-weighted H-score from 0–300 for each region (standard IHC practice). Normalize counts or stained area to the number of eligible nucleated cells or intact tissue area in mm², excluding necrosis and section artifacts (standard IHC practice). Keep retrieval, antibody concentration, DAB development and image acquisition consistent; the selected example used EDTA pH 8.0 and 2 μg/ml primary antibody (datasheet A04969-4). Report cytoplasmic and membrane-associated scores separately when both appear, because the tissue and cell-based localisation records emphasize different compartments (HPA: tissue IHC; HPA: subcellular).
When should I doubt a positive GIPC1 IHC result?
Treat a signal as more credible when it follows intact cells and recurs in comparable sections, with cytoplasmic staining consistent with the tissue IHC profile (HPA: tissue IHC; standard IHC practice). High staining in hepatocytes and kidney tubule cells provides reference patterns, whereas adipocytes and smooth muscle cells were reported as not detected in those tissue contexts (HPA: tissue IHC). Distrust staining confined to tissue edges, folds, necrosis or no-primary controls, and check for endogenous peroxidase before calling brown deposits positive (standard IHC practice). HPA rates tissue staining Approved but reports low consistency with RNA expression, so interpret any surprising compartment or cell population with orthogonal evidence (HPA: tissue IHC reliability).
Boster reagents

Best GIPC1 / PDZ domain-containing protein GIPC1 IHC Antibodies

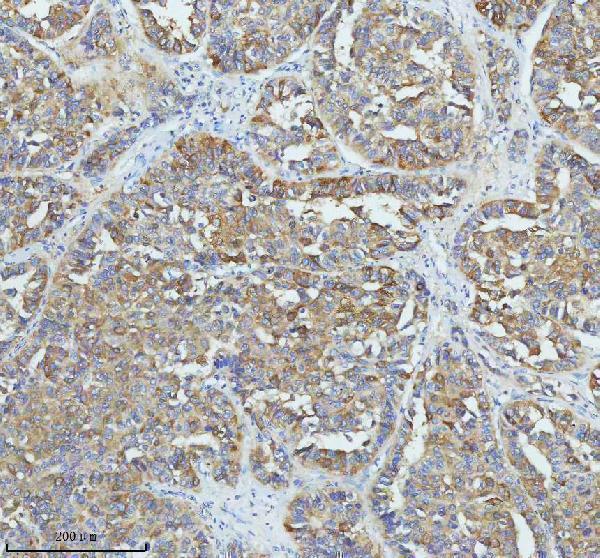
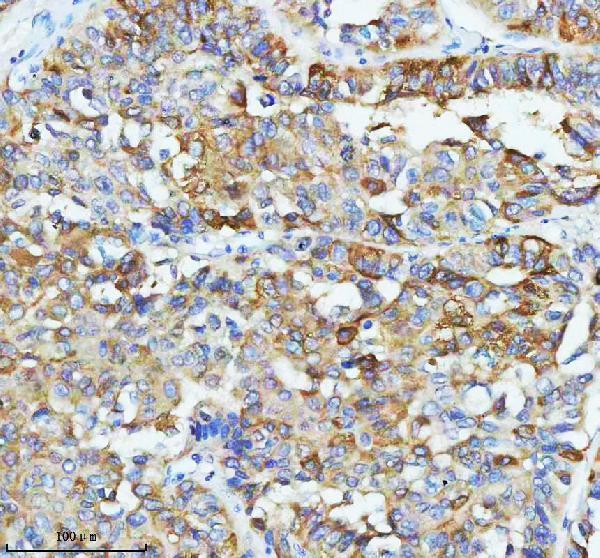
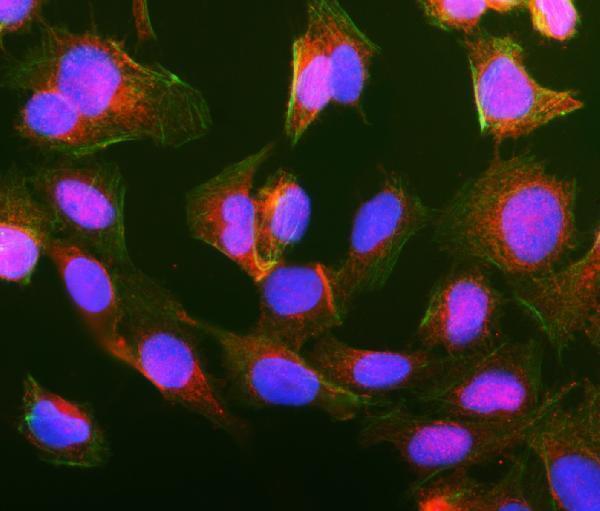
A04969-4 has IHC images from paraffin sections of human liver cancer and mouse small intestine, plus IF data from U2OS cells (catalog image captions).

Real IHC data IHC analysis of GIPC1 using anti-GIPC1 antibody (A04969-4). GIPC1 was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-GIPC1 Antibody (A04969-4) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-GIPC1 Antibody ®
Cat # A04969-4

A04969-4 is shown in IHC on paraffin sections of human liver cancer and mouse small intestine (catalog IHC captions). The same SKU is shown in IF/ICC on U2OS cells and lists human, mouse, and rat reactivity; the IF/ICC dilution is listed for human samples (catalog IF caption and applications).

Which to pick: Choose A04969-4 for paraffin-section IHC: its captions document heat retrieval in EDTA at pH 8.0 and a primary concentration of 2 μg/ml (catalog IHC captions). For IF/ICC, A04969-4 has a U2OS image at 5 μg/ml; for work across species, it lists human, mouse, and rat reactivity, while the supplied IHC images show human and mouse samples (catalog IF caption, reactivity list, and IHC captions). The IHC captions do not report a fixative, and the catalog does not report clonality (catalog IHC captions and clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O14908 (GIPC1_HUMAN, PDZ domain-containing protein GIPC1).
  2. Human Protein Atlas. GIPC1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. GIPC1 subcellular location (ICC-IF): Mainly localized to the plasma membrane and cell junctions. In addition localized to the nucleoplasm..
  4. Human Protein Atlas. GIPC1 antibody validation summary (2 antibodies).
  5. GIPC1 promotes tumor growth and migration in gastric cancer via activating PDGFR/PI3K/AKT signaling. Oncology research 2023 — PMC10765124.
  6. Silencing of Neuropilins and GIPC1 in pancreatic ductal adenocarcinoma exerts multiple cellular and molecular antitumor effects. Scientific reports 2019 — PMC6820541.
  7. CAPG and GIPC1: Breast Cancer Biomarkers for Bone Metastasis Development and Treatment. Journal of the National Cancer Institute 2016 — PMC4808632.
  8. Native human autoantibodies targeting GIPC1 identify differential expression in malignant tumors of the breast and ovary. BMC cancer 2008 — PMC2535783.
  9. PubMed PMID:9770488 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15057824 — UniProt-cited evidence.