This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section GZMB IHC around cytoplasmic staining in subsets of immune cells (HPA tissue IHC). Use bone marrow hematopoietic cells or splenic red-pulp cells as positive tissue references, and account for secretion when interpreting the pattern (HPA tissue IHC; UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Selective cytoplasmic staining in immune-cell subsets (HPA tissue IHC) | |
| Staining pattern | Immune-cell subsets show cytoplasmic staining (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Bone marrow+1 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep formalin fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Secretion may separate protein staining from RNA location (HPA tissue IHC) | |
| Regulation | Expression regulation is not annotated (UniProt) | |
| Isoform / epitope | No isoforms; epitopes in cleaved aa 1–20 may be lost (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet) is paired with two published GZMB IHC protocols (PMC12816328; PMC12146097).
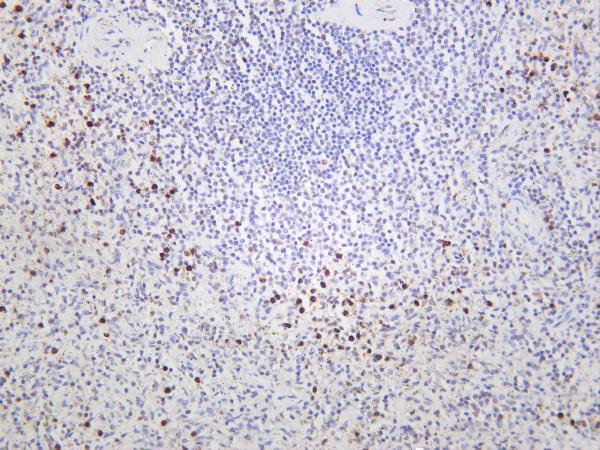
| Sample | Paraffin-embedded human T cell lymphoma tissue; fixative not specified (datasheet M00353-1) |
| Fixation | Image fixative and duration unreported (datasheet M00353-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit monoclonal (clone AAHC-7) anti-GZMB, 1:50-1:200 (datasheet M00353-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | GZMB-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: Medium). HPA tissue profile: Selective cytoplasmic expression in subsets of immune cells. No signal in the no-primary control. |
In paraffin-section IHC, expect selective cytoplasmic GZMB staining in subsets of immune cells, consistent with its cytolytic-granule location (HPA: selective cytoplasmic expression; UniProt P10144: cytolytic granule). Hematopoietic cells in bone marrow and cells in splenic red pulp show medium staining (HPA: tissue IHC). The tissue profile has Enhanced reliability; GZMB has no transmembrane segment and is also secreted, so extracellular signal needs cautious interpretation (HPA: Enhanced; UniProt P10144: topology and location).
| Discrete cytoplasmic staining in scattered immune cells, with stronger representation in the expected positive areas. | This fits the selective tissue pattern (HPA: selective cytoplasmic expression). Granule-associated staining is plausible because GZMB resides in cytolytic granules of cytotoxic T cells and NK cells (UniProt P10144: function and location). HPA does not establish the identity of every stained cell on a section. |
| Predominantly nuclear, uniform membranous, or widespread staining across unrelated cell types. | Reassess specificity and detection artefact: HPA reports selective cytoplasmic tissue staining, while UniProt reports no transmembrane segment (HPA: tissue IHC; UniProt P10144: topology). Secreted GZMB can complicate extracellular interpretation (UniProt P10144: secreted); compartment alone does not prove whether extracellular signal is specific. |
| Strong staining of adipocytes, respiratory epithelium, or glandular cells instead of a selective immune-cell subset. | Check cross-reactivity and endogenous detection activity with controls. These cell classes are reported as not detected in the listed adipose tissue, bronchus, adrenal gland, and cervix samples (HPA: tissue IHC). Compare the exact cell class and tissue; a negative HPA observation is not a universal exclusion. |
| Diffuse chromogen over most of the section, including areas without identifiable positive cells. | Treat the distribution as background until controls resolve it. A broad haze does not resemble the selective cytoplasmic profile (HPA: tissue IHC). As general IHC practice, assess primary-antibody omission, endogenous enzyme activity, blocking, washes, and chromogen development. |
| No staining in bone-marrow hematopoietic cells or splenic red-pulp cells. | Investigate the assay before calling the study tissue negative: both are reported at medium staining level (HPA: tissue IHC). Their positive-cell subsets still require inspection; absence from every cell is not expected from a selective immune-cell pattern (HPA: tissue IHC). |
| Cell population and control tissue (HPA: tissue IHC) | Bone-marrow hematopoietic cells and splenic red-pulp cells are reported at medium level; appendix lymphoid tissue, lymph-node germinal-center cells, and tonsil germinal-center cells are low (HPA: tissue IHC). Choose controls by the reported cell population, then look for selective staining rather than demanding uniform positivity. |
| Granule location and secretion (UniProt P10144: location) | GZMB is associated with cytolytic granules and is secreted (UniProt P10144: location). Cytoplasmic immune-cell staining aligns with HPA tissue observations (HPA: tissue IHC). Extracellular color alone is harder to assign to a producing cell and warrants comparison with controls. |
| Protein processing and epitope information (UniProt P10144: processing) | The precursor has a signal peptide at residues 1–18 and propeptide at 19–20; the annotated chain spans 21–247 (UniProt P10144: processing). Glycosylation sites are annotated at 71 and 104 (UniProt P10144: glycosylation). Without the antibody epitope, these facts cannot predict retrieval choice or staining strength. |
| Antibody validation (HPA: antibody validation) | HPA003418 and CAB000376 each have Enhanced IHC status (HPA: antibody validation). This supports the reported tissue pattern, but does not validate an unspecified catalog antibody, dilution, retrieval condition, or every positive cell in a new specimen. |
| IF/ICC: should its signal define the paraffin-section IHC pattern? | No. HPA reports an approved calyx location in sperm by ICC-IF, while its tissue IHC profile is selective cytoplasmic staining in immune-cell subsets (HPA: subcellular ICC-IF; HPA: tissue IHC). Read the sperm observation in its own sample and assay context. |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive-control section is blank. | Positive cells may be missed, or a general IHC step may have failed; the supplied sources do not establish a GZMB-specific fixation or retrieval effect. | Inspect bone-marrow hematopoietic cells or splenic red pulp reported at medium level (HPA: tissue IHC). As general IHC practice, verify control staining, retrieval, primary incubation, and detection steps before interpreting study negatives. |
| All cells look positive. | Uniform staining conflicts with selective cytoplasmic expression (HPA: tissue IHC); background or overdevelopment is possible under general IHC practice. | Compare a primary-antibody omission control, shorten chromogen development if excessive, and review washes and blocking as general IHC practice. Score only cell-associated staining that remains interpretable. |
| Nuclei or cell borders dominate the signal. | That pattern conflicts with HPA tissue cytoplasmic staining and UniProt granule location; GZMB has no transmembrane segment (HPA: tissue IHC; UniProt P10144: location and topology). | Check the counterstain and detection controls, then compare compartment and cell identity against a known-positive section. Treat the discordant pattern as unconfirmed until controls support it. |
| Unexpected epithelial or adipocyte staining appears. | Cross-reactivity or endogenous detection activity may explain the signal. HPA reports no detection in respiratory epithelial cells of bronchus and adipocytes of adipose tissue (HPA: tissue IHC). | Compare those specific cell types with the immune-cell pattern, run a primary-antibody omission control, and address endogenous enzyme activity as general chromogenic IHC practice. |
| Only extracellular or diffuse signal is visible. | Secreted GZMB is annotated (UniProt P10144: location), but diffuse chromogen can also be nonspecific under general IHC practice. HPA tissue IHC describes selective cytoplasmic cellular staining (HPA: tissue IHC). | Record extracellular signal separately from positive cells. Use detection controls and a positive tissue section to decide whether the cellular pattern is reproducible; avoid assigning the diffuse signal to a particular cell. |
| A low-level lymphoid sample is negative while the positive control works. | The expected signal may be sparse: HPA lists low staining in appendix lymphoid tissue and lymph-node or tonsil germinal-center cells (HPA: tissue IHC). | Review the relevant cell populations and section area before scoring. Keep the medium-level bone-marrow or spleen control in the run (HPA: tissue IHC), and report a negative study section without claiming GZMB is absent from every immune cell. |



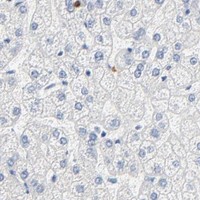


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data. At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Spleen | Cells in red pulp | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
These questions address GZMB staining in paraffin sections with chromogenic detection, with one entry for the separate IF/ICC workflow.
Two human-reactive anti-GZMB antibodies have IHC images from paraffin-embedded human T cell lymphoma and human spleen (catalog image captions). Both list IF, but neither has an IF figure (catalog applications and images).
M00353-1 lists Human IHC, IF and ICC, with an IHC image captioned as paraffin-embedded human T cell lymphoma (catalog applications, reactivity and image caption). M00353-3 lists Human IHC and IF, with an IHC image captioned as human spleen; its tissue processing is unreported (catalog applications, reactivity and image caption).
Which to pick: For paraffin-section tissue IHC, choose M00353-1: its own image caption specifies paraffin-embedded human T cell lymphoma, but does not report the fixative (catalog image caption). For IF/ICC, choose M00353-1 if ICC is required; both M00353-1 and M00353-3 list IF, with 1:50–1:200 and 1:200–1:1000 catalog dilutions respectively (catalog applications and dilutions). For Human/Mouse IHC, consider M00353-4 or PA1738; PA1738 also lists Rat reactivity, but its stated IHC-P species are Human and Mouse (catalog reactivity and application data).