This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic HIBADH IHC in paraffin sections using observed cytoplasmic staining as the tissue reference and mitochondrial localisation as the molecular expectation (HPA tissue IHC; UniProt). Compare high staining in breast glandular cells with undetected staining in oral mucosal squamous cells (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining; mitochondrial protein (HPA tissue IHC; UniProt) | |
| Staining pattern | Cytoplasmic staining in most tissues (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Oral mucosa+2 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Staining varies by cell type, including within epithelia (HPA tissue IHC) | |
| Regulation | No expression regulation specified (UniProt) | |
| Isoform / epitope | No annotated isoforms; mature chain spans aa 37–336 (UniProt) |
The catalog antibody’s IHC-P protocol is paired with a published HIBADH staining protocol for bovine testis and epididymis (PMC4489673).
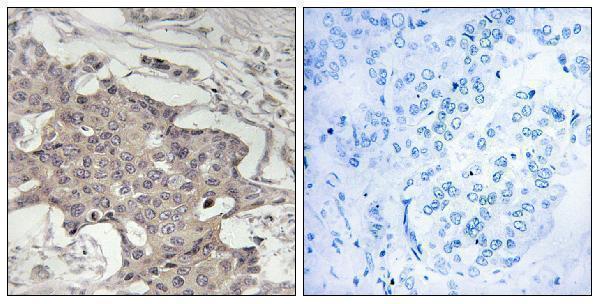
| Sample | Paraffin-embedded human breast carcinoma tissue; fixative not specified (datasheet A08760-1) |
| Fixation | Image fixative and duration unreported (datasheet A08760-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-HIBADH, 1:100 - 1:300 (datasheet A08760-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | HIBADH-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
HIBADH is a mitochondrial protein with no annotated transmembrane segment (UniProt P31937: subcellular location and topology). In paraffin-section IHC, expect cytoplasmic staining in many tissues, including high staining in glandular and respiratory epithelial cells (HPA: tissue IHC). HPA rates the tissue pattern Enhanced, while describing antibody staining and RNA expression as only moderately consistent and external verification as pending (HPA: tissue IHC reliability).
| Clear cytoplasmic staining in adrenal or breast glandular cells, or bronchial respiratory epithelial cells. | This agrees with the reported high staining in those cell populations (HPA: tissue IHC). A granular cytoplasmic appearance would be compatible with mitochondrial localisation (UniProt P31937: mitochondrion), but the supplied HPA tissue profile establishes cytoplasmic staining, not a required granule shape. |
| Strong staining appears predominantly in nuclei or along cell membranes. | Treat this as an unexpected compartment and review controls and staining conditions: HPA reports a cytoplasmic tissue pattern (HPA: tissue IHC), and UniProt places HIBADH in mitochondria without an annotated transmembrane segment (UniProt P31937: location and topology). Appearance alone cannot identify the artefact. |
| Strong signal is confined to oral or vaginal squamous epithelium, or to smooth muscle cells. | Those specific cell populations are reported as not detected (HPA: tissue IHC). Suspect nonspecific antibody staining or endogenous chromogen-generating activity, then compare appropriate negative and detection controls (general chromogenic IHC practice). Do not treat an entire tissue as negative when its other cells were not assessed here. |
| Colour spreads across stroma, extracellular spaces, or most cells without clear cellular boundaries. | This is difficult to score as HIBADH: the reported pattern is cellular and cytoplasmic (HPA: tissue IHC). Review background in a matched negative control and the detection-only control; excessive primary concentration, incomplete blocking, or detection background are general IHC possibilities, not established HIBADH-specific effects. |
| No convincing signal appears in a section expected to contain high-staining cells. | First confirm that the relevant cells are present and preserved. Adrenal and breast glandular cells and bronchial respiratory epithelial cells are reported as high (HPA: tissue IHC). A blank result could reflect a failed staining run or unsuitable assay conditions (general IHC practice); it does not establish HIBADH absence. |
| Cell population and reference intensity | HPA reports high staining in several glandular and epithelial populations, medium in endometrial stromal cells, and no detection in selected squamous epithelial and smooth muscle cells (HPA: tissue IHC). Score the named cell type rather than assigning one intensity to a whole organ. |
| Mitochondrial location and processing | UniProt places HIBADH in mitochondria, annotates a mature chain at residues 37–336, and lists no transmembrane segment (UniProt P31937: location, chain and topology). These annotations guide compartment interpretation; they do not establish an IHC epitope or a particular retrieval condition. |
| Antibody and tissue evidence | Both listed antibodies have Enhanced IHC status (HPA: HPA019522 and HPA021002). The overall tissue reliability description still reports medium agreement with RNA and pending external verification (HPA: tissue IHC). Use these observations as reference patterns, not proof that every sample will match. |
| IF/ICC localisation? | HPA provides no main ICC-IF location and lists no cell lines with ICC-IF images (HPA: subcellular record). Mitochondrial localisation is annotated by UniProt (UniProt P31937: subcellular location), but this payload cannot validate an IF staining pattern or supply an IF protocol. |
| Situation | Likely cause | Next action |
|---|---|---|
| Adrenal or breast glandular cells show no chromogenic signal. | The run may have failed, the relevant cells may be absent, or assay conditions may be unsuitable (general IHC practice). These cells are reported high (HPA: tissue IHC). | Check morphology and a known-positive control from the same run, then review primary dilution, retrieval and detection steps against the validated IHC procedure (general IHC practice). Do not infer a HIBADH-specific fixation effect from this result. |
| The stain is mainly nuclear or outlines plasma membranes. | That distribution conflicts with reported cytoplasmic IHC and mitochondrial annotation (HPA: tissue IHC; UniProt P31937: location and topology); the precise cause is undetermined. | Inspect the detection-only control and repeat with an appropriate positive section; compare localisation at the cellular level before scoring (general IHC practice). |
| Oral or vaginal squamous cells stain strongly. | These cell types are reported as not detected (HPA: tissue IHC). Nonspecific binding or endogenous detection activity are possible general IHC causes. | Compare a no-primary control and, for peroxidase detection, verify the endogenous peroxidase blocking step (general chromogenic IHC practice). Reassess only the named squamous cell population. |
| Smooth muscle cells stain as strongly as neighbouring positive cells. | HPA reports no detection in smooth muscle cells (HPA: tissue IHC); broad colour could arise from background or misidentified cell boundaries (general IHC practice). | Check morphology, staining boundaries and matched negative controls. Record the discrepancy by cell type and avoid calling the whole section HIBADH positive solely from this signal. |
| Diffuse chromogen obscures individual cells. | Widespread background prevents comparison with HPA's cytoplasmic cell pattern (HPA: tissue IHC); excessive detection activity or insufficient blocking are general IHC possibilities. | Review negative and detection-only controls, blocking, washes and primary dilution under the validated IHC workflow (general IHC practice). Score only after cellular localisation is distinguishable. |
| IF/ICC gives a pattern that seems inconsistent with IHC. | HPA supplies no ICC-IF images or assigned main subcellular location for this target (HPA: subcellular record), so the supplied evidence cannot resolve the discrepancy. | Interpret the paraffin IHC slide against its tissue and cell controls (HPA: tissue IHC). Consult the separate IF/ICC guide for that application's validation; mitochondrial location alone does not validate its staining pattern (UniProt P31937: mitochondrion). |



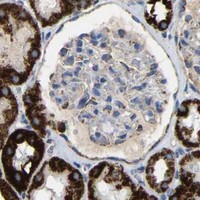
Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
Troubleshoot HIBADH staining in paraffin sections by checking retrieval, cellular pattern and controls before comparing chromogenic signal across samples.
A08760-1 is listed for IHC, IF and ICC in human, mouse and rat (catalog: applications/reactivity). Its IHC figure shows paraffin-embedded human breast carcinoma tissue (catalog: IHC image caption).
A08760-1 will render with an IHC figure of paraffin-embedded human breast carcinoma tissue (catalog: IHC image caption). IF and ICC are listed applications, and human, mouse and rat are listed as reactive species; no IF image is supplied (catalog: applications/reactivity/IF image alts).
Which to pick: For tissue IHC, choose A08760-1 for paraffin sections: its own caption documents human breast carcinoma tissue, but does not report the fixative (catalog: A08760-1 IHC image caption). For IF/ICC, A08760-1 lists both applications and an IF dilution of 1:50 (catalog: A08760-1 applications/IF dilution). For cross-species work, A08760-1 is a rabbit polyclonal listed as reactive with human, mouse and rat; its supplied IHC figure shows human tissue (catalog: A08760-1 host/dilution_raw/reactivity/IHC image caption).