HMGB2 / High mobility group protein B2 · IHC design guide

Design Immunohistochemistry for HMGB2

Plan chromogenic HMGB2 IHC around nuclear tissue staining (HPA tissue IHC) and the catalog antibody’s 0.5–1 μg/mL IHC range (datasheet PB10002). Use marrow hematopoietic cells and lymph node germinal center cells as positive references (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
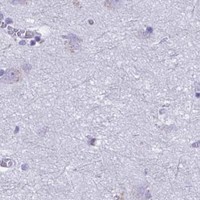
Immunohistochemistry protocol sheet for HMGB2 (IHC for HMGB2): expected localisation Predominantly nuclear tissue staining (HPA tissue IHC), antibody PB10002, validated IHC image, and IHC protocol steps
Printable HMGB2 IHC protocol sheet — expected localisation Predominantly nuclear tissue staining (HPA tissue IHC), antibody PB10002, controls and protocol steps. Open the full HMGB2 IHC guide →

HMGB2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Predominantly nuclear tissue staining (HPA tissue IHC)
Staining pattern Ubiquitous nuclear staining across tissue cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB10002)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Salivary gland+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining may include protein from another gene (HPA tissue IHC)
Regulation Marrow/lymphoid RNA group enriched (HPA tissue RNA)
Isoform / epitope 0 annotated isoforms; one 1–209 chain (UniProt)
Section 1

Recommended HMGB2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol uses EDTA pH 8.0 retrieval (datasheet: PB10002). The published tissue protocols below provide four additional HMGB2 examples (PMC7789524; PMC7576003; PMC9769043; PMC12632091).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse intestine tissue; fixative not specified (datasheet PB10002)
FixationImage fixative and duration unreported (datasheet PB10002); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB10002); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB10002)
Primary antibodyRabbit anti-HMGB2, 0.5-1μg/ml (datasheet PB10002)
Primary incubationOvernight at 4 °C (datasheet PB10002)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB10002)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultHMGB2-positive staining in endocrine cells of appendix (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 for the catalog antibody (datasheet: PB10002); the cited protocols use citrate pH 6.0 where specified (PMC7576003; PMC9769043; PMC12632091).
Section 2

What Is the Expected HMGB2 Staining Pattern?

HMGB2 is predominantly nuclear in its basal state and has no transmembrane segment (UniProt P26583). In paraffin-section IHC, expect nuclear staining across tissues, with high signal reported in bone-marrow hematopoietic cells, lymph-node germinal-center cells, gastrointestinal endocrine cells and skin basal-layer cells (HPA tissue IHC). HPA rates the tissue profile Enhanced for staining–RNA consistency, while cautioning that the target may involve more than one gene (HPA tissue IHC).

What am I looking at on my slide?
Nuclear chromogen is strongest in germinal-center cells or bone-marrow hematopoietic cells.This fits high staining in those cell populations (HPA tissue IHC). Compare the cells that stain, rather than judging the entire tissue section as uniformly positive (general IHC practice).
Membrane outlines dominate, with little nuclear staining in expected positive cells.A dominant membrane pattern conflicts with basal nuclear localization and the absence of a transmembrane segment (UniProt P26583). Review detection and controls before interpreting it as HMGB2 (general IHC practice).
Strong signal appears in salivary-gland glandular cells or skeletal-muscle myocytes.Both are reported as not detected (HPA tissue IHC). Check antibody specificity and endogenous detection activity; an unexpected stain alone does not identify which is responsible (general IHC practice).
Chromogen covers nuclei, cytoplasm and extracellular spaces without clear cell boundaries.Widespread haze cannot establish cellular localization (general IHC practice). Although HMGB2 can be cytoplasmic or secreted (UniProt P26583), those annotations do not validate diffuse tissue background.
No stain appears in a lymph-node germinal center or bone-marrow hematopoietic cells.These are high-staining reference populations (HPA tissue IHC). First assess tissue preservation, counterstain and the positive control, then review the IHC detection workflow (general IHC practice).
💡Expected HMGB2 appearanceCall the result positive when chromogen is predominantly nuclear in the expected cells, with high signal in HPA-listed populations such as lymph-node germinal-center cells (HPA tissue IHC; UniProt P26583); membrane-dominant staining or uniform diffuse haze warrants investigation (general IHC practice).
How each factor affects the staining
Cell type within tissueHPA reports ubiquitous nuclear expression yet names specific high-staining populations, including gastrointestinal endocrine and skin basal-layer cells (HPA tissue IHC). Score identified cells, since neighboring cells need not match their intensity (general IHC practice).
Antibody evidence and specificityHPA rates the tissue profile Enhanced and lists Enhanced IHC evidence for HPA053314 and CAB037206 (HPA tissue IHC; HPA antibodies). Its warning that the target may involve more than one gene limits attribution of every positive cell solely to HMGB2 (HPA tissue IHC).
Compartment and extracellular signalBasal localization is predominantly nuclear, although cytoplasmic and secreted locations are annotated (UniProt P26583). Tissue IHC alone cannot assign diffuse extracellular chromogen specifically to secreted HMGB2 (general IHC interpretation).
IF/ICC Q: what pattern should I expect?A: Mainly nucleoplasmic staining, with additional supported nucleolar localization; principal-piece and annulus locations are approved observations (HPA subcellular ICC-IF). These are localization references, not an IHC protocol (HPA subcellular ICC-IF).
Protein form and membrane expectationUniProt lists one 1–209 chain, no signal peptide, no propeptide, no annotated isoforms and no transmembrane segment (UniProt P26583). The record therefore provides no basis to expect a membrane outline or assign a separate cleavage-product pattern.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive cells have no nuclear stain.The section or detection run may have failed; HPA reports high staining in germinal-center and bone-marrow hematopoietic cells (HPA tissue IHC).Run a known-positive tissue alongside the sample, verify the detection reagents, and review the antibody's IHC-P dilution and retrieval instructions (general IHC practice).
Most cells show similar faint brown haze.Nonspecific background can obscure the cell-restricted nuclear pattern described for HMGB2 (HPA tissue IHC; general IHC practice).Compare no-primary and reagent controls; review blocking, washes and detection exposure while retaining the known-positive tissue (general IHC practice).
Unexpected positive cells stain strongly.Salivary-gland glandular cells and skeletal-muscle myocytes are reported as not detected; cross-reactivity or endogenous detection activity is possible (HPA tissue IHC; general IHC practice).Check a no-primary control and, for enzyme detection, an endogenous-activity control; compare the same cell types in a reference section (general IHC practice).
Brown signal outlines membranes instead of nuclei.That dominant pattern disagrees with basal nuclear localization and no transmembrane segment (UniProt P26583).Inspect the positive control and background controls, then review antibody specificity and chromogen development before scoring membrane signal (general IHC practice).
Cytoplasmic or extracellular staining accompanies nuclei.Cytoplasmic and secreted HMGB2 are annotated, but HPA describes the tissue IHC profile as ubiquitously nuclear (UniProt P26583; HPA tissue IHC).Record each compartment separately and require clean controls and corroborating evidence before assigning nonnuclear signal to HMGB2 (general IHC interpretation).
Staining intensity varies across the section.HPA reports high staining in selected cell populations, so variation by cell type can be real (HPA tissue IHC). Uneven processing can also affect an IHC slide (general IHC practice).Compare the same cell type across well-preserved areas and the positive control; document regional artifacts separately from the cell-specific pattern (general IHC practice).

Sample controls for HMGB2 IHC & IF

🧪Run colon first and look for HMGB2 staining in endocrine cells (HPA: High in colon endocrine cells); use salivary gland glandular cells as the negative tissue (HPA: Not detected in salivary gland glandular cells). On the positive slide, adjacent cells without specific nuclear staining should show only background; do not assume every non-endocrine cell is HMGB2-negative (HPA: colon endocrine-cell staining; UniProt P26583: predominantly nuclear in the basal state).
Positive control tissue: Appendix (Endocrine cells, HPA High)
Negative control tissue: Salivary gland (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show HMGB2 in A-431, U-251MG, U2OS, HEL, Rh30, hTERT-RPE1 (serum starved), Sperm, NIH 3T3, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a rabbit IgG isotype control matched to the primary antibody’s clonality, and HMGB2-knockout tissue as a biological negative (caption: rabbit anti-HMGB2 PB10002; standard IHC practice). For chromogenic staining, quench endogenous peroxidase and assess endogenous biotin in colon if using the caption’s biotin-based detection system (caption: biotinylated secondary, SABC and DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported in the supplied evidence; the selected PB10002 paraffin-section caption does not state a fixative (caption: fixative unreported). Heat retrieval in EDTA at pH 8.0 was used for the mouse intestine IHC example, but retrieval dependence has not been established (caption: EDTA pH 8.0 retrieval). Frozen sections or IF cannot be judged easier from these data; HPA reports mainly nucleoplasmic ICC-IF localization, while endogenous biotin is a potential artefact to check when using biotin-based detection in intestinal tissue (HPA: nucleoplasm supported; caption: intestinal section with SABC detection; standard IHC practice).

HPA tissue IHC evidence for HMGB2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene. At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Endocrine cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Colon Endocrine cells High Protein (IHC) HPA →
Duodenum Endocrine cells High Protein (IHC) HPA →
Lymph node Germinal center cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Salivary gland Glandular cells Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Section 3

Advanced HMGB2 IHC Tips

These IHC troubleshooting answers use the PB10002 paraffin-section caption, HMGB2 annotations, and tissue staining patterns; IF is addressed separately.

What retrieval should I try when HMGB2 staining is weak in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet PB10002). The catalog antibody detected HMGB2 in a paraffin-embedded mouse intestine section after that treatment, followed by 1 μg/ml primary antibody overnight at 4°C (datasheet PB10002). If staining remains weak, compare retrieval duration on matched sections while keeping antibody concentration and chromogen development consistent (standard IHC practice). Inspect nuclear signal alongside tissue integrity, because excessive heating can damage morphology and make compartment-level interpretation unreliable (standard IHC practice; UniProt P26583 localisation). The caption does not state a fixative, so its retrieval result cannot establish performance after a particular fixation method (datasheet PB10002).
How should I troubleshoot inconsistent HMGB2 staining after fixation?
Target-specific sensitivity to any fixation method is unknown from the supplied evidence; the catalog caption identifies paraffin embedding but does not state the fixative (datasheet PB10002). Record the fixative, fixation duration, section thickness, and processing history for each specimen, then compare matched sections using the same EDTA pH 8.0 retrieval (standard IHC practice; datasheet PB10002). Use intact nuclear morphology to judge whether variable staining tracks processing quality, and include a known staining control in each run (standard IHC practice; HPA tissue IHC profile). Do not attribute a fixation effect to HMGB2 acetylation or oxidation without direct validation of the antibody under those conditions (UniProt P26583 modified residues).
Should cytoplasmic or extracellular DAB signal count as HMGB2 positivity?
Score nuclear staining as the primary pattern in routine paraffin-section IHC: HMGB2 is predominantly nuclear at baseline, and HPA reports ubiquitous nuclear expression (UniProt P26583 localisation; HPA tissue IHC profile). HPA further places the main subcellular signal in the nucleoplasm, with nucleolar signal also reported (HPA subcellular). Cytoplasmic and secreted localisation are annotated, so such staining warrants investigation rather than automatic rejection (UniProt P26583 localisation). Compare it with nuclear signal, cellular boundaries, tissue preservation, and a negative control before assigning a compartment (standard IHC practice). Diffuse DAB over several tissue structures without discernible cells is insufficient evidence for extracellular HMGB2 (standard IHC practice).
Can epitope masking or HMGB2 variants explain patchy nuclear staining?
The supplied record annotates 0 isoforms and provides no antibody epitope sequence, so a variant-specific explanation for patchiness is unsupported (UniProt P26583 isoforms; datasheet PB10002). HMGB2 has no transmembrane segment or signal peptide; its basal nuclear localisation makes preserved nuclear staining a useful reference pattern (UniProt P26583 topology and localisation). Several modified residues are annotated, including acetyllysines and phosphoserine at position 35, but their effects on this antibody's binding are unknown (UniProt P26583 modified residues). Compare matched sections with consistent EDTA pH 8.0 retrieval and check staining against intact nuclei before proposing epitope masking (datasheet PB10002; standard IHC practice).
How can IF help check an ambiguous HMGB2 IHC pattern?
Use IF as a separate localisation check, pairing HMGB2 with a marker for the expected cell population and a nuclear counterstain (standard IF practice; HPA tissue IHC profile). In intestinal tissue, an endocrine-cell marker is a relevant multiplex partner because HPA reports high HMGB2 staining in small-intestine endocrine cells (HPA tissue IHC). Choose fluorophores outside prominent tissue autofluorescence, and inspect single-channel controls before interpreting overlap (standard IF practice). Permeabilise cells to assess the predominantly nuclear antigen; HMGB2 has no transmembrane segment, so there is no membrane-side epitope assignment to preserve (standard IF practice; UniProt P26583 topology and localisation). The paraffin-section caption supplies no IF fixation or permeabilisation conditions (datasheet PB10002).
What should I check when HMGB2 DAB staining appears widespread?
First distinguish widespread nuclear staining from background: HPA describes ubiquitous nuclear expression, while the catalog image documents DAB detection in paraffin-embedded mouse intestine (HPA tissue IHC profile; datasheet PB10002). The caption used 10% goat serum blocking, a biotinylated secondary, a streptavidin-biotin detection complex, and DAB (datasheet PB10002). Run a no-primary control and examine it for diffuse chromogen, endogenous peroxidase activity, or signal associated with the biotin-based detection system (standard IHC practice). Apply a peroxidase block and adjust detection or washing if controls show background; these are general IHC steps, not demonstrated HMGB2-specific requirements (standard IHC practice).
How should I quantify HMGB2 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, then report the percentage of HMGB2-positive nuclei and an intensity-based H-score when staining varies (standard IHC practice; UniProt P26583 localisation). Normalise counts to the number of evaluable nuclei within the same annotated tissue compartment; for spatial comparisons, report positive nuclei per mm² of viable tissue (standard IHC practice). Keep thresholds, retrieval, imaging, and DAB development consistent across samples, with a control section in each staining run (standard IHC practice; datasheet PB10002 retrieval). Report cell-specific results because HPA finds high staining in some populations and no detection in others, rather than treating every field as biologically equivalent (HPA tissue IHC).
How can I distinguish true HMGB2 staining from a tissue artefact?
A credible baseline positive has interpretable nuclear DAB within intact cells; this matches HMGB2's predominant nuclear localisation and HPA's nuclear tissue profile (UniProt P26583 localisation; HPA tissue IHC profile). Check whether signal follows a plausible population: HPA reports high staining in bone-marrow hematopoietic cells, but no detection in skeletal-muscle myocytes (HPA tissue IHC). Reconsider staining restricted to section edges, necrotic regions, or areas with poor nuclear preservation, and compare those regions with a no-primary control (standard IHC practice). Endogenous enzyme signal or nonspecific detection can mimic positivity, particularly when DAB appears without a coherent cellular compartment (standard IHC practice). Cytoplasmic or extracellular staining needs separate corroboration because those localisations are annotated but are not the basal pattern (UniProt P26583 localisation).
Boster reagents

Best HMGB2 / High mobility group protein B2 IHC Antibodies

PB10002 has IHC images from paraffin sections of mouse intestine, rat spleen and human intestinal cancer (PB10002 IHC captions), plus IF images from cultured cells and rat intestine (PB10002 IF captions).

Real IHC data IHC analysis of HMGB2 using anti-HMGB2 antibody (PB10002). HMGB2 was detected in a paraffin-embedded section of mouse intestine tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1 μg/ml rabbit anti-HMGB2 Antibody (PB10002) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-HMGB2 Antibody ®
Cat # PB10002

PB10002 will render with its mouse intestine paraffin-section IHC figure (PB10002 card caption); additional IHC captions show rat spleen and human intestinal cancer (PB10002 IHC captions). Its IF captions show U20S and MCF-7 cells and a rat intestine paraffin section (PB10002 IF captions).

Which to pick: Choose PB10002 for tissue IHC: its own mouse intestine caption documents paraffin sections, EDTA retrieval at pH 8.0 and 1 μg/ml primary antibody (PB10002 IHC caption); the fixative is unreported (PB10002 IHC caption). For IF/ICC, PB10002 has cell IF images, while M02651 is a rabbit monoclonal listed for IF/ICC but has no supplied IF figure (PB10002 IF captions; M02651 catalog). For work across species, PB10002 has human, mouse and rat IHC examples and is listed as reactive with all three (PB10002 IHC captions; PB10002 catalog).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P26583 (HMGB2_HUMAN, High mobility group protein B2).
  2. Human Protein Atlas. HMGB2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. HMGB2 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the nucleoli, principal piece and annulus..
  4. Human Protein Atlas. HMGB2 antibody validation summary (4 antibodies).
  5. Identification of differentially expressed proteins and clinicopathological significance of HMGB2 in cervical cancer. Clinical proteomics 2021 — PMC7789524.
  6. High mobility group box 2 modulates the progression of osteosarcoma and is related with poor prognosis. Annals of translational medicine 2020 — PMC7576003.
  7. Pivotal role of High-Mobility Group Box 2 in ovarian folliculogenesis and fertility. Journal of ovarian research 2022 — PMC9769043.
  8. Multi-omics analysis of the HMGB2(+) tumor epithelial cells in lactylation subgroups in colorectal cancer. Cell & bioscience 2025 — PMC12632091.
  9. PubMed PMID:1754403 — UniProt-cited evidence.
  10. PubMed PMID:1551873 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.