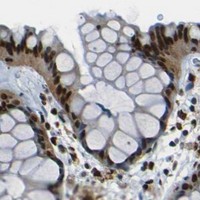
HMGN1 / Non-histone chromosomal protein HMG-14 · IHC design guide

Design Immunohistochemistry for HMGN1

Plan chromogenic HMGN1 IHC in paraffin sections using general nuclear staining as the expected pattern (HPA tissue IHC). The IHC-validated antibody A03051-2 has a recommended dilution of 1:100–1:300 (datasheet A03051-2); phosphorylation can enrich cytoplasmic HMGN1 (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for HMGN1 (IHC for HMGN1): expected localisation General nuclear staining in tissue (HPA tissue IHC), antibody A03051-2, validated IHC image, and IHC protocol steps
Printable HMGN1 IHC protocol sheet — expected localisation General nuclear staining in tissue (HPA tissue IHC), antibody A03051-2, controls and protocol steps. Open the full HMGN1 IHC guide →

HMGN1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General nuclear staining in tissue (HPA tissue IHC)
Staining pattern Nuclear staining; high in adipocytes (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A03051-2)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ Heart muscle+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Phosphorylation can enrich cytoplasmic signal (UniProt)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope No annotated isoforms; one 1–100 chain (UniProt)
Section 1

Recommended HMGN1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol uses Tris-EDTA pH 9.0 retrieval (datasheet A03051-2). Four published HMGN1 IHC protocols provide additional tissue and staining conditions (PMC9864189; PMC10476618; PMC6297552; PMC5312361).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human tonsil tissue; fixative not specified (datasheet A03051-2)
FixationImage fixative and duration unreported (datasheet A03051-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A03051-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-HMGN1, 1:100-1:300 (datasheet A03051-2)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultHMGN1-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated Tris-EDTA pH 9.0 retrieval for the catalog antibody (datasheet A03051-2); the published citrate and EDTA conditions were reported with other antibodies (PMC9864189; PMC6297552).
Section 2

What Is the Expected HMGN1 Staining Pattern?

HMGN1 is a nuclear chromatin-associated protein with no transmembrane segment (UniProt P05114: function and topology). Expect nuclear staining across many cell types, including strong staining in adipocytes, hematopoietic cells and respiratory epithelial cells (HPA: general nuclear expression; High in these cells). HPA rates the tissue IHC pattern Supported, with medium agreement between staining and RNA data; external verification is pending (HPA: tissue IHC reliability).

What am I looking at on my slide?
Crisp nuclear staining in adipocytes, hematopoietic cells or respiratory epithelium.This fits HPA's general nuclear pattern and High staining in those cells (HPA: tissue IHC). Judge intensity within the identified cell population; neighboring cells in a mixed section need not provide the same reference pattern (general IHC practice).
Predominantly cytoplasmic staining with little or no nuclear signal.Question antibody specificity or slide background when the expected nuclear pattern is absent (HPA: general nuclear expression; general IHC practice). Cytoplasmic signal alone is not conclusive: phosphorylation can enrich HMGN1 in the cytoplasm (UniProt P05114: subcellular location).
Strong staining in cardiomyocytes or skeletal myocytes.These cells are listed as Not detected, making strong staining discordant with the HPA tissue pattern (HPA: heart and skeletal muscle). Consider cross-reactivity or endogenous chromogenic activity before assigning it to HMGN1 (general IHC practice).
Diffuse color over tissue, nuclei and blank areas, without clear cell boundaries.This is background rather than a readable nuclear pattern (HPA: general nuclear expression; general IHC practice). Compare the negative reagent control, washing and blocking performance before scoring individual cells (general IHC practice).
No nuclear signal in a section containing an HPA High cell population.A missing expected internal or matched positive signal leaves that run uninterpretable (HPA: High in listed positive cells; general IHC practice). Confirm that the relevant cells are present, then check the detection workflow and a known-positive control (general IHC practice).
💡Expected HMGN1 appearanceCall a positive result when identified HPA High cells show clear nuclear chromogen above background (HPA: general nuclear expression; High in listed cells); widespread diffuse color or strong muscle-cell staining is suspect (HPA: muscle cells Not detected; general IHC practice).
How each factor affects the staining
Cellular compartmentHMGN1 binds nucleosomal DNA, consistent with the general nuclear IHC pattern (UniProt P05114: function; HPA: tissue IHC). Its supported ICC-IF location is the nucleoplasm (HPA: subcellular).
Choice of positive tissueAdipocytes, adrenal glandular cells, appendix endocrine cells, hematopoietic cells and bronchial respiratory epithelial cells are High (HPA: tissue IHC). Identify the listed cells before judging a mixed section (general IHC practice).
Negative comparatorCardiomyocytes and skeletal myocytes are Not detected in HPA tissue IHC (HPA: heart and skeletal muscle). They are useful pattern checks, but a negative cell alone cannot prove antibody specificity (general IHC practice).
Cytoplasmic exceptionUniProt reports cytoplasmic enrichment upon phosphorylation, while HPA describes general nuclear tissue staining (UniProt P05114: subcellular location; HPA: tissue IHC). Interpret a cytoplasmic result alongside nuclear signal and controls.
Molecular contextThe annotated protein is one chain spanning residues 1–100, with no signal peptide, propeptide or transmembrane segment (UniProt P05114: processing and topology). The supplied record gives no isoform or epitope-specific staining prediction (UniProt P05114: isoforms).
Evidence strengthTwo listed antibodies have Supported IHC status, HPA048694 and CAB012260 (HPA: antibodies). The tissue profile itself has medium staining–RNA agreement and awaits external verification (HPA: tissue IHC reliability); use controls for each run (general IHC practice).
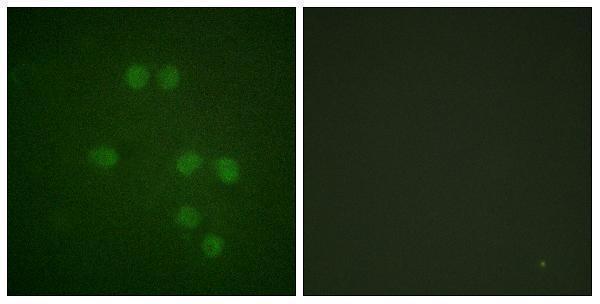
IF/ICC Q&A: Where should fluorescence appear?Predominantly in the nucleoplasm (HPA: ICC-IF subcellular location, supported). UniProt also records cytoplasmic enrichment upon phosphorylation (UniProt P05114: subcellular location). This answers location only; it does not establish an IF protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A listed High cell population is present, but its nuclei are unstained.Possible detection failure, unsuitable antibody conditions or misidentified cells (general IHC practice); HPA reports High staining only for the specified cell types (HPA: tissue IHC).Verify cell identity on the section and run a matched known-positive section; review retrieval, antibody dilution and detection against the validated IHC procedure (general IHC practice).
The whole section has weak, uneven nuclear color.Section-wide variation can arise from inconsistent processing or reagent coverage (general IHC practice); no HMGN1-specific fixation sensitivity is reported in the supplied HPA or UniProt evidence.Check section quality, reagent coverage and positive-control performance; adjust processing only through controlled comparisons (general IHC practice). Avoid attributing the pattern to HMGN1 epitope masking without evidence.
Muscle cells stain strongly alongside expected positive cells.The muscle result conflicts with HPA's Not detected calls and may reflect off-target binding or endogenous chromogenic activity (HPA: heart and skeletal muscle; general IHC practice).Review a negative reagent control and the detection-blocking step; compare another validated antibody if available (general IHC practice; HPA: two listed antibodies have Supported IHC status).
Brown signal spreads through cytoplasm while nuclei are faint.The pattern departs from HPA's general nuclear IHC profile, although phosphorylation-associated cytoplasmic enrichment is possible (HPA: tissue IHC; UniProt P05114: subcellular location).Check the negative control and nuclear counterstain, then score nuclear and cytoplasmic staining separately (general IHC practice). Do not infer phosphorylation from chromogenic localization alone.
Diffuse haze obscures nuclear boundaries.Excess background can follow insufficient washing, inadequate blocking or overly strong detection (general IHC practice); it prevents reliable comparison with HPA's nuclear pattern (HPA: tissue IHC).Compare a negative reagent control and review washes, blocking and detection conditions using the validated IHC workflow (general IHC practice). Reassess only when individual nuclei can be resolved.
Two runs give different proportions of positive cells.Differences in the cell populations sampled or run conditions can change the apparent proportion (general IHC practice). HPA calls the broad pattern Supported but reports medium staining–RNA consistency (HPA: tissue IHC reliability).Compare the same identified cell population and score compartment and intensity with matched controls (general IHC practice). Report discordance rather than treating HPA's tissue profile as an absolute threshold.

Sample controls for HMGN1 IHC & IF

🧪Run adipose tissue first and expect staining in adipocytes (HPA: High in adipocytes); use heart muscle cardiomyocytes as the negative tissue (HPA: Not detected in cardiomyocytes). No cell type within the adipose slide is established here as an internal biological negative; cells without specific staining should retain counterstained nuclei without nuclear chromogen.
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: Heart muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show HMGN1 in HEK293, U2OS, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and host- and clonality-matched isotype controls, plus HMGN1 knockout tissue or a validated immunizing-peptide block as a biological specificity control (standard IHC practice). Quench endogenous peroxidase in adipose sections and assess background around lipid vacuoles (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A03051-2 paraffin-section caption does not state a fixative (selected-SKU tissue-IHC caption: fixative unreported). The caption uses Tris-EDTA retrieval at pH 9.0 and primary antibody at 1:200 overnight at 4°C; this documents a retrieval condition, without establishing that retrieval is required (selected-SKU tissue-IHC caption). Neither frozen sections nor IF are established as easier by the supplied evidence; adipose lipid spaces can complicate interpretation of nonspecific chromogen deposits (standard IHC practice).

HPA tissue IHC evidence for HMGN1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Endocrine cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Adipocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Section 3

Advanced HMGN1 IHC Tips

Troubleshoot HMGN1 staining in paraffin sections by checking nuclear localisation, retrieval conditions, controls and cell level scoring.

What should I change if nuclear HMGN1 staining is weak after retrieval?
Use heat-mediated Tris-EDTA pH 9.0 antigen retrieval for paraffin sections (datasheet A03051-2). The selected tonsil image used this buffer, a 1:200 primary antibody dilution and an overnight incubation at 4°C (caption A03051-2). If nuclei stain weakly, check retrieval temperature and section attachment, then compare a longer retrieval interval on adjacent sections while keeping antibody dilution and detection constant (standard IHC practice). Include a tissue section with expected nuclear staining, since HMGN1 has general nuclear expression (HPA tissue IHC). If the recommended condition still fails, test an alternative buffer as a documented fallback and compare nuclear signal with tissue damage (standard IHC practice).
Could fixation explain weak or uneven HMGN1 staining?
Target-specific fixation sensitivity is unknown because the selected paraffin-section caption does not state a fixative (caption A03051-2). Record the fixative, fixation duration and section age for each specimen before attributing a staining difference to HMGN1 biology (standard IHC practice). Compare sections processed together using Tris-EDTA pH 9.0 retrieval and the same 1:200 primary dilution used in the selected image (datasheet A03051-2; caption A03051-2). Uneven fixation can change antigen accessibility within a section, so inspect tissue preservation and compare well-preserved regions under identical detection conditions (standard IHC practice). Do not infer a particular fixation effect from HPA staining patterns or HMGN1 modifications (HPA tissue IHC; UniProt P05114).
How should I assess cytoplasmic staining when HMGN1 is expected in nuclei?
Score nuclear staining first because tissue IHC shows general nuclear expression and ICC/IF supports nucleoplasmic localisation (HPA tissue IHC; HPA subcellular). UniProt also records cytoplasm and notes cytoplasmic enrichment upon phosphorylation, so cytoplasmic signal is biologically possible but needs independent support (UniProt P05114). Check whether staining follows intact cellular boundaries rather than folds, damaged edges or extracellular deposits (standard IHC practice). Compare matched sections stained with and without primary antibody, and assess the same cell populations under consistent chromogenic development (standard IHC practice). Report nuclear and cytoplasmic fractions separately instead of folding diffuse cytoplasmic colour into a nuclear HMGN1 score (standard IHC practice).
Could an isoform or modified epitope change my IHC result?
The supplied record lists 0 annotated isoforms and a single 1–100 chain, so an isoform-specific explanation lacks support here (UniProt P05114). HMGN1 has annotated phosphorylation, acetylation and ADP-ribosylation sites, which make epitope accessibility a reasonable question if the antibody epitope overlaps a modified residue (UniProt P05114). The selected caption does not identify that epitope, so do not assign a staining change to any particular modification (caption A03051-2). Compare adjacent sections using the same Tris-EDTA pH 9.0 retrieval and 1:200 primary dilution before varying one condition at a time (datasheet A03051-2; caption A03051-2; standard IHC practice). Document staining by compartment and cell type when assessing any resulting difference (standard IHC practice).
How can I check an HMGN1 IHC pattern with multiplex IF?
Use a separate IF/ICC optimisation because the selected 1:200 antibody dilution and retrieval condition come from paraffin-section IHC (caption A03051-2; datasheet A03051-2). Pair HMGN1 with a marker identifying the cell population being assessed, such as an adipocyte marker where adipocytes show high tissue staining (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores and consider a far-red channel when tissue autofluorescence obscures the HMGN1 channel (standard IF practice). HMGN1 is nucleoplasmic and has no transmembrane segment, so permeabilisation should allow antibody access to the nuclear epitope; its precise epitope is unspecified here (HPA subcellular; UniProt P05114; standard IF practice). Check single-stain and no-primary controls before interpreting colocalisation (standard IF practice).
What should I check when DAB appears throughout the section?
First compare the stained slide with a no-primary control to locate background from detection reagents or endogenous activity (standard IHC practice). Apply an endogenous peroxidase block before peroxidase-based DAB detection, and use appropriate protein blocking and washes for the tissue (standard IHC practice). The selected tonsil caption used primary antibody at 1:200 overnight at 4°C and secondary antibody at 1:200 for 45 minutes at room temperature (caption A03051-2). Treat those numbers as conditions of that image, then titrate staining on matched sections if diffuse colour persists (caption A03051-2; standard IHC practice). Judge whether clean nuclear signal remains, consistent with the reported tissue localisation (HPA tissue IHC).
How should I quantify HMGN1 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, since HMGN1 tissue staining is generally nuclear (HPA tissue IHC). For chromogenic IHC, record the percentage of positive nuclei and staining intensity, then calculate a nuclear H-score using intensity categories of 0–3 if that scale is predefined (standard IHC practice). Alternatively, report positive nuclei per mm² alongside total evaluable nuclei per mm², or normalise positive counts to the number of cells of the specified type (standard IHC practice). Keep retrieval, detection, illumination and threshold rules consistent across compared sections (standard IHC practice). Exclude folds, edges and necrotic regions using the same prespecified rule for every sample (standard IHC practice).
When is an apparent HMGN1-positive cell likely an artefact?
A convincing result is predominantly nuclear staining in intact cells, consistent with general nuclear tissue expression and supported nucleoplasmic localisation (HPA tissue IHC; HPA subcellular). High staining has been reported in bone-marrow hematopoietic cells, whereas heart cardiomyocytes were listed as not detected; use such cell-level context cautiously because HPA reliability is Supported with medium staining-to-RNA consistency (HPA tissue IHC). Diffuse colour confined to section edges, folds or necrotic areas warrants repeat assessment away from damaged tissue (standard IHC practice). A no-primary control helps reveal endogenous enzyme activity or detection background in chromogenic IHC (standard IHC practice). Cytoplasmic staining warrants separate reporting and validation because phosphorylation-associated cytoplasmic enrichment is possible (UniProt P05114).
Boster reagents

Best HMGN1 / Non-histone chromosomal protein HMG-14 IHC Antibodies

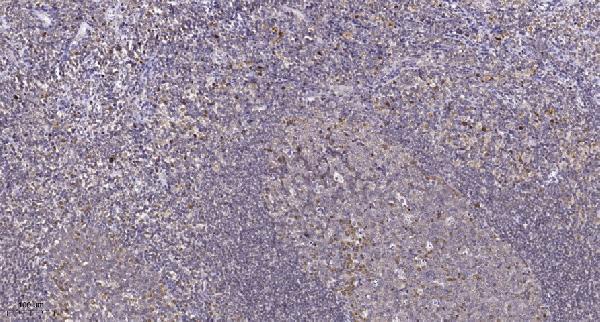
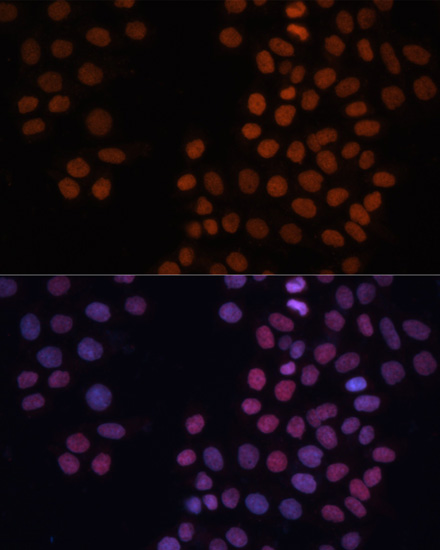
HMGN1 antibody data include paraffin-section human tonsil IHC (A03051-2 IHC image caption) and HeLa-cell IF (A03051-1 IF image caption); catalog reactivity spans human, mouse, and rat (catalog: A03051-2).

Real IHC data Immunohistochemical analysis of paraffin-embedded human tonsil. 1, Tris-EDTA, pH9.0 was used for antigen retrieval. 2 Antibody was diluted at 1:200 (4° overnight.3, Secondary antibody was diluted at 1:200 (room temperature, 45min).
Anti-HMG-14 HMGN1 Antibody
Cat # A03051-2
Real IF data Immunofluorescence analysis of HeLa cells using HMGN1 antibody at dilution of 1:100. Blue: DAPI for nuclear staining.
Anti-HMGN1 Antibody
Cat # A03051-1

A03051-2 lists IHC and IF for human, mouse, and rat, with an IHC image of paraffin-embedded human tonsil (catalog: A03051-2; A03051-2 IHC image caption). A03051-1 lists IF/ICC for human and mouse, with an IF image of HeLa cells stained with DAPI (catalog: A03051-1; A03051-1 IF image caption).

Which to pick: Choose A03051-2 for tissue IHC: its own paraffin-section human tonsil image used Tris-EDTA retrieval at pH 9.0 and primary antibody at 1:200 overnight at 4°C; the fixative is unreported (A03051-2 IHC image caption). Choose A03051-1 for IF/ICC based on its listed applications and HeLa IF image at 1:100 (catalog: A03051-1; A03051-1 IF image caption). For cross-species IHC, A03051-2 is a rabbit polyclonal antibody listed as reactive with human, mouse, and rat; its illustrated paraffin-section IHC result is from human tonsil (catalog: A03051-2; A03051-2 IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P05114 (HMGN1_HUMAN, Non-histone chromosomal protein HMG-14).
  2. Human Protein Atlas. HMGN1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. HMGN1 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. HMGN1 antibody validation summary (2 antibodies).
  5. Acteoside alleviates UUO-induced inflammation and fibrosis by regulating the HMGN1/TLR4/TREM1 signaling pathway. PeerJ 2023 — PMC9864189.
  6. PM(2.5) exposure aggravates kidney damage by facilitating the lipid metabolism disorder in diabetic mice. PeerJ 2023 — PMC10476618.
  7. PD-1/PD-L1 Axis, Rather Than High-Mobility Group Alarmins or CD8+ Tumor-Infiltrating Lymphocytes, Is Associated With Survival in Head and Neck Squamous Cell Carcinoma Patients Who Received Surgical Resection. Frontiers in oncology 2018 — PMC6297552.
  8. Endoplasmic reticulum stress induces secretion of high-mobility group proteins and is associated with tumor-infiltrating lymphocytes in triple-negative breast cancer. Oncotarget 2016 — PMC5312361.
  9. PubMed PMID:3782107 — UniProt-cited evidence.
  10. PubMed PMID:2563381 — UniProt-cited evidence.
  11. PubMed PMID:10830953 — UniProt-cited evidence.