HNRNPA1 / Heterogeneous nuclear ribonucleoprotein A1 · IHC design guide

Design Immunohistochemistry for HNRNPA1

Plan HNRNPA1 paraffin IHC around the ubiquitous nuclear tissue profile (HPA tissue IHC). Start the IHC-validated antibody at 0.5–1 μg/mL (datasheet A01476), and interpret staining with the reported cross-gene detection caution (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for HNRNPA1 (IHC for HNRNPA1): expected localisation Nuclear tissue staining (HPA tissue IHC); cytoplasmic pool possible (UniProt), antibody A01476, validated IHC image, and IHC protocol steps
Printable HNRNPA1 IHC protocol sheet — expected localisation Nuclear tissue staining (HPA tissue IHC); cytoplasmic pool possible (UniProt), antibody A01476, controls and protocol steps. Open the full HNRNPA1 IHC guide →

HNRNPA1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear tissue staining (HPA tissue IHC); cytoplasmic pool possible (UniProt)
Staining pattern Ubiquitous nuclear staining across cell types (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A01476)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A01476)
Caveat Staining may include protein from more than one gene (HPA tissue IHC)
Regulation Staining intensity regulation is unreported (UniProt)
Isoform / epitope 3 isoforms; N-terminal processing may affect N-terminal epitopes (UniProt)
Section 1

Recommended HNRNPA1 IHC & IF Protocols

The catalog antibody’s paraffin section protocol is paired with one published IHC protocol using frozen muscle sections (PMC9735363).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse intestine tissues; fixative not specified (datasheet A01476)
FixationImage fixative and duration unreported (datasheet A01476); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A01476)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01476)
Primary antibodyRabbit anti-HNRNPA1, 0.5-1μg/ml (datasheet A01476)
Primary incubationOvernight at 4 °C (datasheet A01476)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01476)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultHNRNPA1-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteFor paraffin sections, start with heat mediated citrate retrieval at pH 6 (datasheet A01476). The published frozen section excerpt does not specify retrieval (PMC9735363).
Section 2

What Is the Expected HNRNPA1 Staining Pattern?

HNRNPA1 should show widespread nuclear staining in paraffin tissue sections (HPA: ubiquitous nuclear expression; Supported tissue IHC). High staining is reported in adipocytes, glandular cells, hematopoietic cells, respiratory epithelial cells and selected brain cell populations (HPA: High in the listed cells). Its lack of a transmembrane segment supports an intracellular pattern (UniProt P09651 topology).

What am I looking at on my slide?
Nuclear staining across several cell types, including glandular or hematopoietic cells.This fits the reported widespread tissue pattern (HPA: ubiquitous nuclear expression; High in glandular and hematopoietic cells). Compare nuclei with the counterstain when scoring. HPA calls the tissue evidence Supported, while cautioning that the antibody staining may detect protein from more than one gene (HPA: reliability description).
Predominantly cytoplasmic staining with little nuclear signal.Recheck compartment assignment and background before calling this an expected tissue result: HPA reports ubiquitous nuclear IHC staining (HPA: tissue profile). Cytoplasmic localization is biologically possible because HNRNPA1 shuttles with mRNA and occurs in cytoplasmic mRNP granules (UniProt P09651 subcellular location); the supplied tissue data do not establish a cytoplasm-only IHC pattern.
Signal appears chiefly in an unexpected cell population or in acellular material.Treat the assignment as uncertain, then inspect morphology and controls for cross-reactivity or endogenous detection activity (general IHC practice). HPA reports low tissue specificity and supplies no negative cell population here, so staining outside the listed high examples cannot alone establish an off-target result (HPA: RNA specificity; tissue IHC list).
Diffuse color obscures nuclear borders or covers the section evenly.This is difficult to score as specific nuclear signal against the reported pattern (HPA: ubiquitous nuclear expression). Check a no-primary control and the detection system for nonspecific or endogenous color development; assess whether wash, blocking or reagent concentration needs adjustment (general chromogenic IHC practice).
No visible nuclear signal in a listed high-staining tissue.A technical failure is plausible if comparable cells are present: adipocytes, bone marrow hematopoietic cells and bronchial respiratory epithelial cells are among the High examples (HPA: tissue IHC). Review section quality, primary antibody use, retrieval and detection controls before interpreting a negative specimen (general IHC practice).
💡Expected HNRNPA1 appearanceCall a section positive when interpretable nuclei stain across the expected cells, with strong staining plausible in HPA High examples; isolated acellular deposits or diffuse color without nuclear contrast are suspect (HPA: ubiquitous nuclear expression; High in listed cells; general IHC interpretation).
How each factor affects the staining
Cell and tissue contextThe reference pattern is widespread nuclear staining, with High examples spanning adipocytes, glandular cells, hematopoietic cells, respiratory epithelial cells, caudate glial cells and cerebellar granular-layer cells (HPA: tissue IHC). No negative or low examples are supplied, so do not designate an unlisted tissue as a negative control.
Compartment and topologyNuclear IHC is the expected tissue readout (HPA: ubiquitous nuclear expression). HNRNPA1 has no transmembrane segment and can shuttle between nucleus and cytoplasm, including cytoplasmic mRNP granules (UniProt P09651 topology and subcellular location). A cytoplasmic signal therefore needs context and controls rather than automatic rejection.
Antibody interpretationThe tissue profile is Supported but carries a warning that staining may target protein from more than one gene (HPA: reliability description). HPA lists IHC Supported for HPA001609, HPA001666 and CAB010894 (HPA: antibody validation). Use antibody-specific validation when assigning a signal to HNRNPA1.
Isoforms and epitope coverageUniProt lists three isoforms, A1-B, A1-A and 2, plus full-length and N-terminally processed chains (UniProt P09651 isoforms and processing). Without an antibody epitope in the supplied evidence, isoform coverage and the effect of N-terminal processing on staining cannot be predicted; avoid explaining intensity differences from either alone.
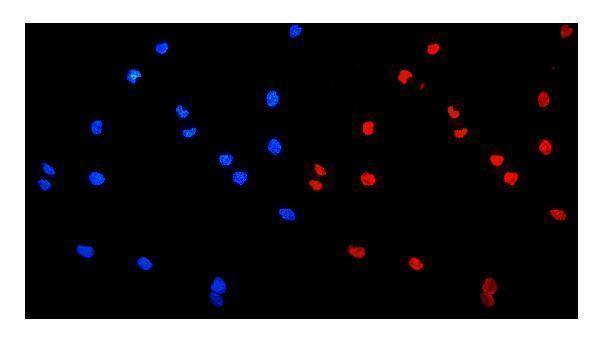
IF/ICC comparisonQ: What should a companion IF/ICC image show? A: Nucleoplasmic enrichment is the HPA reference (HPA: subcellular summary; main location, nucleoplasm enhanced). This supports compartment comparison with IHC, but the supplied IF/ICC record does not establish a paraffin-section protocol or tissue staining intensity.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
High-example tissue has no nuclear stain.The section or staining run may have failed; the missing signal alone does not establish absent HNRNPA1 (HPA: High in listed cells).Confirm the expected cells are present, then check a known-positive section, primary antibody, retrieval and detection steps (general IHC practice). Do not infer target-specific retrieval or fixation sensitivity from the supplied sources.
Only cytoplasm is strongly colored.This diverges from HPA's nuclear tissue profile, although UniProt allows cytoplasmic localization (HPA: tissue profile; UniProt P09651 subcellular location).Compare intact nuclei and a positive control; assess diffuse background and detection controls before reporting a cytoplasm-dominant finding (general IHC practice). Describe the deviation rather than assigning a mechanism.
Widespread haze hides cell boundaries.Background or overly strong detection may obscure a nuclear pattern (general chromogenic IHC practice).Inspect the no-primary control and reagent controls; review blocking, washes, antibody concentration and development time (general IHC practice). Score only nuclei distinguishable from surrounding background.
Unexpected cells or acellular structures carry the strongest color.Cross-reactivity or endogenous detection activity is possible (general IHC practice). HPA's low tissue specificity does not provide a negative-cell benchmark (HPA: RNA specificity).Check morphology, no-primary and detection controls. If needed, compare an independently validated IHC antibody; HPA lists three with Supported IHC status (HPA: antibody validation).
Two antibodies give different cell patterns.Reagent specificity may differ; HPA cautions that its tissue staining may target protein from more than one gene (HPA: reliability description).Record antibody identity and validation status, compare staining on the same tissue, and resolve disagreement with independent evidence before assigning it to HNRNPA1 (general IHC interpretation).
IF/ICC looks nucleoplasmic, but tissue IHC is weak.The assays provide different readouts: HPA reports nucleoplasmic IF/ICC localization and widespread nuclear tissue IHC (HPA: subcellular summary; tissue profile).Use the IF/ICC image to check compartment expectations only; evaluate the tissue section with its own positive and detection controls (general IHC practice). Do not use IF/ICC localization as proof of IHC sensitivity.

Sample controls for HNRNPA1 IHC & IF

🧪Run bone marrow first: hematopoietic cells should stain strongly (HPA: High in bone marrow hematopoietic cells). HPA detects HNRNPA1 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and expect enucleated erythrocytes on the positive slide to lack nuclear staining (HPA: no negative tissue; standard IHC practice).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: None in HPA: HNRNPA1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show HNRNPA1 in A-549, PC-3, U2OS, Rh30, SH-SY5Y, Hep-G2, REH, with annotated localisation: Nucleoplasm (enhanced) (HPA subcellular).
Technical controls: Run a secondary-only slide and a concentration-matched, nonimmune rabbit IgG isotype control alongside a validated HNRNPA1 knockout specimen or a validated peptide-block control (catalog caption: rabbit primary antibody; standard IHC practice). Block endogenous peroxidase and inspect erythrocytes for heme-related chromogen background in bone marrow (standard chromogenic IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence; the selected A01476 paraffin-section caption does not state its fixative (catalog caption). That caption reports heat retrieval in citrate buffer at pH 6 for 20 minutes, but does not establish whether retrieval is required (catalog caption). The evidence does not establish that frozen sections or IF are easier than IHC-P; IF/ICC offers a nucleoplasmic readout, while marrow erythrocytes warrant attention to heme-related background (HPA: nucleoplasm enhanced; standard IHC practice).

HPA tissue IHC evidence for HNRNPA1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — High consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: HNRNPA1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced HNRNPA1 IHC Tips

Troubleshoot HNRNPA1 staining in paraffin sections by checking retrieval, nuclear localisation, antibody specificity, detection background and cell-level scoring.

What retrieval conditions should I try first for weak HNRNPA1 staining?
Start with heat-mediated citrate retrieval at pH 6 for 20 minutes on paraffin sections (datasheet A01476; caption A01476). Let sections cool before washing, and keep retrieval temperature, vessel and timing consistent across the comparison batch (standard IHC practice). The illustrated workflow then used 1 µg/mL catalog antibody overnight at 4°C, so check those conditions before attributing weak staining to retrieval (caption A01476). If nuclear staining remains weak, compare a modestly adjusted heating time or an alternative retrieval buffer on adjacent sections while monitoring tissue damage and background (standard IHC practice). Judge improvement by crisp nuclear staining rather than increased diffuse color alone (HPA tissue IHC profile; standard IHC practice).
Could fixation explain weak or uneven nuclear staining?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative, and the supplied record provides no HNRNPA1 fixation comparison (caption A01476). Record each block’s fixative, fixation duration and processing history before comparing staining across specimens (standard IHC practice). For newly prepared material, keep fixation and processing consistent, then compare adjacent sections using the same citrate retrieval at pH 6 for 20 minutes (datasheet A01476; caption A01476; standard IHC practice). Uneven staining may also reflect section adhesion, incomplete dewaxing or uneven reagent coverage, so inspect these before changing antibody concentration (standard IHC practice). Nuclear enrichment provides a useful readout, but does not establish which fixation condition is optimal for HNRNPA1 (HPA tissue IHC profile; standard IHC practice).
How should I assess nuclear versus cytoplasmic HNRNPA1 staining?
Expect predominantly nuclear staining in tissue sections, consistent with the reported ubiquitous nuclear IHC profile and enhanced nucleoplasmic localisation (HPA tissue IHC; HPA subcellular). Assess nuclei against a counterstain and score cytoplasmic signal separately, rather than combining both compartments into one intensity value (standard IHC practice). HNRNPA1 also shuttles with mRNA between nucleus and cytoplasm and can occur in cytoplasmic mRNP granules, so cytoplasmic signal is biologically plausible (UniProt P09651). A strong diffuse cytoplasmic deposit without clear nuclei warrants checks of retrieval, antibody dilution, blocking and detection background (standard IHC practice). Compare the pattern with an adjacent control section and intact tissue architecture before interpreting a change in compartment distribution (standard IHC practice).
Can this stain distinguish HNRNPA1 isoforms or modified epitopes?
Do not assign an isoform from this chromogenic stain unless the antibody’s mapped epitope and isoform recognition have been established independently (standard IHC practice). The supplied record lists 3 isoforms, A1-B, A1-A and 2, plus RRM domains at residues 14–97 and 105–184 (UniProt P09651). It also lists multiple modified residues, so an epitope overlapping a modification could behave differently, but no such effect is documented for the catalog antibody here (UniProt P09651; caption A01476). Review the antibody’s immunogen or epitope documentation before making variant-specific claims, and use an independently validated isoform-specific method if that distinction drives the experiment (standard IHC practice). Report the result as HNRNPA1 immunoreactivity until that specificity is demonstrated (standard IHC practice).
How can I check the IHC localisation pattern with multiplex IF?
For an IF comparison, pair HNRNPA1 with a nuclear counterstain and a marker for the cell population being assessed; pan-cytokeratin can identify glandular epithelial cells where relevant (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores and place the weaker signal in a channel with low tissue autofluorescence, checking unstained tissue and single-stain controls (standard IF practice). HNRNPA1 has no transmembrane segment and is reported in the nucleus and cytoplasm, so permeabilisation must allow antibody access to intracellular epitopes (UniProt P09651; standard IF practice). Titrate permeabilisation to preserve nuclear structure while allowing access, and compare nuclear and cytoplasmic signals within the same identified cells (standard IF practice). Treat IF staining conditions as a separate optimisation from the paraffin-section IHC workflow (caption A01476; standard IF practice).
What should I check when DAB staining is widespread or granular?
First compare a no-primary control and inspect the distribution of DAB relative to nuclei and tissue edges (standard IHC practice). The illustrated method used 10% goat serum blocking, a biotinylated secondary antibody, a streptavidin–biotin detection complex and DAB, so check each detection step for unwanted signal (caption A01476). Quench endogenous peroxidase for a peroxidase-based workflow, and assess endogenous biotin when using biotin-dependent detection (standard IHC practice). Then titrate the catalog antibody around the illustrated 1 µg/mL condition and maintain consistent washes across sections (caption A01476; standard IHC practice). A clean nuclear pattern is the stronger reference for HNRNPA1 than generalized brown tissue coloration (HPA tissue IHC profile; standard IHC practice).
How should I quantify HNRNPA1 across heterogeneous tissue regions? ⚠ ANSWER MARKED FOR VERIFICATION
Define intact tissue regions and the cell population of interest before scoring, then apply the same rules to all sections (standard IHC practice). For nuclear HNRNPA1, report the percentage of positive nuclei and an intensity-based H-score, with the intensity scale and positivity threshold stated explicitly (HPA tissue IHC profile; standard IHC practice). If spatial distribution matters, report positive-cell density per mm² of viable tissue alongside the denominator of evaluable cells or nuclei (standard IHC practice). Analyse cytoplasmic staining separately because HNRNPA1 can shuttle and occur in cytoplasmic mRNP granules (UniProt P09651). Normalise comparisons to the same cell type, viable area, section handling and detection batch; exclude folds and necrosis by a preset rule (standard IHC practice).
How do I distinguish genuine HNRNPA1 signal from staining artefact?
A convincing result shows cell-associated nuclear staining in intact morphology, matching the reported ubiquitous nuclear IHC profile and enhanced nucleoplasmic localisation (HPA tissue IHC; HPA subcellular). Cytoplasmic staining can be plausible because HNRNPA1 shuttles and enters cytoplasmic mRNP granules, but evaluate it alongside nuclear signal and appropriate controls (UniProt P09651; standard IHC practice). Distrust staining confined to cut edges, folds, necrotic regions or a compartment inconsistent with the surrounding intact cells (standard IHC practice). Check a no-primary section for endogenous enzyme or detection-system color before calling weak DAB deposits positive (standard IHC practice). HPA labels its tissue staining supported while cautioning that its antibodies target protein from more than one gene, so that profile alone does not establish specificity for this catalog antibody (HPA tissue IHC).
Boster reagents

Best HNRNPA1 / Heterogeneous nuclear ribonucleoprotein A1 IHC Antibodies

A01476 and M01476 list IHC and IF for human, mouse, and rat; A01476 includes tissue IHC and IF images (catalog: applications and reactivity; A01476 image captions).

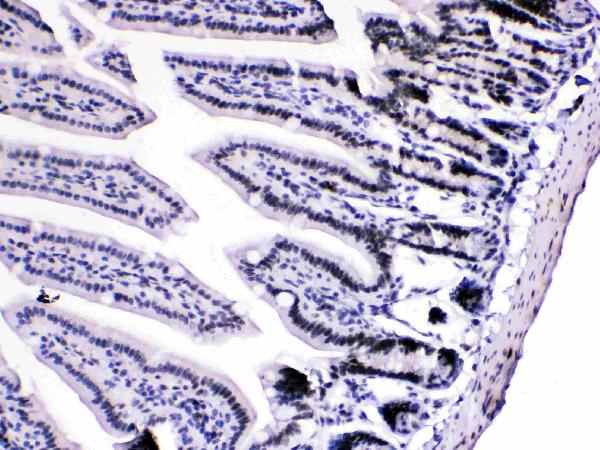
Real IHC data IHC analysis of HnRNP A1 using anti-HnRNP A1 antibody (A01476). HnRNP A1 was detected in paraffin-embedded section of mouse intestine tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-HnRNP A1 Antibody (A01476) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-HnRNP A1/HNRNPA1 Antibody ®
Cat # A01476

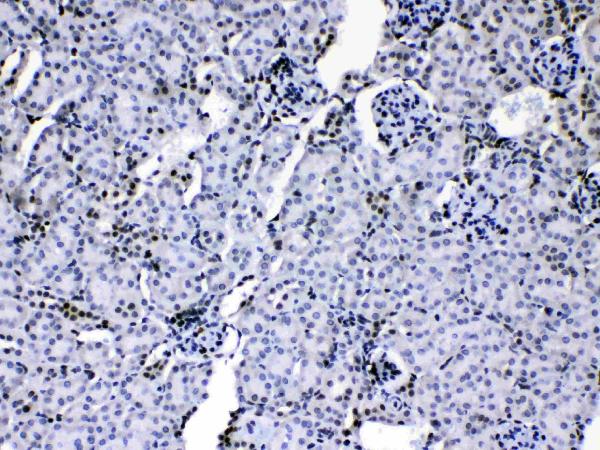
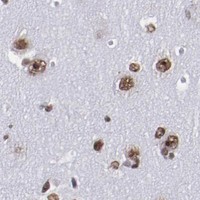
A01476 has IHC images from paraffin sections of mouse intestine and kidney, rat kidney, and human intestinal cancer, plus IF images from cells and paraffin sections (A01476 image captions). M01476 lists IHC and IF/ICC for human, mouse, and rat, but has no supplied image captions (M01476 catalog: applications, reactivity, image captions).

Which to pick: Choose A01476 for tissue IHC: its own images document paraffin sections across all three listed species; the fixative is unreported (A01476 IHC captions). For IF/ICC, A01476 has cell and tissue IF images, while M01476 is a rabbit monoclonal option with listed IF/ICC applications but no supplied images (A01476 IF captions; M01476 catalog: clone, applications, image captions). Both list human, mouse, and rat reactivity; A01476 offers cross-species tissue IHC images (catalog: reactivity; A01476 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P09651 (ROA1_HUMAN, Heterogeneous nuclear ribonucleoprotein A1).
  2. Human Protein Atlas. HNRNPA1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. HNRNPA1 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. HNRNPA1 antibody validation summary (6 antibodies).
  5. hnRNPA1-SF3B3 interaction drives radioresistance in oral squamous cell carcinoma by modulating MARF1 alternative splicing isoforms. Journal of experimental & clinical cancer research : CR 2026 — PMC13126795.
  6. iTRAQ-based proteomic analysis of the molecular mechanisms and downstream effects of fatty acid synthase in osteosarcoma cells. Journal of clinical laboratory analysis 2021 — PMC7957979.
  7. Clinical heterogeneity in a family with flail arm syndrome and review of hnRNPA1-related spectrum. Annals of clinical and translational neurology 2022 — PMC9735363.
  8. Spatial protein expression patterns across pathologically-associated fibers revealed molecular specialization in inclusion body myositis. Cell communication and signaling : CCS 2026 — PMC13032386.
  9. PubMed PMID:2760922 — UniProt-cited evidence.
  10. PubMed PMID:2836799 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.