HNRNPH1 / Heterogeneous nuclear ribonucleoprotein H · IHC design guide

Design Immunohistochemistry for HNRNPH1

Plan chromogenic paraffin-section IHC for HNRNPH1 using the widespread nuclear pattern as a reference (HPA tissue IHC). The catalog antibody has an IHC dilution of 2–5 μg/mL (datasheet A07691); assess nuclear staining with the reported multi-gene detection caveat in mind (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for HNRNPH1 (IHC for HNRNPH1): expected localisation Nuclear staining (HPA tissue IHC); nucleoplasm expected (UniProt), antibody A07691, validated IHC image, and IHC protocol steps
Printable HNRNPH1 IHC protocol sheet — expected localisation Nuclear staining (HPA tissue IHC); nucleoplasm expected (UniProt), antibody A07691, controls and protocol steps. Open the full HNRNPH1 IHC guide →

HNRNPH1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining (HPA tissue IHC); nucleoplasm expected (UniProt)
Staining pattern Nuclei across many tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A07691)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining may detect proteins from more than one gene (HPA tissue IHC)
Regulation Broad expression across tissues (HPA tissue IHC)
Isoform / epitope 0 isoforms; chains start at aa 1 or 2, affecting N-terminal epitope mapping (UniProt)
Section 1

Recommended HNRNPH1 IHC & IF Protocols

The catalog antibody uses EDTA retrieval (datasheet A07691). One published IHC protocol provides a tissue microarray workflow with citrate retrieval (PMC13039110).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A07691)
FixationImage fixative and duration unreported (datasheet A07691); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A07691); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A07691)
Primary antibodyRabbit anti-HNRNPH1, 2-5 μg/ml (datasheet A07691)
Primary incubationOvernight at 4 °C (datasheet A07691)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A07691)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultHNRNPH1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet A07691). Use pH 6.0 citrate retrieval when reproducing the published workflow (PMC13039110).
Section 2

What Is the Expected HNRNPH1 Staining Pattern?

HNRNPH1 should appear predominantly in nuclei, especially the nucleoplasm, across many cell types (UniProt P31943: nucleoplasm; HPA: ubiquitous nuclear expression). Strong staining is documented in adrenal and breast glandular cells, bone marrow hematopoietic cells, and several other listed populations (HPA: High). HPA rates its tissue IHC pattern Supported, while cautioning that the antibodies may recognize proteins from more than one gene (HPA: Supported; HPA: multi-gene caution). HNRNPH1 has no transmembrane segment (UniProt P31943: topology).

What am I looking at on my slide?
Crisp nuclear staining in glandular cells of adrenal gland, appendix, or breast, or in bone marrow hematopoietic cells.This fits the reported compartment and documented High cell populations (HPA: ubiquitous nuclear expression; HPA: High in these cells). Score the nuclear signal within the relevant cell population; apparent strength alone does not establish HNRNPH1 specificity because HPA flags possible recognition of proteins from more than one gene (HPA: multi-gene caution).
Predominantly cytoplasmic or membranous staining with little nuclear signal.The dominant compartment conflicts with nucleoplasmic localization (UniProt P31943: nucleoplasm; HPA: nucleoplasm). Treat it as a possible staining artefact or antibody specificity problem and inspect a documented High tissue alongside it (standard IHC practice; HPA: High in listed tissues).
Signal is confined to an unexpected cell population while documented High cells in the same specimen remain unstained.The mismatch warrants checking cell identification, cross-reactivity, and endogenous detection activity (standard IHC practice; HPA: multi-gene caution). An unlisted cell type is not automatically negative: HPA describes ubiquitous nuclear expression and provides no negative tissue list (HPA: tissue IHC).
Diffuse staining covers nuclei, cytoplasm, and spaces between cells.Poor compartment contrast makes the result difficult to interpret against the expected nuclear pattern (UniProt P31943: nucleoplasm; standard IHC practice). Background may arise from detection or staining conditions; use control sections to locate its source before scoring (standard IHC practice).
No nuclear signal appears in a documented High population, such as bone marrow hematopoietic cells.The expected positive result has failed for that section (HPA: High in bone marrow hematopoietic cells). Check tissue preservation, retrieval, antibody application, and detection controls as general IHC troubleshooting; the supplied sources establish no HNRNPH1-specific fixation sensitivity (standard IHC practice; HPA: tissue IHC; UniProt P31943).
💡Expected HNRNPH1 appearanceA positive IHC result is predominantly nuclear staining, potentially strong in documented High cell populations; diffuse cytoplasmic, membranous, or cell-free color should prompt a background or specificity check (HPA: ubiquitous nuclear expression; HPA: High in listed cells; UniProt P31943: nucleoplasm; standard IHC practice).
How each factor affects the staining
Tissue and cell selection (HPA: tissue IHC).HPA reports ubiquitous nuclear expression and High staining in the listed adrenal, appendix, bone marrow, breast, bronchus, caudate, cerebellum, and cerebral cortex populations (HPA: tissue IHC). These are useful expected-positive populations; the payload supplies no validated negative tissue (HPA: negative list empty).
Antibody interpretation (HPA: validation and multi-gene caution).HPA lists IHC as Supported for HPA001359, HPA016884, and CAB032820, yet cautions that its tissue profile targets proteins from more than one gene (HPA: antibody validation; HPA: multi-gene caution). A matching nuclear pattern supports interpretation but cannot by itself prove gene-specific staining (standard IHC practice).
Localization and molecular form (UniProt P31943).The annotated location is nucleoplasm, with no transmembrane segment, signal peptide, propeptide, or reported isoforms (UniProt P31943: location, topology, processing, isoforms). The record lists full-length and N-terminally processed chains; it does not establish different tissue staining patterns for them (UniProt P31943: processing).
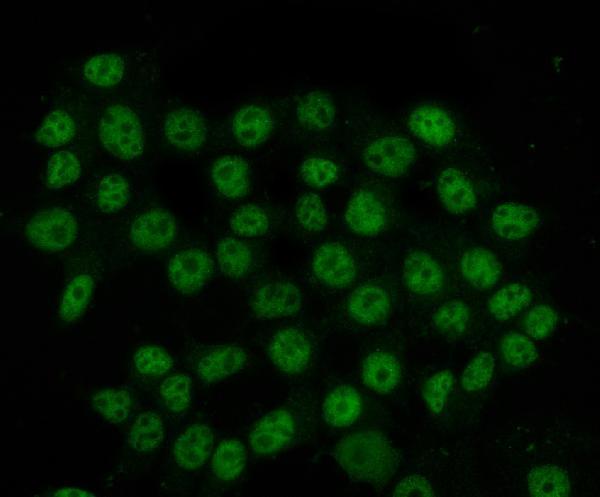
IF/ICC Q: What localization should a separate IF/ICC experiment show? (HPA: subcellular ICC-IF).A: Mainly nucleoplasmic signal (HPA: nucleoplasm, enhanced). HPA lists ICC-IF images from A-431, U-251MG, and U2OS, but cautions that the localization assessment uses antibodies targeting proteins from multiple genes (HPA: subcellular ICC-IF). This observation does not specify an IF/ICC protocol (HPA: subcellular ICC-IF).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A documented High tissue shows no nuclear stain (HPA: tissue IHC).The section, primary antibody step, or detection sequence may have failed; the sources do not identify a target-specific fixation mechanism (standard IHC practice; HPA: tissue IHC; UniProt P31943).Run a documented High population as a positive control and verify retrieval, antibody application, detection reagents, and counterstain against the laboratory's validated IHC procedure (HPA: High in listed cells; standard IHC practice).
Color is chiefly cytoplasmic or membranous (UniProt P31943: nucleoplasm).The compartment differs from the reported nuclear pattern and may reflect nonspecific binding or detection background (HPA: ubiquitous nuclear expression; standard IHC practice).Compare with the positive control and a section omitting primary antibody; interpret only reproducible nuclear signal with adequate contrast (standard IHC practice; HPA: nuclear expression).
Unexpected cells stain strongly while expected High cells do not (HPA: tissue IHC).Cell identification, cross-reactivity, or endogenous detection activity may explain the mismatch; HPA also flags potential multi-gene recognition (standard IHC practice; HPA: multi-gene caution).Confirm cell morphology and compare the pattern across documented High populations and appropriate detection controls before assigning HNRNPH1 positivity (HPA: High in listed cells; standard IHC practice).
Brown color persists in the primary-omission control (standard IHC practice).The primary antibody cannot account for that control signal; endogenous detection activity or detection-reagent background is possible (standard IHC practice).Review the detection chemistry and apply the corresponding endogenous-activity block when indicated by that chemistry; repeat the omission control (standard IHC practice).
Diffuse color obscures nuclear boundaries (standard IHC practice).Background from staining or detection conditions can prevent reliable compartment scoring (standard IHC practice).Check reagent concentration, blocking, washes, and detection development within the validated IHC procedure, then compare a positive section and omission control (standard IHC practice; HPA: High in listed cells).
Two antibodies yield different nuclear patterns (standard IHC practice).HPA reports Supported IHC validation but also warns of possible recognition of proteins from more than one gene; agreement cannot be assumed (HPA: antibody validation; HPA: multi-gene caution).Record each antibody's pattern separately and resolve the discrepancy with appropriate specificity controls before treating either pattern as HNRNPH1-specific (standard IHC practice; HPA: multi-gene caution).

Sample controls for HNRNPH1 IHC & IF

🧪Run breast first and expect glandular cells to stain (HPA: High in breast glandular cells). HPA detects HNRNPH1 in all 45 scored tissues, so use no-primary and isotype controls for negative staining; no cell type on the positive slide is established as an internal negative, although cytoplasm should show less signal than nuclei (HPA: no negative tissues; UniProt P31943: nucleoplasm).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: HNRNPH1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show HNRNPH1 in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (enhanced) (HPA subcellular).
Technical controls: Include a secondary-only slide, a concentration-matched nonimmune rabbit IgG isotype control, and HNRNPH1 knockout material or a validated peptide-block control (caption: rabbit primary antibody; standard IHC controls). Block endogenous peroxidase and check background in the breast section before interpreting DAB staining (caption: breast section with HRP/DAB detection; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A07691 paraffin-section caption leaves the fixative unreported (caption: fixative not stated). That caption supports heat retrieval in EDTA at pH 8.0 before IHC, but does not establish a requirement for that retrieval condition (caption: EDTA retrieval). Frozen sections are not shown to be easier; HPA has ICC-IF images in A-431, U-251MG and U2OS, with a caution that its nucleoplasmic localisation summary draws on antibodies targeting proteins from multiple genes (HPA: subcellular record).

HPA tissue IHC evidence for HNRNPH1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — High consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: HNRNPH1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced HNRNPH1 IHC Tips

Troubleshoot HNRNPH1 chromogenic IHC by checking nuclear staining, retrieval conditions, antibody controls and cell-level scoring (UniProt P31943; caption A07691).

Which retrieval conditions should I use for weak HNRNPH1 staining in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A07691). The selected tissue image used this retrieval before incubation with 2 µg/ml antibody overnight at 4°C, giving a documented starting combination (caption A07691). If staining remains weak, compare modest changes in heating and cooling time on matched sections while holding antibody concentration and detection constant (standard IHC practice). Include a known positive section, such as breast glandular tissue, and assess nuclear signal rather than overall DAB darkness (HPA tissue IHC; UniProt P31943 localisation). Excessive retrieval can damage morphology or increase background, so evaluate tissue preservation alongside staining intensity (standard IHC practice).
How can I assess whether fixation is limiting HNRNPH1 IHC?
The selected image shows a paraffin-embedded breast cancer section, but its fixative and fixation time are unreported (caption A07691). Target-specific sensitivity to fixation is therefore unknown from the supplied evidence; do not infer it from HNRNPH1 localisation or tissue staining (caption A07691; UniProt P31943; HPA tissue IHC). Record the fixative, duration and block history for each sample, then compare matched sections using EDTA at pH 8.0 and the same detection settings (datasheet A07691; standard IHC practice). Fixation can alter epitope access in IHC generally, so assess nuclear staining and morphology together when comparing preparations (standard IHC practice). Keep a positive control in each run to distinguish preparation effects from a failed staining run (standard IHC practice).
What staining pattern should I expect, and how should I investigate cytoplasmic signal?
Expect predominantly nucleoplasmic staining: UniProt places HNRNPH1 in the nucleus, and HPA reports enhanced nucleoplasmic localisation (UniProt P31943; HPA subcellular). HPA also describes ubiquitous nuclear tissue expression, so compare nuclei across several preserved cell populations rather than relying on one field (HPA tissue IHC). If DAB appears mainly cytoplasmic, inspect nuclear counterstain, section quality and the no-primary control before scoring it as HNRNPH1 (standard IHC practice; UniProt P31943 localisation). Repeat the documented EDTA pH 8.0 retrieval and 2 µg/ml primary concentration on a control section to check technical consistency (datasheet A07691; caption A07691). HPA cautions that its localisation evidence uses antibodies targeting proteins from multiple genes, which limits target-specific certainty (HPA subcellular).
Could processing or epitope position explain inconsistent nuclear staining?
The supplied UniProt record lists 0 isoforms and two chains beginning at residues 1 and 2, respectively (UniProt P31943 processing; UniProt P31943 isoforms). It also places RNA recognition motifs at residues 11–90, 111–188 and 289–364, with reported modified residues including phosphoserines 23, 54 and 63 (UniProt P31943 domains; UniProt P31943 modified residues). The supplied caption does not identify the antibody epitope, so those features cannot establish which processing state or modification affects staining (caption A07691). Compare matched sections under identical EDTA pH 8.0 retrieval and detection conditions before attributing differences to epitope biology (datasheet A07691; standard IHC practice). If an independently validated antibody with a documented epitope is available, concordant nuclear staining can help investigate epitope-dependent results (standard IHC practice).
How should I investigate HNRNPH1 by multiplex IF alongside this IHC guide?
For a separate IF/ICC experiment, assess nucleoplasmic signal, the localisation reported by UniProt and HPA (UniProt P31943; HPA subcellular). In breast tissue, multiplex with an epithelial marker such as pan-cytokeratin to identify glandular cells, which show high staining in HPA tissue IHC (HPA tissue IHC; standard IF practice). Choose a far-red fluorophore when shorter-wavelength tissue autofluorescence interferes, and check single-stain and unstained controls before interpreting overlap (standard IF practice). Titrate permeabilisation to give antibody access to the nuclear compartment; HNRNPH1 has no transmembrane segment, so there is no membrane-facing epitope to target (UniProt P31943 topology; standard IF practice). The selected antibody image documents chromogenic tissue IHC, so establish IF performance with its own controls (caption A07691; standard IF practice).
How can I separate true nuclear DAB staining from background?
First inspect a no-primary control for secondary reagent binding, endogenous peroxidase activity and nonspecific DAB deposition (standard IHC practice). The selected image used 10% goat serum blocking, a peroxidase-conjugated secondary incubated for 30 minutes at 37°C, and DAB development (caption A07691). Treat a peroxidase block as a general chromogenic IHC step, then compare matched sections with the same primary concentration and development time (standard IHC practice). Reduce background by checking washing, blocking and primary concentration while retaining a section processed with the documented 2 µg/ml condition (caption A07691; standard IHC practice). Score crisp nuclear signal separately from diffuse staining or pigment, since HNRNPH1 is reported mainly in the nucleoplasm (UniProt P31943; HPA subcellular).
What is a defensible way to quantify HNRNPH1 IHC across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score nuclear staining within a predefined cell population and tissue region, because HNRNPH1 is mainly nucleoplasmic and broadly expressed (UniProt P31943; HPA tissue IHC). Report the percentage of positive nuclei and, when intensity matters, an H-score calculated as the sum of percentages at intensities 1–3 multiplied by those intensities, yielding 0–300 (standard IHC practice). Normalise positive counts to all evaluable nuclei of the same cell type, or report positive nuclei per mm² with the sampled area stated (standard IHC practice). Apply one threshold, counterstain standard and DAB development setting across comparison groups, with blinded review if feasible (standard IHC practice). Exclude folds, damaged edges and necrotic regions before scoring, and record exclusions so another reader can reproduce the result (standard IHC practice).
Which findings support genuine HNRNPH1 staining rather than artefact?
Convincing staining is predominantly nuclear in preserved cells, consistent with the reported nucleoplasmic location and ubiquitous nuclear tissue profile (UniProt P31943; HPA tissue IHC). HPA lists high staining in breast glandular cells, but cautions that its tissue antibody evidence can reflect proteins from more than one gene (HPA tissue IHC). Treat strong cytoplasmic-only signal, staining confined to section edges or necrotic areas, and deposits without intact nuclei as reasons to investigate artefact (UniProt P31943 localisation; standard IHC practice). Check a no-primary control and peroxidase blocking when brown signal follows endogenous enzyme activity rather than cellular nuclei (standard IHC practice). Interpret group differences only after confirming comparable retrieval, counterstaining and DAB development, including the documented EDTA pH 8.0 condition where applicable (datasheet A07691; standard IHC practice).
Boster reagents

Best HNRNPH1 / Heterogeneous nuclear ribonucleoprotein H IHC Antibodies

Catalog antibody A07691 has IHC images from human paraffin sections and IF images from human cells, human paraffin sections, and rat brain paraffin sections (catalog image captions).

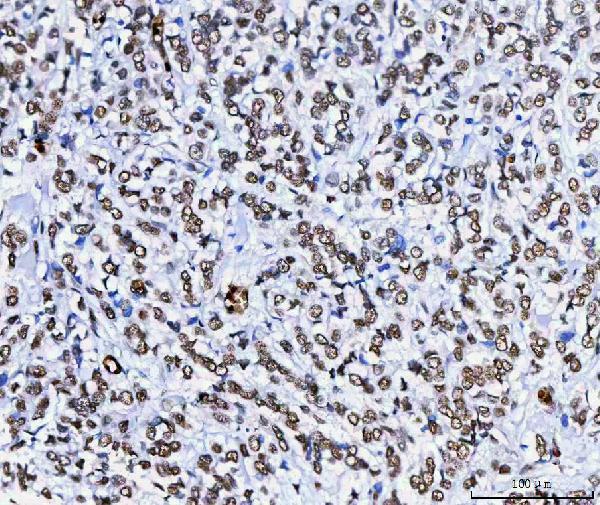
Real IHC data IHC analysis of HnRNP H/HNRNPH1 using anti-HnRNP H/HNRNPH1 antibody (A07691). HnRNP H/HNRNPH1 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-HnRNP H/HNRNPH1 Antibody (A07691) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-HnRNP H/HNRNPH1 Antibody ®
Cat # A07691

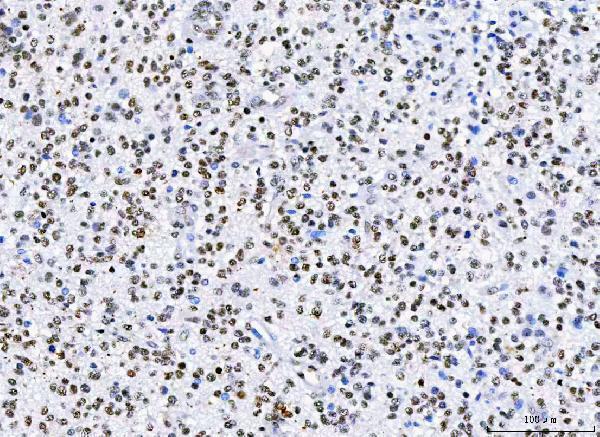
A07691 has IHC images from paraffin sections of human breast cancer, glioblastoma, ovarian serous adenocarcinoma, and colorectal adenocarcinoma (A07691 IHC captions). Its IF images cover MCF-7 cells, human breast cancer paraffin sections, and rat brain paraffin sections (A07691 IF captions).

Which to pick: Choose A07691 for tissue IHC in paraffin sections; its IHC captions document EDTA pH 8.0 retrieval and 2 μg/ml primary antibody, while the fixative is unreported (A07691 IHC captions). For IF/ICC, A07691 has MCF-7 cell IF data and a listed concentration of 5 μg/ml for immunocytochemistry/immunofluorescence (A07691 IF caption; catalog dilution). For work across species, A07691 lists human, mouse, and rat reactivity, although the supplied IHC images show human tissue; its host is rabbit and clonality is unreported (catalog reactivity and host; A07691 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P31943 (HNRH1_HUMAN, Heterogeneous nuclear ribonucleoprotein H).
  2. Human Protein Atlas. HNRNPH1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. HNRNPH1 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. Caution: Based on antibodies targeting proteins from multiple genes..
  4. Human Protein Atlas. HNRNPH1 antibody validation summary (4 antibodies).
  5. Predicting lymphoma prognosis using machine learning-based genes associated with lactylation. Translational oncology 2024 — PMC11375145.
  6. HNRNPH1 drives glioblastoma progression by regulating the splicing of cell cycle genes. Cell death & disease 2026 — PMC13039110.
  7. Dysregulation of miR-212 Promotes Castration Resistance through hnRNPH1-Mediated Regulation of AR and AR-V7: Implications for Racial Disparity of Prostate Cancer. Clinical cancer research : an official journal of the American Association for Cancer Research 2016 — PMC7472565.
  8. SRSF3 and HNRNPH1 Regulate Radiation-Induced Alternative Splicing of Protein Arginine Methyltransferase 5 in Hepatocellular Carcinoma. International journal of molecular sciences 2022 — PMC9738276.
  9. PubMed PMID:7499401 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.