HPGD / 15-hydroxyprostaglandin dehydrogenase [NAD(+)] · IHC design guide

Design Immunohistochemistry for HPGD

Plan chromogenic IHC for HPGD in paraffin sections using its observed cytoplasmic tissue pattern (HPA tissue IHC; datasheet A02686-3). Compare staining with cell-specific HPA results when choosing controls and interpreting signal (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
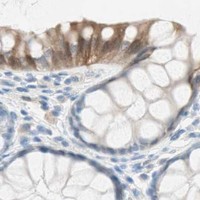
Immunohistochemistry protocol sheet for HPGD (IHC for HPGD): expected localisation Cytoplasmic staining in several cell types (HPA tissue IHC), antibody A02686-3, validated IHC image, and IHC protocol steps
Printable HPGD IHC protocol sheet — expected localisation Cytoplasmic staining in several cell types (HPA tissue IHC), antibody A02686-3, controls and protocol steps. Open the full HPGD IHC guide →

HPGD Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in several cell types (HPA tissue IHC)
Staining pattern Cytoplasmic signal in urothelium and GI surface epithelium (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02686-3)
Positive control ⓘ Duodenum+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A02686-3)
Caveat Signal varies by cell type and tissue (HPA tissue IHC)
Regulation HPGD expression regulation is not specified (UniProt)
Isoform / epitope Five isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended HPGD IHC & IF Protocols

The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet A02686-3). The published options cover human synovium (PMC4526038) and breast tissues (PMC5410267).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A02686-3)
FixationImage fixative and duration unreported (datasheet A02686-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02686-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02686-3)
Primary antibodyRabbit anti-HPGD, 2-5 μg/ml (datasheet A02686-3)
Primary incubationOvernight at 4 °C (datasheet A02686-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A02686-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultHPGD-positive staining in paneth cells of duodenum (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several different cell types, including urothelial cells and surface epithelium of the gastrointestinal tract. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 for the catalog antibody (datasheet A02686-3); consider citrate retrieval when adapting the synovium protocol (PMC4526038).
Section 2

What Is the Expected HPGD Staining Pattern?

HPGD is cytoplasmic and has no transmembrane segment (UniProt P15428: subcellular location and topology). In tissue sections, expect cell-specific cytoplasmic staining, including urothelial cells and gastrointestinal surface epithelium (HPA: tissue IHC profile). HPA rates the tissue pattern Enhanced, with medium consistency between staining and RNA data (HPA: tissue IHC reliability). Interpret the stained cell type alongside its compartment.

What am I looking at on my slide?
Cytoplasmic staining in stomach glandular cells, bladder urothelial cells, or intestinal Paneth cells.This fits reported high HPGD staining in those cells (HPA: tissue IHC). Compare cells within the same section; a high designation does not prescribe a numerical intensity cutoff.
Predominantly nuclear or membranous staining in an IHC section.Reassess localisation and controls: HPGD is cytoplasmic with no transmembrane segment (UniProt P15428). Nucleoplasmic signal is additionally reported in ICC-IF (HPA: subcellular), so nuclear signal alone does not prove an artefact.
Strong staining in a cell type reported as not detected, such as adipocytes or esophageal squamous epithelium.Consider cross-reactivity or endogenous chromogenic activity (HPA: tissue IHC; general IHC practice). Check the stained cell identity and detection controls before assigning the signal to HPGD.
Diffuse color across cells and surrounding tissue, with little cell-specific contrast.This obscures the cytoplasmic pattern reported for HPGD (HPA: tissue IHC). General IHC practice points to nonspecific binding or detection background; inspect a no-primary control and review blocking and washes.
No staining in a selected high-staining tissue and cell type.This conflicts with the reported pattern, but a single negative section does not establish absent HPGD (HPA: tissue IHC). Verify that the expected cells are present, then review the staining run and antibody conditions.
💡Expected HPGD appearanceCall positive when identifiable urothelial, stomach glandular, or intestinal Paneth cells show clear cytoplasmic staining consistent with their reported high levels (HPA: tissue IHC); widespread uniform color or dominant membrane staining warrants a specificity check (UniProt P15428: topology; general IHC practice).
How each factor affects the staining
Compartment and topologyHPGD is cytoplasmic, with no transmembrane segment or signal peptide (UniProt P15428). Read IHC signal against cell boundaries and the counterstain; membrane-dominant staining is discordant with that annotation.
Cell-specific tissue distributionHigh staining is reported in duodenal and small-intestinal Paneth cells, lung endothelial cells, stomach glandular cells, and bladder urothelial cells (HPA: tissue IHC). Select controls by both tissue and cell type.
Low and undetected comparatorsBronchial respiratory epithelium and liver cholangiocytes are listed as low; adipocytes and esophageal squamous epithelial cells are not detected (HPA: tissue IHC). Low cells may offer limited contrast, and an undetected entry is not a universal biological absence claim.
Evidence and antibody validationThe tissue profile is rated Enhanced but has medium staining–RNA consistency (HPA: tissue IHC reliability). HPA004919 and HPA005679 each have Enhanced IHC validation (HPA: antibodies); these summaries support pattern checking, not a guarantee for every section.
Isoforms and epitope scopeUniProt lists five HPGD isoforms (UniProt P15428: isoforms). The supplied record gives no antibody epitope or isoform coverage, so isoform-specific staining cannot be inferred from a positive or negative IHC result.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive cells are blank.The selected section may lack the relevant cells, or the staining run may have failed (HPA: tissue IHC; general IHC practice).Confirm cell identity on the counterstain; run a high-staining tissue alongside the sample, then review the antibody dilution, retrieval, and detection steps (HPA: tissue IHC; general IHC practice).
Color is diffuse across the section.Nonspecific binding or detection background can mask cell-specific signal (general IHC practice).Compare a no-primary control, check blocking and wash conditions, and score only signal that remains distinguishable within cells (general IHC practice).
Signal appears mainly on membranes or only in nuclei.Membrane dominance conflicts with HPGD topology (UniProt P15428). Nuclear staining requires context because ICC-IF also reports nucleoplasmic localisation (HPA: subcellular).Inspect cytoplasmic signal in a high-staining cell type and compare detection controls before calling the IHC pattern positive (HPA: tissue IHC; general IHC practice).
An unexpected cell type stains strongly.Cell misidentification, cross-reactivity, or endogenous chromogenic activity may explain the result (general IHC practice).Confirm morphology and compare the no-primary control; interpret the result against the named cells in the HPA tissue profile, rather than tissue name alone (HPA: tissue IHC; general IHC practice).
A presumed negative control stains.The control may contain another HPGD-positive cell type, or the signal may reflect detection background (HPA: tissue IHC; general IHC practice).Check the exact cell population: HPA reports adipocytes and esophageal squamous epithelial cells as not detected (HPA: tissue IHC). Use a no-primary control to assess detection background (general IHC practice).
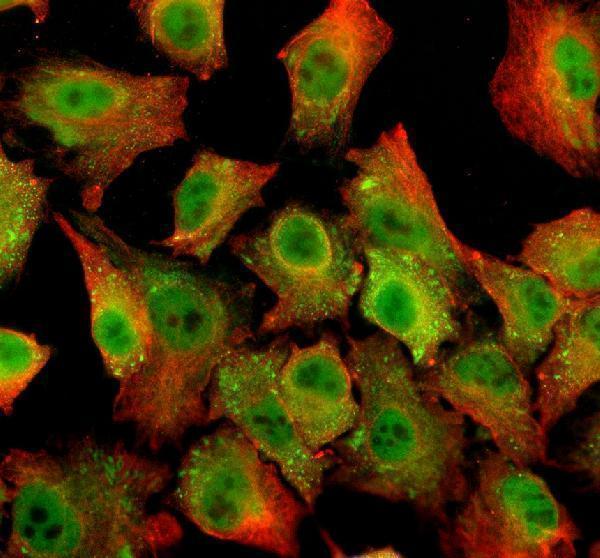
What should IF/ICC show?HPA reports supported cytosolic and additional approved nucleoplasmic localisation in ICC-IF (HPA: subcellular).Use those locations to interpret an IF image, while keeping the tissue IHC pattern and its cell-specific controls as the basis for this paraffin-section guide (HPA: subcellular; HPA: tissue IHC).

Sample controls for HPGD IHC & IF

🧪Run duodenum first and require staining in Paneth cells (HPA: duodenum Paneth cells High); use adipose tissue adipocytes as the biological negative tissue (HPA: adipocytes Not detected). On the duodenum slide, adjacent cells without specific cytoplasmic staining provide an internal background reference; interpret them against the Paneth-cell signal rather than assuming every neighboring cell is negative (HPA: duodenum Paneth cells High; UniProt P15428: cytoplasm).
Positive control tissue: Duodenum (Paneth cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show HPGD in RT-4, U-251MG, U2OS, NIH 3T3, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control for the rabbit catalog antibody, plus HPGD-knockout material if available (selected SKU A02686-3 caption: rabbit anti-HPGD). For chromogenic duodenum IHC, block endogenous peroxidase and inspect background before scoring DAB staining (selected SKU A02686-3 caption: peroxidase secondary and DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact selected-SKU paraffin-section caption does not state a fixative (selected SKU A02686-3 caption). The caption uses heat retrieval in EDTA at pH 8.0, but it does not establish that retrieval is required; neither frozen sections nor IF/ICC is established as easier by the supplied evidence (selected SKU A02686-3 caption; HPA: ICC-IF images in RT-4, U-251MG, U2OS and NIH 3T3). In duodenum, account for background from endogenous peroxidase when assessing Paneth-cell DAB signal (HPA: duodenum Paneth cells High; standard IHC practice).

HPA tissue IHC evidence for HPGD

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Duodenum Paneth cells High Protein (IHC) HPA →
Lung Endothelial cells High Protein (IHC) HPA →
Small intestine Paneth cells High Protein (IHC) HPA →
Stomach Glandular cells High Protein (IHC) HPA →
Urinary bladder Urothelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Cerebral cortex Endothelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced HPGD IHC Tips

Troubleshoot HPGD staining in paraffin sections by checking retrieval, cytoplasmic localisation, cell identity and matched controls before interpreting signal strength.

What retrieval should I try first when HPGD staining is weak?
Start with heat-mediated antigen retrieval in EDTA pH 8.0 for the catalog antibody (datasheet A02686-3). The product image used a paraffin section of human breast cancer tissue, but its caption does not report the fixative (datasheet A02686-3). If staining remains weak, compare retrieval duration on adjacent sections while keeping antibody concentration and detection constant; excessive heating can damage tissue morphology (standard IHC practice). Include a known positive cell population, such as stomach glandular cells, so a weak experimental section can be distinguished from a failed staining run (HPA: High in stomach glandular cells; standard IHC practice).
Can fixation explain variable HPGD staining between paraffin blocks?
It can affect epitope accessibility, but target-specific fixation sensitivity for HPGD is unknown from the supplied evidence (standard IHC practice; datasheet A02686-3: fixative unreported). The catalog image establishes staining in a paraffin section, with EDTA pH 8.0 retrieval; it does not establish which fixative preserves this epitope best (datasheet A02686-3). Record each block’s documented fixative and processing history, then compare adjacent sections using one retrieval and staining run (standard IHC practice). If signal differs, assess morphology and a reference cell population before assigning the difference to HPGD expression or to fixation (standard IHC practice; HPA: High in stomach glandular cells).
Where should convincing HPGD staining appear within positive cells?
Expect predominantly cytoplasmic signal: UniProt places HPGD in the cytoplasm, and HPA describes cytoplasmic tissue staining and a mainly cytosolic subcellular pattern (UniProt P15428: subcellular location; HPA: tissue profile and subcellular summary). A smaller nuclear component may warrant investigation because HPA also reports nucleoplasmic localisation in its cell imaging data (HPA: additional nucleoplasm location). HPGD has no annotated transmembrane segment, so a crisp membrane-only outline should prompt a specificity check (UniProt P15428: topology). Compare the signal with cell morphology and a positive tissue reference; avoid counting diffuse section haze as intracellular staining (standard IHC practice; HPA: High in stomach glandular cells).
Could isoforms or epitope accessibility account for discordant HPGD staining?
HPGD has 5 annotated isoforms, so the detected isoforms cannot be inferred without an epitope map for the catalog antibody (UniProt P15428: isoforms 1–5). The supplied record describes no signal peptide, propeptide, annotated glycosylation sites or modified residues; those annotations do not establish which epitopes survive section processing (UniProt P15428: processing and modifications). If staining conflicts with an independent assay, request the immunogen or epitope information and check whether it is shared by the relevant isoforms (standard IHC practice; UniProt P15428: isoforms 1–5). Test any proposed explanation with matched sections and an orthogonal control before attributing a staining difference to splicing (standard IHC practice).
How should I evaluate HPGD localisation by multiplex IF?
On the separate IF/ICC guide, pair HPGD with a marker identifying the expected cell type, such as a validated urothelial marker when examining bladder epithelium (HPA: High in urinary bladder urothelial cells; standard IF practice). Choose fluorophores after inspecting unstained tissue for autofluorescence, and include single-label controls to assess spectral bleed-through (standard IF practice). HPGD is mainly cytosolic and has no annotated transmembrane segment; use permeabilisation appropriate for an intracellular epitope, while checking that cell boundaries remain interpretable (HPA: supported cytosol location; UniProt P15428: topology; standard IF practice). Compare nuclear signal cautiously with the reported additional nucleoplasmic localisation and verify it against background controls (HPA: approved nucleoplasm location; standard IF practice).
What controls help distinguish HPGD signal from chromogenic background?
Inspect a no-primary section for signal from secondary reagents or endogenous enzyme activity, and apply a peroxidase block before HRP and DAB detection (standard IHC practice). The catalog image used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and an HRP/DAB workflow; these are conditions for that image, not universal tissue settings (datasheet A02686-3). If background persists, compare a lower primary concentration and shorter development while retaining a positive reference on the same run (standard IHC practice). Treat uniform staining across negative cell populations as suspect, particularly when intracellular detail disappears (HPA: adipocytes Not detected in breast; standard IHC practice).
How can I quantify HPGD without confusing cell composition with expression? ⚠ ANSWER MARKED FOR VERIFICATION
Score cytoplasmic HPGD in a defined cell population using the percentage of positive cells and an intensity-based H-score; record the scoring thresholds before reviewing groups (HPA: cytoplasmic tissue profile; standard IHC practice). Normalise counts to the number of eligible cells, or report positive-cell density per mm² of viable tissue when cell abundance itself matters (standard IHC practice). Exclude folds, necrosis and poorly preserved edges consistently, and analyse sections stained in the same run where feasible (standard IHC practice). Report compartment and cell identity because HPA shows high signal in selected epithelial and other cell populations rather than uniform tissue-wide expression (HPA: tissue IHC profile and positive-cell list).
How do I recognise a true HPGD-positive result rather than an artefact?
A credible result shows intracellular staining in identifiable cells, preferably with a mainly cytoplasmic pattern and a reference population expected to express HPGD (UniProt P15428: cytoplasm; HPA: High in stomach glandular cells). Question a membrane-only outline, broad acellular deposit, or signal confined to torn edges or necrotic areas (UniProt P15428: no transmembrane segment; standard IHC practice). Check a no-primary control for endogenous peroxidase or detection background, particularly when DAB colour is widespread (standard IHC practice; datasheet A02686-3: HRP/DAB detection). Interpret negative cells by identity: HPA reports breast adipocytes as not detected, whereas its atlas reports high staining in several distinct cell types (HPA: breast adipocytes Not detected; HPA: positive-cell list).
Boster reagents

Best HPGD / 15-hydroxyprostaglandin dehydrogenase [NAD(+)] IHC Antibodies

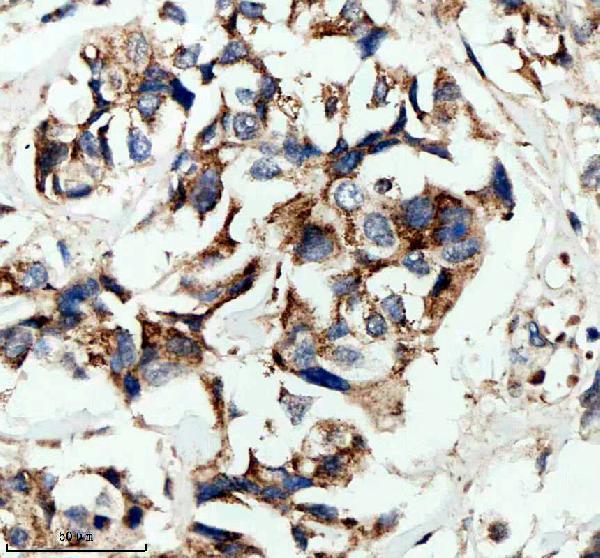
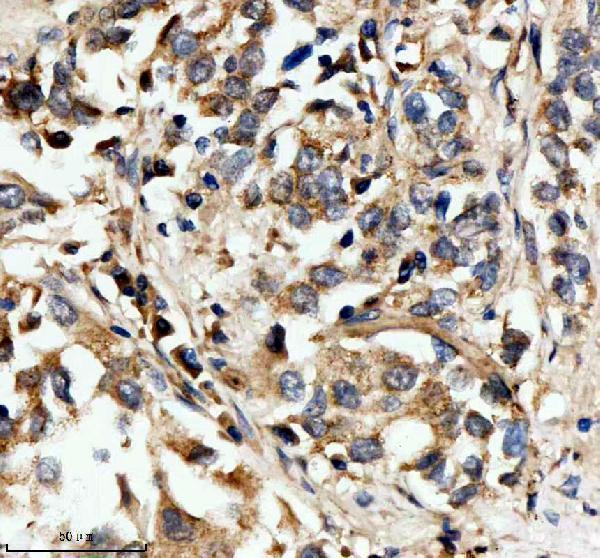
A02686-3 has IHC images from human breast and lung cancer sections and mouse and rat kidney sections, plus IF images from A549 cells and a human breast cancer section (A02686-3 image captions).

Real IHC data IHC analysis of HPGD using anti-HPGD antibody (A02686-3). HPGD was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-HPGD Antibody (A02686-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-HPGD Antibody ®
Cat # A02686-3

A02686-3 is the figure-backed card: its IHC captions document paraffin-embedded human breast and lung cancer sections and mouse and rat kidney sections; its IF captions document A549 cells and a paraffin-embedded human breast cancer section (A02686-3 image captions). M02686 lists human IHC and IF/ICC applications, but has no IHC or IF image caption in the supplied catalog and therefore no qualifying card figure (M02686 catalog).

Which to pick: Choose A02686-3 for tissue IHC: its captions document paraffin-embedded sections with EDTA pH 8.0 retrieval and 2 μg/ml primary antibody; the fixative is unreported (A02686-3 IHC image captions). Choose A02686-3 for image-supported IF/ICC; M02686 is a rabbit monoclonal with human IF/ICC listed, but no supplied IF image caption (A02686-3 IF image captions; M02686 catalog). For cross-species work, A02686-3 lists human, mouse and rat reactivity and has IHC images for all three (A02686-3 catalog and IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P15428 (PGDH_HUMAN, 15-hydroxyprostaglandin dehydrogenase [NAD(+)]).
  2. Human Protein Atlas. HPGD tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. HPGD subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to the nucleoplasm..
  4. Human Protein Atlas. HPGD antibody validation summary (2 antibodies).
  5. 15-hydroxyprostaglandin dehydrogenase is upregulated by hydroxychloroquine in rheumatoid arthritis fibroblast-like synoviocytes. Molecular medicine reports 2015 — PMC4526038.
  6. Association of 15-hydroxyprostaglandin dehydrogenate and poor prognosis of obese breast cancer patients. Oncotarget 2017 — PMC5410267.
  7. Downregulation of 15-hydroxyprostaglandin dehydrogenase during acquired tamoxifen resistance and association with poor prognosis in ERα-positive breast cancer. Exploration of targeted anti-tumor therapy 2020 — PMC7116369.
  8. Down-regulation of HPGD by miR-146b-3p promotes cervical cancer cell proliferation, migration and anchorage-independent growth through activation of STAT3 and AKT pathways. Cell death & disease 2018 — PMC6192999.
  9. PubMed PMID:2337593 — UniProt-cited evidence.
  10. PubMed PMID:1697582 — UniProt-cited evidence.
  11. PubMed PMID:7557451 — UniProt-cited evidence.