HPN / Serine protease hepsin · IHC design guide

Design Immunohistochemistry for HPN

Plan HPN staining in paraffin sections using colon glandular cells as a high-staining reference (HPA tissue IHC). Interpret the observed cytoplasmic pattern alongside the expected apical membrane location and the reported low consistency between staining and RNA expression (HPA tissue IHC; UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for HPN (IHC for HPN): expected localisation General cytoplasmic staining (HPA tissue IHC); apical membrane expected (UniProt), antibody A02350-1, validated IHC image, and IHC protocol steps
Printable HPN IHC protocol sheet — expected localisation General cytoplasmic staining (HPA tissue IHC); apical membrane expected (UniProt), antibody A02350-1, controls and protocol steps. Open the full HPN IHC guide →

HPN Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic staining (HPA tissue IHC); apical membrane expected (UniProt)
Staining pattern Glandular cells show cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02350-1)
Positive control ⓘ Colon+4 more · see all
Negative control ⓘ Salivary gland
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Antibody staining has low consistency with RNA expression (HPA tissue IHC)
Regulation Staining intensity varies by tissue (HPA tissue IHC)
Isoform / epitope No isoforms annotated; two chains; map cytoplasmic vs extracellular epitopes (UniProt)
Section 1

Recommended HPN IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: A02350-1) is accompanied by a published ovarian-tissue IHC protocol (PMC2409606).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon tissue; fixative not specified (datasheet A02350-1)
FixationImage fixative and duration unreported (datasheet A02350-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02350-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02350-1)
Primary antibodyRabbit anti-HPN, 2-5 μg/ml (datasheet A02350-1)
Primary incubationOvernight at 4 °C (datasheet A02350-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A02350-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
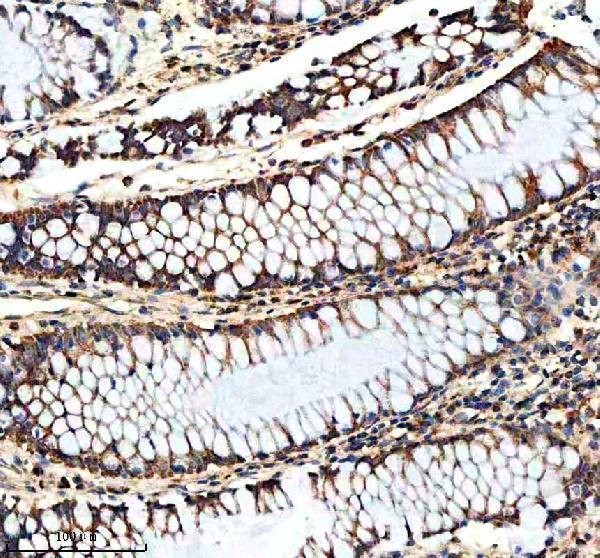
Expected resultHPN-positive staining in glandular cells of colon (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: A02350-1). The published ovarian protocol uses microwave Tris-EDTA for 25 min (PMC2409606).
Section 2

What Is the Expected HPN Staining Pattern?

HPN is a membrane-anchored protease with an extracellular region and an apical cell-membrane annotation (UniProt P05981 topology and subcellular location). In tissue IHC, expect staining in the cell populations reported as high by HPA, including colon glandular cells and pancreatic exocrine glandular cells (HPA tissue IHC). Interpret the compartment cautiously: HPA describes general cytoplasmic expression, and its IHC reliability is Approved with low consistency between staining and RNA data (HPA tissue IHC).

What am I looking at on my slide?
Clear staining in colon or rectum glandular cells, or pancreatic exocrine glandular cells.These are reported high-staining populations (HPA tissue IHC). Assess whether signal follows the relevant cells and remains distinct from surrounding tissue; high staining alone does not establish antibody specificity (general IHC practice).
Membrane-associated signal, with or without some cytoplasmic staining, in a reported positive cell population.Membrane signal fits the apical membrane annotation and transmembrane topology (UniProt P05981). Cytoplasmic staining also appears in HPA’s tissue profile, so its presence alone cannot disqualify a result (HPA tissue IHC).
Predominantly nuclear staining, without convincing signal in the expected cells.Nuclear localisation conflicts with UniProt’s membrane annotation and HPA’s general cytoplasmic profile (UniProt P05981; HPA tissue IHC). Treat this as suspect and check the control slide, detection system and antibody specificity (general IHC practice).
Strong staining in salivary gland glandular cells or in cells outside the reported positive population.Salivary gland glandular cells are reported as not detected (HPA tissue IHC). Unexpected staining raises possible cross-reactivity or endogenous detection activity; compare a no-primary control before assigning HPN expression (general IHC practice).
Uniform haze across cells, stroma and blank areas, or no signal in a reported high-staining tissue.Haze that ignores tissue boundaries suggests background rather than a cell-specific pattern (general IHC practice). An unstained reported positive tissue is inconclusive until section quality, detection and antibody conditions are checked (HPA tissue IHC; general IHC practice).
💡Expected HPN appearanceCall a section positive when a reported high-staining cell population shows clear cell-associated signal, with membrane-associated and potentially cytoplasmic staining; widespread haze or strong salivary gland glandular-cell staining needs investigation (UniProt P05981; HPA tissue IHC; general IHC practice).
How each factor affects the staining
Compartment and topology (UniProt P05981).HPN spans the membrane at residues 24–44; residues 45–417 are extracellular (UniProt P05981 topology). The antibody epitope is unspecified, so topology cannot predict this antibody’s exact IHC outline or retrieval response.
Observed tissue profile and validation (HPA tissue IHC; HPA antibodies).HPA reports high staining in several glandular populations and not-detected staining in salivary gland glandular cells (HPA tissue IHC). Its listed antibody, HPA006804, is IHC Approved, while tissue staining has low consistency with RNA data (HPA antibodies; HPA tissue IHC).
Protein processing and glycosylation (UniProt P05981).UniProt lists non-catalytic residues 1–162, catalytic residues 163–417 and a glycosylation site at 112 (UniProt P05981). Without an epitope map, these annotations do not identify which form this antibody detects in sections.
IF/ICC Q&A: should the same compartment be expected?Membrane localisation is supported by UniProt and HPA’s subcellular summary (UniProt P05981; HPA subcellular). HPA supplies no ICC/IF image cell lines or main-location assignment, and its listed antibody has no ICC status; establish IF/ICC performance separately (HPA subcellular; HPA antibodies).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in colon glandular cells or pancreatic exocrine glandular cells (HPA tissue IHC).Section, primary-antibody or detection failure is possible; HPA’s high staining is a reference pattern, not a guarantee for every specimen (HPA tissue IHC; general IHC practice).Check tissue preservation and a working detection control, then review the IHC-validated antibody’s stated conditions and optimise retrieval or dilution as general IHC practice.
Strong, widespread brown signal including areas without the expected cells.Nonspecific background or endogenous chromogenic activity can obscure cell-associated staining (general IHC practice).Run a no-primary control; review blocking, washes and endogenous-enzyme blocking appropriate to the detection chemistry (general IHC practice).
Predominantly nuclear staining in a putative positive section.The distribution conflicts with the membrane annotation and HPA’s cytoplasmic tissue profile (UniProt P05981; HPA tissue IHC).Compare with a reported positive tissue and a no-primary control; review antibody dilution and detection background before interpreting nuclear signal as HPN (HPA tissue IHC; general IHC practice).
Salivary gland glandular cells stain strongly.HPA reports this population as not detected; cross-reactivity or endogenous detection activity is possible (HPA tissue IHC; general IHC practice).Repeat alongside a reported high-staining tissue and a no-primary control; assess whether signal follows cells rather than deposits or diffuse background (HPA tissue IHC; general IHC practice).
Cytoplasmic signal is present, but apical membrane signal is weak or absent.HPA reports general cytoplasmic expression despite UniProt’s apical membrane annotation; the evidence does not specify this antibody’s epitope or a target-specific fixation effect (HPA tissue IHC; UniProt P05981).Record the observed compartment and compare it with a reported positive tissue; optimise standard IHC conditions without assuming membrane-only staining is required (HPA tissue IHC; general IHC practice).
Staining appears in a tissue with low or uncertain expected signal.HPA’s tissue entries vary by cell population, and its Approved profile has low staining-to-RNA consistency (HPA tissue IHC). Tissue-level RNA enrichment does not itself verify staining in a particular cell population (HPA tissue IHC).Identify the stained cell type, compare a high-staining reference tissue and the no-primary control, and report any departure from the HPA pattern as unresolved until independently supported (HPA tissue IHC; general IHC practice).

Sample controls for HPN IHC & IF

🧪Run colon first: glandular cells should stain (HPA: High in colon glandular cells; selected-SKU IHC caption: colon staining). Run salivary gland as the negative tissue (HPA: Not detected in salivary gland glandular cells); compare adjacent nonglandular cells on the colon slide for background staining, without assuming they are HPN-negative.
Positive control tissue: Colon (Glandular cells, HPA High)
Negative control tissue: Salivary gland (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for HPN; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include no-primary (secondary-only), a concentration-matched rabbit isotype control for the rabbit catalog antibody, and HPN-knockout tissue or a peptide-block control if a suitable immunizing peptide is available (selected-SKU IHC caption: rabbit primary antibody; standard IHC controls). Quench endogenous peroxidase before HRP/DAB detection on colon sections (selected-SKU IHC caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence; the selected-SKU paraffin-section caption does not state a fixative (selected-SKU IHC caption: fixative unreported). The documented colon IHC procedure used heat-mediated retrieval in EDTA at pH 8.0, but the evidence does not establish that retrieval is required for every HPN antibody (selected-SKU IHC caption: EDTA retrieval). There is no matched frozen-section or IF protocol here to establish that either is easier; check colon autofluorescence if adapting the assay to IF (supplied evidence: IHC caption only; standard IF practice).

HPA tissue IHC evidence for HPN

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Colon Glandular cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Heart muscle Cardiomyocytes High Protein (IHC) HPA →
Pancreas Exocrine glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Salivary gland Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced HPN IHC Tips

Use the catalog antibody’s colon section protocol as the IHC starting point, then assess staining against HPN topology and tissue patterns (datasheet A02350-1; UniProt P05981; HPA tissue IHC).

Which retrieval conditions should I start with for HPN in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A02350-1). The catalog antibody’s paraffin-embedded human colon image used that retrieval before 10% goat-serum blocking and 2 μg/ml primary antibody overnight at 4°C (datasheet A02350-1). If staining is weak, compare retrieval heating and cooling conditions on adjacent sections while holding primary concentration and detection constant (standard IHC practice). Include the same tissue control across runs, and assess epithelial staining alongside background and tissue preservation; colon glandular cells have reported high staining (HPA tissue IHC).
How should I troubleshoot inconsistent HPN staining after fixation?
HPN-specific sensitivity to fixative type or fixation duration is unknown from the supplied evidence (datasheet A02350-1; HPA tissue IHC). The catalog image identifies a paraffin-embedded human colon section but does not state its fixative, so its staining cannot establish a preferred fixation condition (datasheet A02350-1). Record fixation method and duration for each block, then compare sections processed with the same EDTA pH 8.0 retrieval and antibody conditions (datasheet A02350-1; standard IHC practice). Check morphology and staining in an internal glandular-cell control before attributing a weak result to fixation; colon glandular cells are reported as high (HPA tissue IHC).
Should HPN appear at the membrane or throughout the cytoplasm?
HPN is annotated at the cell membrane, including the apical membrane, with an extracellular region spanning residues 45–417 (UniProt P05981 topology and subcellular location). HPA describes its tissue IHC pattern as generally cytoplasmic, despite summarising its subcellular location as membrane (HPA tissue IHC; HPA subcellular). Score membrane-associated and diffuse cytoplasmic signal separately instead of assuming that either pattern alone establishes specificity (UniProt P05981; HPA tissue IHC; standard IHC practice). Compare intact glandular-cell architecture and matched controls; colon glandular cells are reported high, whereas salivary-gland glandular cells are reported not detected (HPA tissue IHC).
How can HPN processing and epitope position change the staining pattern?
The supplied record lists 0 isoforms and places HPN’s transmembrane segment at residues 24–44, followed by an extracellular region (UniProt P05981). It describes a non-catalytic chain at 1–162, a catalytic chain at 163–417, and glycosylation at residue 112 (UniProt P05981 processing and glycosylation). Because the catalog antibody’s epitope is not supplied, its accessibility on either chain after paraffin processing cannot be assigned from these annotations alone (datasheet A02350-1; UniProt P05981). Request epitope mapping before interpreting compartment differences as cleavage, and compare retrieval conditions only against a controlled, morphologically intact tissue section (standard IHC practice).
How should I adapt this HPN assessment to multiplex immunofluorescence?
Treat IF as a separate validation experiment: the supplied catalog example documents chromogenic IHC in a paraffin-embedded colon section, and HPA lists no cell lines with ICC/IF images (datasheet A02350-1; HPA subcellular). Multiplex HPN with a validated marker of the expected glandular cells, such as those reported high in colon, and inspect channel overlap within intact cells (HPA tissue IHC; standard IF practice). Choose fluorophores after measuring tissue autofluorescence and include single-color and no-primary controls for bleed-through and background (standard IF practice). Set permeabilisation according to the mapped epitope: HPN residues 1–23 are cytoplasmic and 45–417 extracellular, while this antibody’s epitope is unspecified (UniProt P05981 topology; datasheet A02350-1).
What should I check when HPN DAB staining is widespread?
First inspect a no-primary control for secondary-reagent binding, residual endogenous peroxidase, and nonspecific DAB deposition (standard chromogenic IHC practice). The catalog colon example used 10% goat-serum blocking, 2 μg/ml primary antibody overnight at 4°C, a peroxidase-conjugated secondary, and DAB development (datasheet A02350-1). Apply a peroxidase block and keep DAB development consistent across comparison sections; these are general workflow controls, not demonstrated HPN-specific requirements (standard chromogenic IHC practice). If diffuse signal persists, assess blocking, washing, primary concentration, and section edges against cell-specific staining; HPA reports high colon glandular-cell staining but no detection in salivary-gland glandular cells (HPA tissue IHC; standard IHC practice).
How should I quantify HPN staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and compartment before reviewing groups; HPN has a membrane annotation, while HPA describes general cytoplasmic tissue staining (UniProt P05981; HPA tissue IHC; standard IHC practice). Report the percentage of positive glandular cells and an intensity-based H-score from 0–300, keeping membrane and cytoplasmic scores separate (standard IHC scoring practice). For spatial analyses, report positive-cell density per mm² of viable tissue and normalise comparisons to the same eligible cell population or tissue area (standard IHC scoring practice). Use matched retrieval, detection, counterstaining, and image thresholds across samples, and interpret scores cautiously because HPA reports low consistency between antibody staining and RNA expression (HPA tissue IHC; standard IHC practice).
How can I distinguish credible HPN staining from tissue or detection artefacts?
Give greatest weight to reproducible staining in intact cells with an appropriate compartment pattern: HPN is annotated at the cell and apical membranes, while HPA reports general cytoplasmic tissue staining (UniProt P05981; HPA tissue IHC). Colon glandular cells are reported high and salivary-gland glandular cells not detected, providing tissue comparisons rather than proof of antibody specificity (HPA tissue IHC; standard IHC practice). Review unexpected cell types or compartments against morphology and controls, particularly staining confined to section edges or necrotic areas (standard IHC practice). A no-primary control and adequate peroxidase blocking help identify secondary-reagent or endogenous-enzyme signal during DAB detection (standard chromogenic IHC practice).
Boster reagents

Best HPN / Serine protease hepsin IHC Antibodies

The IHC-validated anti-HPN antibody has real staining data from human paraffin sections; catalog reactivity also includes mouse and rat (A02350-1 IHC captions; catalog reactivity).

Real IHC data IHC analysis of Hepsin/HPN using anti-Hepsin/HPN antibody (A02350-1). Hepsin/HPN was detected in a paraffin-embedded section of human colon tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Hepsin/HPN Antibody (A02350-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Hepsin/HPN Antibody ®
Cat # A02350-1

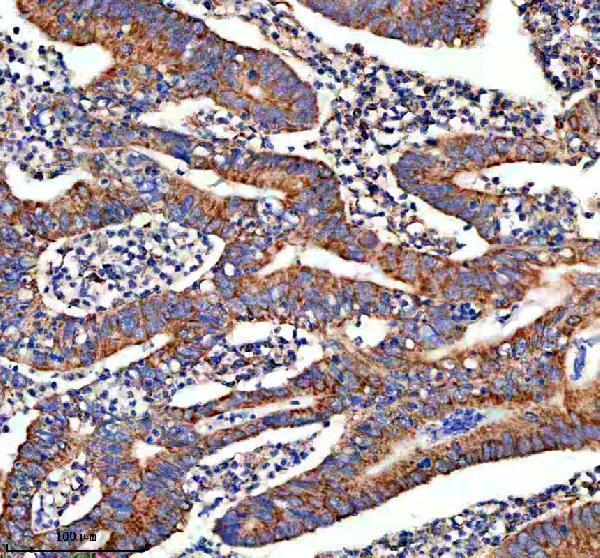
A02350-1 has IHC images from human colon, colon cancer and prostate cancer paraffin sections (A02350-1 IHC captions). Its listed applications include IHC, while IF/ICC is unlisted (A02350-1 catalog applications).

Which to pick: Choose A02350-1 for human paraffin-section IHC; its caption uses EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody, but does not report the fixative (A02350-1 IHC caption). No listed SKU has IF/ICC validation, so an IF/ICC choice cannot be supported here (A02350-1 catalog applications). A02350-1 lists mouse and rat reactivity, but its IHC images and IHC dilution entry cover human samples only (A02350-1 catalog reactivity; IHC captions; dilution entry).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P05981 (HEPS_HUMAN, Serine protease hepsin).
  2. Human Protein Atlas. HPN tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. HPN subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. HPN antibody validation summary (1 antibodies).
  5. Implication of Hepsin from Primary Tumor in the Prognosis of Colorectal Cancer Patients. Cancers 2022 — PMC9264764.
  6. Predicting biomarkers for ovarian cancer using gene-expression microarrays. British journal of cancer 2004 — PMC2409606.
  7. HPN-07, a free radical spin trapping agent, protects against functional, cellular and electrophysiological changes in the cochlea induced by acute acoustic trauma. PloS one 2017 — PMC5568441.
  8. The POR rs10954732 polymorphism decreases susceptibility to hepatocellular carcinoma and hepsin as a prognostic biomarker correlated with immune infiltration based on proteomics. Journal of translational medicine 2022 — PMC8842912.
  9. PubMed PMID:2835076 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.