HYOU1 / Hypoxia up-regulated protein 1 · IHC design guide

Design Immunohistochemistry for HYOU1

Plan paraffin-section IHC for HYOU1 using pancreatic exocrine cells as a high-staining reference (HPA tissue IHC). This guide covers fixation consistency, interpretation of mainly cytoplasmic staining, and the reported mismatch between staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for HYOU1 (IHC for HYOU1): expected localisation Mainly cytoplasmic staining in tissues (HPA tissue IHC), antibody A04934-2, validated IHC image, and IHC protocol steps
Printable HYOU1 IHC protocol sheet — expected localisation Mainly cytoplasmic staining in tissues (HPA tissue IHC), antibody A04934-2, controls and protocol steps. Open the full HYOU1 IHC guide →

HYOU1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Mainly cytoplasmic staining in tissues (HPA tissue IHC)
Staining pattern Pancreatic exocrine cells: high, mainly cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04934-2)
Positive control ⓘ Pancreas+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining has low consistency with RNA expression (HPA tissue IHC)
Regulation Up-regulated by hypoxia (UniProt)
Isoform / epitope 2 isoforms; signal peptide 1–32 is cleaved (UniProt)
Section 1

Recommended HYOU1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A04934-2) is paired with a published nasopharyngeal carcinoma IHC protocol (PMC4749358).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human gall bladder adenosquamous carcinoma tissue; fixative not specified (datasheet A04934-2)
FixationImage fixative and duration unreported (datasheet A04934-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04934-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04934-2)
Primary antibodyRabbit anti-HYOU1, 1-2 μg/ml (datasheet A04934-2)
Primary incubationOvernight at 4 °C (datasheet A04934-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A04934-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultHYOU1-positive staining in exocrine glandular cells of pancreas (HPA tissue IHC: High). HPA tissue profile: Mainly cytoplasmic expression in several different tissue types. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet A04934-2); the published protocol does not state a retrieval condition (PMC4749358).
Section 2

What Is the Expected HYOU1 Staining Pattern?

HYOU1 is a soluble endoplasmic reticulum lumen protein with no transmembrane segment, so staining should appear mainly in the cytoplasm rather than the nucleus or cell surface (UniProt Q9Y4L1: location and topology). Pancreatic exocrine glandular cells are a strong tissue reference (HPA: High). Interpret that reference with care: HPA rates the tissue IHC antibody Approved but reports low consistency between staining and RNA expression (HPA: reliability).

What am I looking at on my slide?
Cytoplasmic staining is strong in pancreatic exocrine glandular cells, with little nuclear staining (HPA: High in pancreatic exocrine cells; UniProt Q9Y4L1: ER lumen).This fits the reported cell type and compartment. Score the stained cells and intensity, rather than treating every cell in the section as an expected positive (HPA: tissue IHC; general IHC practice).
Staining is predominantly nuclear or sharply confined to the cell surface (UniProt Q9Y4L1: ER lumen; no transmembrane segment).That distribution conflicts with the annotated location. Treat it as a possible staining or interpretation artifact and compare it with a known-positive section and a primary-antibody omission control (UniProt Q9Y4L1: location; general IHC practice).
Adipocytes stain strongly in adipose tissue or breast sections, or hematopoietic cells stain strongly in bone marrow (HPA: Not detected in those specified cells).These are cell-specific discrepancies, not proof that the entire tissue must be blank. Consider cross-reactivity or endogenous detection activity; inspect an omission control before assigning HYOU1 positivity (HPA: tissue IHC; general IHC practice).
Chromogen covers extracellular space, empty areas or many unrelated cell types with similar intensity (general IHC practice).A widespread, poorly cell-delimited deposit is less persuasive than cytoplasmic staining in the expected cells. Check detection background, blocking and wash steps before scoring it as HYOU1 (HPA: High in pancreatic exocrine cells; general IHC practice).
Pancreatic exocrine glandular cells show no signal (HPA: High in pancreatic exocrine cells).The expected reference pattern has failed. Review the catalog antibody’s IHC-P conditions, section quality and detection controls before interpreting other sections as negative (HPA: tissue IHC; general IHC practice).
💡Expected HYOU1 appearanceA convincing positive is cell-delimited, mainly cytoplasmic chromogenic staining, strongest in pancreatic exocrine glandular cells; predominantly nuclear or cell-surface signal is suspect (HPA: tissue IHC; UniProt Q9Y4L1: ER lumen and topology).
How each factor affects the staining
Antibody evidence (HPA: HPA049296, IHC Approved).Approved does not mean every tissue result agrees with RNA: HPA reports low staining–RNA consistency, so use morphology and controls when judging unexpected positives or negatives (HPA: reliability description).
Cell and tissue choice (HPA: tissue IHC).Pancreatic exocrine cells are High; neuronal cells in cerebral cortex and hippocampus and several glandular cell groups are Medium. Compare like cell types when setting an intensity reference (HPA: tissue IHC).
Negative-reference choice (HPA: tissue IHC).HPA's Not detected calls name specific cells, including adipocytes and bone-marrow hematopoietic cells. They do not establish that every other cell in those sections is negative (HPA: tissue IHC).
Protein form and epitope (UniProt Q9Y4L1: processing and isoforms).UniProt annotates a cleaved signal peptide at residues 1–32 and two isoforms. The supplied record gives no antibody epitope, so it cannot establish which forms this IHC stain detects (UniProt Q9Y4L1; HPA: HPA049296).
Antigen retrieval (general IHC practice).Use the catalog antibody’s IHC-P conditions as the starting point and assess retrieval with controls. Neither source here establishes an HYOU1-specific fixation or retrieval effect (general IHC practice; UniProt Q9Y4L1; HPA: tissue IHC).
IF/ICC Q&A: Is an IF pattern validated here? (HPA: subcellular and antibody records).No HPA main ICC-IF location or cell-line images are supplied, and HPA049296 has no ICC status. The ER annotation suggests a cytoplasmic expectation, but this IHC evidence does not validate an IF pattern (HPA: subcellular; UniProt Q9Y4L1: location).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in a pancreatic reference section (HPA: High in exocrine glandular cells).The expected reference failed; preparation or detection may have failed, but the image alone cannot identify which step (HPA: tissue IHC; general IHC practice).Check the catalog antibody’s IHC-P conditions, section quality, detection reagents and a working positive control before scoring study sections (general IHC practice).
Strong nuclear staining dominates the section (UniProt Q9Y4L1: ER lumen).Nuclear dominance conflicts with the annotated compartment and may reflect nonspecific signal or misread counterstain (UniProt Q9Y4L1; general IHC practice).Compare chromogen with the counterstain, review a pancreatic reference and inspect a primary-antibody omission control (HPA: High in pancreatic exocrine cells; general IHC practice).
Unexpected staining appears in HPA-negative reference cells (HPA: Not detected in adipocytes and bone-marrow hematopoietic cells).Cross-reactivity or endogenous detection activity is possible; the HPA call applies to the named cells (HPA: tissue IHC; general IHC practice).Confirm cell identity, inspect an omission control and assess the relevant endogenous-activity block before attributing the signal to HYOU1 (general IHC practice).
Diffuse chromogen obscures cell boundaries (general IHC practice).Excess background can arise during blocking, washing or detection; this appearance does not establish target localization (general IHC practice).Check omission controls, wash steps and detection conditions, then score only cell-delimited staining that remains interpretable (general IHC practice).
Staining varies across sections or appears weaker than expected in another tissue (HPA: tissue IHC).HPA reports different cell-specific levels and low staining–RNA consistency; equal intensity across tissues is not established (HPA: tissue IHC and reliability).Compare the same cell type where possible, keep scoring criteria consistent and include a pancreatic reference section (HPA: High in pancreatic exocrine cells; general IHC practice).
An IF/ICC image appears inconsistent with the IHC result (HPA: ICC status unavailable for HPA049296).The supplied HPA record has no main ICC-IF location or cell-line images, so it does not establish a validated IF comparison (HPA: subcellular and antibody records).Judge the paraffin-section result against IHC cell patterns and controls; use the separate IF/ICC guide for IF-specific validation (HPA: tissue IHC; general IHC practice).

Sample controls for HYOU1 IHC & IF

🧪Run pancreas first: exocrine glandular cells should stain (HPA: High in pancreas exocrine glandular cells). Use adipose tissue as the negative comparator, focusing on adipocytes (HPA: Not detected in adipocytes); on the pancreas slide, acellular areas should show only background, while other cell types should not be assumed negative (standard IHC practice).
Positive control tissue: Pancreas (Exocrine glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for HYOU1; derive a cell-line control from the positive tissue's cell type (Exocrine glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include no-primary (secondary-only) and species- and isotype-matched nonimmune rabbit IgG controls (caption: rabbit primary antibody; standard IHC practice), plus HYOU1 knockout material or a validated peptide-block control (standard IHC practice). In pancreas, quench endogenous peroxidase and check for endogenous biotin background because the selected detection uses SABC/DAB (caption: SABC/DAB; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected IHC caption does not state a fixative (caption: fixative unreported). The paraffin-section example uses heat retrieval in EDTA at pH 8.0, followed by 2 μg/ml primary antibody overnight at 4°C; it does not establish whether retrieval is required for other preparations (caption: retrieval and incubation conditions). Frozen sections and IF require separate optimization, so neither is established as easier here; pancreatic staining with biotin-based detection needs background checks (HPA: no ICC-IF images listed; caption: SABC/DAB; standard IHC practice).

HPA tissue IHC evidence for HYOU1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Pancreas Exocrine glandular cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells Medium Protein (IHC) HPA →
Duodenum Glandular cells Medium Protein (IHC) HPA →
Hippocampus Neuronal cells Medium Protein (IHC) HPA →
Seminal vesicle Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced HYOU1 IHC Tips

Troubleshoot chromogenic HYOU1 IHC in paraffin sections using the catalog antibody’s tissue example, protein annotations, and tissue staining patterns.

What retrieval should I start with if HYOU1 staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A04934-2). The selected tissue example used this retrieval before 10% goat-serum blocking and 2 μg/ml primary antibody overnight at 4°C (datasheet A04934-2). If staining is weak, first compare retrieval time across adjacent sections while holding antibody concentration and DAB development constant (standard IHC practice). Check that any gain appears in the expected cytoplasmic compartment and in a positive control, rather than solely at section edges (UniProt Q9Y4L1 localisation; HPA: mainly cytoplasmic; standard IHC practice).
How should I assess fixation as a cause of variable HYOU1 staining?
Record the fixative, fixation duration, specimen thickness, and time before fixation for each paraffin block before comparing staining (standard IHC practice). The selected tissue caption identifies a paraffin-embedded section but does not state its fixative, so target-specific fixation sensitivity remains unknown (datasheet A04934-2). Compare adjacent sections from blocks with documented processing using the same EDTA pH 8.0 retrieval and 2 μg/ml primary concentration (datasheet A04934-2; standard IHC practice). Include a concurrently stained control section and interpret differences only after checking tissue preservation, section adherence, and comparable DAB development (standard IHC practice).
Where should convincing HYOU1 staining appear in paraffin sections?
Expect predominantly cytoplasmic staining at the light-microscope level, consistent with HYOU1 localisation in the endoplasmic-reticulum lumen (HPA: mainly cytoplasmic; UniProt Q9Y4L1 localisation). A membrane outline or isolated nuclear signal warrants review because the annotated protein has no transmembrane segment and is processed from a signal-bearing precursor (UniProt Q9Y4L1 topology and processing). Compare staining with a concurrent tissue control: pancreatic exocrine glandular cells are reported high, whereas adipocytes in adipose tissue are reported not detected (HPA: tissue IHC). Score epithelial or glandular cells separately from infiltrating cells, because HYOU1 is also reported in macrophages within aortic atherosclerotic plaques (UniProt Q9Y4L1 tissue specificity; standard IHC practice).
Could epitope choice explain discordant HYOU1 IHC results?
Check the antibody’s documented immunogen or epitope before interpreting differences between assays; the supplied tissue caption does not identify the recognized sequence (datasheet A04934-2). HYOU1 has 2 annotated isoforms and a signal peptide at residues 1–32, followed by a chain spanning 33–999 (UniProt Q9Y4L1 isoforms and processing). Its 9 annotated glycosylation sites could matter when comparing antibodies against different regions, but epitope sensitivity cannot be assigned without mapping (UniProt Q9Y4L1 glycosylation; standard IHC practice). Keep retrieval, antibody concentration, and tissue controls matched when comparing reagents, then report the epitope information available for each (standard IHC practice).
How can IF help check an ambiguous chromogenic HYOU1 pattern?
Use IF as a separate localisation check and validate its staining conditions independently; the supplied catalog example documents paraffin-section chromogenic IHC (datasheet A04934-2). Multiplex HYOU1 with a marker for the cell population being evaluated, such as a macrophage marker when assessing plaque macrophages (UniProt Q9Y4L1 tissue specificity; standard IF practice). Choose spectrally separated fluorophores after examining tissue autofluorescence and include single-label controls to assess bleed-through (standard IF practice). Because HYOU1 is annotated in the endoplasmic-reticulum lumen, establish permeabilisation sufficient to expose the luminal epitope in the IF preparation and verify the result against morphology (UniProt Q9Y4L1 localisation; standard IF practice).
How do I reduce diffuse brown background without losing HYOU1 signal?
First inspect a section processed without primary antibody to assess secondary-reagent and detection-system background (standard IHC practice). The selected example used 10% goat-serum blocking, a biotinylated secondary, a streptavidin–biotin complex, and DAB, so evaluate those steps when brown staining is widespread (datasheet A04934-2; standard IHC practice). Apply a peroxidase block and assess endogenous biotin where relevant to the detection system; these are general chromogenic IHC controls, not demonstrated HYOU1-specific requirements (standard IHC practice). Retitrate primary antibody around the documented 2 μg/ml condition while keeping retrieval, washing, and DAB development matched across sections (datasheet A04934-2; standard IHC practice).
What should I measure when comparing HYOU1 across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the anatomical region and cell population before scoring, because staining differs by tissue and cell type (HPA: tissue IHC; standard IHC practice). For cellular staining, record the percentage of positive cells and an intensity-based H-score; for scattered positive cells, report density per mm² of viable tissue (standard IHC practice). Normalise counts to the assessed cell population or viable tissue area, and use identical thresholds, illumination, and DAB development across samples (standard IHC practice). Report cytoplasmic scores separately from questionable nuclear or edge staining, and include a concurrently processed control to track run variation (HPA: mainly cytoplasmic; standard IHC practice).
How can I distinguish true HYOU1 staining from artefact?
Seek reproducible cytoplasmic staining in intact cells, consistent with HYOU1 localisation in the endoplasmic-reticulum lumen and reported mainly cytoplasmic tissue staining (UniProt Q9Y4L1 localisation; HPA: tissue IHC). Pancreatic exocrine glandular cells provide a reported high-staining reference, while adipocytes in adipose tissue are reported not detected (HPA: tissue IHC). Review unexpected staining at section edges, in necrotic areas, or in a predominantly nuclear pattern against morphology and control sections (UniProt Q9Y4L1 localisation; standard IHC practice). Use a no-primary control to investigate brown signal from endogenous enzyme activity or detection reagents, and avoid equating staining intensity with RNA abundance because the HPA assessment reports low staining–RNA consistency (HPA: reliability assessment; standard IHC practice).
Boster reagents

Best HYOU1 / Hypoxia up-regulated protein 1 IHC Antibodies

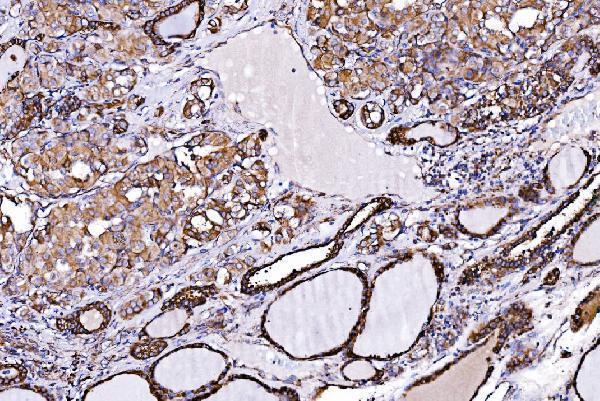
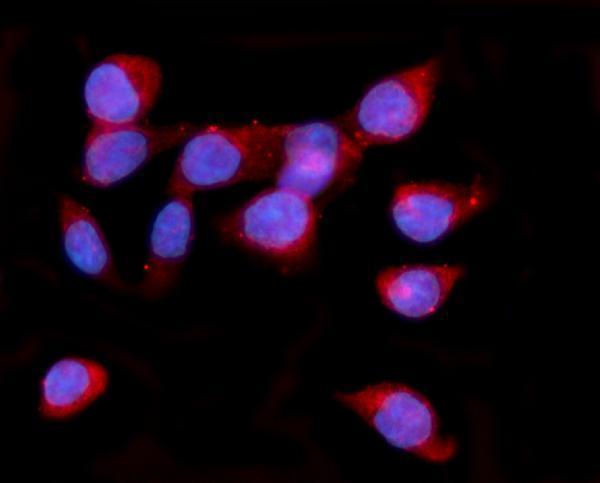
The figure-backed HYOU1 antibody has paraffin-section IHC data from human tumors and IF/ICC data from CACO-2 cells (catalog image captions). Human, mouse, and rat reactivity is listed (catalog: A04934-2).

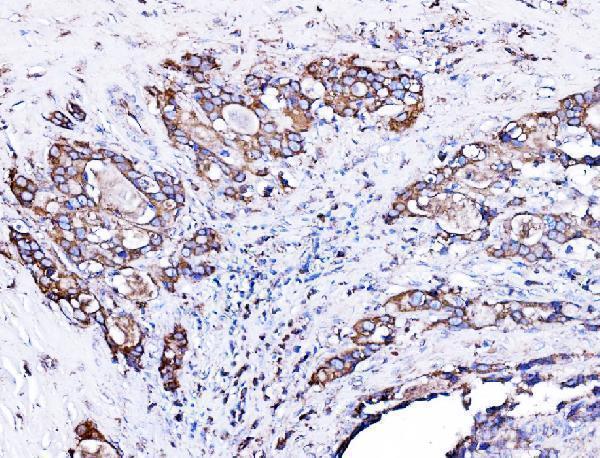
Real IHC data IHC analysis of ORP150/HYOU1 using anti-ORP150/HYOU1 antibody (A04934-2). ORP150/HYOU1 was detected in a paraffin-embedded section of human gall bladder adenosquamous carcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-ORP150/HYOU1 Antibody (A04934-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-ORP150/HYOU1 Antibody ®
Cat # A04934-2

A04934-2 is the SKU with a rendered IHC figure, showing a human gall bladder adenosquamous carcinoma paraffin section (A04934-2 IHC image caption). Its separate IF/ICC image shows CACO-2 cells (A04934-2 IF image caption).

Which to pick: Choose A04934-2 for tissue IHC: its image documents a paraffin section with EDTA pH 8.0 retrieval, while the fixative is unreported (A04934-2 IHC image caption). Choose A04934-2 for IF/ICC because its application list includes both and its IF image shows CACO-2 cells (catalog: A04934-2; A04934-2 IF image caption). For mouse or rat samples, both A04934-2 and rabbit monoclonal M04934-2 list reactivity, but the supplied IHC image evidence for A04934-2 is human only and M04934-2 has no supplied IHC image (catalog: A04934-2, M04934-2).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9Y4L1 (HYOU1_HUMAN, Hypoxia up-regulated protein 1).
  2. Human Protein Atlas. HYOU1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. HYOU1 subcellular location (ICC-IF): Highest expression in EFO-21: 476.0 nTPM.
  4. Human Protein Atlas. HYOU1 antibody validation summary (1 antibodies).
  5. Proteomic profiling of lung adenocarcinoma indicates heightened DNA repair, antioxidant mechanisms and identifies LASP1 as a potential negative predictor of survival. Clinical proteomics 2016 — PMC5084393.
  6. HYOU1, Regulated by LPLUNC1, Is Up-Regulated in Nasopharyngeal Carcinoma and Associated with Poor Prognosis. Journal of Cancer 2016 — PMC4749358.
  7. Unveiling FLNC variants: iPSC-derived myogenic cells as a model to study disease mechanisms. Skeletal muscle 2026 — PMC13063712.
  8. Acidic microenvironment plays a key role in human melanoma progression through a sustained exosome mediated transfer of clinically relevant metastatic molecules. Journal of experimental & clinical cancer research : CR 2018 — PMC6173926.
  9. PubMed PMID:9020069 — UniProt-cited evidence.
  10. PubMed PMID:10965054 — UniProt-cited evidence.
  11. PubMed PMID:17131193 — UniProt-cited evidence.