ICOSLG / ICOS ligand · IHC design guide

Design Immunohistochemistry for ICOSLG

Plan chromogenic IHC of paraffin sections for ICOSLG using the catalog antibody at 2 μg/mL (datasheet). Compare cytoplasmic tissue staining (HPA tissue IHC) with the expected membrane location (UniProt), bearing in mind the low consistency between antibody staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ICOSLG (IHC for ICOSLG): expected localisation Cytoplasmic staining observed (HPA tissue IHC); membrane expected (UniProt), antibody A01965, validated IHC image, and IHC protocol steps
Printable ICOSLG IHC protocol sheet — expected localisation Cytoplasmic staining observed (HPA tissue IHC); membrane expected (UniProt), antibody A01965, controls and protocol steps. Open the full ICOSLG IHC guide →

ICOSLG Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining observed (HPA tissue IHC); membrane expected (UniProt)
Staining pattern High cytoplasmic staining in lung macrophages (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining has low consistency with RNA expression (HPA tissue IHC)
Regulation Expression regulation not specified (UniProt)
Isoform / epitope 3 isoforms; check extracellular vs cytoplasmic epitope (UniProt)
Section 1

Recommended ICOSLG IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with published ICOSLG IHC methods for tumor tissue microarrays, skin sections, and oral squamous cell carcinoma sections (PMC13239265; PMC13324650; PMC10569602).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A01965); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-ICOSLG, 2 μg/mL (datasheet A01965)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultICOSLG-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page antigen retrieval rule); the cited excerpts do not specify retrieval conditions.
Section 2

What Is the Expected ICOSLG Staining Pattern?

ICOSLG is a cell membrane protein with an extracellular region at residues 19–256 and a transmembrane segment at 257–277 (UniProt O75144 topology). In tissue IHC, assess staining in cell populations reported by HPA, including lung macrophages and lymph node germinal center cells (HPA: High). HPA also describes general cytoplasmic staining, but rates the tissue profile Approved with low consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Distinct staining in lung macrophages or lymph node germinal center cells, with a discernible cell border.These are useful positive patterns: HPA reports High staining in both populations (HPA tissue IHC). A membrane component fits ICOSLG topology (UniProt O75144 topology). Record the actual compartment seen, since HPA's tissue summary also describes general cytoplasmic expression (HPA tissue IHC).
Predominantly nuclear staining, or signal confined to a compartment unrelated to the cell border.Treat this as a localisation mismatch requiring review: UniProt places ICOSLG at the cell membrane (UniProt O75144 subcellular location). Check morphology, controls and detection conditions before calling it ICOSLG. Cytoplasmic tissue staining alone is less decisive because HPA reports a general cytoplasmic pattern (HPA tissue IHC).
Strong, uniform staining in an unexpected cell population while expected positive cells are unstained.Consider antibody cross-reactivity or endogenous detection activity and compare with appropriate controls (standard IHC practice). Do not reject a population solely because it is absent from UniProt's immune-cell list: HPA also reports High staining in several glandular and neuronal populations (HPA tissue IHC; UniProt O75144 tissue specificity).
Diffuse color across cells, stroma and blank spaces, without distinguishable cell boundaries.This pattern is difficult to score as specific cellular staining (standard IHC practice). Assess background with a no-primary control, then review blocking, detection reagent and chromogen development under the general IHC workflow (standard IHC practice). HPA's reported cytoplasmic profile does not establish that diffuse slide-wide color is specific (HPA tissue IHC).
No detectable signal in the tested lung macrophages or lymph node germinal center cells.These populations have High staining in HPA images, so absent signal warrants a run-level check (HPA tissue IHC). Verify the population is present in the section and review antibody, retrieval and detection conditions against the chosen validated IHC method (standard IHC practice). HPA's low RNA–staining consistency limits any claim that every specimen must stain (HPA tissue IHC).
💡Expected ICOSLG appearanceCall a result positive when identifiable cells show staining with a plausible membrane component, especially lung macrophages or lymph node germinal center cells reported High by HPA; treat uniform nuclear or slide-wide color as suspect rather than a clear ICOSLG pattern (UniProt O75144 topology; HPA tissue IHC; standard IHC practice).
How each factor affects the staining
Epitope position and topologyICOSLG has extracellular residues 19–256, a transmembrane segment at 257–277 and a short cytoplasmic tail at 278–302 (UniProt O75144 topology). The antibody epitope is unspecified here, so topology predicts the protein's location but cannot establish which retrieval condition exposes this antibody's epitope (UniProt O75144 topology; standard IHC practice).
Tissue evidence and antibody agreementHPA rates the tissue IHC profile Approved while noting low consistency between staining and RNA expression (HPA tissue IHC). Its two listed IHC antibodies are individually Approved; neither is listed as IHC Enhanced in the supplied record (HPA antibodies). Use cell-resolved controls when interpreting unexpected positives (standard IHC practice).
Processing, glycosylation and isoformsUniProt lists a signal peptide at residues 1–18, five glycosylation sites and three isoforms (UniProt O75144 processing, glycosylation, isoforms). These features make antibody epitope information relevant to interpretation, but the supplied record gives no epitope, isoform coverage, shedding result or target-specific fixation sensitivity.
Antigen retrievalChoose retrieval conditions from the IHC-validated antibody's method and check the positive control when conditions change (standard IHC practice). Neither HPA's tissue levels nor UniProt's topology demonstrates a particular retrieval requirement or a formalin-induced change in ICOSLG detection (HPA tissue IHC; UniProt O75144 topology).
IF/ICC: What localisation should be expected?HPA lists plasma membrane localisation as supported and vesicles as uncertain; its ICC-IF images include RT-4, SiHa and U2OS (HPA subcellular). This answers the localisation question for IF/ICC without using its images as an IHC protocol or treating uncertain vesicle signal as a required positive feature (HPA subcellular).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known positive population is present, but its IHC signal is absent.Antibody, retrieval or detection conditions may be inadequate for this run (standard IHC practice).Check the HPA High population in the section, then review the IHC-validated method and run controls (HPA tissue IHC; standard IHC practice).
Only nuclei stain.A nuclear-only pattern conflicts with the reported cell membrane location (UniProt O75144 subcellular location).Compare a no-primary control and cell morphology; reassess antibody specificity and detection background (standard IHC practice).
All cell types show similar color.Nonspecific binding or endogenous detection activity may obscure cell-specific staining (standard IHC practice).Examine no-primary and detection controls, then review blocking and detection conditions (standard IHC practice).
Cytoplasmic staining appears without an obvious membrane rim.HPA reports general cytoplasmic tissue staining, while UniProt places ICOSLG at the membrane (HPA tissue IHC; UniProt O75144).Document the compartment and cell type; compare with controls before assigning specificity (standard IHC practice).
A low-staining comparison tissue looks as intense as a positive population.Background or a specimen difference may explain the contrast; HPA reports low staining in selected cells (HPA tissue IHC).Compare matched sections and controls, and score the identified cells rather than whole-section color (standard IHC practice).
A proposed IF/ICC image shows mainly vesicle-like puncta.HPA marks vesicle localisation uncertain and plasma membrane localisation supported (HPA subcellular).Keep that observation separate from the paraffin IHC call; assess membrane signal and consult the dedicated IF/ICC guide (HPA subcellular).

Sample controls for ICOSLG IHC & IF

🧪Run appendix first and look for staining in glandular cells (HPA: High in appendix glandular cells). HPA detects ICOSLG in all 45 scored tissues, so use no-primary and isotype controls for the negative comparison; cells without specific signal on the appendix slide should show only counterstain, without assuming a particular cell type is ICOSLG-negative (HPA: no negative tissue rows; standard IHC interpretation).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: ICOSLG is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ICOSLG in RT-4, SiHa, U2OS, with annotated localisation: Vesicles (uncertain), Plasma membrane (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and an isotype control matched to the primary antibody’s host species and immunoglobulin class, with a control appropriate to its clonality (standard IHC practice). Use an ICOSLG knockout specimen or a peptide block if a compatible immunizing peptide is available as a biological specificity control; quench endogenous peroxidase and check background in the appendix section (standard IHC practice).
⚠️Feasibility: A target-specific fixation window and antigen-retrieval dependency are unreported in the supplied evidence; the A01965 lymph-node IHC caption reports 2 µg/ml but does not state a fixative (A01965 tissue-IHC caption). The evidence does not establish whether frozen sections or IF/ICC are easier than paraffin IHC, although ICC-IF images exist for RT-4, SiHa and U2OS (HPA subcellular). Assess appendix background alongside the controls because endogenous peroxidase can complicate chromogenic IHC interpretation (standard IHC practice).

HPA tissue IHC evidence for ICOSLG

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: ICOSLG is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced ICOSLG IHC Tips

Use compartment, cell identity, and matched controls to interpret ICOSLG staining in paraffin sections (UniProt O75144; standard IHC practice).

What retrieval conditions should I start with for ICOSLG in paraffin sections?
Start with citrate pH 6.0 heat-induced epitope retrieval at 95–98 °C for 20 min (page retrieval rule: cytoplasmic / membrane antigen). Allow sections to cool in the retrieval buffer, then keep the wash and chromogenic detection steps consistent across test sections (standard IHC practice). Evaluate the result against a matched no-primary control and the catalog antibody’s human lymph-node tissue image, which used 2 µg/mL antibody but did not state the fixative (A01965 tissue-IHC caption). If staining is weak, adjust retrieval duration in small increments while checking morphology and background, because the extracellular ICOSLG region spans residues 19–256 (UniProt O75144 topology; standard IHC practice).
How should I troubleshoot variable ICOSLG staining after fixation?
Target-specific sensitivity of ICOSLG to fixation is unknown from the supplied evidence; the A01965 tissue-IHC caption does not state a fixative (A01965 tissue-IHC caption). Record the fixative, time in fixative, section thickness, and processing history for each specimen, and compare sections processed together before changing antibody conditions (standard IHC practice). If intensity differs between runs, repeat staining with the same citrate pH 6.0 retrieval at 95–98 °C for 20 min and a shared control section (page retrieval rule; standard IHC practice). Check preserved morphology and staining distribution before attributing a difference to ICOSLG abundance, since fixation and processing can affect antigen accessibility in paraffin IHC (standard IHC practice).
Should ICOSLG staining appear on the membrane or in the cytoplasm?
Expect a plasma-membrane component because ICOSLG has an extracellular region at residues 19–256 and a transmembrane segment at 257–277 (UniProt O75144 topology). Vesicular staining is also plausible, although that location is uncertain in the subcellular reference, while its plasma-membrane location is supported (HPA subcellular: vesicles uncertain, plasma membrane supported). Tissue IHC has been described as generally cytoplasmic, so record membrane and cytoplasmic patterns separately rather than treating either pattern alone as proof of specificity (HPA tissue IHC: general cytoplasmic expression; standard IHC practice). Compare each pattern with cell identity, a no-primary control, and section morphology; diffuse extracellular deposit warrants investigation as background (standard IHC practice).
Could ICOSLG isoforms or epitope location explain inconsistent IHC staining?
ICOSLG has 3 reported isoforms, but the supplied evidence does not map the catalog antibody’s epitope to any isoform (UniProt O75144 isoforms; A01965 tissue-IHC caption). Its extracellular region spans residues 19–256, its membrane segment 257–277, and its cytoplasmic tail 278–302 (UniProt O75144 topology). Five glycosylation sites are listed at residues 70, 137, 173, 186, and 225; their effect on this antibody’s paraffin-section staining is unknown (UniProt O75144 glycosylation; A01965 tissue-IHC caption). Check the antibody’s documented immunogen or epitope before interpreting discordant staining as isoform-specific, and compare any alternative antibody with matched sections and controls (standard IHC practice).
How can I use IF to investigate an ambiguous chromogenic ICOSLG pattern?
Use IF as a separate localisation check and multiplex ICOSLG with CD68 in lung sections to assess staining in macrophages, a reported high-staining population (HPA tissue IHC: high in lung macrophages; standard IF practice). Choose fluorophores in spectral regions with low measured tissue autofluorescence, and examine single-label controls before interpreting overlap (standard IF practice). Permeabilisation depends on epitope access: an extracellular epitope may be accessible without it, whereas an intracellular-tail epitope requires access across the membrane; the catalog antibody’s epitope is unspecified (UniProt O75144 topology; A01965 tissue-IHC caption; standard IF practice). Keep IF conclusions distinct from the chromogenic IHC result, since the supplied A01965 image documents tissue IHC only (A01965 tissue-IHC caption).
What should I check when ICOSLG DAB staining is widespread?
First inspect a matched no-primary control for endogenous peroxidase activity and nonspecific detection-system deposits, then confirm that the peroxidase block was applied (standard chromogenic IHC practice). Compare the distribution with ICOSLG’s supported plasma-membrane localisation and uncertain vesicular localisation, while allowing for the generally cytoplasmic pattern reported in tissue IHC (HPA subcellular; HPA tissue IHC). Strong staining across unrelated structures should prompt review of section edges, damaged areas, blocking, wash steps, and DAB development time before changing the ICOSLG interpretation (standard IHC practice). Retitrate the primary antibody around the documented 2 µg/mL image condition using matched sections, without treating that image concentration as a validated optimum for every specimen (A01965 tissue-IHC caption; standard IHC practice).
How should I quantify ICOSLG staining across lymph-node sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scoring compartment and cell population before counting; the reference reports high staining in lymph-node germinal-center cells, while ICOSLG has a supported plasma-membrane location (HPA tissue IHC: high in lymph-node germinal-center cells; HPA subcellular). Score the percentage of positive cells and staining intensity as an H-score, or count positive cells per mm² within a consistently annotated region (standard IHC practice). Normalise positive-cell counts to the total eligible cells or measured viable tissue area, and use the same threshold, counterstain, and imaging settings for every section (standard IHC practice). Report membrane and cytoplasmic scores separately and exclude folds, necrosis, and section edges from the analysed area (HPA tissue IHC: general cytoplasmic expression; standard IHC practice).
How can I distinguish true ICOSLG staining from tissue artefact?
Interpret staining alongside cell identity: ICOSLG protein is reported on peripheral-blood B cells, monocytes, and monocyte-derived dendritic cells, and tissue IHC reports high staining in lung macrophages and lymph-node germinal-center cells (UniProt O75144 tissue specificity; HPA tissue IHC). A membrane-associated signal is biologically compatible with its transmembrane topology, but the tissue reference also reports general cytoplasmic staining (UniProt O75144 topology; HPA tissue IHC). Treat isolated edge staining, necrotic deposits, or signal reproduced by a no-primary control as potential artefact; review peroxidase blocking when DAB signal persists without primary antibody (standard chromogenic IHC practice). Weigh unexpected cell or compartment staining cautiously because the tissue IHC reference reports low consistency between antibody staining and RNA expression (HPA tissue IHC: reliability description).
Boster reagents

Best ICOSLG / ICOS ligand IHC Antibodies

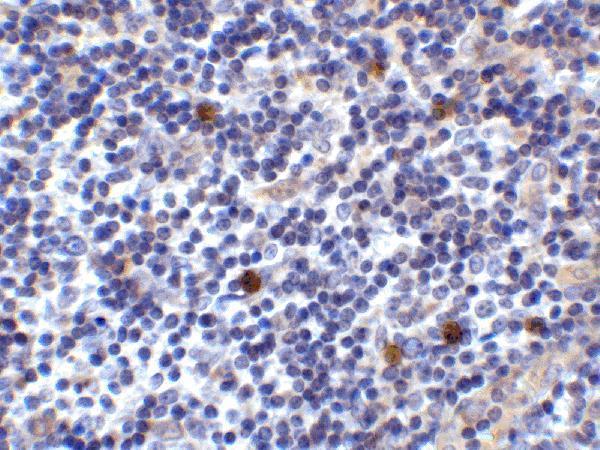
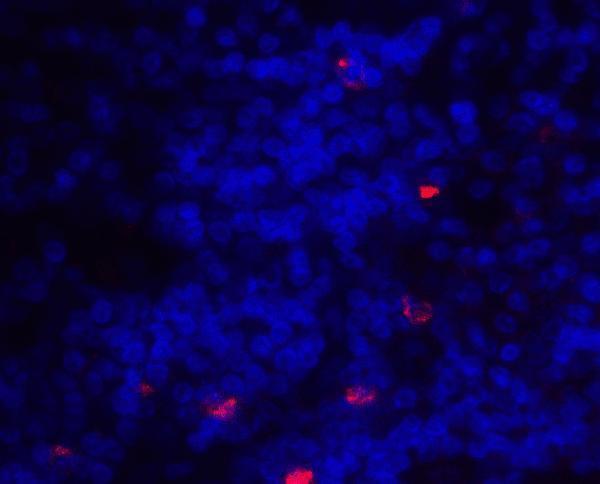
A01965 has IHC and IF images from human lymph node tissue (catalog image captions); human is the only listed reactivity (catalog: Human).

Real IHC data Immunohistochemistry of ICOSLG in human lymph node tissue with ICOSLG antibody at 2 μg/ml.
Anti-ICOS ligand ICOSLG Antibody
Cat # A01965

A01965 is listed for IHC and IF in human samples (catalog: applications and reactivity). Its IHC and IF images each show human lymph node tissue (catalog: IHC and IF image captions).

Which to pick: Choose A01965 for human tissue IHC: its own IHC image shows human lymph node tissue at 2 μg/mL (catalog: IHC image caption). A01965 is also listed for IF, with a human lymph node IF image; ICC validation is unreported (catalog: applications and IF image caption). No cross-species reactivity is listed, and the IHC caption does not report section processing or fixative (catalog: reactivity and IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O75144 (ICOSL_HUMAN, ICOS ligand).
  2. Human Protein Atlas. ICOSLG tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. ICOSLG subcellular location (ICC-IF): Localized to the plasma membrane and vesicles..
  4. Human Protein Atlas. ICOSLG antibody validation summary (3 antibodies).
  5. Inducible T Cell Costimulator Ligand and Inducible T Cell Costimulator Stratification Identify Dichotomous Tumor Microenvironment and Guide Chemo-Immunotherapy in Small Cell Lung Cancer. MedComm 2026 — PMC13239265.
  6. RUNX1 recruitment of GCN5 in keratinocytes upregulates ICOSLG and promotes T cell activation in the psoriasis microenvironment. Experimental & molecular medicine 2026 — PMC13324650.
  7. Identification of Prognostic Markers of Gynecologic Cancers Utilizing Patient-Derived Xenograft Mouse Models. Cancers 2022 — PMC8834149.
  8. ICOSLG-associated immunological landscape and diagnostic value in oral squamous cell carcinoma: a prospective cohort study. Frontiers in cell and developmental biology 2023 — PMC10569602.
  9. PubMed PMID:11023515 — UniProt-cited evidence.
  10. PubMed PMID:11007762 — UniProt-cited evidence.
  11. PubMed PMID:10657606 — UniProt-cited evidence.