IFIT2 / Interferon-induced protein with tetratricopeptide repeats 2 · IHC design guide

Design Immunohistochemistry for IFIT2

Plan chromogenic IHC on paraffin sections with the catalog antibody at 2–5 μg/ml (datasheet A04428-1). Assess cytoplasmic staining in immune cells and interpret intensity cautiously because staining and RNA expression show very low consistency (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for IFIT2 (IHC for IFIT2): expected localisation Cytoplasm in immune cells (HPA tissue IHC); ER (UniProt), antibody A04428-1, validated IHC image, and IHC protocol steps
Printable IFIT2 IHC protocol sheet — expected localisation Cytoplasm in immune cells (HPA tissue IHC); ER (UniProt), antibody A04428-1, controls and protocol steps. Open the full IFIT2 IHC guide →

IFIT2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasm in immune cells (HPA tissue IHC); ER (UniProt)
Staining pattern Cytoplasmic immune-cell staining; texture unspecified (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04428-1)
Positive control ⓘ Kidney
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Very low consistency between staining and RNA expression (HPA tissue IHC)
Regulation Interferon induced (UniProt)
Isoform / epitope No annotated isoforms; chain spans residues 2–472 (UniProt)
Section 1

Recommended IFIT2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by four published IFIT2 IHC protocols (PMC8797327; PMC6781603; PMC4161885; PMC9644211).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver cancer tissue; fixative not specified (datasheet A04428-1)
FixationImage fixative and duration unreported (datasheet A04428-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04428-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04428-1)
Primary antibodyRabbit anti-IFIT2, 2-5 μg/ml (datasheet A04428-1)
Primary incubationOvernight at 4 °C (datasheet A04428-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A04428-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultIFIT2-positive staining in cells in tubules of kidney (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in immune cells. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet A04428-1). Use the cited citrate conditions when reproducing those studies (PMC6781603; PMC4161885).
Section 2

What Is the Expected IFIT2 Staining Pattern?

IFIT2 is annotated in the cytoplasm and endoplasmic reticulum, with no transmembrane segment (UniProt P09913). In tissue IHC, expect cytoplasmic staining in immune cells, with high staining reported in kidney tubular cells and low staining in selected lymph node and bone marrow cells (HPA tissue IHC). HPA rates the IHC staining Approved but reports very low consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
High cytoplasmic staining in kidney tubular cells.This matches the strongest supplied tissue example (HPA tissue IHC: High in kidney tubular cells). Score the tubular cells and their cytoplasm, rather than treating every stained area of the section as equally informative (general IHC practice).
Faint cytoplasmic staining in germinal center or hematopoietic cells.Low staining is reported for lymph node germinal center cells and bone marrow hematopoietic cells (HPA tissue IHC). A faint result there can fit the reference pattern; compare it with the stronger kidney tubular example before calling the assay negative (HPA tissue IHC).
Predominantly nuclear or sharply membranous staining.That distribution conflicts with the cytoplasmic and endoplasmic reticulum annotation and the absence of a transmembrane segment (UniProt P09913). Treat it as unresolved staining and check controls before assigning it to IFIT2 (general IHC practice).
Strong staining in a listed negative cell population.Adipocytes in adipose tissue and respiratory epithelial cells in bronchus are reported as Not detected (HPA tissue IHC). Strong signal in either population warrants checks for cross-reactivity or endogenous chromogenic detection activity; the slide alone cannot distinguish those causes (general IHC practice).
Uniform color across cells, stroma and section edges.A pattern that ignores cell boundaries is less persuasive than cell-associated cytoplasmic staining (HPA tissue IHC; general IHC practice). Review a no-primary control and the distribution of chromogen before scoring the section as IFIT2 positive (general IHC practice).
💡Expected IFIT2 appearanceCall a result positive when kidney tubular cells show high cytoplasmic staining (HPA tissue IHC); predominantly nuclear staining or uniform color across tissue is an unresolved result (UniProt P09913; general IHC practice).
How each factor affects the staining
Tissue and cell selectionKidney tubular cells provide the supplied high-staining reference; lymph node germinal center cells and bone marrow hematopoietic cells are low, while several listed populations are Not detected (HPA tissue IHC). Select and score the stated cell population, not the tissue name alone (general IHC practice).
Strength of the tissue evidenceThe antibody's IHC status is Approved, yet HPA reports very low consistency between staining and RNA expression (HPA tissue IHC). Use the observed pattern as a comparison point; confirm unexpected staining with appropriate controls before interpreting it biologically (general IHC practice).
Topology and processingIFIT2 has no transmembrane segment, signal peptide or propeptide in the supplied record (UniProt P09913). Those annotations support an intracellular interpretation; they supply no target-specific antigen-retrieval setting or fixation-sensitivity claim (UniProt P09913).
IF/ICC: should vesicular puncta count?Yes, vesicles are the approved main ICC-IF location (HPA subcellular). UniProt also annotates cytoplasm and endoplasmic reticulum (UniProt P09913). Read puncta within the IF/ICC context; the ICC-IF observation does not require visibly resolved vesicles in chromogenic paraffin-section IHC (HPA subcellular; general IHC practice).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Kidney tubular cells have no discernible signal.This disagrees with the reported High staining, but a failed assay cannot be inferred from one section alone (HPA tissue IHC; general IHC practice).Check tissue preservation, section handling, the established IHC-P retrieval and antibody steps, and detection controls; repeat with a suitable positive section (general IHC practice).
Signal is nuclear or concentrated at cell borders.The dominant compartment differs from the supplied cytoplasm and endoplasmic reticulum annotation (UniProt P09913).Compare with a no-primary control and a positive reference section; withhold a specific IFIT2 call if the discordant pattern persists (general IHC practice).
Listed negative cells stain strongly.Staining in adipose-tissue adipocytes or bronchial respiratory epithelium conflicts with their Not detected entries (HPA tissue IHC). Cross-reactivity or endogenous detection activity remains possible (general IHC practice).Run no-primary and detection controls, inspect which cell population carries the color, and avoid treating the unexpected signal as confirmed IFIT2 (general IHC practice).
Color appears throughout the section.Diffuse background can obscure the cell-associated cytoplasmic pattern reported for IFIT2 (HPA tissue IHC; general IHC practice).Inspect no-primary controls; review blocking, washing, antibody concentration and chromogen development within the established IHC workflow (general IHC practice).
Lymph node or bone marrow looks weak beside kidney.Low staining is reported in germinal center and hematopoietic cells, whereas kidney tubular cells are High (HPA tissue IHC).Score the named cells and compare like-for-like sections; do not impose the kidney intensity threshold on these low-staining populations (HPA tissue IHC; general IHC practice).
IHC staining and RNA evidence disagree.HPA explicitly reports very low consistency between antibody staining and RNA expression despite its Approved IHC rating (HPA tissue IHC).Record the discrepancy and seek independent confirmation before making a tissue-specific expression claim; do not use the IHC rating alone to resolve it (HPA tissue IHC; general IHC practice).

Sample controls for IFIT2 IHC & IF

🧪Run kidney first; tubular cells should stain strongly (HPA: High in kidney cells in tubules). Use adipose tissue as a negative tissue (HPA: Not detected in adipocytes); on the kidney slide, assess other cell types for staining below the tubular signal, without assuming they are negative because HPA does not annotate them (HPA: kidney cells in tubules High).
Positive control tissue: Kidney (Cells in tubules, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show IFIT2 in A-431, HeLa, U2OS, with annotated localisation: Vesicles (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and host-matched rabbit IgG isotype controls, plus IFIT2-knockout material as a biological negative (caption: rabbit anti-IFIT2 primary; standard IHC practice). For chromogenic kidney sections, quench endogenous peroxidase and check tubular background; if using avidin–biotin detection, control for endogenous biotin (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A04428-1 tissue-IHC caption does not state a fixative (caption: fixative not stated). That paraffin-section example used heat retrieval in EDTA at pH 8.0, but whether IFIT2 staining depends on that retrieval condition is unreported (caption: EDTA pH 8.0 heat retrieval). The supplied evidence does not establish that frozen sections or IF are easier; kidney tubules may require care with endogenous biotin if avidin–biotin detection is used (standard IHC practice).

HPA tissue IHC evidence for IFIT2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Very low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Kidney Cells in tubules High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced IFIT2 IHC Tips

Troubleshoot IFIT2 staining in paraffin sections by checking retrieval, compartment, cell type and controls before comparing chromogenic signal across samples.

How should I retrieve IFIT2 in paraffin sections when staining is weak?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin-section IHC (datasheet A04428-1). The selected image used this retrieval before overnight incubation at 4°C with 2 μg/ml catalog antibody (datasheet A04428-1). If signal is weak, compare a small series of heating times, such as 10 and 20 minutes, while keeping the detection steps identical (standard IHC practice). Include kidney tubules as a reference with reported high staining, but assess them alongside a negative control because staining and RNA data show very low consistency (HPA: High in kidney tubules; HPA: very low consistency). Excessive heating can damage section morphology, so choose the shortest condition that preserves interpretable cells (standard IHC practice).
Can fixation explain inconsistent IFIT2 staining between paraffin blocks?
Target-specific sensitivity to fixation is unknown; the selected paraffin-section caption does not state a fixative (datasheet A04428-1). Record each block's fixative and fixation duration, then compare sections processed with the same EDTA pH 8.0 retrieval and detection conditions (datasheet A04428-1; standard IHC practice). If formalin was used, prolonged exposure can mask epitopes in general, so compare controlled processing groups before changing retrieval (standard IHC practice). Use an adjacent section to check whether weak staining tracks poor preservation or tissue loss rather than the expected cytoplasmic pattern (UniProt P09913; standard IHC practice). Do not assign a fixation effect to IFIT2 without a matched experiment (standard IHC practice).
Where should convincing IFIT2 chromogenic staining appear?
Evaluate staining primarily in the cytoplasm, with possible association with the endoplasmic reticulum (UniProt P09913). IFIT2 has no annotated transmembrane segment, so a sharp cell-surface rim alone warrants scrutiny rather than a membrane score (UniProt P09913 topology; standard IHC practice). HPA reports cytoplasmic expression in immune cells and high staining in kidney tubule cells, making cell identity important when scoring mixed tissue (HPA tissue IHC). Its separate ICC/IF record reports vesicles; use that observation as context, not as proof that every chromogenic section must look punctate (HPA subcellular: Vesicles). Compare the pattern with morphology and a negative control under the same DAB exposure (standard IHC practice).
Could isoforms or processing explain a changed IFIT2 staining pattern?
The supplied record lists 0 isoforms and no signal peptide or propeptide, so it provides no named splice variant or cleaved precursor to explain a staining shift (UniProt P09913). It lists a chain spanning residues 2–472 and an example N-terminal acetylation at residue 2, but the antibody's recognized epitope is not supplied (UniProt P09913; datasheet A04428-1). Do not attribute loss of staining to that modification without epitope mapping or a direct comparison (standard IHC practice). Keep EDTA retrieval at pH 8.0 constant while testing antibody concentration and controls (datasheet A04428-1; standard IHC practice). Concordant staining with an independently validated epitope would strengthen an epitope-specific interpretation (standard IHC practice).
How can IF complement the IFIT2 chromogenic IHC result?
Use IF as a separate localization check, and multiplex IFIT2 with a validated marker for the expected cell type; HPA reports cytoplasmic staining in immune cells (HPA tissue IHC; standard IF practice). Choose fluorophores after measuring the tissue's unstained autofluorescence, favoring a spectrally distinct channel for a weak IFIT2 signal (standard IF practice). Because IFIT2 is cytoplasmic and associated with endoplasmic reticulum, permeabilize for intracellular antibody access; a short 0.1% Triton X-100 trial is a general IF starting condition (UniProt P09913; standard IF practice). Its lack of a transmembrane segment does not establish an ER luminal epitope (UniProt P09913 topology). Compare puncta with the reported vesicular ICC/IF pattern, while treating the paraffin-section EDTA protocol as IHC evidence only (HPA subcellular: Vesicles; datasheet A04428-1).
How do I reduce diffuse DAB background without losing IFIT2 signal?
First compare the tissue with a no-primary control and inspect whether background follows tissue edges, folds or areas of poor morphology (standard IHC practice). Block endogenous peroxidase before HRP detection, and use matched blocking and wash steps when comparing sections (standard IHC practice). The selected paraffin-section image used 10% goat serum, 2 μg/ml primary antibody overnight at 4°C, and DAB detection (datasheet A04428-1). If background persists, titrate the primary downward and shorten DAB development while retaining a reference section in the same run (standard IHC practice). Judge improvement by cytoplasmic cellular staining, not a uniformly darker field (UniProt P09913; standard IHC practice).
What is a defensible way to quantify IFIT2 IHC across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population before measuring signal, because the reported IHC pattern includes cytoplasmic immune-cell staining and high staining in kidney tubules (HPA tissue IHC; standard IHC practice). For a defined population, record the percentage of positive cells and an intensity-based H-score from 0–300 using consistent thresholds (standard IHC practice). For scattered positive cells, report their density per mm² of viable tissue and identify the compartment being counted (standard IHC practice). Normalize counts to viable tissue area or the number of eligible cells, excluding folds and necrosis by a prespecified rule (standard IHC practice). Interpret small differences cautiously because HPA reports very low consistency between antibody staining and RNA expression (HPA tissue IHC).
What separates credible IFIT2 staining from artefact in a positive section?
A credible result has cellular cytoplasmic staining in an identified cell population, consistent with the recorded IFIT2 location and tissue IHC profile (UniProt P09913; HPA tissue IHC). Compare kidney tubules, reported as high, with a no-primary control and with adipocytes, reported as not detected, while accounting for each specimen's processing (HPA tissue IHC; standard IHC practice). Flag isolated nuclear or sharp membrane-only signal, edge-heavy staining and staining confined to necrosis for review against morphology (UniProt P09913 topology; standard IHC practice). Endogenous peroxidase can also produce misleading DAB signal, so verify that the peroxidase block and no-primary control behave as expected (standard IHC practice). Avoid treating RNA agreement as confirmation: HPA rates its staining-to-RNA consistency very low (HPA tissue IHC).
Boster reagents

Best IFIT2 / Interferon-induced protein with tetratricopeptide repeats 2 IHC Antibodies

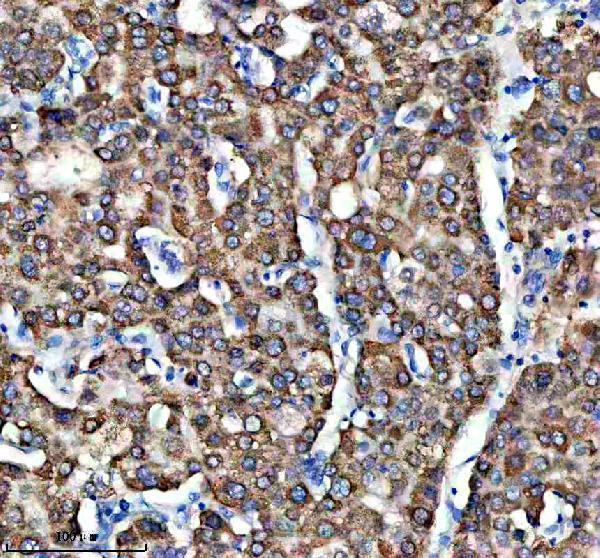
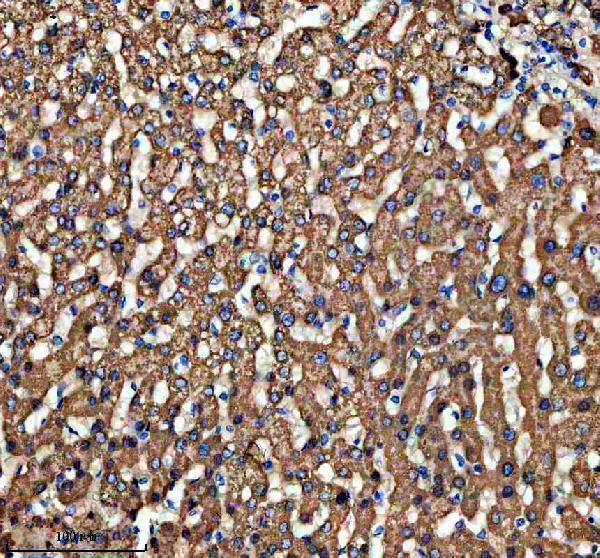
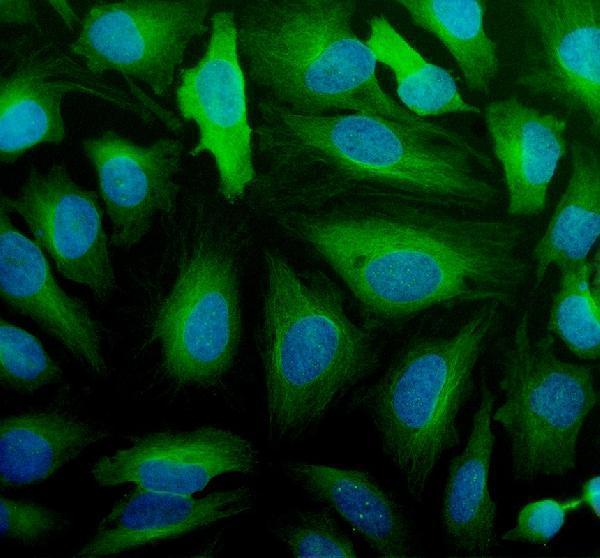
The catalog antibody has IHC data from human paraffin sections and IF/ICC data from HeLa cells (catalog image captions); its listed reactivity is human, mouse and rat (catalog reactivity).

Real IHC data IHC analysis of IFIT2 using anti-IFIT2 antibody (A04428-1). IFIT2 was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-IFIT2 Antibody (A04428-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-IFIT2 Antibody ®
Cat # A04428-1

A04428-1 has IHC images of human liver cancer, liver and skin cancer paraffin sections (catalog IHC image captions). It also has an IF/ICC image of HeLa cells (catalog IF image caption) and lists human, mouse and rat reactivity (catalog reactivity).

Which to pick: Choose A04428-1 for tissue IHC: its caption documents human paraffin sections with EDTA retrieval at pH 8.0 and DAB detection; the fixative is unreported (catalog IHC image captions). The same SKU is listed for IF/ICC and has a HeLa cell IF image (catalog applications; catalog IF image caption). For work across species, its listed reactivity covers human, mouse and rat, while the supplied IHC and IF images show human samples only (catalog reactivity; catalog image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P09913 (IFIT2_HUMAN, Interferon-induced protein with tetratricopeptide repeats 2).
  2. Human Protein Atlas. IFIT2 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. IFIT2 subcellular location (ICC-IF): Localized to vesicles..
  4. Human Protein Atlas. IFIT2 antibody validation summary (1 antibodies).
  5. Clinical significance of IFIT2 expression in human renal cancer tissues. Translational cancer research 2020 — PMC8797327.
  6. Decreased IFIT2 Expression In Human Non-Small-Cell Lung Cancer Tissues Is Associated With Cancer Progression And Poor Survival Of The Patients. OncoTargets and therapy 2019 — PMC6781603.
  7. MicroRNA-645, up-regulated in human adencarcinoma of gastric esophageal junction, inhibits apoptosis by targeting tumor suppressor IFIT2. BMC cancer 2014 — PMC4161885.
  8. METTL3/m(6)A/IFIT2 regulates proliferation, invasion and immunity in esophageal squamous cell carcinoma. Frontiers in pharmacology 2022 — PMC9644211.
  9. PubMed PMID:3466167 — UniProt-cited evidence.
  10. PubMed PMID:15164054 — UniProt-cited evidence.
  11. PubMed PMID:2454816 — UniProt-cited evidence.