This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
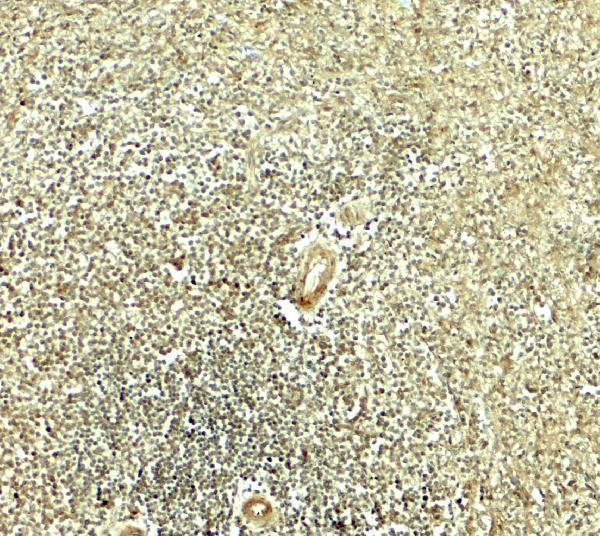
Plan paraffin-section IKZF2 IHC around the expected nuclear staining pattern (HPA tissue IHC). The catalog antibody has a human spleen IHC image at 5 μg/mL (datasheet).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear staining in tissue (HPA tissue IHC) | |
| Staining pattern | General nuclear staining (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Bone marrow+2 more · see all |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Nuclear positivity alone does not identify Tregs (HPA tissue IHC; UniProt) | |
| Regulation | Expressed in activated T cells (UniProt) | |
| Isoform / epitope | 8 isoforms; confirm epitope coverage (UniProt) |
The catalog antibody's IHC-P protocol is followed by published chromogenic IHC methods for IKZF2 in cutaneous T cell lymphoma and gastric cancer sections (PMC9472098; PMC7555661).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A05228); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-IKZF2, 5 μg/mL (datasheet A05228) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | IKZF2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control. |
IKZF2 is a nuclear transcription factor with no transmembrane segment (UniProt Q9UKS7). In paraffin-section IHC, assess nuclear staining in the relevant cells: HPA reports high staining in several glandular, respiratory epithelial, endothelial, and stromal cell populations, alongside tissue-enhanced RNA expression in lymphoid tissue (HPA tissue IHC). HPA describes its tissue IHC profile as general nuclear expression, with Approved reliability and medium consistency between antibody staining and RNA data (HPA tissue IHC).
| Distinct nuclear chromogen in the expected cells, with interpretable counterstained nuclei. | This fits the general nuclear tissue IHC profile (HPA tissue IHC) and nuclear localization (UniProt Q9UKS7). Compare cells within the same section before scoring intensity; a positive nucleus supports localization but does not, by itself, identify a T-cell subtype or establish that every cell in that tissue expresses IKZF2. |
| Strong cytoplasm-only, membranous, or extracellular staining, with little nuclear signal. | A cytoplasm-only IHC pattern conflicts with the main nuclear expectation (UniProt Q9UKS7; HPA tissue IHC). Investigate background or nonspecific binding before calling it positive. HPA also reports additional cytosolic localization by ICC-IF, so limited cytosolic signal alone cannot settle whether a particular IHC stain is an artifact (HPA subcellular ICC-IF). |
| Prominent staining in a cell population reported as not detected by HPA. | For example, HPA reports no detection in bone-marrow hematopoietic cells and hippocampal glial cells (HPA tissue IHC). Unexpected staining warrants checks for nonspecific antibody binding or endogenous detection activity (general IHC practice). These observations concern the sampled cell categories; do not extend them to every cell or specimen from either tissue. |
| Chromogen spreads across cells, extracellular spaces, or much of the section without clear nuclear boundaries. | Diffuse deposition prevents a confident nuclear call against the HPA tissue IHC profile (HPA tissue IHC). Uneven reagent coverage, nonspecific binding, or endogenous enzyme activity can produce broad background in chromogenic IHC (general IHC practice). Compare a matched detection-only control and inspect whether the counterstain still separates individual nuclei. |
| No nuclear staining in a section chosen as an HPA high-staining example. | Absence of signal in the relevant cells of that section raises a technical or specimen question before a biological negative call. HPA reports high staining in adrenal-gland glandular cells and bronchial respiratory epithelial cells (HPA tissue IHC). Confirm that the expected cell population is present, then review the staining run with a suitable control (general IHC practice). |
| Subcellular distribution | UniProt places IKZF2 in the nucleus and describes association with centromeric heterochromatin in T-cell nuclei (UniProt Q9UKS7). HPA describes nucleoplasm and nuclear bodies as approved main ICC-IF locations, with additional approved cytosol (HPA subcellular ICC-IF); use the tissue IHC profile for the primary slide call. |
| Choice of comparison tissue and cell population | HPA scores high staining in appendix glandular cells, colon endothelial cells, and endometrial stromal cells, among others (HPA tissue IHC). Match the scored cell type to the tissue entry: a tissue name alone does not make every cell in its section an expected positive. |
| Expression context | UniProt reports IKZF2 expression in developing thymocytes, activated T cells, regulatory T cells, and MAIT cells (UniProt Q9UKS7). HPA also reports high tissue IHC staining in several non-lymphoid cell categories and tissue-enhanced RNA expression in lymphoid tissue (HPA tissue IHC). Keep those evidence types distinct when selecting controls or interpreting mixed sections. |
| Antibody evidence | HPA lists HPA059142 as Approved for IHC and ICC, while its tissue IHC summary reports medium consistency with RNA expression (HPA antibodies; HPA tissue IHC). Treat this as support for the documented patterns, with the stated reliability limit; the supplied record does not establish an Enhanced IHC validation designation. |
| Isoforms and modifications | UniProt lists eight IKZF2 isoforms and annotated phosphoserines and an acetyllysine (UniProt Q9UKS7). The supplied evidence gives no antibody epitope or isoform coverage, so an IHC intensity difference cannot be assigned to a particular isoform or modification from these records alone. |
| Topology and processing | UniProt reports no transmembrane segment, signal peptide, or propeptide, and describes one chain spanning residues 1–526 (UniProt Q9UKS7). This supports assessing a nuclear protein rather than expecting a cell-surface outline; the supplied record does not support a shedding-based explanation for extracellular chromogen. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive cells are present, but their nuclei are unstained. | The result may reflect the staining run or specimen; the high-staining HPA entry alone cannot identify the failure step (HPA tissue IHC). | Check a suitable positive control and the detection-only control, then review antigen retrieval and reagent performance using the established paraffin IHC workflow (general IHC practice). |
| The apparent positive result is mainly cytoplasmic. | It does not match the general nuclear tissue IHC profile (HPA tissue IHC), although additional cytosol is reported in ICC-IF (HPA subcellular ICC-IF). | Check for nuclear signal in the same cells and compare matched controls; report the compartment actually observed rather than assigning a nuclear positive score (general IHC practice). |
| Unexpected cells stain strongly beside plausible positive cells. | Nonspecific binding or endogenous detection activity may imitate a positive chromogenic signal (general IHC practice); HPA cell-level patterns vary within and across tissues (HPA tissue IHC). | Identify the stained cell population, compare it with the matching HPA entry, and inspect a detection-only control before attributing the signal to IKZF2 (general IHC practice). |
| Background obscures nuclear boundaries across the section. | Diffuse chromogen makes comparison with the HPA general nuclear pattern unreliable (HPA tissue IHC); nonspecific binding or endogenous enzyme activity are possible causes (general IHC practice). | Review blocking, wash steps, detection chemistry, and counterstain visibility; use a matched detection-only control to locate background introduced by the staining workflow (general IHC practice). |
| Two specimens give different proportions of stained nuclei. | A change in sampled cell populations could alter the apparent result; HPA assigns levels to specified cells, and reports medium consistency between tissue staining and RNA data (HPA tissue IHC). | Score the same identifiable cell population in each specimen and record nuclear intensity and the fraction of stained cells separately (general IHC practice). Do not infer an isoform or modification change from intensity alone (UniProt Q9UKS7). |
| IF/ICC Q&A: Should cytosolic fluorescence override a nuclear paraffin IHC interpretation? | HPA approves nucleoplasm and nuclear bodies as main ICC-IF locations and cytosol as an additional location (HPA subcellular ICC-IF); it describes general nuclear expression in tissue IHC (HPA tissue IHC). | Interpret each preparation against its own documented pattern and controls. For paraffin IHC, base the positive call on identifiable nuclear staining in the relevant cells (HPA tissue IHC; general IHC practice). |
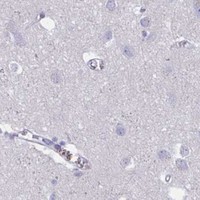


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Cervix | Glandular cells | High | Protein (IHC) | HPA → |
Troubleshoot IKZF2 staining by checking retrieval, nuclear signal, controls, and cell-specific scoring before interpreting chromogenic IHC.
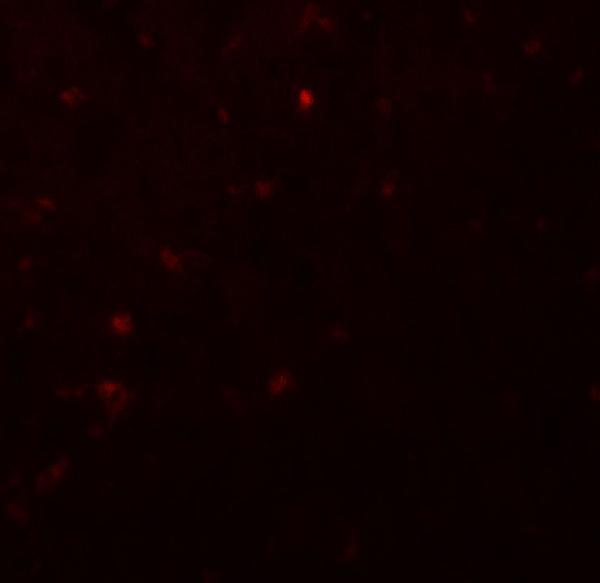
The catalog antibody has IHC and IF images from human spleen (catalog image captions); Human, Mouse and Rat reactivity is listed (catalog: A05228 reactivity).
A05228 is listed for IHC-P and IF (catalog: A05228 applications). Its images show human spleen IHC at 5 μg/mL and IF at 20 μg/mL (catalog: A05228 image captions).
Which to pick: For paraffin-section IHC, choose A05228: IHC-P is listed, and its own IHC caption shows human spleen at 5 μg/mL (catalog: A05228 applications and IHC image caption); the fixative is unreported (catalog: A05228 IHC image caption). For IF, A05228 has a human spleen image at 20 μg/mL (catalog: A05228 IF image caption); ICC is not listed (catalog: A05228 applications). For Mouse or Rat samples, A05228 lists reactivity in both species (catalog: A05228 reactivity), while the supplied IHC and IF images show Human tissue (catalog: A05228 image captions).