IMPDH1 / Inosine-5'-monophosphate dehydrogenase 1 · IHC design guide

Design Immunohistochemistry for IMPDH1

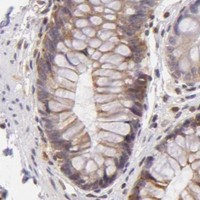
Plan IMPDH1 chromogenic IHC around cytoplasmic and nuclear tissue staining (HPA tissue IHC). Use the catalog antibody at 2–5 μg/ml (datasheet: A03791-1), with spermatogonia as a high-staining control and skeletal muscle myocytes as a negative control (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for IMPDH1 (IHC for IMPDH1): expected localisation Cytoplasmic and nuclear staining in several tissues (HPA tissue IHC), antibody A03791-1, validated IHC image, and IHC protocol steps
Printable IMPDH1 IHC protocol sheet — expected localisation Cytoplasmic and nuclear staining in several tissues (HPA tissue IHC), antibody A03791-1, controls and protocol steps. Open the full IMPDH1 IHC guide →

IMPDH1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear staining in several tissues (HPA tissue IHC)
Staining pattern Cells in several tissues show cytoplasmic and nuclear staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03791-1)
Positive control ⓘ Testis+4 more · see all
Negative control ⓘ Skeletal muscle
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A03791-1)
Caveat Staining may reflect proteins from more than one gene (HPA tissue IHC)
Regulation Type II predominates over type I in tumors (UniProt)
Isoform / epitope 7 isoforms; check antibody epitope coverage (UniProt)
Section 1

Recommended IMPDH1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet A03791-1) with four published IMPDH1 chromogenic IHC protocols (PMC9945078; PMC10197894; PMC9102537; PMC9733023).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A03791-1)
FixationImage fixative and duration unreported (datasheet A03791-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03791-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03791-1)
Primary antibodyRabbit anti-IMPDH1, 2-5 μg/ml (datasheet A03791-1)
Primary incubationOvernight at 4 °C (datasheet A03791-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03791-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultIMPDH1-positive staining in spermatogonia cells of testis (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and nuclear expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet A03791-1). Use the cited paper’s retrieval conditions when reproducing its protocol.
Section 2

What Is the Expected IMPDH1 Staining Pattern?

IMPDH1 is assigned to the cytoplasm and nucleus, with no transmembrane segment (UniProt P20839: location and topology). In paraffin-section IHC, expect the strongest listed staining in testis spermatogonia and medium staining in several other cell types (HPA: tissue IHC). Treat this as a guide to the observed pattern, not proof of IMPDH1-specific signal: HPA rates the tissue profile Approved with medium RNA agreement and cautions that the antibody targets proteins from more than one gene (HPA: tissue IHC).

What am I looking at on my slide?
Strong intracellular staining in spermatogonia.This matches the highest listed tissue result (HPA: High in testis spermatogonia). Assess cytoplasmic and nuclear signal separately, since both compartments are reported for IMPDH1 (UniProt P20839: location; HPA: tissue IHC profile).
Moderate intracellular staining in adipocytes or bronchial respiratory epithelial cells.These are plausible positive patterns (HPA: Medium in adipose adipocytes and bronchial respiratory epithelial cells). Compare like cells, rather than averaging stain across the section; an unstained neighboring cell population does not negate a cell-specific positive result (standard IHC interpretation).
Predominantly membrane-edge, extracellular, or tissue-border staining.This distribution does not fit the reported cytoplasmic and nuclear pattern or the absence of a transmembrane segment (UniProt P20839: location and topology; HPA: tissue IHC profile). Check morphology and detection controls before scoring it as target staining (standard IHC practice).
Strong staining in skeletal muscle myocytes.This conflicts with the listed myocyte result (HPA: Not detected in skeletal muscle myocytes). Consider nonspecific antibody binding or endogenous detection activity; the HPA multi-gene targeting caution also limits attribution of a positive stain to IMPDH1 alone (HPA: tissue IHC reliability).
Uniform haze across cells, stroma, and empty areas, or no stain in testis spermatogonia.Neither is an interpretable positive pattern: spermatogonia are listed High (HPA: tissue IHC). Broad haze suggests background, while an absent positive control calls for a check of staining and detection conditions before interpreting a negative specimen (standard IHC practice).
💡Expected IMPDH1 appearanceA convincing chromogenic positive shows intracellular cytoplasmic and/or nuclear staining in identifiable spermatogonia at the highest listed level (HPA: High in testis spermatogonia; HPA: cytoplasmic and nuclear tissue profile); diffuse deposits outside cells or strong skeletal-muscle myocyte staining warrant investigation (HPA: myocytes Not detected; standard IHC interpretation).
How each factor affects the staining
Cell type and tissue selectionTestis spermatogonia provide a listed High reference; adipocytes, respiratory epithelial cells, and several other listed populations are Medium (HPA: tissue IHC). Skeletal-muscle myocytes are listed Not detected, making them a useful pattern comparison within the limits of the HPA assay (HPA: tissue IHC).
Compartment and topologyCytoplasm and nucleus are reported locations, and no transmembrane segment is annotated (UniProt P20839: location and topology). Score intracellular compartments explicitly; a membrane-only pattern needs independent scrutiny rather than automatic acceptance as IMPDH1 staining (standard IHC interpretation).
Antibody attributionThe tissue IHC profile is Approved but has medium consistency with RNA data and a multi-gene targeting caution (HPA: tissue IHC reliability). An expected tissue pattern supports assay plausibility; it does not by itself identify which protein produced every stained pixel (HPA: tissue IHC reliability).
Isoforms and mapped epitopeSeven isoforms are listed, but this payload gives no antibody epitope or isoform coverage (UniProt P20839: isoforms; HPA: HPA001400 validation). Do not assign an isoform from a stained section or explain a negative cell population by isoform loss without additional evidence.
Processing and fixation evidenceThe record lists no signal peptide or propeptide and a chain spanning residues 2–514 (UniProt P20839: processing). These annotations do not predict staining sensitivity after fixation; target-specific fixation effects are unreported in the supplied UniProt and HPA evidence.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Testis spermatogonia are unstained.The listed High reference was not recovered (HPA: testis spermatogonia); the failure point is not established by the image alone.Check tissue identity, retrieval, primary-antibody application, detection reagents, and a run control; then repeat or adjust the general IHC workflow as needed (standard IHC practice).
Every compartment has a weak, even brown haze.Diffuse background can obscure the intracellular pattern expected from the HPA tissue profile (HPA: cytoplasmic and nuclear expression; standard IHC interpretation).Inspect a no-primary control, blocking, washes, and detection-reagent exposure; score only cell-associated signal that rises above the local background (standard IHC practice).
Myocytes stain strongly despite an otherwise plausible section.Skeletal-muscle myocytes are listed Not detected (HPA: tissue IHC); nonspecific binding, endogenous activity, or multi-gene recognition may account for discordance (HPA: reliability caution; standard IHC practice).Compare a no-primary control and the listed positive cells; review blocking and endogenous-activity controls before attributing the myocyte signal to IMPDH1 (standard IHC practice).
Only membrane edges or extracellular deposits are prominent.The distribution conflicts with intracellular locations and the lack of a transmembrane segment (UniProt P20839: location and topology; HPA: tissue IHC profile).Recheck focus and tissue morphology, inspect a no-primary control, and score cytoplasmic and nuclear compartments independently (standard IHC practice).
A negative sample is being called IMPDH1-negative.Absent stain is inconclusive if the run failed to show the listed High spermatogonial reference (HPA: testis spermatogonia; standard IHC interpretation).Require an interpretable positive run control and intact tissue morphology; document the specific cell type and compartment assessed before reporting a negative result (standard IHC practice).
IF/ICC Q&A: Are cytosolic rods and rings an expected finding?HPA reports cytosol as supported and rods and rings as approved in ICC-IF, with a multi-gene antibody caution (HPA: subcellular ICC-IF).They can be an observed IF pattern, but do not infer that every structure is IMPDH1-specific or require rods and rings in paraffin IHC (HPA: subcellular ICC-IF; HPA: tissue IHC).

Sample controls for IMPDH1 IHC & IF

🧪Run testis first and assess staining in spermatogonia (High; HPA: testis), then run skeletal muscle and assess myocytes as the negative tissue (HPA: Not detected in myocytes). Cells on the testis slide that lack specific staining should show only counterstain or background signal; the supplied HPA rows do not identify a particular testicular cell type as an internal negative (HPA: testis row).
Positive control tissue: Testis (Spermatogonia cells, HPA High)
Negative control tissue: Skeletal muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show IMPDH1 in A-431, U-251MG, U2OS, ASC52telo, hTERT-RPE1 (serum starved), with annotated localisation: Cytosol (supported), Rods & Rings (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a rabbit isotype control matched to the primary antibody’s clonality when known, and a validated IMPDH1 knockout or peptide-block control (caption: rabbit primary; standard IHC practice). Check testis sections for endogenous peroxidase background in DAB detection; assess endogenous biotin if using biotin-based detection (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A03791-1 tissue-IHC caption does not state a fixative (caption: fixative not stated). The reported paraffin-section procedure used heat-mediated retrieval in EDTA at pH 8.0, but retrieval dependence beyond that example is unreported (caption: EDTA retrieval). The supplied evidence does not establish whether frozen sections or IF are easier, or identify a testis-specific staining artefact (supplied IHC caption; HPA: testis row).

HPA tissue IHC evidence for IMPDH1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Testis Spermatogonia cells High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Lymphoid tissue Medium Protein (IHC) HPA →
Breast Adipocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Section 3

Advanced IMPDH1 IHC Tips

Troubleshoot IMPDH1 staining in paraffin section chromogenic IHC, then use IF as a separate check of cell identity and localisation.

Which retrieval condition should I start with for IMPDH1 paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A03791-1). The selected tissue image used this condition with 2 μg/ml primary antibody overnight at 4°C, so keep those variables aligned when reproducing it (datasheet A03791-1). If staining is weak, compare retrieval duration on adjacent sections before changing antibody concentration, and inspect tissue integrity after heating (standard IHC practice). Record the heating method and duration because retrieval intensity can change both signal and background (standard IHC practice). Treat any alternative buffer as a fallback to validate with controls, rather than an established IMPDH1 condition (datasheet A03791-1).
How should I troubleshoot fixation when IMPDH1 staining is weak?
The selected IMPDH1 image identifies a paraffin-embedded section but does not state its fixative, so target-specific fixation sensitivity is unknown (datasheet A03791-1). Record fixative, time in fixative, and processing history for each specimen before comparing staining intensity (standard IHC practice). Run sections with different processing histories through the same EDTA pH 8.0 retrieval and detection run, using the selected image conditions as the starting point (datasheet A03791-1; standard IHC practice). Compare preservation of tissue morphology alongside signal, since damaged sections complicate interpretation of weak or diffuse staining (standard IHC practice). Do not attribute a difference to an IMPDH1-specific fixation effect without a controlled comparison (datasheet A03791-1).
Is nuclear IMPDH1 staining plausible, and how should I assess it?
Score cytoplasmic and nuclear staining separately because both compartments are listed for IMPDH1 (UniProt P20839 subcellular location). HPA tissue IHC also reports cytoplasmic and nuclear expression across several tissues, but its staining has only medium consistency with RNA data and may recognize proteins from more than one gene (HPA tissue IHC). Inspect matched controls for diffuse nuclear DAB, especially where counterstain or heavy development makes compartments hard to distinguish (standard IHC practice). Use cell boundaries and nuclear counterstain to define scoring regions, and document any mixed pattern rather than collapsing it into one intensity value (standard IHC practice). A compartment pattern alone cannot establish antibody specificity (HPA tissue IHC).
Can this antibody distinguish IMPDH1 isoforms or modified epitopes in sections?
Do not assign an isoform from chromogenic staining alone: UniProt lists 7 IMPDH1 isoforms, and the supplied image does not map the antibody epitope (UniProt P20839 isoforms; datasheet A03791-1). IMPDH1 contains two CBS domains at residues 114–173 and 179–237, plus reported modifications at residues 160, 341, and 355 (UniProt P20839 domains and modified residues). Whether these features affect this antibody's tissue staining is unestablished because its epitope is not supplied (datasheet A03791-1). Ask for an epitope map or compare independently validated reagents before interpreting staining differences as isoform-specific (standard IHC practice). HPA additionally cautions that its tissue antibodies can target proteins from more than one gene (HPA tissue IHC).
How can IF help check IMPDH1 cell identity and compartment staining?
For a separate IF experiment, multiplex IMPDH1 with a marker identifying the expected cell population, such as spermatogonia in testis, where HPA reports high tissue IHC staining (HPA tissue IHC). Choose a fluorophore in a channel with low measured tissue autofluorescence, and include single-channel and no-primary controls when assessing colocalisation (standard IF practice). IMPDH1 has no transmembrane segment and is reported in cytoplasm and nucleus, so optimise permeabilisation for access to cytosolic or nuclear epitopes, then check that cell structure remains intact (UniProt P20839 topology and subcellular location; standard IF practice). Interpret rod-and-ring patterns cautiously because the HPA IF localisation annotation carries a cross-gene antibody warning (HPA subcellular).
What should I change when DAB obscures IMPDH1 staining?
Start by checking a no-primary section and the distribution of DAB before judging IMPDH1 signal (standard IHC practice). The selected tissue image used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, an anti-rabbit peroxidase secondary for 30 minutes at 37°C, and DAB development (datasheet A03791-1). Include a peroxidase block in the chromogenic workflow and verify that it reduces endogenous enzyme signal (standard IHC practice). If background persists, titrate primary antibody or shorten DAB development while holding retrieval and controls constant (standard IHC practice). Distinguish diffuse staining from the reported cytoplasmic or nuclear pattern before calling a section positive (UniProt P20839 subcellular location; standard IHC practice).
How should I quantify IMPDH1 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and viable tissue area before scoring, and keep acquisition and DAB development settings consistent across sections (standard IHC practice). For intensity scoring, calculate an H-score from percentages at intensities 0–3, giving a 0–300 range; report cytoplasmic and nuclear scores separately (standard IHC practice; UniProt P20839 subcellular location). Alternatively, report percent positive cells or positive-cell density per mm², with thresholds set using control sections (standard IHC practice). Normalise counts to the relevant nucleated cell population or viable area, and record excluded necrotic regions (standard IHC practice). Avoid treating HPA staining as an absolute calibration standard because its tissue antibody annotation warns of cross-gene recognition (HPA tissue IHC).
Which staining patterns would make an IMPDH1 result questionable?
A credible result should have interpretable cytoplasmic or nuclear cell staining, the compartments reported for IMPDH1, with low signal in the no-primary control (UniProt P20839 subcellular location; standard IHC practice). HPA reports high staining in testis spermatogonia and no detection in skeletal muscle myocytes, useful comparison populations when those tissues are available (HPA tissue IHC). Treat staining confined to section edges, necrotic regions, or sites of endogenous peroxidase activity as suspect until controls resolve it (standard IHC practice). Strong staining restricted to an unexpected compartment or cell population warrants checking morphology, counterstain, and antibody specificity (UniProt P20839 subcellular location; standard IHC practice). HPA's cross-gene warning limits claims that DAB positivity identifies IMPDH1 alone (HPA tissue IHC).
Boster reagents

Best IMPDH1 / Inosine-5'-monophosphate dehydrogenase 1 IHC Antibodies

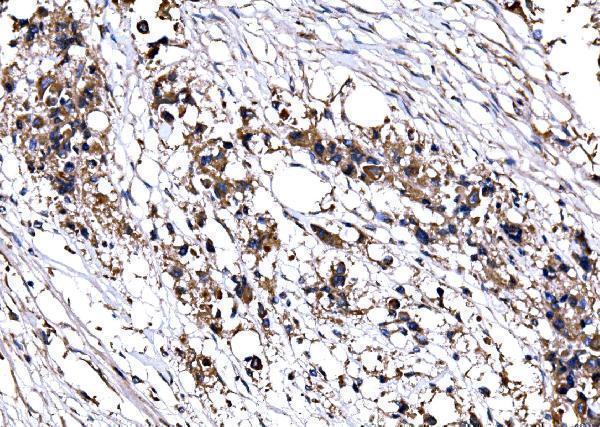
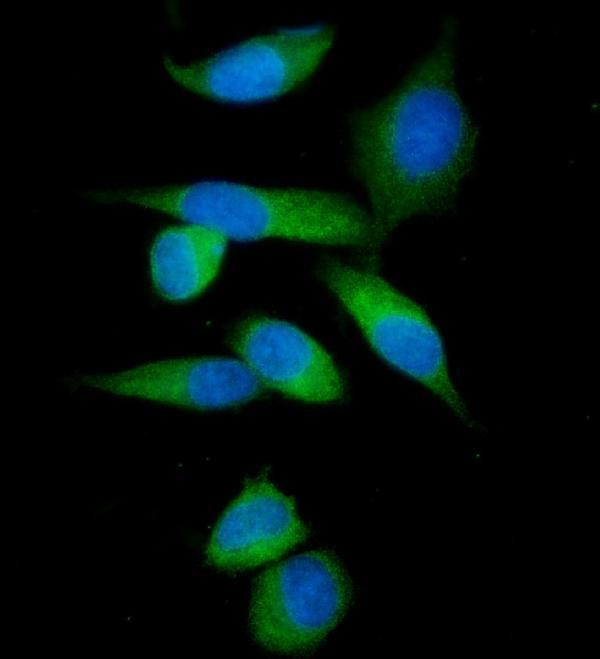
A03791-1 has IHC images from human paraffin sections and IF data from PC-3 cells (catalog image captions); its listed reactivity is human and mouse (catalog reactivity).

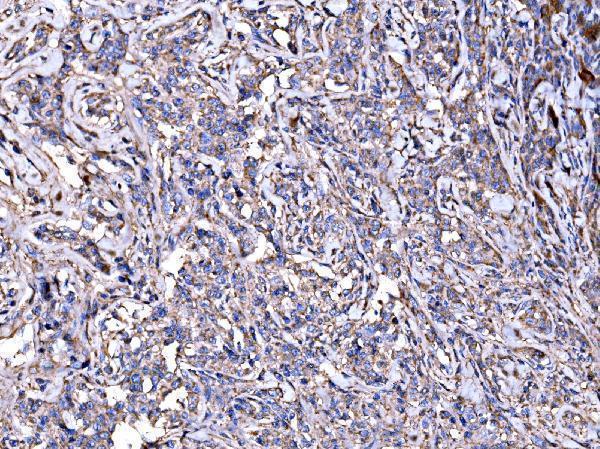
Real IHC data IHC analysis of IMPDH1 using anti-IMPDH1 antibody (A03791-1). IMPDH1 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-IMPDH1 Antibody (A03791-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-IMPDH1 Antibody ®
Cat # A03791-1

A03791-1 is shown in IHC on human paraffin sections of breast cancer, lymphoma, renal cell carcinoma, and ruptured spleen tissue (catalog IHC image captions). The same SKU is shown in IF on PC-3 cells (catalog IF image caption) and lists human and mouse reactivity (catalog reactivity).

Which to pick: Choose A03791-1 for human paraffin-section IHC because its IHC captions document that preparation; the fixative is unreported (catalog IHC image captions). Choose A03791-1 for IF/ICC because those applications are listed and its IF caption shows PC-3 cells (catalog applications; catalog IF image caption). For mouse samples, A03791-1 lists mouse reactivity, but the supplied IHC and IF images show human samples; clonality is unreported (catalog reactivity; catalog image captions; catalog clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P20839 (IMDH1_HUMAN, Inosine-5'-monophosphate dehydrogenase 1).
  2. Human Protein Atlas. IMPDH1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. IMPDH1 subcellular location (ICC-IF): Localized to the cytosol and rods & rings. Caution: Based on antibodies targeting proteins from multiple genes..
  4. Human Protein Atlas. IMPDH1 antibody validation summary (1 antibodies).
  5. Potential prognostic and predictive value of UBE2N, IMPDH1, DYNC1LI1 and HRASLS2 in colorectal cancer stool specimens. Biomedical reports 2023 — PMC9945078.
  6. LncRNA UCA1 Participates in De Novo Synthesis of Guanine Nucleotides in Bladder Cancer by Recruiting TWIST1 to Increase IMPDH1/2. International journal of biological sciences 2023 — PMC10197894.
  7. Inosine monophosphate dehydrogenase type1 sustains tumor growth in hepatocellular carcinoma. Journal of clinical laboratory analysis 2022 — PMC9102537.
  8. MYBL2 regulates de novo purine synthesis by transcriptionally activating IMPDH1 in hepatocellular carcinoma cells. BMC cancer 2022 — PMC9733023.
  9. PubMed PMID:1969416 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:12853948 — UniProt-cited evidence.