This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin section IHC for INHA using its observed cytoplasmic tissue pattern (HPA tissue IHC). Compare adrenal gland, testis and ovary staining while accounting for secretion and processing (HPA tissue IHC; UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining (HPA tissue IHC); secreted protein (UniProt) | |
| Staining pattern | Cytoplasm in adrenal, testis Sertoli and ovarian granulosa cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A02413-3) | |
| Positive control | Adrenal gland+2 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Secretion can separate tissue protein from its RNA source (HPA tissue IHC) | |
| Regulation | Adrenal expression extends in hyperplasia (UniProt) | |
| Isoform / epitope | No isoforms annotated; cleavage yields a mature chain at 233–366 (UniProt) |
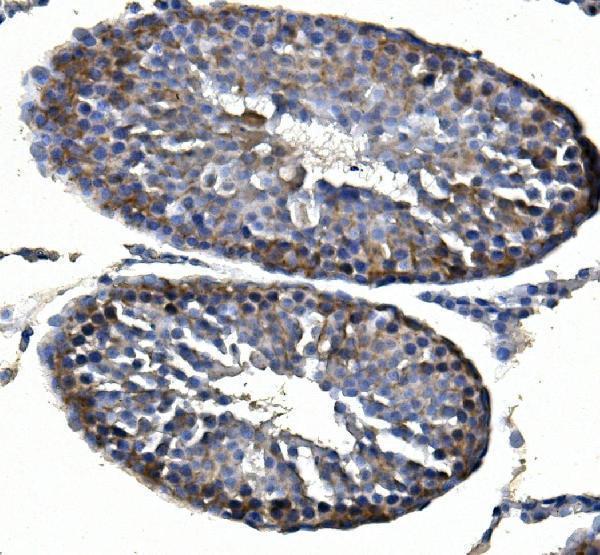
The catalog antibody has an IHC-P protocol (datasheet A02413-3). Two published INHA protocols provide paraffin-section examples from adrenocortical tumors and nasopharyngeal tissues (PMC3777642; PMC11155563).
| Sample | Paraffin-embedded rat testis tissue; fixative not specified (datasheet A02413-3) |
| Fixation | Image fixative and duration unreported (datasheet A02413-3); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A02413-3); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A02413-3) |
| Primary antibody | Rabbit anti-INHA, 2-5μg/ml (datasheet A02413-3) |
| Primary incubation | Overnight at 4 °C (datasheet A02413-3) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet A02413-3) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | INHA-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Distinct cytoplasmic expression in adrenal gland, Sertoli cells in testis and granulosa cells in ovary. No signal in the no-primary control. |
INHA is a secreted protein with no transmembrane segment (UniProt P05111), and HPA reports distinct cytoplasmic IHC staining in adrenal gland, testis and ovary (HPA: Enhanced tissue reliability). Assess the signal in the annotated cells: adrenal glandular cells and testis Leydig cells stain strongly, while ovary follicle cells show medium staining (HPA: tissue IHC). HPA’s profile also describes Sertoli and granulosa cell expression (HPA: tissue IHC profile).
| Strong cytoplasmic staining in adrenal glandular or testis Leydig cells; medium staining in ovary follicle cells (HPA: tissue IHC). | This matches HPA’s cell-level IHC results. Score intensity within the relevant cells and compare it with adjacent tissue; do not treat every cell in a positive organ as an expected positive (HPA: tissue IHC; general IHC practice). |
| Predominantly nuclear or sharply membranous staining, with little cytoplasmic signal. | That distribution conflicts with HPA’s cytoplasmic tissue pattern and UniProt’s secreted, non-transmembrane annotation. Treat it as suspect until controls and an independently validated antibody support it (HPA: tissue IHC; UniProt P05111 topology; general IHC practice). |
| Strong staining in adipocytes or appendix glandular cells. | HPA reports INHA as not detected in those specified cells. Check whether the signal follows cell boundaries or appears in controls before interpreting it as INHA; unexpected staining can reflect cross-reactivity or detection background (HPA: tissue IHC; general IHC practice). |
| Diffuse color across cells and stroma, without a recognizable cellular pattern. | The slide cannot establish the HPA-described cytoplasmic pattern. Review the no-primary control, blocking, washing and chromogen development for nonspecific or endogenous signal before assigning expression (HPA: tissue IHC; general IHC practice). |
| No staining in adrenal glandular cells or testis Leydig cells. | Both are high-staining reference cell populations in HPA’s tissue IHC data. First check that the intended cells are present; then review the antibody, retrieval and detection workflow. An unstained positive control makes a negative test section inconclusive (HPA: tissue IHC; general IHC practice). |
| Cell-level reference pattern | HPA lists high staining in adrenal glandular and testis Leydig cells, and medium staining in ovary follicle cells. Its narrative also names Sertoli and granulosa cells; preserve that distinction when selecting and scoring fields (HPA: tissue IHC). |
| Secretory location | INHA has a signal peptide, is secreted and has no annotated transmembrane segment (UniProt P05111). A cytoplasmic production-site pattern is consistent with HPA tissue IHC; staining alone cannot establish where secreted protein travels (HPA: tissue IHC; UniProt P05111). |
| Protein processing and epitope | UniProt maps the signal peptide to residues 1–18, propeptide regions to 19–232 and the inhibin alpha chain to 233–366. If the antibody epitope is known, compare its location with these regions; the supplied record gives no epitope (UniProt P05111). |
| Glycosylation | Three glycosylation sites are annotated at residues 146, 268 and 302 (UniProt P05111). The supplied evidence does not show whether glycosylation changes staining by the catalog antibody; use the sites only when interpreting a documented epitope (UniProt P05111). |
| Antibody validation | HPA019141 and CAB000047 have Enhanced IHC status; HPA048834 has no listed IHC status (HPA: antibodies). Enhanced supports agreement with independent antibodies or orthogonal data, but each new staining run still needs appropriate controls (HPA: antibody-validation summary; general IHC practice). |
| Retrieval and chromogenic detection | Choose antigen retrieval and detection settings from the IHC-validated antibody’s documented protocol, then verify them with positive and no-primary controls (general IHC practice). No INHA-specific fixation sensitivity or retrieval effect is supplied by HPA or UniProt. |
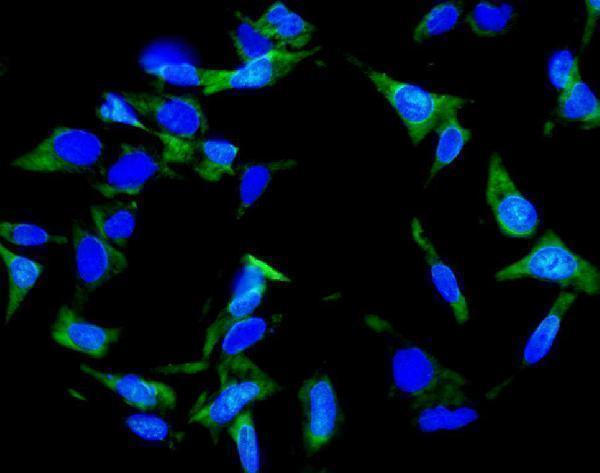
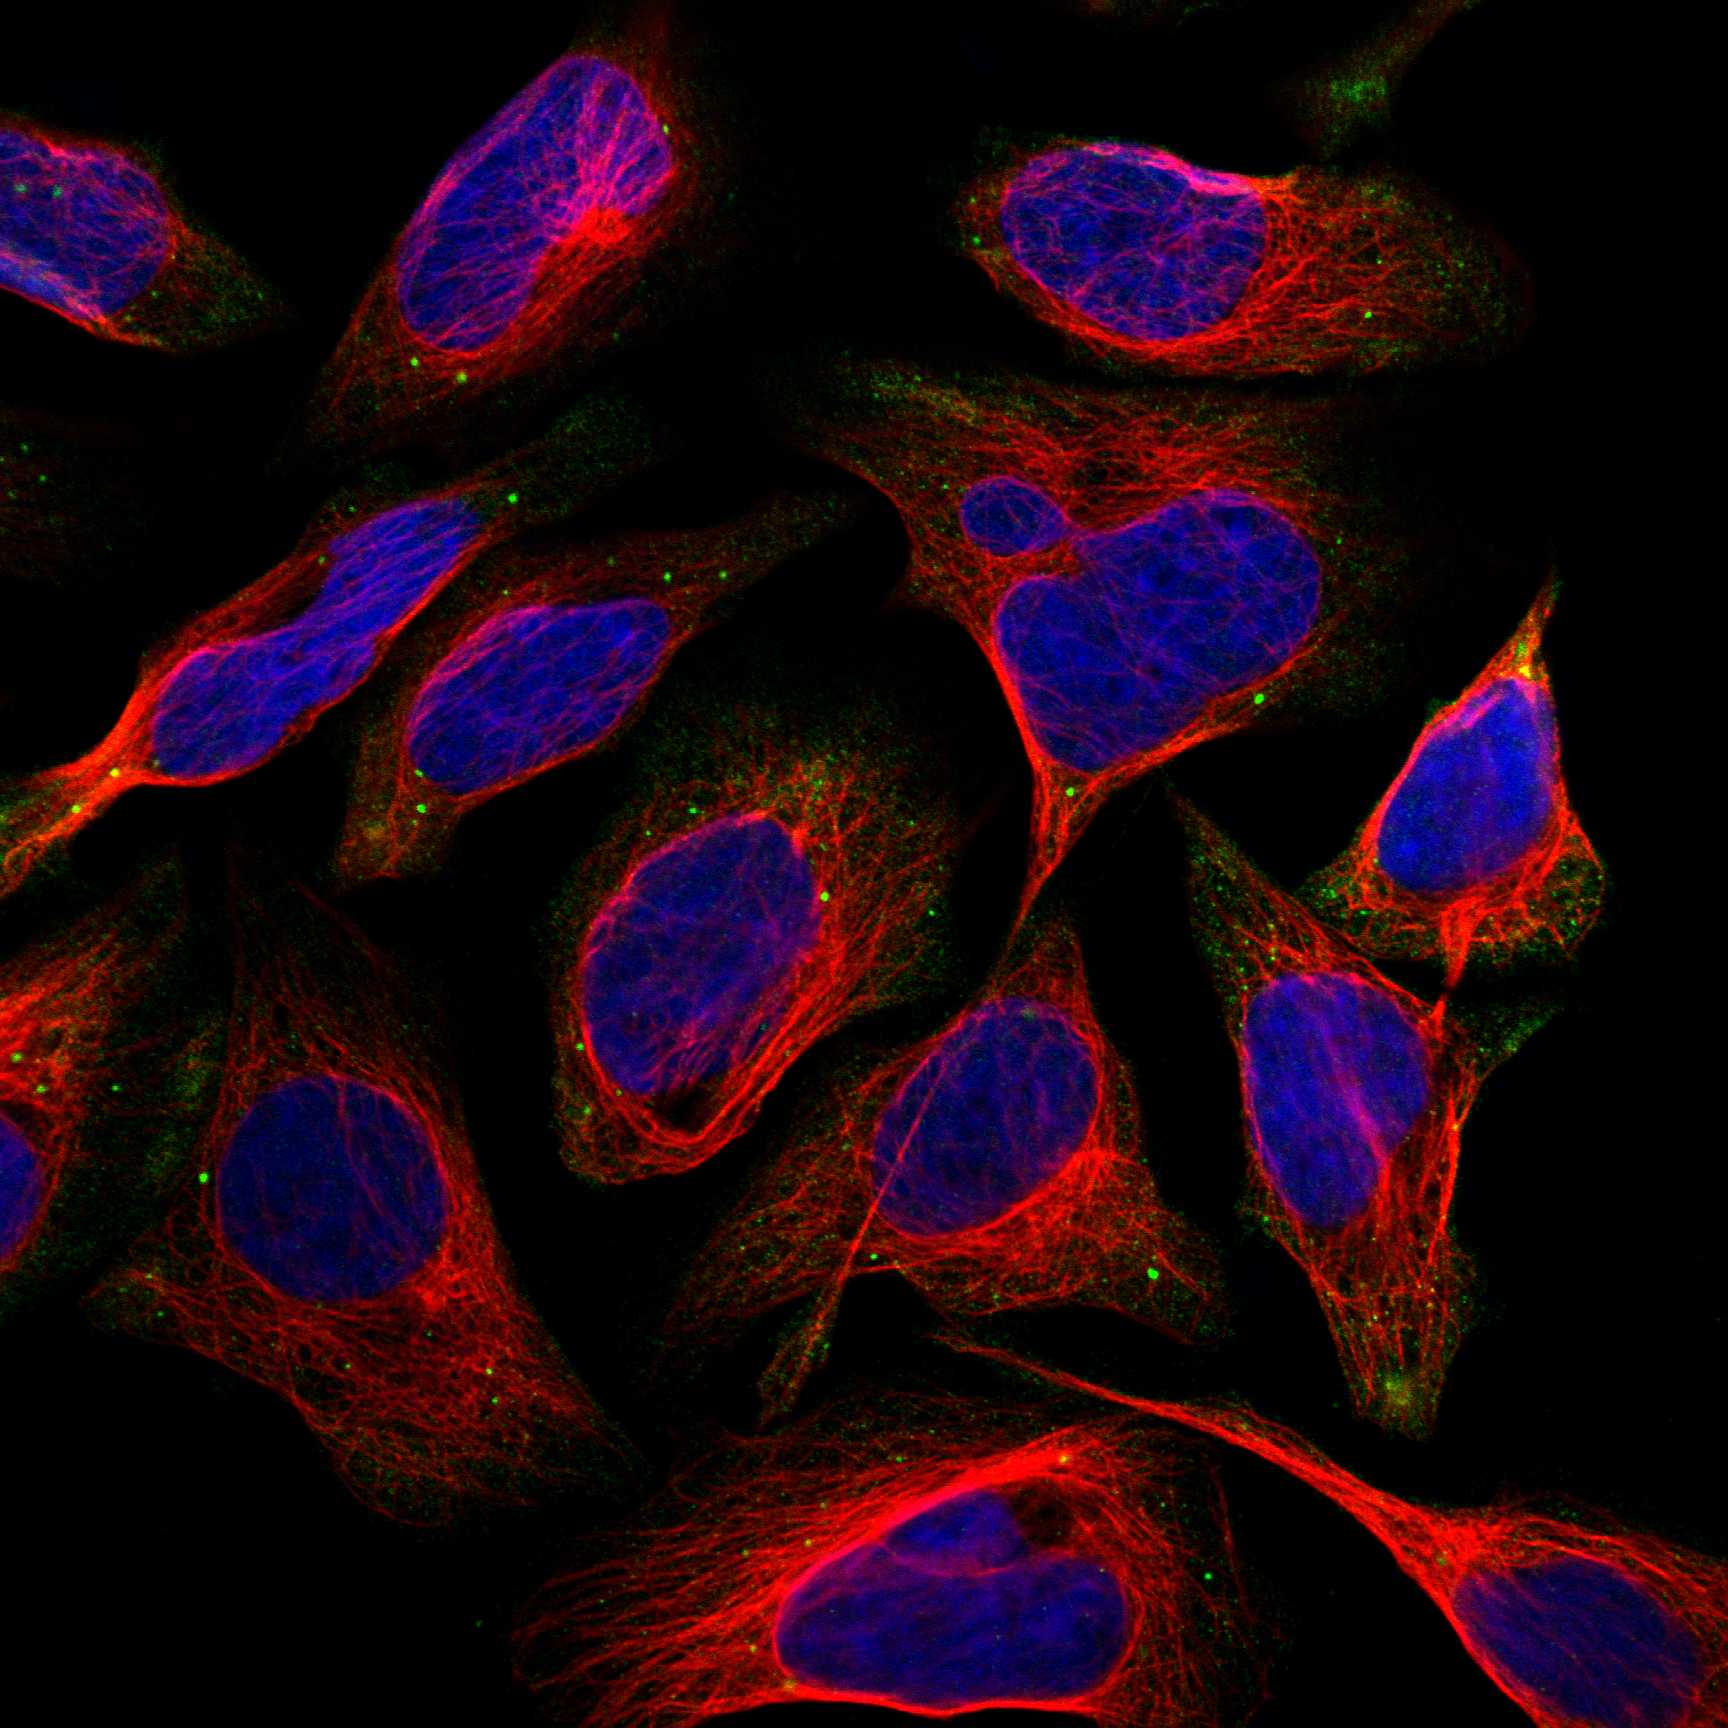
| IF/ICC Q&A | What location can IF/ICC show? HPA reports mainly vesicles, with additional Golgi localization, in its approved ICC-IF data (HPA: subcellular ICC-IF). This informs localization checks; it is not an IHC-P protocol or evidence that every tissue section resolves those structures. |
| Situation | Likely cause | Next action |
|---|---|---|
| The adrenal positive control is blank. | The expected glandular-cell signal is high (HPA: tissue IHC); an absent control signal leaves a workflow or reagent problem unresolved (general IHC practice). | Confirm glandular cells are present, then check antibody identity, documented retrieval conditions, detection reagents and run controls before scoring test sections negative (HPA: tissue IHC; general IHC practice). |
| Only nuclei or cell outlines stain. | That pattern differs from HPA’s cytoplasmic IHC description and the secreted, non-transmembrane annotation (HPA: tissue IHC; UniProt P05111 topology). | Compare the no-primary control and an expected positive tissue; review antibody specificity and chromogen localization before calling the signal INHA (general IHC practice). |
| Adipocytes or appendix glandular cells appear strongly positive. | Those cell populations are listed as not detected, so unexpected color needs verification; the image alone cannot distinguish cross-reactivity from detection background (HPA: tissue IHC; general IHC practice). | Recheck cell identification, examine the no-primary control and compare a positive reference section under the same detection conditions (general IHC practice). |
| Brown color is widespread without cell-specific contrast. | Diffuse background can obscure the HPA-described cytoplasmic pattern; nonspecific binding or endogenous detection activity are possible general IHC causes (HPA: tissue IHC; general IHC practice). | Inspect no-primary and detection controls; review blocking, washing and chromogen development, then repeat scoring only when the cellular pattern is readable (general IHC practice). |
| Ovary appears weaker than adrenal gland or testis. | HPA grades ovary follicle cells medium, versus high in adrenal glandular and testis Leydig cells; lower intensity can therefore fit the reference pattern (HPA: tissue IHC). | Score the follicle cells themselves and compare slides stained in the same run; use the tissue-specific HPA levels rather than one intensity threshold for all three organs (HPA: tissue IHC; general IHC practice). |
| Testis staining is assigned to different cell types by different reviewers. | HPA’s cell-level table lists Leydig cells as high, while its profile describes Sertoli-cell cytoplasmic expression; the supplied HPA descriptions differ in emphasis (HPA: tissue IHC). | Record the stained cell type and morphology explicitly, review the matching HPA image and antibody validation, and avoid collapsing Leydig and Sertoli observations into one claim (HPA: tissue IHC; general IHC practice). |
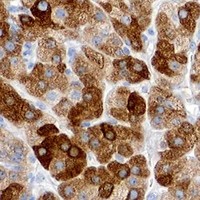
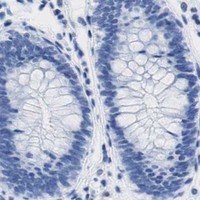
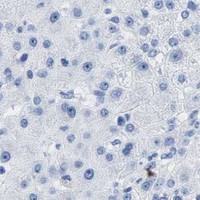
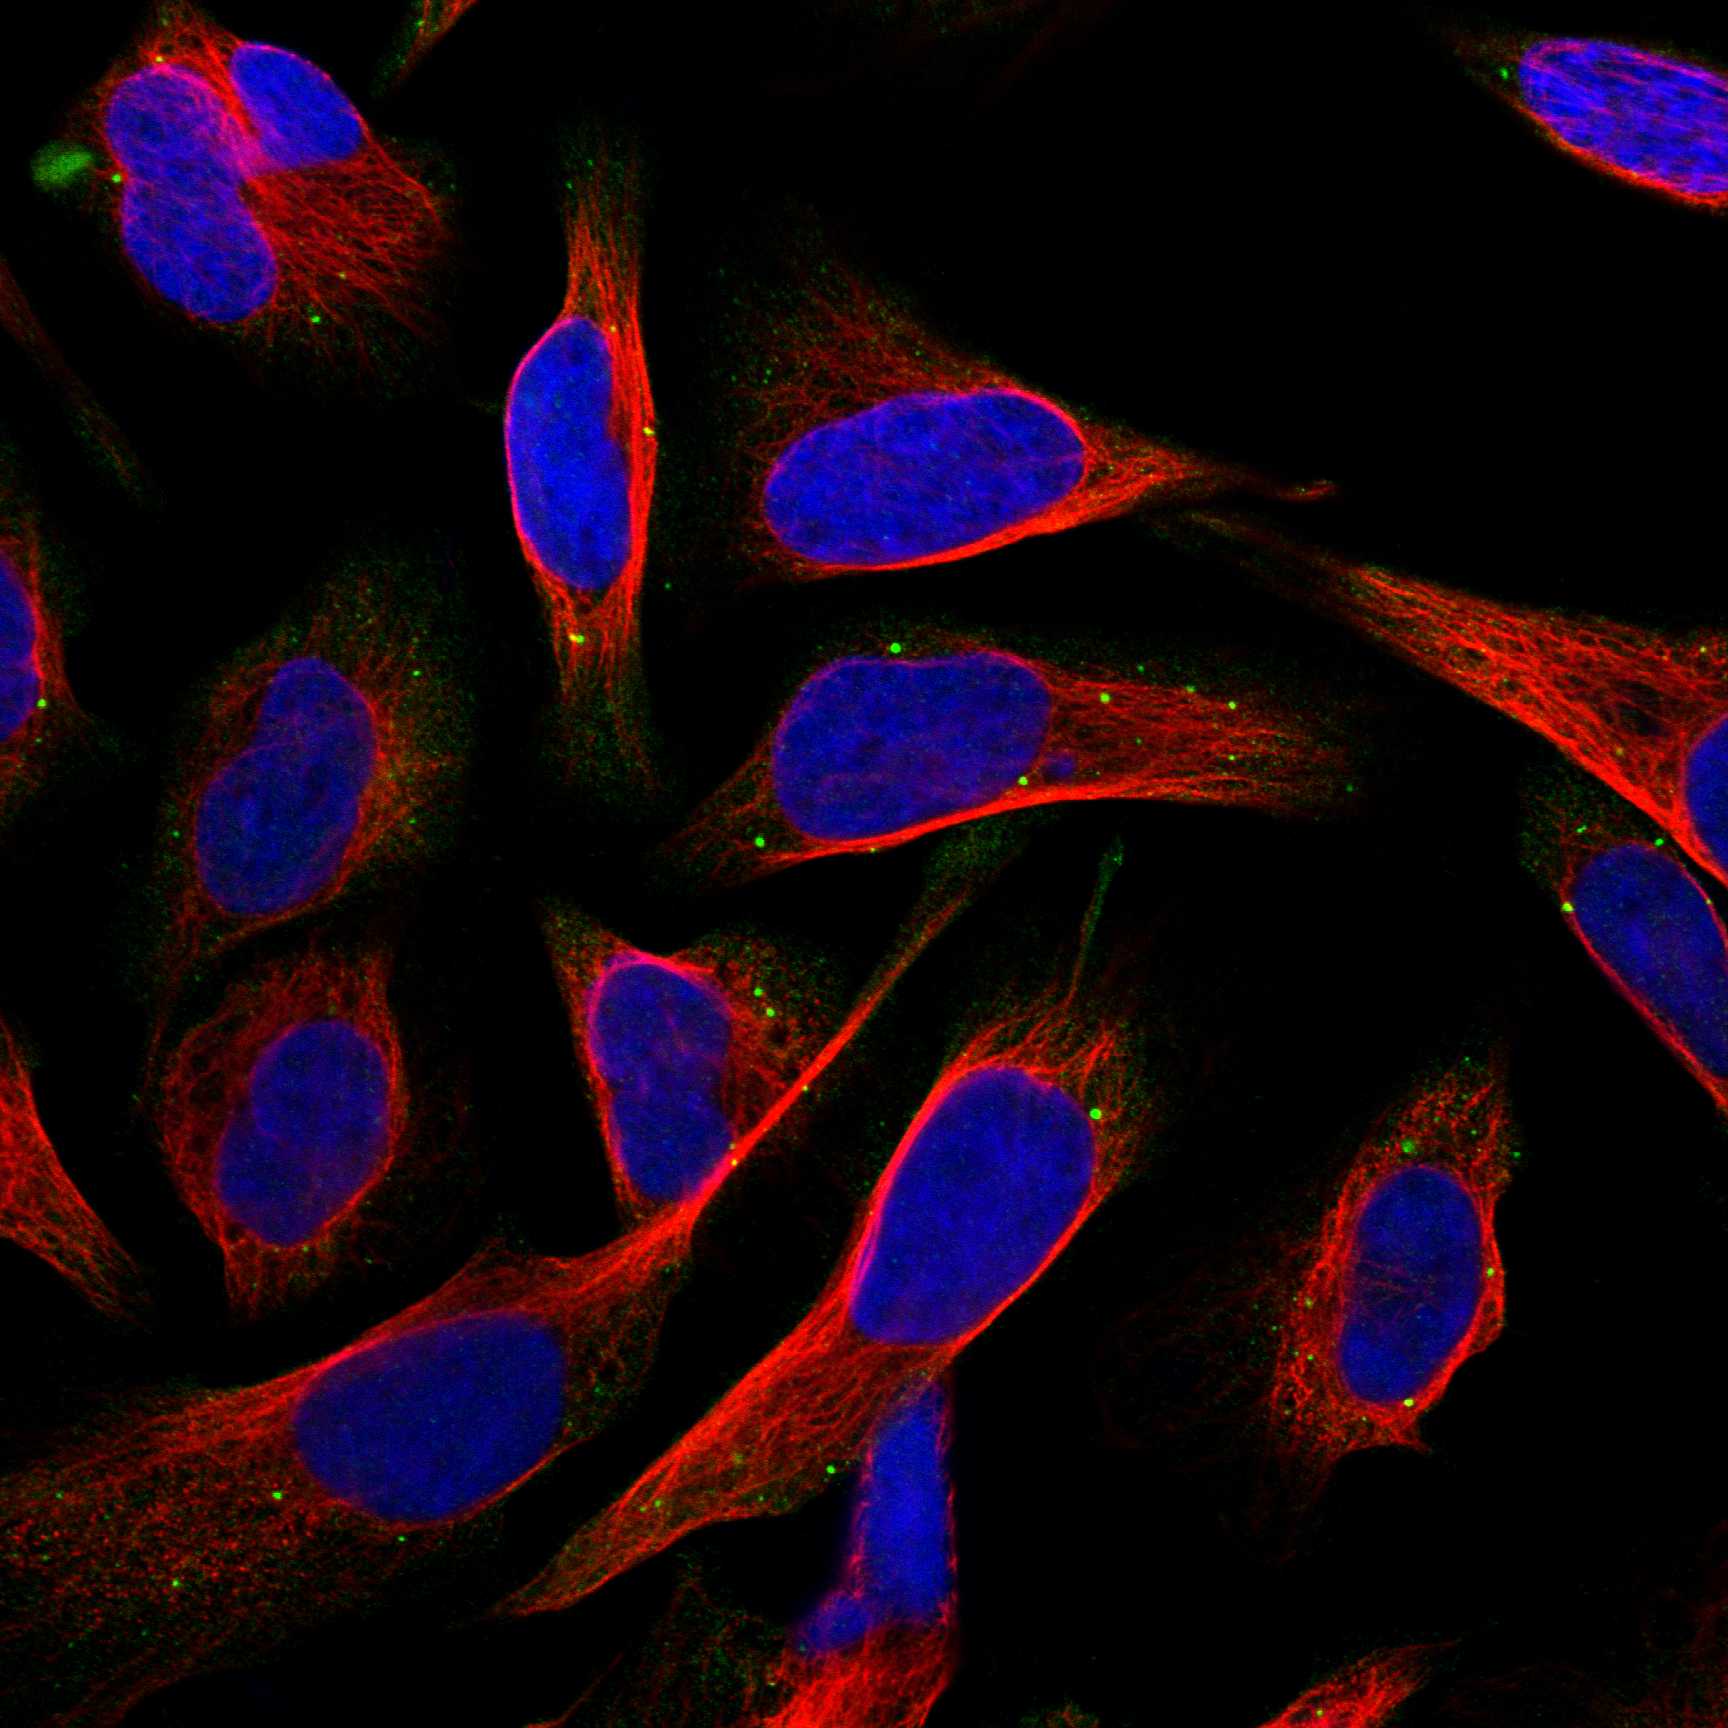
Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data. Secreted protein, tissue location of RNA and protein is expected to differ.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Testis | Leydig cells | High | Protein (IHC) | HPA → |
| Ovary | Follicle cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot INHA staining by checking retrieval, compartment, cell type and detection controls before comparing signal across sections.
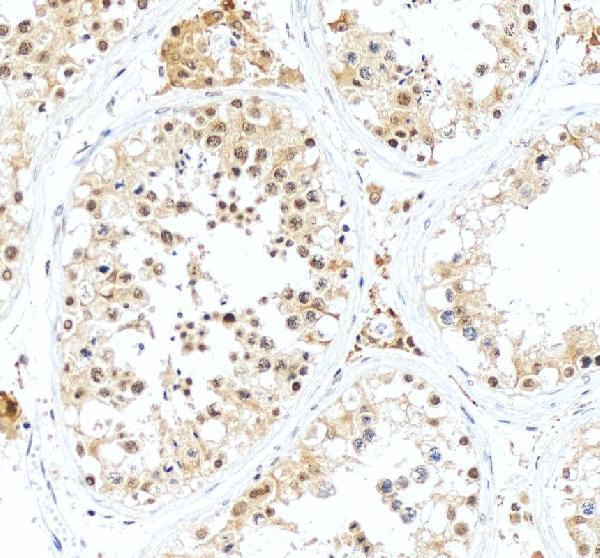
The IHC-validated catalog antibody covers human, mouse and rat (catalog: A02413-3 reactivity); its image captions show paraffin-section IHC in rat and human testis and IF/ICC in U20S cells (A02413-3 captions).
A02413-3 will render with its rat testis paraffin-section IHC figure; its other captions document human testis paraffin-section IHC and U20S-cell IF/ICC (A02413-3 image captions). M02413-2 will render as a human-reactive IHC antibody, with no IHC figure supplied (M02413-2 catalog).
Which to pick: Choose A02413-3 for tissue IHC when a demonstrated paraffin-section procedure matters: its captions document rat and human testis staining, but do not report the fixative (A02413-3 IHC image captions). Choose A02413-3 for IF/ICC or work spanning human, mouse and rat because those applications and species are listed, and its IF caption shows U20S cells; the shown IHC tissue data cover rat and human only (A02413-3 catalog and image captions). M02413-2 offers a rabbit monoclonal for human IHC, though no IHC image or tissue-processing details are supplied (M02413-2 catalog).