This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic IHC on paraffin sections using testis Leydig cells as the positive reference (HPA tissue IHC). Compare cytoplasmic staining with controls, accounting for INSL3 secretion and processing (HPA tissue IHC; UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Leydig cell cytoplasm (HPA tissue IHC) | |
| Staining pattern | Selective cytoplasmic staining in Leydig cells (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Testis | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Secretion may separate protein staining from its cellular source (HPA tissue IHC; UniProt) | |
| Regulation | Prenatal and postnatal Leydig cell expression (UniProt) | |
| Isoform / epitope | 2 isoforms; signal peptide and propeptide processing make epitope choice relevant (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet) is accompanied by four published INSL3 IHC methods (PMC8382946; PMC12420327; PMC4808909; PMC8072358).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A01712); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-INSL3, 1:50 - 1:100 (datasheet A01712) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | INSL3-positive staining in leydig cells of testis (HPA tissue IHC: High). HPA tissue profile: Selective cytoplasmic expression in Leydig cells in testis. No signal in the no-primary control. |
INSL3 is a secreted protein without a transmembrane segment (UniProt P51460 topology). In paraffin-section IHC, expect selective cytoplasmic staining of testicular Leydig cells, with a High staining level in the HPA reference tissue (HPA: testis, Leydig cells, High). HPA rates this tissue pattern Enhanced because staining is consistent with RNA expression; it cautions that a secreted protein's RNA and protein locations may differ (HPA: tissue IHC).
| Selective cytoplasmic signal in cells between testicular tubules. | This fits the reported Leydig-cell pattern when cell identity is established from morphology and tissue context (HPA: selective cytoplasmic expression in Leydig cells). Compare the distribution and intensity with a known-positive testis section; HPA reports High staining in Leydig cells, but that rating does not set an intensity threshold for every specimen (HPA: testis, Leydig cells, High). |
| Predominantly nuclear or membrane-restricted signal in the presumed positive cells. | That compartment differs from HPA's observed cytoplasmic tissue pattern (HPA: tissue IHC). INSL3 is secreted and has no transmembrane segment, so a crisp membrane-only pattern needs independent verification before it is scored as target staining (UniProt P51460 topology). Check morphology, the no-primary control and detection background; an unexpected compartment alone does not identify the cause (general IHC practice). |
| Strong signal in cells outside the expected Leydig-cell population. | First confirm cell identity on the counterstained section: HPA describes the testis pattern as selective for Leydig cells (HPA: tissue IHC). Staining elsewhere could reflect nonspecific antibody binding or detection activity, but should not be assigned either cause from appearance alone (general IHC practice). Review a no-primary control and a second specificity control before extending the cell-type interpretation. |
| Diffuse colour across stroma, tubules and section edges. | A broad, poorly cell-resolved deposit does not resemble selective Leydig-cell cytoplasm (HPA: tissue IHC). In chromogenic IHC, incomplete blocking, inadequate washing or detection background can produce diffuse colour (general IHC practice). Judge whether the same distribution appears in a no-primary control; background that obscures cell boundaries prevents a reliable call even if some Leydig cells look darker. |
| No discernible signal in morphologically identifiable Leydig cells. | A negative testis slide is discordant with the HPA reference pattern of High Leydig-cell staining (HPA: testis, Leydig cells, High). Confirm the section contains identifiable Leydig cells, then assess staining controls and the validated antibody workflow (general IHC practice). A failed positive control makes the run inconclusive; absence of colour in one specimen does not establish absence of INSL3. |
| Secretion and location | UniProt classifies INSL3 as secreted, while HPA observes cytoplasmic staining in Leydig cells (UniProt P51460 subcellular location; HPA: tissue IHC). Interpret tissue colour as an observed distribution, not proof that all INSL3 stays inside those cells. HPA explicitly notes that RNA and protein locations may differ for a secreted protein (HPA: reliability description). |
| Protein processing | The precursor has a signal sequence and a propeptide, and the functional subunit is described as linked A and B chains (UniProt P51460 processing and subunit). The supplied record does not locate the IHC antibody's epitope. Its recognition of precursor versus processed protein therefore cannot be inferred from processing annotations; consult epitope documentation before explaining a discrepant result. |
| Antibody evidence | HPA lists antibody HPA028615 as IHC Enhanced, and its tissue profile describes selective Leydig-cell cytoplasm (HPA: antibodies; HPA: tissue IHC). That supports the reported IHC pattern, without establishing how another antibody behaves or validating a specific ICC-IF distribution. HPA provides no ICC-IF images or main subcellular location for this target (HPA: subcellular). |
| Choice of comparison tissue | HPA reports High staining in testicular Leydig cells and Not detected in specified populations including adrenal glandular cells and adipose-tissue adipocytes (HPA: tissue IHC). Use the named cell populations when comparing sections; these entries do not establish that every cell in those tissues is negative. UniProt also lists expression outside testis (UniProt P51460 tissue specificity). |
| Situation | Likely cause | Next action |
|---|---|---|
| The expected Leydig-cell signal is absent. | The positive tissue may be missing identifiable Leydig cells, or the staining run may have failed; the slide alone cannot distinguish these possibilities (HPA: testis, Leydig cells, High; general IHC practice). | Locate Leydig cells on the counterstain and review a known-positive testis section run alongside the sample (HPA: testis tissue IHC). If the control also fails, review the validated antibody dilution, retrieval and detection steps as general IHC troubleshooting. |
| Colour appears throughout the section. | The distribution is broader than HPA's selective Leydig-cell pattern (HPA: tissue IHC). Nonspecific detection or inadequate blocking and washing are possible general IHC causes. | Compare a no-primary control, then inspect blocking, washing and chromogen development (general IHC practice). Score INSL3 only where cell-resolved staining can be distinguished from the background (HPA: selective Leydig-cell pattern). |
| Strong colour appears in an unexpected testicular cell population. | Cell misidentification, antibody cross-reactivity or endogenous detection activity are possibilities (general IHC practice); HPA reports selective Leydig-cell cytoplasm in testis (HPA: tissue IHC). | Recheck morphology and counterstain, inspect the no-primary control and seek independent antibody or orthogonal evidence before assigning that population as INSL3 positive (general IHC practice). |
| Signal is mainly nuclear or outlines cell membranes. | That appearance conflicts with the HPA cytoplasmic observation; membrane-only staining also lacks support from INSL3's no-transmembrane topology (HPA: tissue IHC; UniProt P51460 topology). | Check focus, section morphology and control staining, then verify the unexpected compartment independently (general IHC practice). Do not use compartment alone to diagnose a particular staining failure. |
| A comparison tissue shows unexpected positive cells. | HPA's Not detected calls apply to named cell populations, such as adrenal glandular cells and adipose-tissue adipocytes, rather than every cell in either tissue (HPA: tissue IHC). | Identify the stained cell type before comparing it with HPA, and examine a no-primary control if its staining is unexpected (general IHC practice). Interpret the result against the population-specific HPA entry. |
| IF/ICC Q: Does a fluorescent compartment pattern confirm INSL3? | HPA reports no ICC-IF images or main subcellular location, and lists no ICC status for HPA028615 (HPA: subcellular; HPA: antibodies). | A: No compartment-specific IF/ICC pattern is established by these payloads. Use an independently validated IF/ICC assay and its controls to interpret fluorescence; the HPA Leydig-cell observation is tissue IHC evidence (HPA: tissue IHC; general IF practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data. Secreted protein, tissue location of RNA and protein is expected to differ.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Testis | Leydig cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot INSL3 chromogenic IHC in paraffin sections using the specified retrieval conditions and cell-specific controls; the IF entry addresses multiplex imaging.
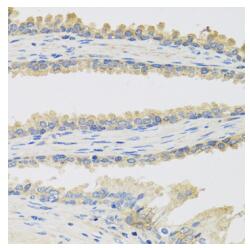
A01712 has real IHC data from a human prostate paraffin section (catalog image caption). IF/ICC is listed for human, mouse, and rat, with no IF image supplied (catalog applications, reactivity, image alts).
A01712 is listed for IHC-P and IF/ICC in human, mouse, and rat (catalog applications, reactivity). Its image shows IHC on a human prostate paraffin section at 1:100; no IF image is supplied (catalog image caption, IF image alts).
Which to pick: Choose A01712 for paraffin-section tissue IHC because its own image documents that preparation in human prostate; the fixative is unreported (catalog image caption). Choose A01712 for IF/ICC because those applications are listed, although no IF image is supplied (catalog applications, IF image alts). For mouse or rat samples, A01712 lists reactivity with both species, but its IHC image shows human tissue only (catalog reactivity, image caption).