This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Use tonsil germinal center cells as a positive reference for paraffin IRF8 IHC (HPA tissue IHC). This guide covers fixation consistency, the catalog antibody’s 2–5 μg/ml IHC range (datasheet PA2209), and interpretation of nuclear staining in lymphoid cells (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear in a subset of lymphoid cells (HPA tissue IHC) | |
| Staining pattern | Selective nuclear staining in some lymphoid cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet PA2209) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Resting macrophages can retain cytoplasmic IRF8 (UniProt) | |
| Regulation | IFN-γ induces nuclear translocation (UniProt) | |
| Isoform / epitope | No annotated isoforms or processing; one 1–426 chain (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet: PA2209) with four published IRF8 IHC protocols (PMC7992828; PMC3498170; PMC9601976; PMC2605678).
| Sample | Paraffin-embedded human tonsil tissue; fixative not specified (datasheet PA2209) |
| Fixation | Image fixative and duration unreported (datasheet PA2209); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet PA2209); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet PA2209) |
| Primary antibody | Rabbit anti-IRF8, 2-5μg/ml (datasheet PA2209) |
| Primary incubation | Overnight at 4 °C (datasheet PA2209) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet PA2209) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | IRF8-positive staining in lymphoid tissue of appendix (HPA tissue IHC: High). HPA tissue profile: Selective nuclear expression in a subset a lymphoid cells. No signal in the no-primary control. |
IRF8 is a nuclear transcription factor, with cytoplasmic localisation reported in resting macrophages and nuclear translocation after IFN-gamma induction (UniProt Q02556). In paraffin sections, expect selective nuclear staining in a subset of lymphoid cells, especially germinal center cells (HPA: tissue IHC). IRF8 has no transmembrane segment (UniProt Q02556 topology). HPA rates its tissue IHC reliability Enhanced, with medium consistency between antibody staining and RNA expression (HPA: tissue IHC).
| Distinct nuclear staining in a subset of lymphoid cells, strongest in germinal centers. | This matches the selective tissue pattern: germinal center cells in lymph node and tonsil are High, and appendix lymphoid tissue is High (HPA: tissue IHC). Judge the labelled cell population and compartment together; a positive section need not show staining in every cell (HPA: tissue IHC). |
| Predominantly cytoplasmic staining, with little convincing nuclear signal. | In lymphoid tissue, this departs from the selective nuclear IHC pattern and calls for a compartment check (HPA: tissue IHC). Cytoplasm alone is not conclusive evidence of artefact in macrophages: resting macrophages can contain cytoplasmic IRF8, which moves to the nucleus after IFN-gamma induction (UniProt Q02556). |
| Strong staining across respiratory epithelium or other cells expected to be negative. | HPA reports IRF8 as Not detected in bronchial respiratory epithelial cells, so widespread staining there warrants a specificity check (HPA: tissue IHC). Cross-reactivity or endogenous chromogenic detection activity are possible explanations (general IHC practice); the pattern alone does not identify which one occurred. |
| A diffuse chromogen haze obscures nuclei and tissue boundaries. | The slide cannot be scored confidently for the selective nuclear pattern while background masks cell identity (HPA: tissue IHC; general IHC practice). Review blocking, washing, detection controls and counterstain intensity before deciding whether the apparent staining belongs to IRF8-positive cells (general IHC practice). |
| No signal in lymph node or tonsil germinal centers. | Both are reported High in germinal center cells, making them useful known-positive tissue checks (HPA: tissue IHC). An entirely blank section may reflect assay failure, unsuitable antibody conditions or detection failure (general IHC practice); it does not by itself establish biological absence of IRF8. |
| Which tissue and cells are being scored? | HPA reports High staining in appendix lymphoid tissue and lymph node and tonsil germinal center cells; bone marrow hematopoietic cells, lung macrophages and splenic red-pulp cells are Medium (HPA: tissue IHC). Compare each observed population with its own reference level rather than applying one intensity threshold across tissues (general IHC interpretation). |
| Does cellular state affect the compartment? | UniProt places IRF8 in nucleus and cytoplasm, specifying cytoplasmic localisation in resting macrophages and nuclear translocation after IFN-gamma induction (UniProt Q02556). Record cell type and experimental state when interpreting macrophage cytoplasm; HPA's selective nuclear tissue profile remains the reference for routine lymphoid-section scoring (HPA: tissue IHC). |
| How strong is the validation evidence? | HPA lists tissue IHC reliability as Enhanced, while describing only medium consistency between antibody staining and RNA expression (HPA: tissue IHC). Three listed antibodies have Enhanced IHC validation: HPA002267, HPA002531 and CAB013480 (HPA: antibodies). Treat an unexpected pattern as a reason to verify specificity, not as proof of a new expression site. |
| What molecular features guide the compartment check? | IRF8 is a 426-residue protein with no transmembrane segment, signal peptide, propeptide or annotated alternative isoforms in the supplied record (UniProt Q02556 topology and processing). These facts fit an intracellular staining assessment; they do not predict antigen retrieval requirements or fixation sensitivity (UniProt Q02556; source-scope limitation). |
| IF/ICC Q&A: where should fluorescence appear? | HPA reports enhanced nucleoplasmic localisation in ICC-IF (HPA: subcellular). UniProt also reports cytoplasmic IRF8 in resting macrophages and nuclear translocation after IFN-gamma induction (UniProt Q02556). Use cell identity and state when interpreting fluorescence; the ICC-IF localisation record does not define an IHC-P protocol (HPA: subcellular). |
| Situation | Likely cause | Next action |
|---|---|---|
| Known-positive germinal centers are blank. | A failed primary-antibody or detection step is possible; lymph node and tonsil germinal center cells are High in the reference profile (HPA: tissue IHC; general IHC practice). | Repeat with a known-positive section and review the IHC-validated antibody's specified conditions, reagent integrity and chromogenic detection controls before interpreting a negative sample (general IHC practice). |
| Signal is mostly cytoplasmic in lymphoid cells. | This differs from HPA's selective nuclear lymphoid IHC profile; macrophage cytoplasm is a documented state-dependent exception (HPA: tissue IHC; UniProt Q02556). | Identify the stained cells, inspect nuclear boundaries with the counterstain and compare a known-positive lymphoid section; record macrophage activation state when known (general IHC practice; UniProt Q02556). |
| Bronchial respiratory epithelium stains strongly. | Those epithelial cells are Not detected in the HPA tissue profile; cross-reactivity or endogenous chromogenic activity may contribute (HPA: tissue IHC; general IHC practice). | Compare the pattern with a matched no-primary detection control and a known-positive lymphoid section; review blocking and antibody dilution if the unexpected signal persists (general IHC practice). |
| Brown haze covers both positive and expected-negative areas. | Nonspecific background or endogenous detection activity may obscure the selective nuclear pattern (general IHC practice; HPA: tissue IHC). | Check no-primary controls, washing and blocking; adjust chromogenic development and counterstain so individual nuclei remain readable (general IHC practice). |
| A Medium-reference population stains less than germinal centers. | The reference levels differ: bone marrow hematopoietic cells, lung macrophages and splenic red-pulp cells are Medium, while lymph node and tonsil germinal center cells are High (HPA: tissue IHC). | Score the correct cell type against its tissue-specific HPA level before changing assay conditions; compare sections using the same staining run where possible (HPA: tissue IHC; general IHC practice). |
| Staining appears in nearly every cell of a lymphoid section. | Uniform staining conflicts with HPA's selective expression in a subset of lymphoid cells and may reflect background or antibody cross-reactivity (HPA: tissue IHC; general IHC practice). | Check whether stained nuclei belong to the expected population, then compare a no-primary control and an expected-negative cell population before calling the section positive (general IHC practice; HPA: tissue IHC). |


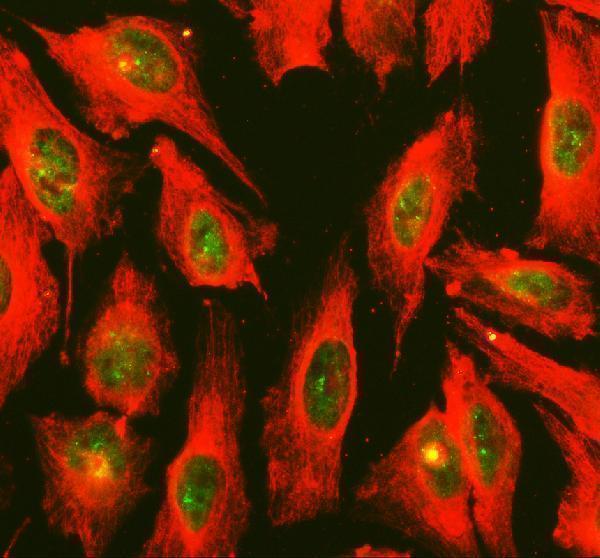
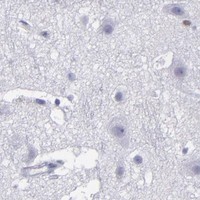
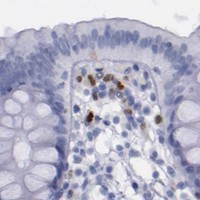
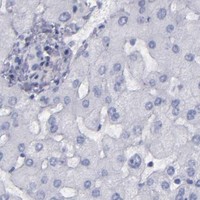


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Lymphoid tissue | High | Protein (IHC) | HPA → |
| Lymph node | Germinal center cells | High | Protein (IHC) | HPA → |
| Tonsil | Germinal center cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Lung | Macrophages | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot IRF8 chromogenic IHC in paraffin sections by checking retrieval, nuclear staining, cell identity, and matched controls (datasheet PA2209; HPA tissue IHC).
PA2209 has IHC data from human tonsil and mouse spleen paraffin sections (catalog IHC captions), plus IF/ICC data from U2OS cells (catalog IF caption).
PA2209 was tested by IHC on human tonsil and mouse spleen paraffin sections (catalog IHC captions). PA2209 also has IF/ICC data from U2OS cells (catalog IF caption).
Which to pick: Choose PA2209 for paraffin-section IHC: its captions document EDTA retrieval at pH 8.0 and primary antibody at 2 μg/ml (PA2209 IHC captions); the fixative is unreported (PA2209 IHC captions). For IF/ICC, PA2209 has a U2OS-cell image at 5 μg/ml (PA2209 IF caption). For human and mouse tissue work, PA2209 lists reactivity with both species and has IHC images from each (PA2209 catalog; PA2209 IHC captions); clonality is unreported (PA2209 catalog).