KIF5B / Kinesin-1 heavy chain · IHC design guide

Design Immunohistochemistry for KIF5B

Plan KIF5B chromogenic IHC on paraffin sections around the expected cytoplasmic pattern (HPA tissue IHC). Cerebral cortex glial cells offer a high-staining reference, while adipocytes are reported as unstained (HPA tissue IHC); the catalog antibody’s IHC dilution range is 1:50–1:400 (datasheet A01934-2).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for KIF5B (IHC for KIF5B): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A01934-2, validated IHC image, and IHC protocol steps
Printable KIF5B IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A01934-2, controls and protocol steps. Open the full KIF5B IHC guide →

KIF5B Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Cytoplasmic signal in glandular, epithelial and glial cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01934-2)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A01934-2)
Caveat Adipocytes and chondrocytes may lack staining (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope 0 isoforms; chain 2–963; cytoplasmic epitope expected (UniProt)
Section 1

Recommended KIF5B IHC & IF Protocols

The catalog antibody protocol is followed by 3 published KIF5B paraffin-section protocols, including two with chromogenic detection (PMC3012189; PMC7950107; PMC4401754).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat brain tissue; fixative not specified (datasheet A01934-2)
FixationImage fixative and duration unreported (datasheet A01934-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01934-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01934-2)
Primary antibodyRabbit anti-KIF5B, 1:50 recommended; image 1:100 (datasheet A01934-2)
Primary incubationOvernight at 4 °C (datasheet A01934-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A01934-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultKIF5B-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in all tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A01934-2); the published Tris/EDTA pH 9.0 method is an alternative (PMC7950107 methods).
Section 2

What Is the Expected KIF5B Staining Pattern?

KIF5B is a cytoskeletal motor without a transmembrane segment (UniProt P33176 topology). In paraffin-section IHC, expect predominantly cytoplasmic staining across many cell types (HPA tissue IHC: cytoplasmic expression in all tissues; Approved, with medium consistency against RNA data). Strong examples include bronchial respiratory epithelium, colonic glands, and cerebral-cortex glia (HPA tissue IHC: High in each). Interpret intensity by cell type within the section.

What am I looking at on my slide?
Cytoplasmic signal in bronchial respiratory epithelial cells or colonic glandular cells.This matches two reported strong IHC patterns (HPA tissue IHC: High in both). Assess identifiable cells and their cytoplasm, rather than treating every stained area in the tissue as equivalent (general IHC practice).
Predominantly nuclear staining, with little cytoplasmic signal in identifiable positive cells.The compartment conflicts with the reported tissue pattern (HPA tissue IHC: cytoplasmic expression). Check whether the signal follows nuclei or overlays cytoplasm before calling it specific (general IHC practice).
Strong staining confined to adipocytes or chondrocytes, while expected positive cells are unstained.Those two cell types were reported as not detected (HPA tissue IHC). Consider cross-reactivity or endogenous chromogenic activity; first verify the cell identity and compare the signal with a detection-only control (general IHC practice).
Uniform colour over cells and cell-free areas, obscuring cytoplasmic boundaries.This distribution does not permit a cell-specific KIF5B call (general IHC practice). Excess detection background or incomplete washing is possible; compare a detection-only control and reassess washing and development (general IHC practice).
No visible cytoplasmic signal in bronchial respiratory epithelium or colonic glands.These are reported High cell populations (HPA tissue IHC), so an entirely blank result warrants a run check. Confirm tissue identity, antibody exposure, detection reagents, and a positive control before inferring biological absence (general IHC practice).
💡Expected KIF5B appearanceA convincing positive is identifiable cytoplasmic staining, potentially strong in bronchial respiratory epithelium or colonic glands (HPA tissue IHC: High); isolated nuclear colour or uniform cell-free colour is suspect (HPA tissue IHC: cytoplasmic profile; general IHC practice).
How each factor affects the staining
Tissue and cell selectionThe HPA profile is broad, but intensity varies by cell type: cerebral-cortex glia are High, whereas hippocampal glia are Low (HPA tissue IHC). Use the named cell population when judging a control; a weak result in one population does not define the whole organ.
Negative-reference cellsAdipocytes and chondrocytes are reported as Not detected (HPA tissue IHC). They can help flag unexpected colour in those cells, but neither finding establishes that the entire adipose or soft-tissue section must be blank.
Antibody evidenceThree listed antibodies have IHC status Approved: HPA037589, HPA037590, and CAB009846 (HPA antibodies). HPA describes the tissue IHC profile as having medium consistency with RNA data (HPA tissue IHC); compare the observed pattern with tissue controls.
Topology and processingKIF5B has no transmembrane segment, signal peptide, or propeptide in the supplied record (UniProt P33176). Its lysosome and cytolytic-granule membrane associations do not make membrane-only chromogenic staining the expected tissue result (UniProt P33176 subcellular; HPA tissue IHC).
IF/ICC Q&A: what localisation is expected?Mainly cytosol and centriolar satellites, with an additional end-piece location, are reported in ICC-IF (HPA subcellular). HPA037589 and HPA037590 have ICC status Enhanced (HPA antibodies). These ICC-IF details do not set an IHC-P scoring requirement.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A reported High cell population is blank.The run may have failed, or the intended cell population may be absent from the examined area (general IHC practice).Verify cell identity and section coverage, then review antibody dilution, detection steps, and a concurrently stained positive control (general IHC practice); bronchial respiratory epithelium and colonic glands are High references (HPA tissue IHC).
Only nuclei appear positive.Nuclear-only signal conflicts with the cytoplasmic tissue profile (HPA tissue IHC); counterstain or nonspecific colour may complicate interpretation (general IHC practice).Examine a lighter counterstain or detection-only control, and require a clear cytoplasmic pattern in identifiable cells before scoring KIF5B positivity (general IHC practice).
Adipocytes or chondrocytes stain strongly.This disagrees with the reported Not detected levels for those cells (HPA tissue IHC); cross-reactivity or endogenous detection activity is possible (general IHC practice).Confirm the stained cell type, inspect a detection-only control, and review the assay's endogenous-activity blocking step where applicable (general IHC practice).
The entire section has diffuse chromogenic colour.Background can arise from nonspecific reagent retention, washing, or detection development (general IHC practice); the HPA cytoplasmic profile cannot validate a uniform haze (HPA tissue IHC).Compare detection-only and positive controls, then review blocking, washing, antibody dilution, and development time as general IHC variables (general IHC practice).
A low-reference cell type is weak while a High-reference cell type stains.Cell-type variation is documented: hippocampal glia are Low and cerebral-cortex glia are High (HPA tissue IHC).Score each named cell population against its reported level and retain the stronger population as the practical positive reference (HPA tissue IHC; general IHC practice).
Changing fixation or retrieval appears to change the signal.No KIF5B-specific fixation or retrieval sensitivity is established by the supplied UniProt or HPA records.Treat the change as an assay observation: hold tissue and detection conditions constant, compare appropriate controls, and record the conditions before attributing the difference to KIF5B (general IHC practice).

Sample controls for KIF5B IHC & IF

🧪Run appendix first: glandular cells should show KIF5B staining (HPA: High in appendix glandular cells). Use adipose tissue adipocytes as the negative tissue (HPA: Not detected in adipocytes); on the appendix slide, assess adjacent nonglandular cells for background, but do not assume they are KIF5B-negative because HPA does not designate an internal negative cell population there.
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show KIF5B in A-431, A-549, U2OS, RPTEC/TERT1, hTERT-RPE1 (serum starved), Sperm, HeLa BAC 5114, HeLa , NIH 3T3, with annotated localisation: Centriolar satellite (approved), Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide, a matched nonimmune rabbit IgG control, and a KIF5B-knockout biological control where available (caption: rabbit primary antibody; standard IHC control practice). Quench endogenous peroxidase before HRP/DAB detection, particularly when assessing appendix inflammatory cells (caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A KIF5B-specific fixation window and fixation effect are unreported, and the selected A01934-2 paraffin-section caption does not state the fixative (selected-SKU tissue-IHC caption). The caption uses heat retrieval in EDTA at pH 8.0 before staining, but does not establish whether retrieval is required for every specimen (selected-SKU tissue-IHC caption). Whether frozen sections or IF are easier is unreported; endogenous peroxidase in inflammatory cells is a potential appendix artefact with HRP/DAB detection (standard IHC practice).

HPA tissue IHC evidence for KIF5B

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Cerebral cortex Glial cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Soft tissue Chondrocytes Not detected Protein (IHC) HPA →
Section 3

Advanced KIF5B IHC Tips

Troubleshoot KIF5B staining in paraffin sections by checking retrieval, cytoplasmic localisation, background controls and cell-level scoring.

What retrieval should I start with for KIF5B in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A01934-2). The selected antibody stained a paraffin-embedded rat brain section after that retrieval, followed by 10% goat serum block and primary antibody at 1:100 overnight at 4°C (caption A01934-2). Keep heating and cooling conditions consistent across comparison sections, then assess cytoplasmic signal against a no-primary control (HPA: cytoplasmic expression in all tissues; standard IHC practice). If staining is weak, vary retrieval duration on matched sections before changing antibody concentration; inspect tissue preservation alongside signal (standard IHC practice).
How can I tell whether fixation is suppressing KIF5B staining?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative (caption A01934-2). Record the actual fixative, fixation interval and processing history for each specimen, and compare matched sections with identical retrieval and detection conditions (standard IHC practice). Uneven staining across a section can reflect processing differences, so check morphology and include a no-primary control before attributing loss to KIF5B biology (standard IHC practice). The reported starting conditions are EDTA at pH 8.0 and primary antibody at 1:100 overnight at 4°C; those conditions establish a staining example, not a fixation tolerance range (caption A01934-2).
Which staining pattern fits KIF5B, and which patterns need checking?
Expect predominantly cytoplasmic staining in tissue sections (HPA: cytoplasmic expression in all tissues; UniProt P33176: cytoplasm and cytoskeleton). KIF5B is a microtubule-dependent motor involved in mitochondrial and lysosomal distribution, so cytoplasmic variation may be biologically plausible (UniProt P33176: function). Its reported membrane associations include lysosomes and cytolytic granules, but it has no transmembrane segment; a sharp, continuous plasma-membrane rim warrants scrutiny (UniProt P33176: localisation and topology). Compare the suspect pattern with morphology, a no-primary section and a second antibody when available, keeping retrieval at EDTA pH 8.0 during that comparison (datasheet A01934-2; standard IHC practice).
Could epitope position or modification explain discordant KIF5B staining?
The supplied record lists 0 isoforms, so it does not support assigning a staining difference to a documented splice isoform (UniProt P33176: isoforms). KIF5B contains a kinesin motor domain at residues 8–325 and reported modifications at residues 2, 933 and 956 (UniProt P33176: domains and modified residues). The antibody epitope is not supplied, so those features cannot establish epitope masking or modification-sensitive binding for this reagent (supplied A01934-2 caption; UniProt P33176). If sections disagree, compare processing and retrieval first, then seek documented epitope information or an independently targeted antibody before interpreting the difference as molecular (standard IHC practice).
How should I investigate KIF5B by multiplex IF alongside this IHC assay?
For a separate IF experiment, pair KIF5B with a marker for the cell population being assessed and include single-stain controls to evaluate channel bleed-through (standard IF practice). Choose fluorophores after measuring tissue autofluorescence, placing the weaker expected signal in a cleaner channel when possible (standard IF practice). KIF5B is mainly cytosolic, with reported centriolar satellite localisation, so permeabilise sufficiently to expose intracellular epitopes; its membrane associations do not make it a transmembrane protein (HPA: subcellular localisation; UniProt P33176: topology). Optimise permeabilisation on matched samples and use antibody omission controls; the paraffin-section conditions at 1:100 are IHC evidence, not an IF dilution recommendation (caption A01934-2; standard IF practice).
What should I check when KIF5B DAB staining looks diffuse?
The selected paraffin-section example used a peroxidase-conjugated secondary antibody and DAB development, so evaluate enzyme-related background with appropriate detection controls (caption A01934-2; standard IHC practice). Block endogenous peroxidase for chromogenic IHC and compare a no-primary section to identify staining from the secondary or detection system (standard IHC practice). The reported primary concentration was 1:100, with 10% goat serum block and overnight incubation at 4°C; use those as documented starting conditions, not proof that diffuse signal is specific (caption A01934-2). If background persists, titrate the primary antibody and review washing, section edges and damaged areas while checking whether cytoplasmic contrast remains (HPA: cytoplasmic expression; standard IHC practice).
How should I score KIF5B staining across different tissue regions? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region before scoring, then record cytoplasmic intensity and the percentage of positive cells to calculate an H-score (HPA: cytoplasmic tissue expression; standard IHC practice). An H-score sums each intensity category multiplied by its percentage of cells; use the same thresholds and counterstain settings across slides (standard IHC practice). If counting discrete positive cells instead, report their number per mm² of evaluable tissue and normalise comparisons to the same cell population or tissue compartment (standard IHC practice). Separate staining intensity from cell abundance, since HPA reports high signal in some cell populations and low or undetected signal in others (HPA: tissue IHC profile).
How do I distinguish genuine KIF5B staining from section artefact?
A credible result shows cytoplasmic staining in intact cells and a reproducible pattern across comparable sections (HPA: cytoplasmic expression in all tissues; standard IHC practice). HPA reports high staining in cerebral cortex glial cells but low staining in hippocampal glial cells, so cell identity and anatomical context matter when comparing fields (HPA: tissue IHC profile). Treat a dominant nuclear pattern, edge-only signal, necrotic-area staining or signal in a no-primary section as reasons to investigate artefact before assigning KIF5B expression (UniProt P33176: cytoplasmic localisation; standard IHC practice). For DAB sections, check endogenous peroxidase blocking and compare adjacent intact regions under the same retrieval and detection conditions (standard IHC practice).
Boster reagents

Best KIF5B / Kinesin-1 heavy chain IHC Antibodies

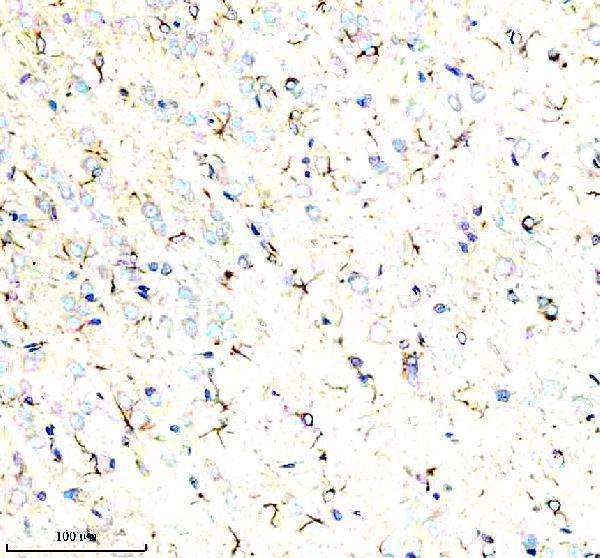
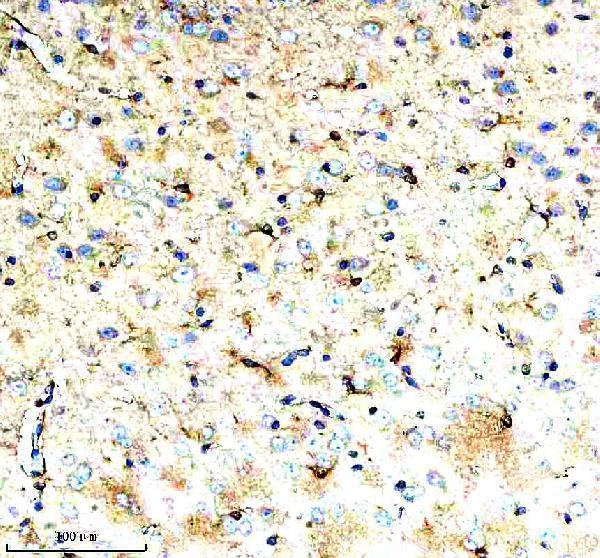
Both anti-KIF5B antibodies list human, mouse, and rat reactivity (catalog: reactivity). Supplied IHC images show A01934-2 in rat and mouse brain paraffin sections (A01934-2 image captions).

Real IHC data IHC analysis of KIF5B using anti-KIF5B antibody (A01934-2). KIF5B was detected in a paraffin-embedded section of rat brain tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:100 rabbit anti-KIF5B Antibody (A01934-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-KIF5B Antibody
Cat # A01934-2

A01934-2 is listed for IHC in human, mouse, and rat (catalog: A01934-2 applications/reactivity), with IHC images from rat and mouse brain paraffin sections (A01934-2 image captions). M01934 is listed for IHC and IF/ICC in human, mouse, and rat (catalog: M01934 applications/reactivity); no IHC or IF image is supplied for it (catalog: M01934 image alts).

Which to pick: For tissue IHC, choose polyclonal A01934-2 for its rat and mouse brain paraffin-section examples; the captions do not report the fixative (catalog: A01934-2 dilution raw; A01934-2 image captions). For IF/ICC, choose monoclonal M01934, clone 29K30, based on its application listing; no IF image is supplied (catalog: M01934 title/applications/IF image alts). For cross-species work, both list human, mouse, and rat reactivity, while A01934-2 has supplied IHC images only for rat and mouse brain (catalog: reactivity; A01934-2 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P33176 (KINH_HUMAN, Kinesin-1 heavy chain).
  2. Human Protein Atlas. KIF5B tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. KIF5B subcellular location (ICC-IF): Mainly localized to the cytosol and centriolar satellites. In addition localized to the end piece..
  4. Human Protein Atlas. KIF5B antibody validation summary (3 antibodies).
  5. Targeted inactivation of kinesin-1 in pancreatic β-cells in vivo leads to insulin secretory deficiency. Diabetes 2011 — PMC3012189.
  6. Quantitative Proteomics Reveals Association of Neuron Projection Development Genes ARF4, KIF5B, and RAB8A With Hirschsprung Disease. Molecular & cellular proteomics : MCP 2021 — PMC7950107.
  7. Analysis of Kif5b expression during mouse kidney development. PloS one 2015 — PMC4401754.
  8. KIF5B-RET Fusion gene may coincide oncogenic mutations of EGFR or KRAS gene in lung adenocarcinomas. Diagnostic pathology 2015 — PMC4535765.
  9. PubMed PMID:1607388 — UniProt-cited evidence.
  10. PubMed PMID:15164054 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.