KPNB1 / Importin subunit beta-1 · IHC design guide

Design Immunohistochemistry for KPNB1

Plan chromogenic KPNB1 IHC on paraffin sections using the IHC-validated antibody (datasheet M01851-2). Compare cytoplasmic and nuclear staining across cell types, using high staining in kidney glomerular cells as a reference (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for KPNB1 (IHC for KPNB1): expected localisation Cytoplasmic and nuclear staining (HPA tissue IHC), antibody M01851-2, validated IHC image, and IHC protocol steps
Printable KPNB1 IHC protocol sheet — expected localisation Cytoplasmic and nuclear staining (HPA tissue IHC), antibody M01851-2, controls and protocol steps. Open the full KPNB1 IHC guide →

KPNB1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear staining (HPA tissue IHC)
Staining pattern Cytoplasmic/nuclear signal; high in glomerular cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M01851-2)
Positive control ⓘ Caudate+4 more · see all
Negative control ⓘ Liver+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation Intensity varies by cell type (HPA tissue IHC)
Isoform / epitope 2 isoforms; epitope differences are unspecified (UniProt)
Section 1

Recommended KPNB1 IHC & IF Protocols

The catalog antibody uses EDTA pH 8.0 heat retrieval (datasheet M01851-2). The published gastric cancer protocol below uses pH 9.0 retrieval (PMC9808660).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human thyroiditis tissue; fixative not specified (datasheet M01851-2)
FixationImage fixative and duration unreported (datasheet M01851-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M01851-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M01851-2)
Primary antibodyMouse monoclonal (clone 3I11F2) anti-KPNB1, 2 μg/ml (datasheet M01851-2)
Primary incubationOvernight at 4 °C (datasheet M01851-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M01851-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultKPNB1-positive staining in neuronal cells of caudate (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic and nuclear expression. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet M01851-2); compare pH 9.0 retrieval during optimization (PMC9808660).
Section 2

What Is the Expected KPNB1 Staining Pattern?

KPNB1 should show cytoplasmic and nuclear-associated staining across many cell types, with prominent signal in selected cells such as kidney glomerular cells and testis pachytene spermatocytes (HPA: ubiquitous cytoplasmic and nuclear expression; High in those cells). Its nuclear-envelope and cytoplasmic locations fit a transport protein without a transmembrane segment (UniProt Q14974: location, topology). Treat tissue comparisons cautiously: HPA rates its IHC evidence Supported, with medium consistency between staining and RNA expression (HPA: reliability).

What am I looking at on my slide?
Cytoplasmic staining with nuclear-associated signal in glomerular cells or pachytene spermatocytes.This fits the expected compartments and two High-staining cell populations (UniProt Q14974: location; HPA: tissue IHC). Judge intensity against cells in the same section; a chromogenic IHC section may not resolve a thin nuclear rim (general IHC practice).
A sharp plasma-membrane-only or extracellular pattern, without convincing cytoplasmic or nuclear-associated signal.That distribution conflicts with the reported locations; inspect morphology and controls before assigning it to KPNB1 (UniProt Q14974: location, no transmembrane segment; HPA: tissue profile). Nuclear-envelope signal is a different observation from plasma-membrane signal (HPA: subcellular ICC-IF).
Strong staining confined to cholangiocytes, parathyroid glandular cells, or vaginal squamous epithelial cells.These specific populations were Not detected in HPA tissue IHC, so check antibody cross-reactivity or endogenous chromogen activity (HPA: tissue IHC; general IHC practice). Other cells in those tissues may still stain; the negative calls apply only to the listed populations (HPA: tissue IHC).
Diffuse chromogen over nuclei, stroma, and blank regions, obscuring cell boundaries.An even haze is less interpretable than compartmental cell staining; it can arise from nonspecific binding, incomplete blocking or washing, or detection background (general IHC practice). Do not score intensity until a control establishes the background level (general IHC practice).
No convincing signal in adequately sampled glomerular cells or pachytene spermatocytes.Both are High in HPA tissue IHC, making them useful positive-reference populations (HPA: tissue IHC). First review section quality and detection controls, then optimize general IHC conditions; absence alone cannot establish loss of KPNB1 (general IHC practice).
💡Expected KPNB1 appearanceCall a section positive when cells show cytoplasmic and nuclear-associated chromogen, with strong signal plausible in glomerular cells or pachytene spermatocytes (UniProt Q14974: location; HPA: tissue IHC); isolated plasma-membrane or diffuse background staining warrants review (general IHC practice).
How each factor affects the staining
Tissue and cell selectionHPA reports High staining in caudate neuronal cells, cerebellar molecular-layer cell nuclei, glomerular cells, and pachytene spermatocytes; several glandular populations are Low or Not detected (HPA: tissue IHC). Interpret the named cell population, not the tissue as uniformly positive or negative (HPA: tissue IHC).
IHC antibody evidenceHPA029878 and CAB034449 have Supported IHC validation; HPA050302 has no listed IHC status (HPA: antibody validation). HPA's overall tissue evidence has medium staining–RNA consistency, so a discrepant cell pattern merits controls and independent review (HPA: tissue reliability).
Protein architecture and isoformsUniProt lists a single 1–876 chain, no signal peptide or propeptide, no transmembrane segment, and two isoforms (UniProt Q14974: processing, topology, isoforms). These facts support an intracellular interpretation; they do not identify which isoform an unspecified antibody recognizes (UniProt Q14974: record).
Antigen retrieval and detectionRetrieval conditions, antibody dilution, and chromogen controls require validation for the chosen IHC-validated antibody (general IHC practice). Neither HPA tissue levels nor UniProt topology establishes KPNB1-specific fixation sensitivity or an optimal retrieval condition (HPA: tissue IHC; UniProt Q14974: topology).
IF/ICC Q&A: what location should a separate IF guide assess?A nuclear-membrane-enriched pattern with additional nucleoplasm and cytosol is reported by HPA ICC-IF; HPA029878 and HPA050302 have Enhanced ICC validation (HPA: subcellular ICC-IF, antibody validation). This is localisation evidence, not an IHC-P protocol or a guarantee of identical chromogenic resolution (general IHC practice).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive glomerular cells or pachytene spermatocytes have no chromogen.The run, tissue preservation, detection, or antibody conditions may have failed; HPA reports these cells as High (HPA: tissue IHC; general IHC practice).Check tissue morphology, reagent controls, and a working positive section; then validate retrieval and antibody conditions for the selected reagent (general IHC practice).
Staining is faint in salivary, small-intestinal, or prostate glandular cells.Those named cell populations are Low in HPA tissue IHC, so weak signal can fit the reference pattern (HPA: tissue IHC).Compare a High-reference cell population on a suitable control section before increasing detection sensitivity; preserve comparable scoring conditions (HPA: tissue IHC; general IHC practice).
Cholangiocytes stain strongly while expected positive cells stain weakly.HPA lists cholangiocytes as Not detected; cross-reactivity or detection background is possible (HPA: tissue IHC; general IHC practice).Review cell identity and staining boundaries; run appropriate primary-omission and detection controls, and assess another IHC-supported antibody if available (general IHC practice; HPA: antibody validation).
A brown haze covers tissue and blank areas.Nonspecific antibody binding, inadequate washing, or endogenous detection activity can obscure a true cell pattern (general IHC practice).Inspect a primary-omission control, strengthen the relevant blocking or washing step, and score only after background is controlled (general IHC practice).
Only a crisp cell-surface rim appears.Plasma-membrane-only signal conflicts with KPNB1's reported cytoplasmic and nuclear-envelope distribution (UniProt Q14974: location, topology).Distinguish cell surface from a nuclear rim using morphology and counterstain; review controls and antibody specificity before calling it positive (general IHC practice; HPA: subcellular ICC-IF).
A nuclear rim appears in IF but is indistinct in chromogenic IHC.HPA ICC-IF highlights the nuclear membrane, while section thickness and chromogenic resolution can blur a fine rim (HPA: subcellular ICC-IF; general IHC practice).For IHC, assess the broader cytoplasmic and nuclear-associated pattern against tissue controls; use the separate IF/ICC guide for finer compartment assessment (HPA: tissue IHC, subcellular ICC-IF).

Sample controls for KPNB1 IHC & IF

🧪Run kidney first: cells in glomeruli should stain strongly (HPA: High in cells in glomeruli). Use liver cholangiocytes as the tissue negative (HPA: Not detected in cholangiocytes); the kidney slide has no HPA-verified target-negative cell type, so treat any less-stained neighboring cells as a comparison, not a confirmed negative.
Positive control tissue: Caudate (Neuronal cells, HPA High)
Negative control tissue: Liver (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show KPNB1 in A-431, U-251MG, U2OS, CACO-2, HEK293, HeLa BAC 5737, HeLa , NIH 3T3, with annotated localisation: Nuclear membrane (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched mouse IgG isotype control (selected-SKU caption: mouse primary antibody); use KPNB1 knockout material, if available, as a biological specificity control. For chromogenic kidney IHC, block endogenous peroxidase and check for background before interpreting DAB staining (selected-SKU caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported in the supplied evidence; the selected-SKU paraffin-section caption does not state a fixative (selected-SKU caption: fixative unreported). Heat retrieval with EDTA at pH 8.0 was used in the reported thyroiditis IHC example, but retrieval dependence for kidney is unreported (selected-SKU caption: EDTA pH 8.0 in thyroiditis). The supplied evidence does not establish that frozen sections or IF are easier; for IF, nuclear membrane staining with additional nucleoplasmic and cytosolic signal is a localisation reference (HPA subcellular: nuclear membrane, nucleoplasm and cytosol).

HPA tissue IHC evidence for KPNB1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebellum Molecular layer cells - nucleus High Protein (IHC) HPA →
Kidney Cells in glomeruli High Protein (IHC) HPA →
Testis Pachytene spermatocytes High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Parathyroid gland Glandular cells Not detected Protein (IHC) HPA →
Vagina Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced KPNB1 IHC Tips

Troubleshoot KPNB1 staining by checking retrieval, compartment pattern and controls before comparing signal across paraffin sections (datasheet M01851-2; HPA tissue IHC).

What should I change when KPNB1 staining is weak after antigen retrieval?
Begin with heat-mediated EDTA at pH 8.0 for paraffin-section KPNB1 IHC (datasheet M01851-2). The selected image used this retrieval before 2 μg/ml primary antibody overnight at 4°C, so reproduce that sequence when troubleshooting weak staining (caption M01851-2). If signal remains weak, compare heat exposures on adjacent sections while keeping antibody concentration and DAB development constant; excessive heating can damage morphology (standard IHC practice). Only then trial citrate at pH 6.0 as a fallback, and assess whether signal remains cytoplasmic or near the nuclear envelope as expected for KPNB1 (UniProt Q14974; HPA subcellular).
Could fixation explain inconsistent KPNB1 staining between paraffin sections?
KPNB1-specific fixation sensitivity is unknown: the selected paraffin-section caption does not report a fixative (caption M01851-2). Record the fixative, fixation duration and processing history for each specimen before attributing a staining difference to the antibody (standard IHC practice). Compare matched sections processed together, using the documented EDTA retrieval at pH 8.0 and the same detection conditions (datasheet M01851-2; standard IHC practice). If one batch is weak, check preservation and morphology alongside a positive control; tissue expression patterns and KPNB1 topology cannot establish a fixation effect (standard IHC practice; HPA tissue IHC; UniProt Q14974).
Should KPNB1 appear in nuclei, cytoplasm or at the nuclear rim?
Expect a cytoplasmic component and signal associated with the nuclear envelope in KPNB1 IHC (UniProt Q14974 subcellular). The HPA tissue profile reports ubiquitous cytoplasmic and nuclear expression, while its subcellular profile emphasizes the nuclear membrane with additional nucleoplasmic and cytosolic signal (HPA tissue IHC; HPA subcellular). Assess rim staining against a hematoxylin counterstain and inspect several intact cells, because section plane and dense nuclei can make a perinuclear pattern difficult to resolve in chromogenic IHC (standard IHC practice). A purely extracellular deposit or signal confined to damaged section edges warrants a background check before calling it KPNB1 (standard IHC practice).
Can an epitope or isoform difference explain discordant KPNB1 IHC patterns?
KPNB1 has 2 annotated isoforms, and its importin N-terminal domain spans residues 21–101 (UniProt Q14974). The supplied caption does not map the M01851-2 epitope or establish which isoforms it detects, so an isoform-specific interpretation would require additional antibody documentation (caption M01851-2; UniProt Q14974). KPNB1 has annotated modifications including phosphoserine 12 and acetyllysines 211, 835 and 867; their effect on this antibody's tissue staining is unknown (UniProt Q14974). When antibodies disagree, compare their documented immunogens and staining compartments on matched sections before attributing the difference to a particular isoform or modification (standard IHC practice).
How can I investigate KPNB1 localisation by IF alongside this IHC guide?
Use IF as a separate localisation check, pairing KPNB1 with a validated marker for the expected cell population, such as neuronal cells in caudate (HPA tissue IHC). Choose a fluorophore channel with low tissue autofluorescence, then inspect each channel separately for bleed-through before interpreting overlap (standard IF practice). Because KPNB1 has no transmembrane segment and occurs at the nuclear membrane and in the cytosol, intracellular epitope access may need permeabilisation; the antibody's precise epitope side is not supplied (UniProt Q14974; HPA subcellular; caption M01851-2). Optimise mild permeabilisation against morphology and include single-stain controls rather than transferring the paraffin IHC conditions directly to IF (standard IF practice).
What should I check when DAB staining obscures KPNB1-positive cells?
Start with a no-primary control to separate secondary-reagent or tissue background from antibody-dependent staining (standard IHC practice). The selected paraffin-section image used 10% goat serum block, a peroxidase-conjugated anti-mouse secondary and DAB development; its caption does not state a peroxidase-block step (caption M01851-2). Include an appropriate endogenous-peroxidase block and compare shorter DAB development on matched sections if diffuse brown signal persists (standard chromogenic IHC practice). Judge any remaining staining against intact cytoplasmic and nuclear-envelope patterns, since KPNB1 is reported in those compartments and nonspecific deposits can obscure that distribution (UniProt Q14974; HPA subcellular; standard IHC practice).
How should I score KPNB1 IHC when nuclear and cytoplasmic signals differ? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because KPNB1 can appear in cytoplasm and at the nuclear envelope (UniProt Q14974 subcellular). For cell-level staining, record the percentage of positive cells and an H-score from intensity categories; report nuclear-associated and cytoplasmic scores separately where morphology permits (standard IHC scoring practice). If counting positive cells per mm², normalise to analysable tissue area and retain the total eligible-cell count so cellularity differences remain visible (standard image-analysis practice). Keep retrieval, DAB development, illumination and positivity thresholds consistent across specimens, and document excluded necrotic or damaged regions before comparing scores (standard IHC practice).
How do I distinguish convincing KPNB1 staining from artefact?
A convincing result follows intact cellular boundaries and shows cytoplasmic, nuclear-associated or nuclear-membrane signal in an expected cell population (UniProt Q14974; HPA tissue IHC; HPA subcellular). For example, HPA reports high staining in caudate neuronal cells and cerebellar molecular-layer cell nuclei, but its tissue-IHC reliability is Supported with medium RNA concordance (HPA tissue IHC). Signal restricted to necrosis, torn edges or extracellular material, or present in a no-primary control, should prompt an artefact check (standard IHC practice). Confirm uncertain staining with matched-section controls and morphology before interpreting a compartment shift as altered KPNB1 transport (standard IHC practice; UniProt Q14974 function).
Boster reagents

Best KPNB1 / Importin subunit beta-1 IHC Antibodies

The catalog includes paraffin-section IHC images with M01851-2 and CACO-2 IF images with both antibodies; both list Human, Mouse and Rat reactivity (catalog applications, reactivity and image captions).

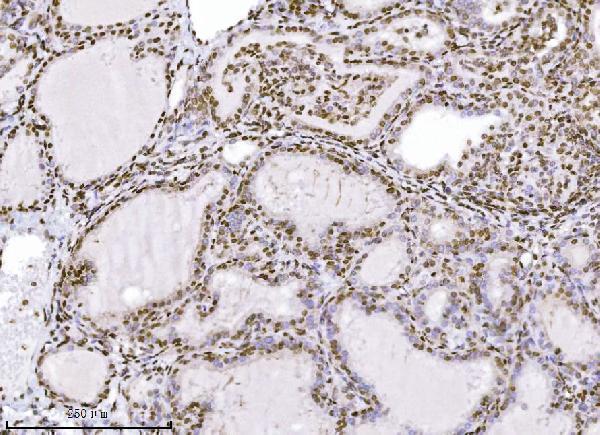
Real IHC data IHC analysis of KPNB1 using anti-KPNB1 antibody (M01851-2). KPNB1 was detected in a paraffin-embedded section of human thyroiditis tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml mouse anti-KPNB1 Antibody (M01851-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Mouse IgG Super Vision Assay Kit (Catalog # SV0001) with DAB as the chromogen.
Anti-KPNB1 Antibody ® (monoclonal, 3I11F2)
Cat # M01851-2
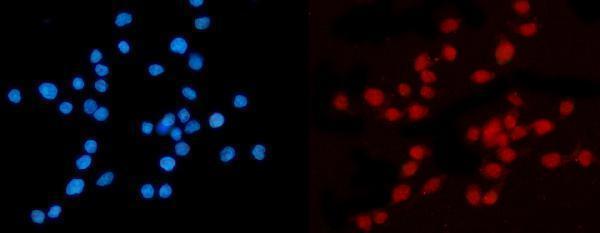
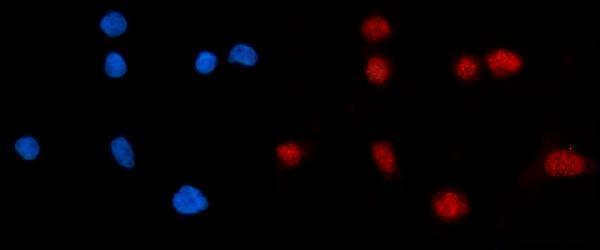
Real IF data IF analysis of KPNB1 using anti-KPNB1 antibody (A01851-2). KPNB1 was detected in an immunocytochemical section of CACO-2 cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 5 μg/mL rabbit anti-KPNB1 Antibody (A01851-2) overnight at 4°C. DyLight®594 Conjugated Goat Anti-Rabbit IgG (BA1142) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-KPNB1 Antibody ®
Cat # A01851-2

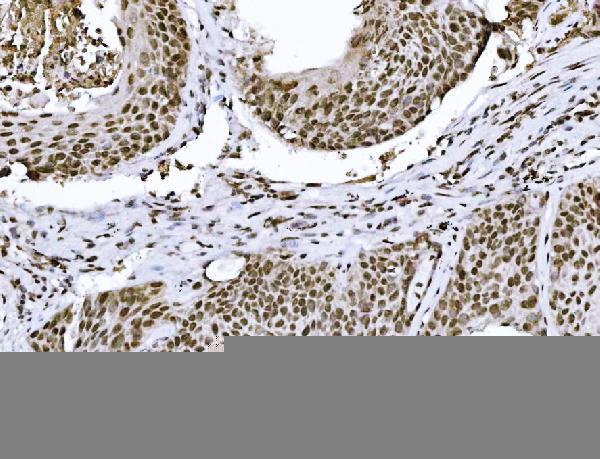
M01851-2 lists IHC and IF applications, with paraffin-section IHC images from human thyroiditis, squamous cell lung carcinoma, renal carcinoma and breast cancer tissue (catalog applications and M01851-2 IHC captions). A01851-2 lists IF/ICC applications and has a CACO-2 IF image (catalog applications and A01851-2 IF caption).

Which to pick: Choose mouse monoclonal M01851-2 for tissue IHC: its images show staining of human paraffin sections after EDTA pH 8.0 retrieval, while the fixative is unreported (catalog clone and M01851-2 IHC captions). Choose rabbit A01851-2 for IF/ICC when a rabbit primary suits the detection setup; its IF image uses CACO-2 cells (catalog host and A01851-2 IF caption). Both list Human, Mouse and Rat reactivity, but the supplied IHC images show human tissue and the supplied IF images show CACO-2 cells (catalog reactivity and image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q14974 (IMB1_HUMAN, Importin subunit beta-1).
  2. Human Protein Atlas. KPNB1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. KPNB1 subcellular location (ICC-IF): Mainly localized to the nuclear membrane. In addition localized to the nucleoplasm and cytosol..
  4. Human Protein Atlas. KPNB1 antibody validation summary (3 antibodies).
  5. Expression of Karyopherin Alpha 2 and Karyopherin Beta 1 Correlate with Poor Prognosis in Gastric Cancer. Oncology 2022 — PMC9808660.
  6. EZH2-miR-30d-KPNB1 pathway regulates malignant peripheral nerve sheath tumour cell survival and tumourigenesis. The Journal of pathology 2014 — PMC4166508.
  7. Multi-omics analysis identifies a major histocompatibility complex class II-associated antigen-presenting cancer-associated fibroblast-like state linked to the nuclear factor erythroid 2-related factor 2-karyopherin subunit beta 1 axis in nonsmall cell lung cancer. Journal of cell communication and signaling 2026 — PMC13238553.
  8. KPNB1-ATF4 induces BNIP3-dependent mitophagy to drive odontoblastic differentiation in dental pulp stem cells. Cellular & molecular biology letters 2024 — PMC11600598.
  9. PubMed PMID:7615630 — UniProt-cited evidence.
  10. PubMed PMID:7627554 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.