KRT4 / Keratin, type II cytoskeletal 4 · IHC design guide

Design Immunohistochemistry for KRT4

Plan KRT4 paraffin IHC around cytoplasmic staining in non-keratinized squamous and airway epithelia (HPA tissue IHC). Use esophageal squamous epithelium as a positive reference and assess unexpected signal cautiously because presumed off-target binding was observed (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for KRT4 (IHC for KRT4): expected localisation Cytoplasmic staining in squamous and airway epithelia (HPA tissue IHC), antibody A07410-3, validated IHC image, and IHC protocol steps
Printable KRT4 IHC protocol sheet — expected localisation Cytoplasmic staining in squamous and airway epithelia (HPA tissue IHC), antibody A07410-3, controls and protocol steps. Open the full KRT4 IHC guide →

KRT4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in squamous and airway epithelia (HPA tissue IHC)
Staining pattern Cytoplasmic signal in non-keratinized squamous and airway epithelia (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A07410-3)
Positive control ⓘ Cervix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet A07410-3); verify before use.
Caveat Presumed off-target staining may complicate interpretation (HPA tissue IHC)
Regulation Suprabasal enriched; basal lowest (UniProt)
Isoform / epitope No isoforms or processing-related epitope shifts (UniProt)
Section 1

Recommended KRT4 IHC & IF Protocols

The catalog antibody protocol is followed by published KRT4 IHC protocols for cervical and oral squamous tissue (PMC4026928; PMC13056625).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human endometrioid adenocarcinoma tissue; fixative not specified (datasheet A07410-3)
FixationImage fixative and duration unreported (datasheet A07410-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A07410-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A07410-3)
Primary antibodyRabbit anti-KRT4, 2-5 μg/ml (datasheet A07410-3)
Primary incubationOvernight at 4 °C (datasheet A07410-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A07410-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultKRT4-positive staining in glandular cells of cervix (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in non-keratinized squamous epithelia and airway epithelia. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet A07410-3). The cervical study used citrate at pH 6.0 (PMC4026928).
Section 2

What Is the Expected KRT4 Staining Pattern?

KRT4 should stain the cytoplasm of non-keratinized squamous epithelial cells, particularly in esophagus, oral mucosa, tonsil, and vagina (HPA tissue IHC: Medium staining). Its filamentous distribution fits its role in keratin intermediate filaments and its lack of a transmembrane segment (UniProt P19013: function and topology; HPA subcellular: intermediate filaments). HPA rates the tissue IHC pattern Enhanced, while reporting medium consistency with RNA data and disregarded presumed off-target binding (HPA tissue IHC: reliability).

What am I looking at on my slide?
Cytoplasmic staining in suprabasal esophageal squamous cells, with weaker basal staining.This fits KRT4 distribution: UniProt reports protein in the suprabasal layer and the lowest esophageal expression in the basal layer (UniProt P19013: tissue specificity). HPA reports Medium staining in esophageal squamous epithelial cells (HPA tissue IHC: Esophagus).
Signal is predominantly nuclear or outlines cell membranes without cytoplasmic staining.That distribution conflicts with the expected cytoplasmic, intermediate-filament pattern (HPA tissue IHC: profile; HPA subcellular: supported location). Check staining controls and review the slide for artefact before interpreting it as KRT4 (general IHC practice).
Strong staining appears in adipocytes or hematopoietic cells.HPA reports KRT4 as Not detected in adipocytes from adipose tissue and hematopoietic cells from bone marrow (HPA tissue IHC: negative examples). Investigate cross-reactivity or detection-system activity; this pattern alone does not identify which is responsible (general IHC practice).
Chromogen is spread across the section rather than confined to expected epithelial cells.Widespread background obscures whether epithelial cytoplasm is specifically positive. Compare a no-primary control, blocking, and detection steps before scoring the target pattern (general IHC practice). HPA's tissue profile describes cell-associated cytoplasmic staining (HPA tissue IHC: profile).
An esophageal squamous epithelium control has no visible staining.This is unexpected because HPA reports Medium staining there and UniProt detects KRT4 in its suprabasal layer (HPA tissue IHC: Esophagus; UniProt P19013: tissue specificity). Check the run and control integrity before treating the sample as KRT4-negative (general IHC practice).
💡Expected KRT4 appearanceCall a result positive when cytoplasmic staining is visible in non-keratinized squamous epithelial cells, typically at HPA's Medium level; isolated nuclear or membrane-only staining is discordant (HPA tissue IHC: profile and positive tissues; HPA subcellular: intermediate filaments).
How each factor affects the staining
Which tissue best demonstrates the expected pattern?Esophageal squamous epithelium combines HPA Medium staining with UniProt's suprabasal distribution (HPA tissue IHC: Esophagus; UniProt P19013: tissue specificity). Oral mucosa, tonsil, and vagina are further HPA Medium examples (HPA tissue IHC: positive tissues).
How should antibody validation affect interpretation?HPA lists HPA034881 as IHC Enhanced and CAB002154 as IHC Supported (HPA antibodies: IHC validation). The overall tissue profile is Enhanced but has only medium RNA–staining consistency and notes disregarded presumed off-target binding (HPA tissue IHC: reliability).
Does the protein architecture predict a surface stain?No transmembrane segment is annotated, and KRT4 forms intracellular intermediate-filament networks with KRT13 (UniProt P19013: topology and function). Interpret a membrane-only pattern cautiously against HPA's cytoplasmic IHC profile (HPA tissue IHC: profile).
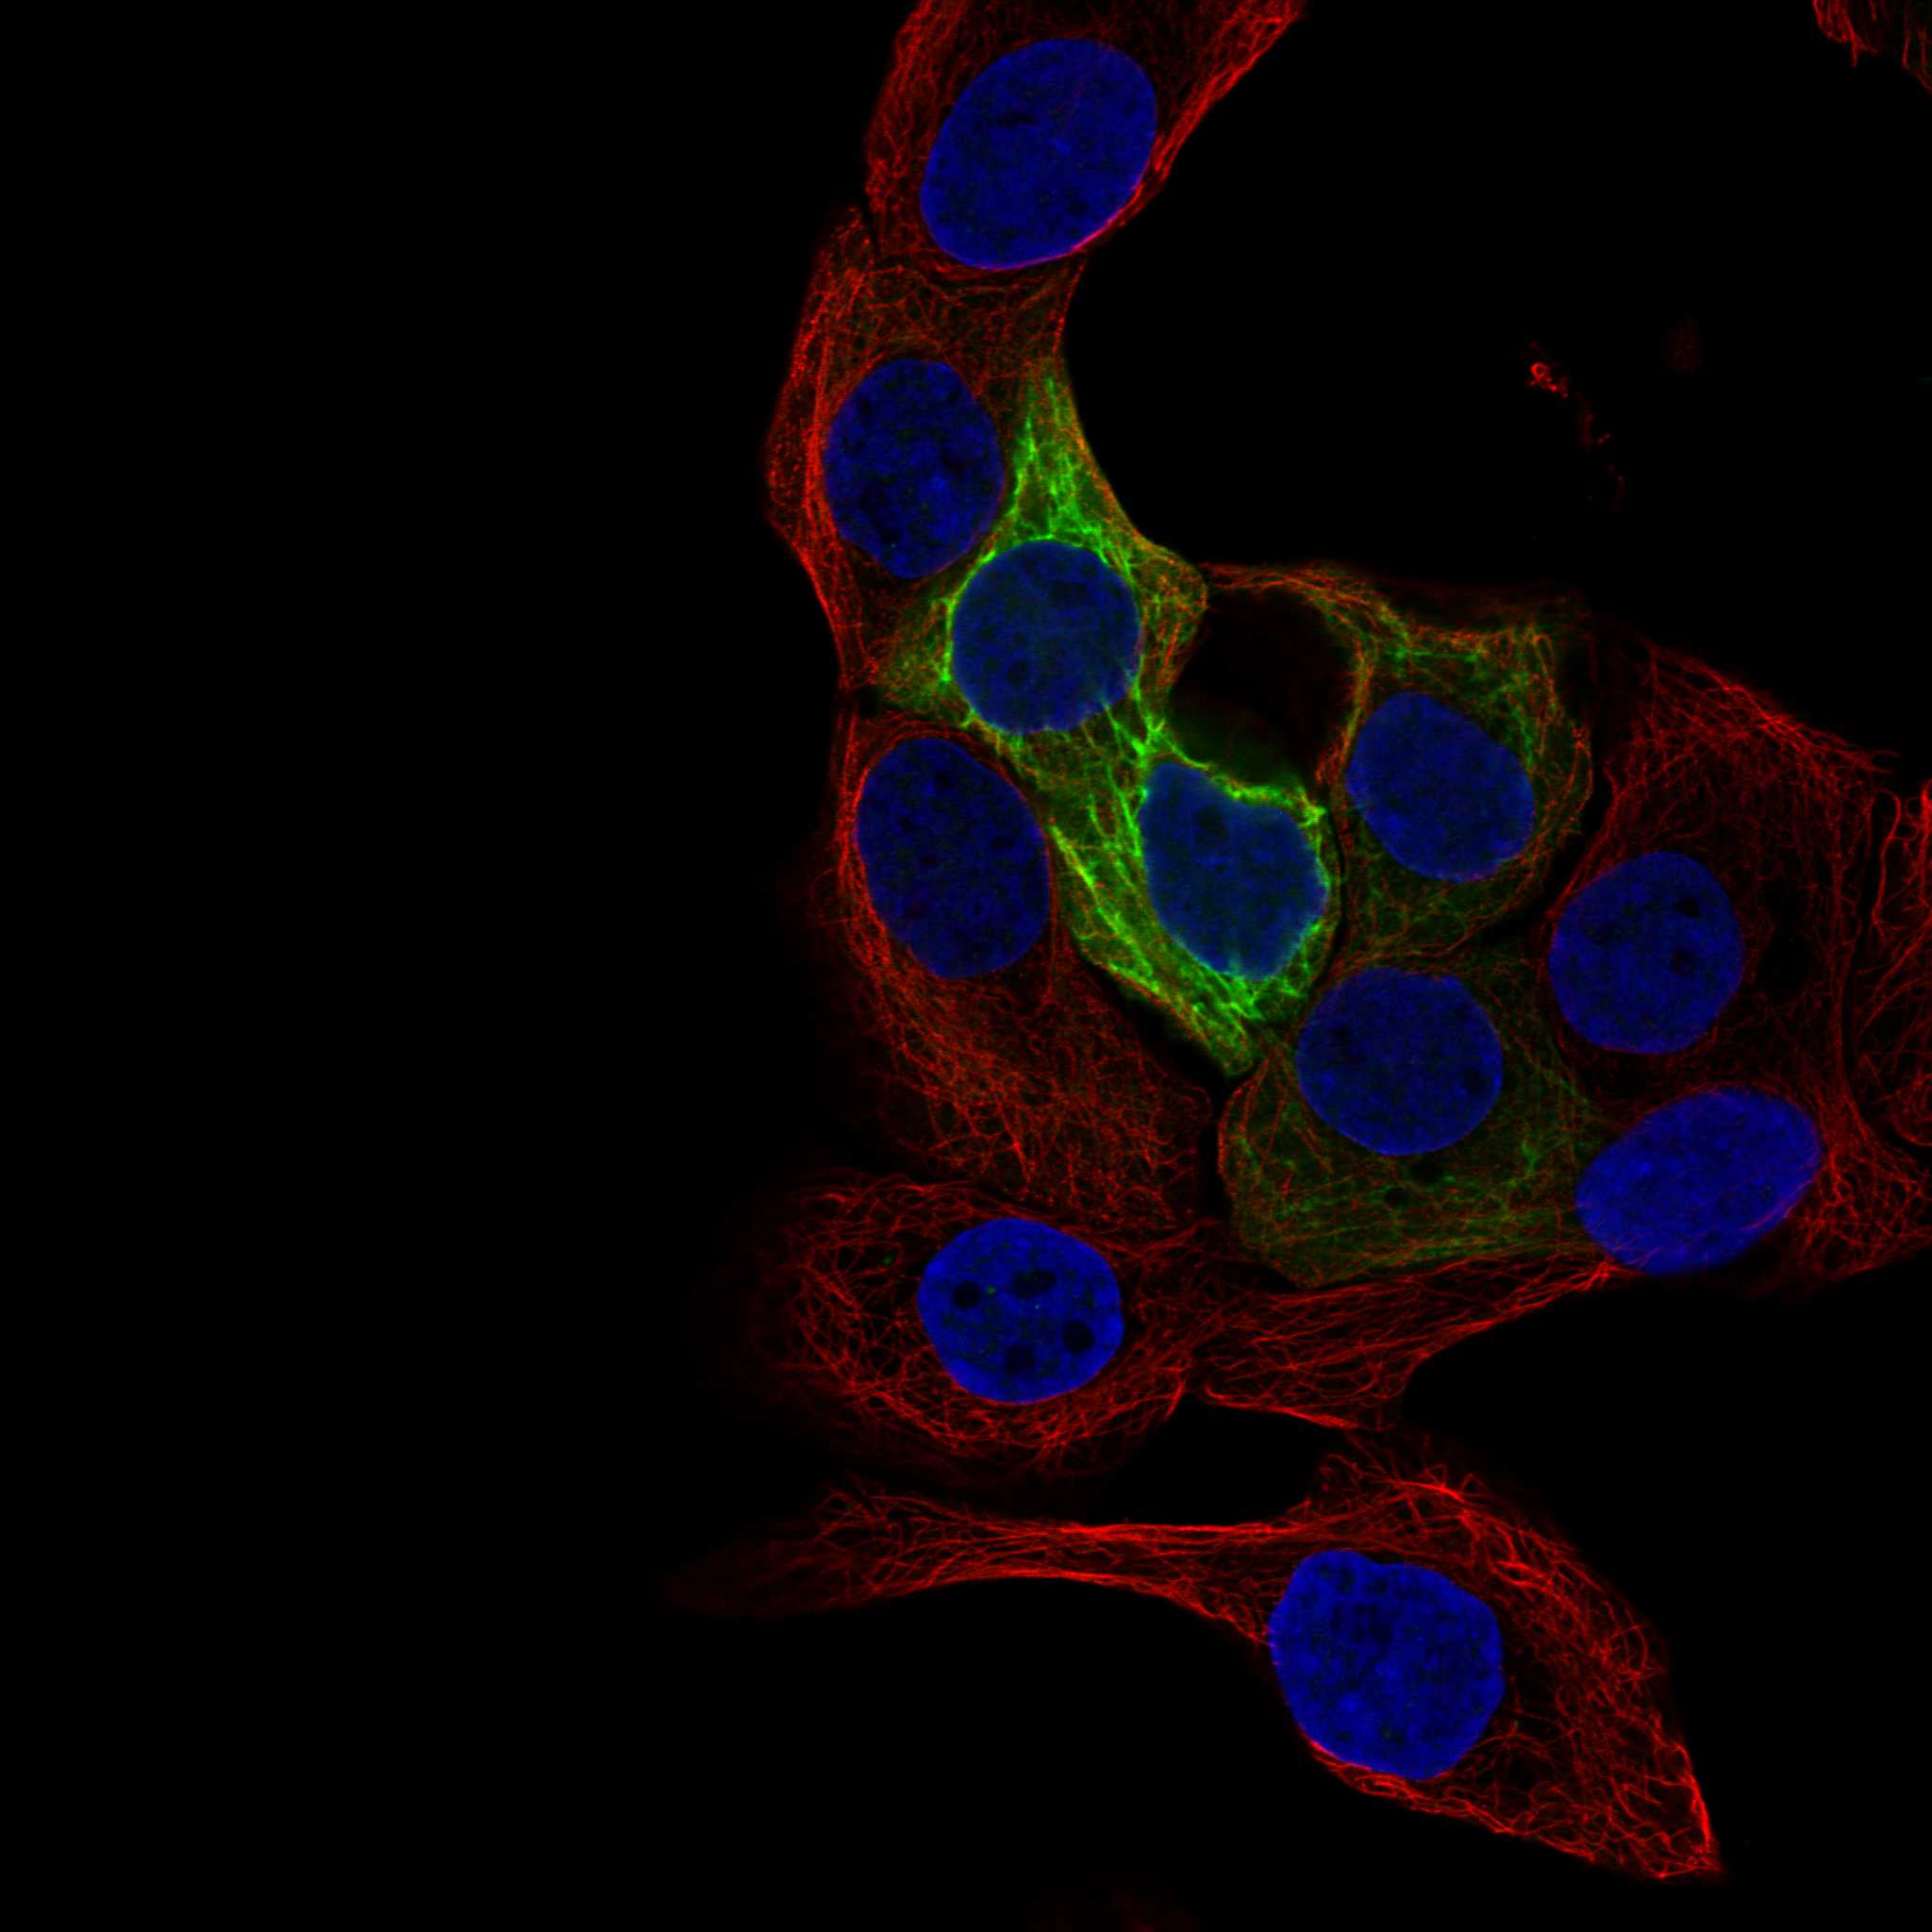
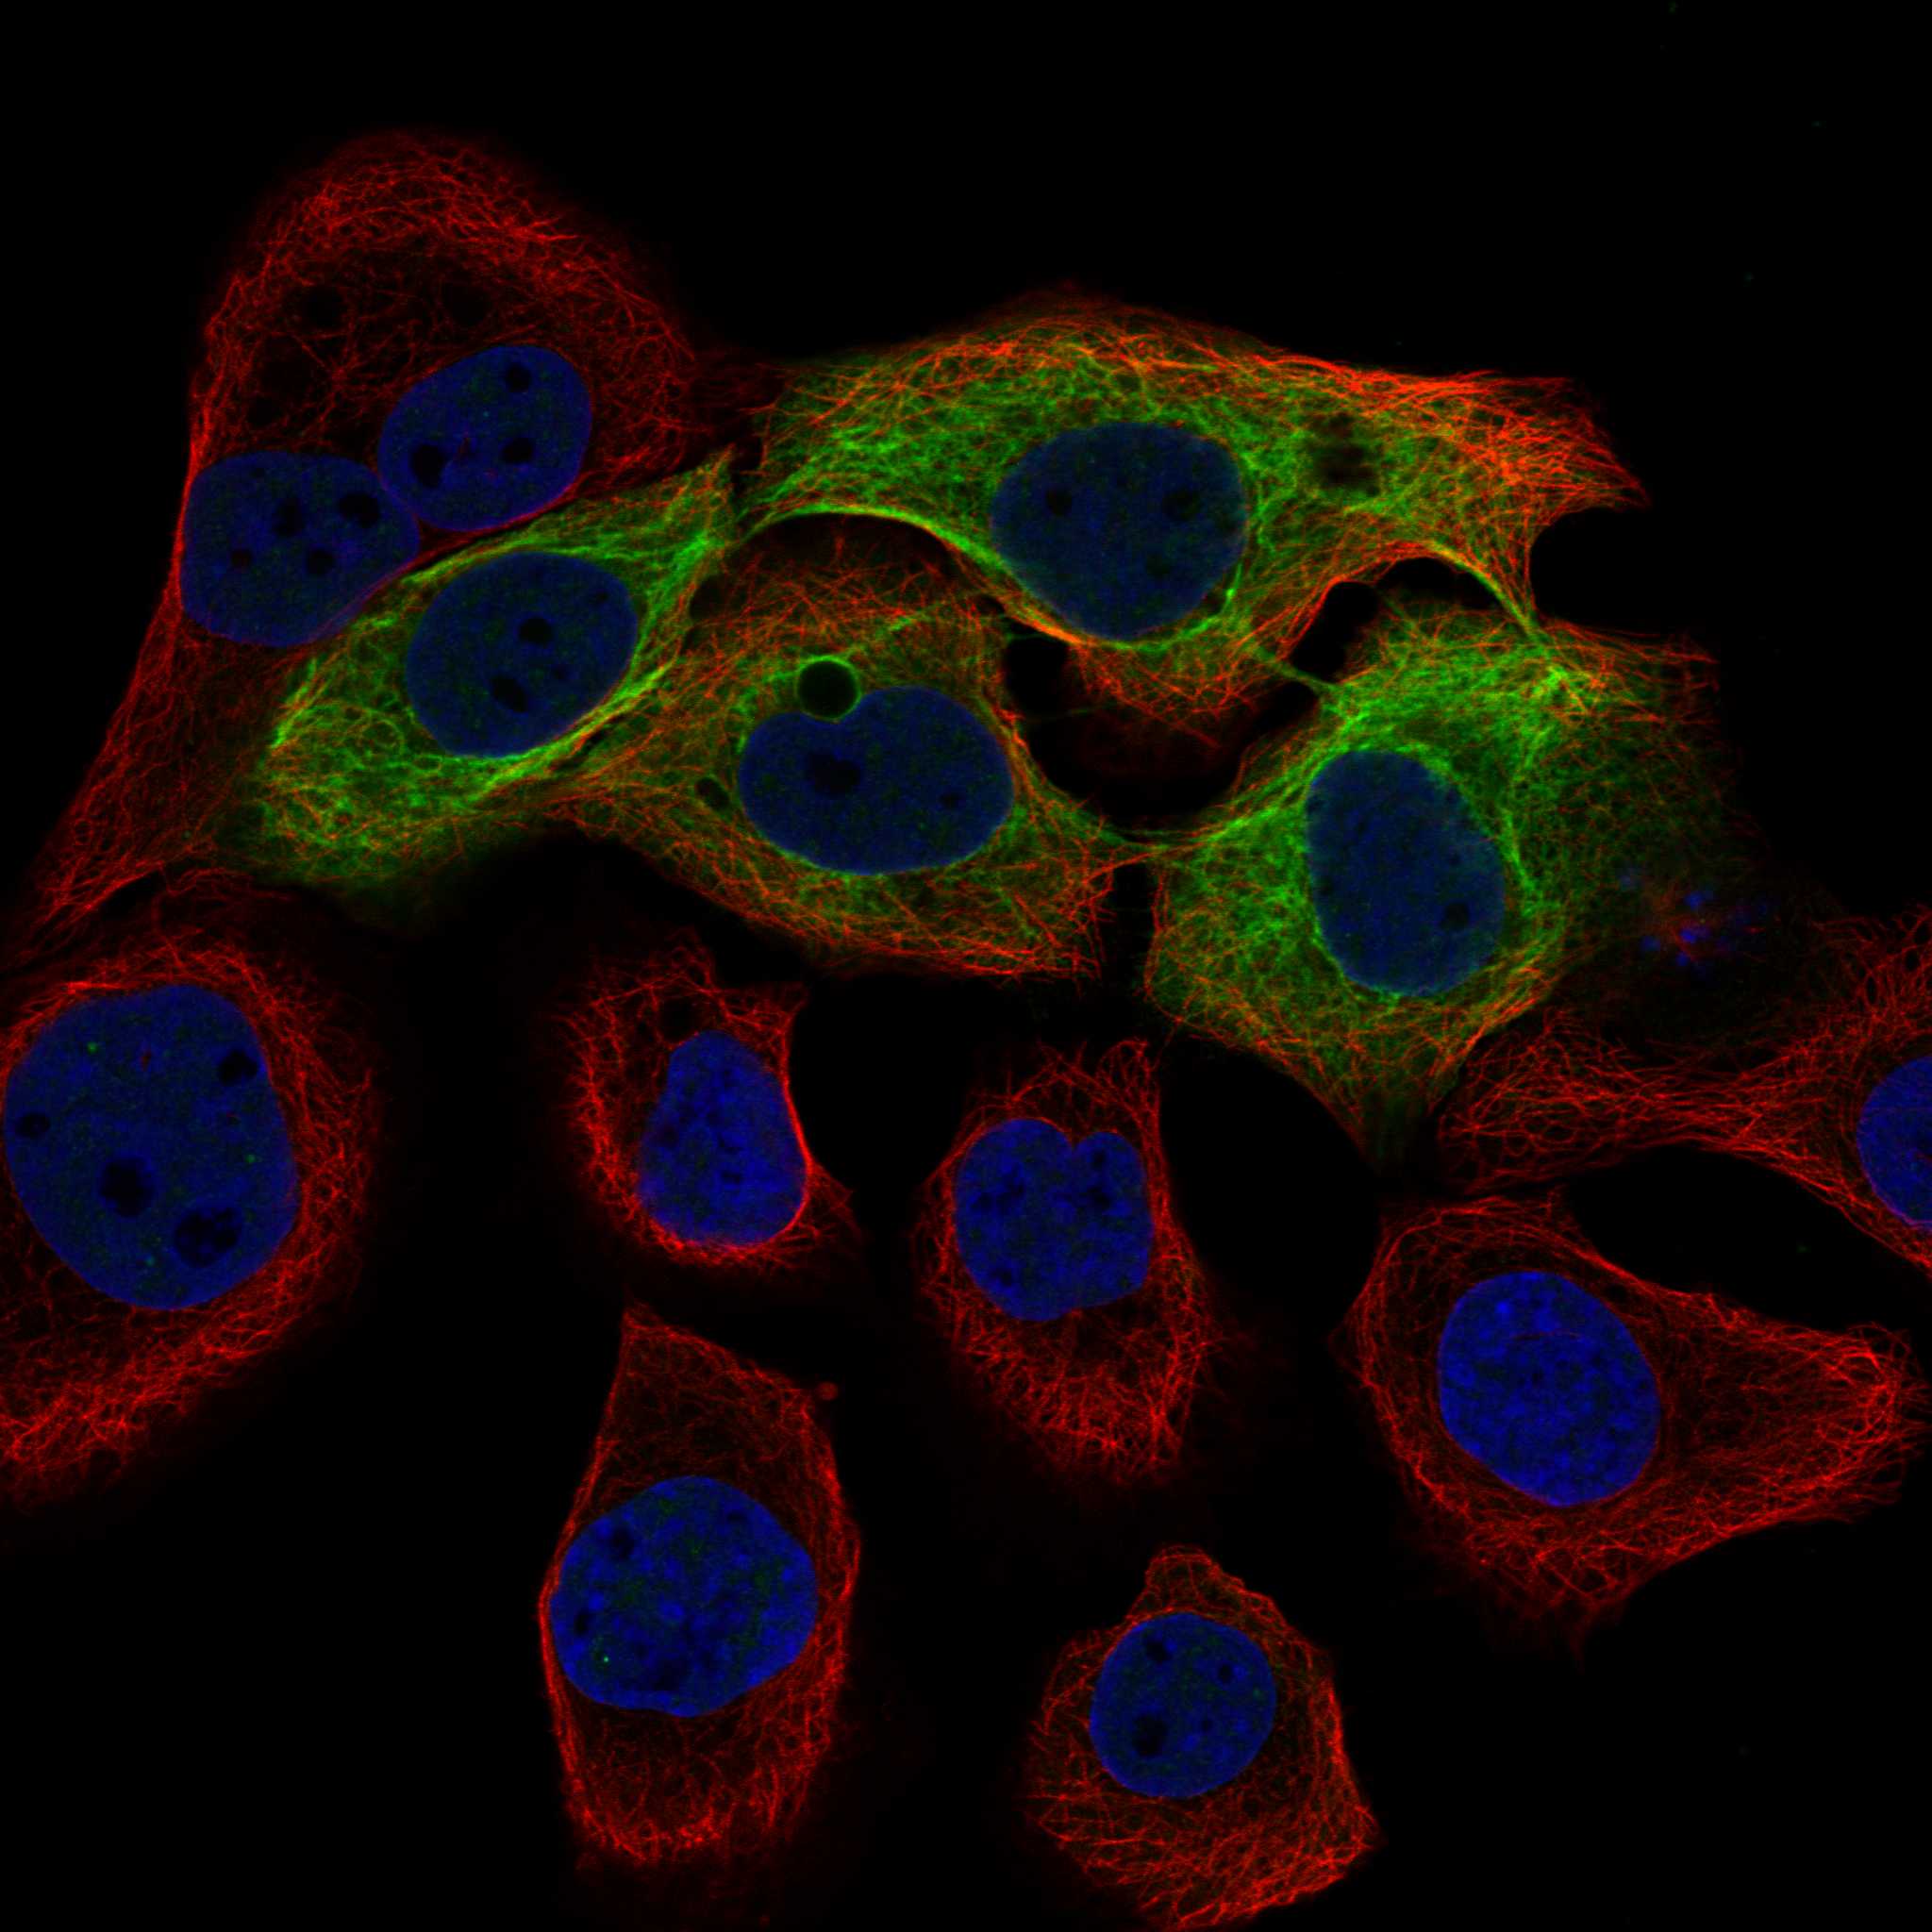
IF/ICC Q&A: where should fluorescence appear?HPA supports localization to intermediate filaments and lists HaCaT ICC-IF images; HPA034881 has ICC Approved status (HPA subcellular: location and images; HPA antibodies: ICC validation). This informs localization, not an IF/ICC protocol or an IHC dilution.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The known-positive esophageal control is blank.A staining-run failure is possible; HPA reports Medium signal in esophageal squamous epithelial cells (HPA tissue IHC: Esophagus).Verify that the primary antibody, detection reagents, and control section were included and worked as intended; review antigen retrieval against the antibody's validated IHC-P instructions (general IHC practice).
The sample is blank, but the esophageal control stains.A negative sample can be credible when the evaluated cells are outside the expected pattern; HPA reports Not detected in several specified cell types (HPA tissue IHC: negative examples).Confirm the sample's cell identity and score only the relevant compartment; do not infer whole-tissue negativity from a listed negative cell type (general IHC practice; HPA tissue IHC: cell-specific entries).
Only nuclei or cell borders stain.The distribution conflicts with HPA's cytoplasmic IHC profile and supported intermediate-filament localization (HPA tissue IHC: profile; HPA subcellular: location).Compare the control slide and antibody-specific validation, then repeat with an appropriate negative control if the discordance persists (general IHC practice).
Chromogen appears in unexpected negative cell types.Cross-reactivity or endogenous detection activity is possible; HPA reports some presumed off-target binding was disregarded (HPA tissue IHC: reliability).Run a no-primary control and inspect blocking and detection steps. Interpret any remaining staining against HPA's named cell types rather than treating it as KRT4 automatically (general IHC practice; HPA tissue IHC: profile).
Diffuse background makes epithelial cells hard to score.Non-specific staining or excess detection signal may obscure the cell-associated pattern (general IHC practice; HPA tissue IHC: cytoplasmic profile).Check control background, washing, blocking, and the validated antibody and detection conditions; score only distinguishable epithelial cytoplasm (general IHC practice).
Staining is weak in the esophageal basal layer.Basal signal can be lower than suprabasal signal; UniProt reports the lowest esophageal expression in the basal layer (UniProt P19013: tissue specificity).Compare basal and suprabasal cells within the same section before calling the run weak; use the suprabasal pattern and the positive control to assess performance (UniProt P19013: tissue specificity; general IHC practice).

Sample controls for KRT4 IHC & IF

🧪Run esophagus first: squamous epithelial cells should stain (HPA: Medium in esophageal squamous epithelial cells). Use adipose tissue as the negative, with adipocytes unstained (HPA: Not detected in adipocytes); on the esophageal slide, basal epithelial cells should stain less than suprabasal cells (UniProt P19013: lowest expression in the basal layer).
Positive control tissue: Cervix (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show KRT4 in HaCaT, with annotated localisation: Intermediate filaments (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control (selected-SKU caption: rabbit primary antibody). Use KRT4 knockout tissue or a validated peptide block as a biological negative, and quench endogenous peroxidase before HRP/DAB detection (selected-SKU caption: HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported; the selected-SKU paraffin-section caption does not state the fixative. Heat-mediated retrieval with EDTA at pH 8.0 is documented for this antibody (selected-SKU caption), but the supplied evidence does not establish whether frozen sections or IF are easier. In esophageal mucosa, inspect folds and section edges for staining artefacts when scoring the squamous epithelium (HPA: Medium in esophageal squamous epithelial cells).

HPA tissue IHC evidence for KRT4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cervix Glandular cells Medium Protein (IHC) HPA →
Esophagus Squamous epithelial cells Medium Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Medium Protein (IHC) HPA →
Tonsil Squamous epithelial cells Medium Protein (IHC) HPA →
Vagina Squamous epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced KRT4 IHC Tips

Use the catalog antibody’s paraffin section evidence as the starting point, and assess staining against KRT4’s expected epithelial and filament patterns.

Which retrieval condition should I try first for weak KRT4 staining in paraffin sections?
Start with heat mediated antigen retrieval in EDTA at pH 8.0 for paraffin section KRT4 IHC (datasheet A07410-3). The selected tissue image used this condition before incubation with 2 μg/ml primary antibody overnight at 4°C (datasheet A07410-3). If staining remains weak, check deparaffinization and compare controlled heating and cooling conditions on adjacent sections before changing buffer (standard IHC practice). Include an esophageal squamous epithelium control, where KRT4 is detected, to distinguish retrieval failure from a low expressing specimen (UniProt P19013 tissue specificity). Keep detection and exposure conditions matched across that comparison (standard IHC practice).
Could fixation explain inconsistent KRT4 staining across paraffin blocks?
The selected paraffin section caption does not report a fixative, so target specific KRT4 fixation sensitivity is unknown (datasheet A07410-3). Record each block’s fixative and fixation duration, then compare matched sections under the same EDTA pH 8.0 retrieval and detection conditions (datasheet A07410-3; standard IHC practice). Process an esophageal epithelial control alongside the affected blocks to separate a run wide staining problem from a specimen dependent one (UniProt P19013 tissue specificity; standard IHC practice). Assess tissue preservation and staining together, since damaged morphology makes epithelial layer assignment unreliable (standard IHC practice). Do not infer fixation tolerance from tissue distribution or protein topology (UniProt P19013 record).
Where should KRT4 staining appear within the tissue and the cell?
Expect cytoplasmic staining with an intermediate filament pattern in positive epithelial cells (HPA tissue IHC; HPA subcellular). In stratified mucosal squamous epithelium, compare suprabasal cells with the basal layer, where expression is lowest in the reported esophageal and exocervical distribution (UniProt P19013 tissue specificity). Esophageal, oral mucosal, vaginal, and tonsillar squamous epithelial cells are useful tissue context for this assessment (HPA tissue IHC). KRT4 has no transmembrane segment, and its reported function is in keratin filament networks, so a purely membranous rim warrants scrutiny (UniProt P19013 topology and function). Check that the counterstain resolves epithelial layers before assigning a compartment (standard IHC practice).
How should I investigate patchy staining or possible keratin cross reactivity?
The supplied record lists 0 isoforms and one KRT4 chain spanning residues 1–520; it does not identify this antibody’s epitope (UniProt P19013 record; datasheet A07410-3). Its intermediate filament rod spans residues 137–450, while an example modified residue is arginine 13 (UniProt P19013 domains and modified residues). Neither feature establishes an effect on antibody binding or retrieval without epitope mapping (UniProt P19013 record). Compare staining with an independently validated KRT4 antibody recognizing a documented distinct epitope, if available, and evaluate agreement in the same epithelial layers (standard IHC practice). Treat disagreement as a specificity question requiring controls, not as proof of an isoform (standard IHC practice).
How can paired IF help verify a KRT4 chromogenic IHC pattern?
For a paired IF assessment, multiplex KRT4 with KRT13, its reported type I keratin partner, and compare their distribution within the expected epithelium (UniProt P19013 function). Choose spectrally separated fluorophores and inspect unstained tissue channels before assigning dim signal, because tissue autofluorescence can mimic fluorescence staining (standard IF practice). Use validated mild permeabilization to reach the cytoplasmic filament network; KRT4 has no transmembrane segment and localizes to intermediate filaments (UniProt P19013 topology; HPA subcellular). Retain an appropriate nuclear counterstain to identify cell boundaries and epithelial layers (standard IF practice). The A07410-3 paraffin chromogenic image alone does not establish that antibody’s IF performance (datasheet A07410-3).
What controls help separate KRT4 staining from diffuse DAB background?
The selected paraffin image used 10% goat serum blocking, a peroxidase linked secondary incubation for 30 minutes at 37°C, and DAB development (datasheet A07410-3). Add an endogenous peroxidase block and a no primary control to assess enzyme driven color and secondary reagent background (standard chromogenic IHC practice). Compare staining in expected positive squamous epithelium with adipocytes, where KRT4 was not detected in the supplied tissue profile (HPA tissue IHC). The tissue profile also reports presumed off target binding that was disregarded, so isolated unexpected cells need corroboration (HPA tissue IHC reliability). Evaluate background before increasing primary antibody concentration (standard IHC practice).
How should I score KRT4 across uneven epithelial layers? ⚠ ANSWER MARKED FOR VERIFICATION
Define epithelial regions on the counterstain and score suprabasal and basal compartments separately, because reported KRT4 expression is lowest in the basal layer (UniProt P19013 tissue specificity; standard IHC practice). For each region, record the percentage of viable epithelial cells at intensity 0–3 and calculate an H-score from 0–300 (standard IHC scoring practice). Report the percentage positive as well, with the positivity threshold set before comparing specimens (standard IHC scoring practice). Normalize counts to viable epithelial cells or measured epithelial area rather than total section area (standard IHC practice). Keep retrieval, DAB development, and image acquisition consistent across compared sections (standard IHC practice).
When should an unexpected KRT4 positive focus be considered artefactual?
A convincing focus should show cytoplasmic filament associated staining in morphologically intact epithelial cells, consistent with KRT4’s reported localization (HPA tissue IHC; HPA subcellular). Check whether the cells fit the expected suprabasal mucosal distribution; isolated nuclear staining or a purely membranous outline is discordant with the supplied localization evidence (UniProt P19013 tissue specificity and topology; HPA subcellular). Exclude section edges, folds, and necrotic areas from interpretation because they can produce misleading chromogenic signal (standard IHC practice). Compare any unexpected focus with a no primary control and an endogenous peroxidase block (standard chromogenic IHC practice). Seek independent corroboration, since the tissue profile notes presumed off target binding (HPA tissue IHC reliability).
Boster reagents

Best KRT4 / Keratin, type II cytoskeletal 4 IHC Antibodies

Anti-KRT4 options cover human IHC and IF, with rat reactivity listed for M07410 (catalog applications/reactivity). A07410-3 has illustrated human paraffin-section IHC and IF (A07410-3 image captions).

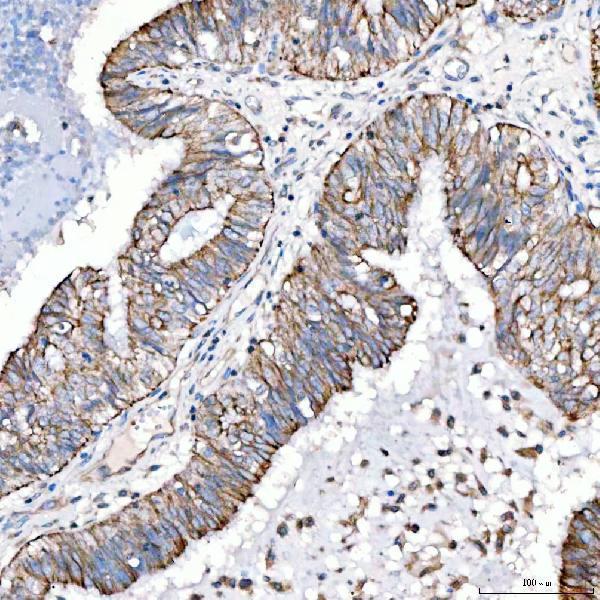
Real IHC data IHC analysis of Cytokeratin 4/KRT4 using anti-Cytokeratin 4/KRT4 antibody (A07410-3). Cytokeratin 4/KRT4 was detected in a paraffin-embedded section of human endometrioid adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Cytokeratin 4/KRT4 Antibody (A07410-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Cytokeratin 4/KRT4 Antibody ®
Cat # A07410-3

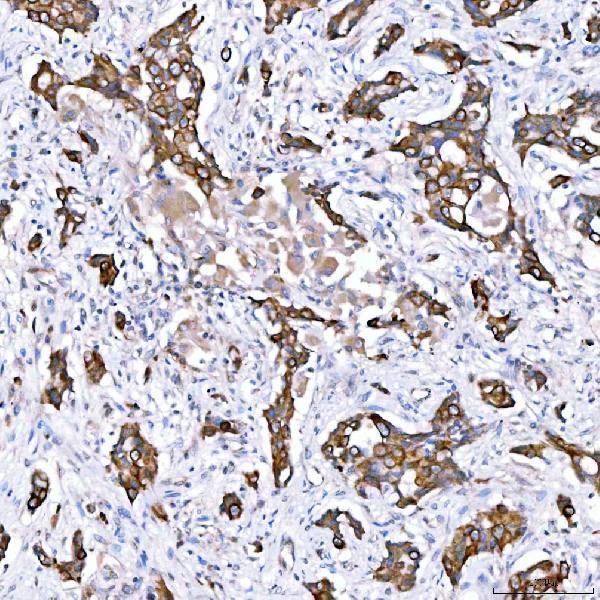
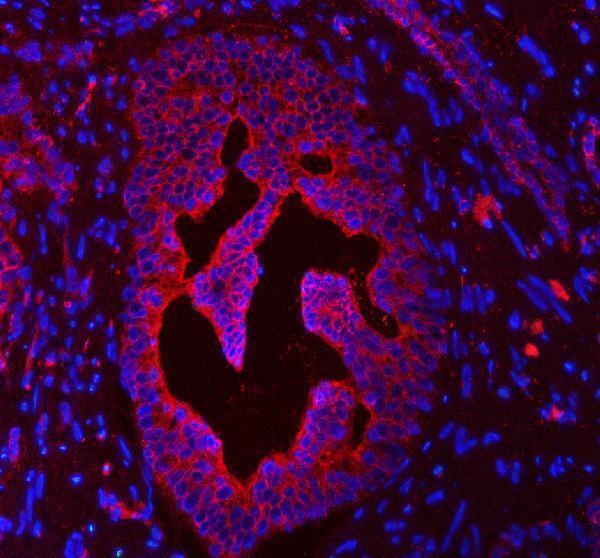
A07410-3 shows IHC in human paraffin sections of endometrioid, lung and prostate adenocarcinoma, plus IF in a paraffin section of human prostatic cancer (A07410-3 image captions). M07410 lists human and rat IHC and ICC/IF; M07410-1 lists human IHC and ICC/IF, with no IHC or IF images supplied for either (catalog applications/reactivity; catalog image lists).

Which to pick: Choose A07410-3 for tissue IHC: its human paraffin-section images document EDTA pH 8.0 retrieval and 2 μg/ml primary antibody; the fixative is unreported (A07410-3 IHC captions). For IF, A07410-3 has an illustrated human paraffin-section example at 5 μg/ml; for ICC, M07410 and M07410-1 list that application but have no supplied images (A07410-3 IF caption; catalog applications/image lists). For rat samples, M07410 is the listed option because its reactivity includes rat, although no rat IHC or IF image is supplied (M07410 catalog reactivity/image lists).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P19013 (K2C4_HUMAN, Keratin, type II cytoskeletal 4).
  2. Human Protein Atlas. KRT4 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. KRT4 subcellular location (ICC-IF): Localized to the intermediate filaments..
  4. Human Protein Atlas. KRT4 antibody validation summary (2 antibodies).
  5. Keratin 17 in premalignant and malignant squamous lesions of the cervix: proteomic discovery and immunohistochemical validation as a diagnostic and prognostic biomarker. Modern pathology : an official journal of the United States and Canadian Academy of Pathology, Inc 2014 — PMC4026928.
  6. Gene expression profiling to predict recurrence of advanced squamous cell carcinoma of the tongue: discovery and external validation. Oncotarget 2017 — PMC5617464.
  7. Exfoliative Cytology and Genetic Analysis for a Non-Invasive Approach to the Diagnosis of White Sponge Nevus: Case Series. Bioengineering (Basel, Switzerland) 2023 — PMC9952746.
  8. MUC21 is downregulated in oral squamous cell carcinoma and associated with poor prognosis. Frontiers in oncology 2026 — PMC13056625.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:16541075 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.