KSR2 / Kinase suppressor of Ras 2 · IHC design guide

Design Immunohistochemistry for KSR2

Plan chromogenic KSR2 IHC in paraffin sections with the IHC-validated antibody at 1:50–1:200 (datasheet). Use CNS cytoplasmic staining, especially in Purkinje cells, as a reference and score cell populations separately (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for KSR2 (IHC for KSR2): expected localisation Cytoplasmic CNS staining; cerebellar membrane signal (HPA tissue IHC), antibody A06876-1, validated IHC image, and IHC protocol steps
Printable KSR2 IHC protocol sheet — expected localisation Cytoplasmic CNS staining; cerebellar membrane signal (HPA tissue IHC), antibody A06876-1, controls and protocol steps. Open the full KSR2 IHC guide →

KSR2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic CNS staining; cerebellar membrane signal (HPA tissue IHC)
Staining pattern CNS cytoplasmic staining, prominent in Purkinje cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Cerebellum+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A06876-1)
Caveat Signal varies markedly by cell population (HPA tissue IHC)
Regulation Expression regulation is unreported (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended KSR2 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with four published KSR2 IHC workflows (PMC9036720; PMC12713192; PMC13100183; PMC9345969).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human brain tissue; fixative not specified (datasheet A06876-1)
FixationImage fixative and duration unreported (datasheet A06876-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-KSR2, 1:50-1:200 (datasheet A06876-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultKSR2-positive staining in molecular layer cells - cytoplasm/membrane of cerebellum (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in CNS. Highly expressed in Purkinje cells. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 heat retrieval at 95–98 °C for 20 min (page retrieval rule).
Section 2

What Is the Expected KSR2 Staining Pattern?

KSR2 is cytoplasmic and membrane-associated, with no transmembrane segment (UniProt Q6VAB6). In paraffin-section IHC, expect staining in CNS cells, especially Purkinje cells; cerebellar molecular-layer cells and cortical neuronal projections are also reported as High (HPA: tissue IHC). HPA rates the tissue pattern Enhanced, with external verification pending (HPA: tissue IHC).

What am I looking at on my slide?
Strong cytoplasmic staining in Purkinje cells, with staining in nearby molecular-layer cells.This fits the reported cerebellar pattern: Purkinje cells are highly expressed, and molecular-layer cells are High in cytoplasm/membrane (HPA: tissue IHC). Evaluate the cell type and compartment together; color intensity alone is insufficient to identify a positive cell.
Staining follows neuronal projections in cerebral cortex.High staining of cortical neuronal projections is reported (HPA: tissue IHC), consistent with a cytoplasmic or membrane-associated protein (UniProt Q6VAB6). Projection staining may differ in shape from a filled cell body; assess it against the expected anatomy.
Strong staining appears confined to nuclei.A nuclear-only pattern conflicts with the reported cytoplasm/membrane localization (UniProt Q6VAB6; HPA: tissue IHC). Treat it as suspect until an independent control supports it; review counterstain, antibody specificity and detection background (general IHC practice).
Strong staining dominates adipocytes or bronchial respiratory epithelium.Those cell types are Not detected in the supplied tissue profile (HPA: tissue IHC). Check whether the signal persists without primary antibody; persistence suggests detection background, while primary-dependent staining warrants an antibody-specificity check (general IHC practice).
No cellular signal appears in a well-preserved cerebellar positive-control section.That disagrees with the reported strong CNS pattern (HPA: tissue IHC). Check section quality, primary-antibody application and detection controls before calling the specimen negative; optimize retrieval on replicate sections as a general IHC workflow step, without assuming KSR2-specific fixation sensitivity.
💡Expected KSR2 appearanceA convincing positive shows strong cytoplasmic or membrane-associated signal in Purkinje cells and High cerebellar molecular-layer staining (HPA: tissue IHC; UniProt Q6VAB6); uniform nuclear color or equally strong staining in HPA Not detected cell types is suspect (HPA: tissue IHC).
How each factor affects the staining
Compartment and morphologyKSR2 is listed in cytoplasm and at membranes, without a transmembrane segment (UniProt Q6VAB6). Interpret a membrane-associated rim alongside cytoplasmic staining; do not require a continuous plasma-membrane outline to call a cell positive.
Choice of tissue and cell-level controlCerebellar molecular-layer cells and cortical neuronal projections are High; kidney glomerular cells are Medium, while adipocytes are Not detected (HPA: tissue IHC). Score the specified cells, since a tissue-wide positive or negative label would obscure these differences.
Antibody evidenceHPA035536 has Enhanced IHC validation, meaning its pattern was supported by independent antibodies or orthogonal data; HPA also states that external verification is pending (HPA: antibody validation; HPA: tissue IHC). Keep unexpected staining provisional.
Isoforms and epitope uncertaintyTwo KSR2 isoforms are listed (UniProt Q6VAB6). The supplied record gives no antibody epitope or isoform-specific IHC result, so these data cannot establish whether the catalog antibody detects both isoforms or explain a regional staining difference.
IF/ICC Q&A: Is there a confirmed cellular pattern?HPA provides no main ICC-IF location, image-bearing cell lines or ICC validation for the listed antibody (HPA: subcellular record; HPA: antibody validation). Cytoplasm/membrane is the UniProt location, but an IF/ICC pattern needs its own validation (UniProt Q6VAB6).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The cerebellar positive control has no stain.The result conflicts with High cerebellar staining (HPA: tissue IHC); a failed staining run remains possible (general IHC practice).Check primary application, detection reagents and section quality with run controls; compare retrieval conditions on replicate sections (general IHC practice). No KSR2-specific fixation effect is supplied.
The whole section has diffuse brown color.Widespread color without the reported cell pattern may reflect nonspecific binding or detection background (HPA: tissue IHC; general IHC practice).Compare a no-primary control, review blocking and washes, and optimize primary concentration before scoring cells (general IHC practice).
Nuclei are the strongest structures.Nuclear dominance does not fit the reported cytoplasm/membrane location (UniProt Q6VAB6; HPA: tissue IHC).Compare with counterstain and a no-primary control; verify the expected cytoplasmic pattern in cerebellum before interpreting nuclear color (general IHC practice; HPA: tissue IHC).
Adipocytes stain as strongly as Purkinje cells.Adipocytes are Not detected, whereas Purkinje cells are highly expressed (HPA: tissue IHC); the contrast raises a specificity or background concern.Score the named cells separately; use a no-primary control and review antibody concentration and detection background (general IHC practice).
Kidney shows less signal than cerebellum.That can fit the supplied profile: glomerular cells are Medium, while cerebellar molecular-layer cells are High (HPA: tissue IHC).Inspect glomerular cells rather than judging the entire kidney section; use the stronger cerebellar pattern as a run control (HPA: tissue IHC).
Two tissues give different staining patterns.HPA reports cell-specific levels, and the supplied evidence does not establish an isoform-specific staining pattern (HPA: tissue IHC; UniProt Q6VAB6).Compare the named cell types and compartments first. If a discrepancy persists, check antibody specificity with an independent control (general IHC practice).

Sample controls for KSR2 IHC & IF

🧪Run cerebellum first; molecular layer cells should show cytoplasmic or membrane staining (HPA: High in cerebellar molecular layer cells). Use adipose tissue as the negative tissue, where adipocytes are listed as not detected (HPA: adipocytes Not detected); cells outside the expected staining pattern on the positive slide should show only background, though their KSR2 status is unverified.
Positive control tissue: Cerebellum (Molecular layer cells - cytoplasm/membrane, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for KSR2; derive a cell-line control from the positive tissue's cell type (Molecular layer cells - cytoplasm/membrane) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary (secondary-only) control, an isotype control matched to the primary antibody’s host species and clonality, and a biological negative such as KSR2 knockout tissue or an immunizing-peptide block where available (standard IHC practice). Quench endogenous peroxidase for chromogenic detection; if assessing cerebellum by IF, check tissue autofluorescence (standard IHC/IF practice).
⚠️Feasibility: No target-specific fixation window or retrieval effect is reported in the supplied evidence; optimize antigen retrieval on paired paraffin sections (standard IHC practice). The selected A06876-1 caption shows paraffin-embedded human brain tissue but does not report the fixative (selected-SKU tissue-IHC caption). The evidence does not establish that frozen sections or IF are easier; brain autofluorescence can complicate IF interpretation (standard IF practice).

HPA tissue IHC evidence for KSR2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Molecular layer cells - cytoplasm/membrane High Protein (IHC) HPA →
Cerebral cortex Neuronal projections High Protein (IHC) HPA →
Skeletal muscle Myocytes High Protein (IHC) HPA →
Testis Sertoli cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced KSR2 IHC Tips

Troubleshoot KSR2 chromogenic IHC in paraffin sections by checking retrieval, compartment, cell type and controls before interpreting staining intensity.

How should I retrieve KSR2 antigen in paraffin sections with weak staining?
Use citrate buffer at pH 6.0 for heat-induced epitope retrieval at 95–98 °C for 20 minutes (page retrieval setting). Process a reference section alongside each retrieval trial so differences in staining can be attributed to the changed condition (standard IHC practice). If staining remains weak, test a longer retrieval time on serial sections while checking for tissue detachment and increased background (standard IHC practice). KSR2 is found in cytoplasm and at membranes, with no transmembrane segment (UniProt Q6VAB6); evaluate both compartments rather than treating membrane staining alone as the retrieval endpoint.
Could fixation explain weak or uneven KSR2 staining?
KSR2-specific sensitivity to fixation is unknown from the supplied evidence; the selected antibody caption reports paraffin-embedded human brain tissue but does not state its fixative (caption: A06876-1). Record the actual fixative and fixation duration for each specimen before comparing staining across cases (standard IHC practice). On serial sections, keep section thickness, retrieval and detection conditions constant while assessing whether poorly preserved regions stain differently (standard IHC practice). Judge preservation using morphology and a suitable positive reference, since variable processing can obscure an IHC result (standard IHC practice). Do not assign a KSR2-specific fixation effect from its reported localisation or phosphorylation sites (UniProt Q6VAB6).
Which staining compartments should count as plausible KSR2 signal?
Expect predominantly cytoplasmic staining, with possible membrane-associated signal, because both locations are reported for KSR2 (UniProt Q6VAB6). In cerebellum, compare staining in molecular layer cell cytoplasm or membranes with the reported high signal there, and assess Purkinje cells separately (HPA: cerebellum; HPA: cytoplasmic CNS expression, highly expressed in Purkinje cells). The cerebral cortex also has reported high signal in neuronal projections (HPA: cerebral cortex). A purely nuclear pattern without corresponding expected staining deserves a specificity check using controls and serial sections (UniProt Q6VAB6 localisation; standard IHC practice). Score compartments separately so a diffuse chromogen deposit does not become a membrane-localisation claim (standard IHC practice).
Can this antibody distinguish KSR2 isoforms or phosphorylation states in tissue?
KSR2 has 2 listed isoforms, but the supplied antibody caption gives no epitope sequence or isoform-selectivity data (UniProt Q6VAB6; caption: A06876-1). Treat staining as KSR2-associated signal without assigning it to either isoform until antibody documentation or independent validation resolves the epitope (standard IHC interpretation). The record lists phosphorylated residues, including threonines 272, 276 and 497, and serine 474 (UniProt Q6VAB6). Those modifications do not establish that this antibody detects a particular phosphorylation state (caption: A06876-1; UniProt Q6VAB6). For discordant staining, review the immunogen or mapped epitope and test an independent KSR2 reagent if available (standard IHC practice).
How can I assess KSR2 by multiplex IF alongside this IHC guide?
Treat IF as a separately optimised application; the selected antibody caption documents paraffin-section IHC in human brain, with fixation unreported (caption: A06876-1). Pair KSR2 with an independently validated marker for the cell type being scored, such as a neuronal marker when examining the reported CNS signal (HPA: CNS profile; standard IF practice). Choose fluorophores after inspecting unstained tissue, using spectrally separated channels that avoid its strongest autofluorescence (standard IF practice). Because KSR2 has cytoplasmic and membrane locations but no transmembrane segment, use controlled permeabilisation when testing access to an intracellular epitope; the antibody epitope side is unspecified here (UniProt Q6VAB6; caption: A06876-1).
What should I change when KSR2 chromogenic IHC has widespread background?
Run a no-primary control to identify detection-reagent signal, and compare it with the full stain on adjacent sections (standard IHC practice). For a peroxidase and DAB workflow, include an endogenous-peroxidase block and inspect pigment or deposits before calling brown signal positive (standard IHC practice). Titrate the primary antibody and detection reagent while holding retrieval at citrate pH 6.0, 95–98 °C for 20 minutes initially (page retrieval setting; standard IHC practice). Include a lower-expression reference alongside a positive section; HPA reports KSR2 as not detected in adipocytes from adipose tissue, although that observation alone does not validate a negative control for this antibody (HPA: adipose tissue; standard IHC practice).
How should I quantify KSR2 staining across brain sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the anatomic region, cell class and scoring compartment before reviewing groups; KSR2 has reported cytoplasmic CNS expression and high signal in Purkinje cells (HPA: CNS profile; standard IHC practice). Record the percentage of positive eligible cells and staining intensity on a 0–3 scale, then calculate an H-score from 0–300 if intensity grading is reproducible (standard IHC practice). For projections or diffuse regions, measure positive area or signal density per mm² of evaluable tissue instead (standard IHC practice). Normalise cell counts to eligible cells and area measurements to viable tissue area, excluding folds and damaged edges by a prespecified rule (standard IHC practice).
How can I distinguish genuine KSR2 staining from artefact?
A credible pattern follows the reported cytoplasmic or membrane localisation and occurs in expected cells, including cerebellar molecular layer cells and Purkinje cells (UniProt Q6VAB6; HPA: cerebellum; HPA: CNS profile). Check whether neuronal projections stain in cerebral cortex, where high signal is reported (HPA: cerebral cortex). Treat isolated nuclear staining, section-edge deposits, necrotic areas and signal shared with a no-primary control as reasons to investigate artefact (UniProt Q6VAB6 localisation; standard IHC practice). In peroxidase and DAB assays, inspect the endogenous-peroxidase control before assigning brown pigment to KSR2 (standard IHC practice). HPA labels its tissue IHC reliability Enhanced but pending external verification, so corroborate unexpected patterns independently (HPA: reliability description).
Boster reagents

Best KSR2 / Kinase suppressor of Ras 2 IHC Antibodies

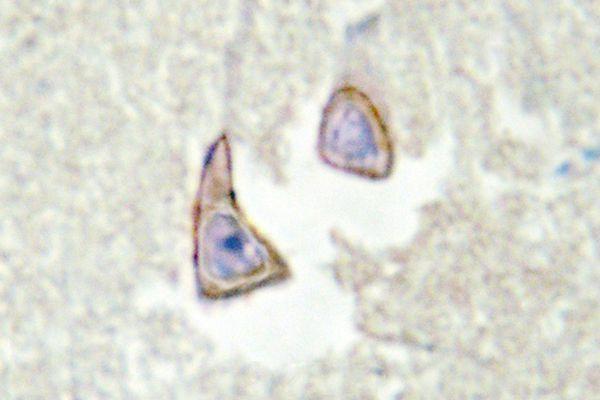
The catalog antibody has an IHC image from paraffin-embedded human brain tissue (catalog IHC image caption); IF is listed without an image, and human, mouse and rat reactivity is listed (catalog applications, IF image alts, reactivity).

Real IHC data Immunohistochemistry (IHC) analyzes of Ksr2 (I694) pAb in paraffin-embedded human brain tissue. .
Anti-Ksr2 (I694) Antibody
Cat # A06876-1

A06876-1 is listed for IHC and IF, with human, mouse and rat reactivity (catalog applications and reactivity). Its IHC image shows paraffin-embedded human brain tissue; no IF image is supplied (catalog IHC and IF image alts).

Which to pick: For tissue IHC, choose A06876-1: its image documents paraffin-embedded human brain tissue, and the listed IHC dilution is 1:50–1:200 (catalog IHC image caption; catalog IHC dilution). The fixative is unreported (catalog IHC image caption). For IF, A06876-1 is listed at 1:50–1:200, but ICC is not listed and no IF image is supplied; human, mouse and rat are listed as reactive species, without tissue images for mouse or rat (catalog applications, IF dilution, IF and IHC image alts, reactivity).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q6VAB6 (KSR2_HUMAN, Kinase suppressor of Ras 2).
  2. Human Protein Atlas. KSR2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. KSR2 subcellular location (ICC-IF): Highest expression in HUVEC/TERT2: 4.2 nTPM.
  4. Human Protein Atlas. KSR2 antibody validation summary (1 antibodies).
  5. KSR2-14-3-3ζ complex serves as a biomarker and potential therapeutic target in sorafenib-resistant hepatocellular carcinoma. Biomarker research 2022 — PMC9036720.
  6. Endothelial KSR2 regulated by genetic variation protects against atherosclerosis through AMPKα1 stabilization. Theranostics 2026 — PMC12713192.
  7. KSR2 functions as a metabolic checkpoint for anti-PD-1 resistance by reprogramming glucose metabolism. Cancer immunology, immunotherapy : CII 2026 — PMC13100183.
  8. Targeted inhibition of ubiquitin signaling reverses metabolic reprogramming and suppresses glioblastoma growth. Communications biology 2022 — PMC9345969.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:16541075 — UniProt-cited evidence.
  11. PubMed PMID:12975377 — UniProt-cited evidence.