LDLR / Low-density lipoprotein receptor · IHC design guide

Design Immunohistochemistry for LDLR

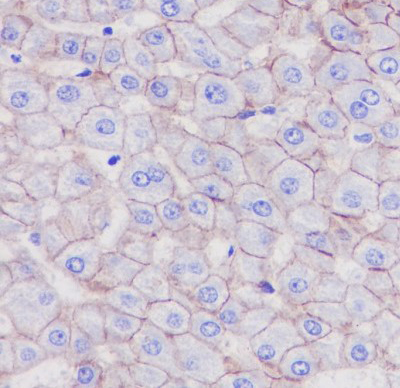
Plan chromogenic LDLR IHC in paraffin sections using 1 μg/mL as a documented starting concentration for A00076-2 (datasheet A00076-2). Expect cytoplasmic staining in liver hepatocytes (HPA tissue IHC); LDLR’s membrane and endosomal locations inform interpretation (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for LDLR (IHC for LDLR): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); membrane and endosomal LDLR (UniProt), antibody A00076-2, validated IHC image, and IHC protocol steps
Printable LDLR IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); membrane and endosomal LDLR (UniProt), antibody A00076-2, controls and protocol steps. Open the full LDLR IHC guide →

LDLR Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); membrane and endosomal LDLR (UniProt)
Staining pattern Cytoplasmic staining in several tissues; high in Leydig cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A00076-2)
Positive control ⓘ Testis+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent (standard IHC practice; not target-specific)
Caveat Antibody staining and RNA show low consistency (HPA tissue IHC)
Regulation LDL binding rapidly triggers endocytosis (UniProt)
Isoform / epitope 6 isoforms; map the epitope to the extracellular or cytoplasmic region (UniProt)
Section 1

Recommended LDLR IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet: A00076-2) with published LDLR IHC methods for ovarian carcinoma, high-grade glioma, rat liver, and small-cell lung cancer (PMC8664653; PMC9958636; PMC6413123; PMC5391547).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver cancer tissue; fixative not specified (datasheet A00076-2)
FixationImage fixative and duration unreported (datasheet A00076-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A00076-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A00076-2)
Primary antibodyRabbit anti-LDLR, 0.5-1μg/ml (datasheet A00076-2)
Primary incubationOvernight at 4 °C (datasheet A00076-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A00076-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultLDLR-positive staining in leydig cells of testis (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet: A00076-2); citrate retrieval is a published alternative (PMC9958636; PMC6413123).
Section 2

What Is the Expected LDLR Staining Pattern?

LDLR is a single-pass cell-surface receptor that also traffics through endosomes and other intracellular compartments (UniProt P01130 topology and subcellular location). In paraffin-section IHC, expect cytoplasmic staining in several tissues, strongest in testicular Leydig cells and moderate in selected glandular cells, kidney tubules, hepatocytes and lung macrophages (HPA tissue IHC). Treat intensity as a guide: HPA rates the tissue staining Approved but reports low consistency with RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Strong Leydig-cell staining, or moderate staining in hepatocytes, kidney tubules or listed glandular cells.This agrees with HPA's observed cell-specific IHC levels: Leydig cells are High; hepatocytes, tubular cells and adrenal, colon, duodenal or stomach glandular cells are Medium (HPA tissue IHC). Evaluate the named cells within the section, rather than treating every cell in a positive tissue as equally positive (HPA tissue IHC; standard IHC practice).
Cytoplasmic staining with some cell-boundary or punctate accentuation in the expected cells.HPA describes cytoplasmic tissue expression; UniProt places LDLR at the cell membrane, coated pits and intracellular trafficking compartments (HPA tissue IHC; UniProt P01130 subcellular location). The balance between these appearances need not be identical in every cell, because LDLR is rapidly endocytosed after ligand binding (UniProt P01130 subcellular location).
A predominantly nuclear pattern with little staining in the expected cellular compartments.Nuclei are outside the reported LDLR locations, so investigate this as possible nonspecific staining before scoring it as LDLR (UniProt P01130 subcellular location; standard IHC practice). Review the negative control and the location of staining in a known-positive section (standard IHC practice).
Strong signal in an unexpected cell type, such as adipocytes, while expected cells are weak.HPA reports adipocytes as Not detected; unexpected staining may reflect cross-reactivity or endogenous detection activity (HPA tissue IHC; standard IHC practice). That comparison is suggestive, not conclusive, because HPA reports low consistency between antibody staining and RNA expression (HPA tissue IHC).
Widespread, diffuse color obscures cell boundaries or appears across unlike tissue compartments.A diffuse pattern cannot be confidently assigned to the cells and compartments reported for LDLR (HPA tissue IHC; UniProt P01130 subcellular location). Check background controls, blocking, washes and detection chemistry before interpreting intensity (standard IHC practice).
💡Expected LDLR appearanceCall a section positive when the expected cells show interpretable cytoplasmic staining, with possible membrane or punctate accentuation and the strongest reference signal in Leydig cells; diffuse field-wide or predominantly nuclear color is suspect (HPA tissue IHC; UniProt P01130 subcellular location; standard IHC practice).
How each factor affects the staining
Topology and antibody epitopeLDLR has an extracellular region at residues 22–788, one transmembrane segment at 789–810, and a cytoplasmic tail at 811–860 (UniProt P01130 topology). Interpret an antibody's staining in light of its documented epitope if that information is available; no epitope is supplied here (standard IHC practice).
Trafficking and compartmentLigand-bound LDLR enters clathrin-coated pits, and UniProt also lists Golgi, early and late endosomes, and lysosomes (UniProt P01130 function and subcellular location). Intracellular signal can therefore fit the biology alongside surface signal (UniProt P01130 subcellular location).
Tissue reference and confidenceHPA records High staining in Leydig cells, Medium staining in several specified cell types, and Not detected in adipocytes and several other cells (HPA tissue IHC). Its Approved rating comes with low staining-to-RNA consistency, so use these as reference patterns rather than absolute diagnostic thresholds (HPA tissue IHC).
IF/ICC Q&A: where should signal appear?Vesicles are the approved main location in HPA ICC-IF images (HPA subcellular ICC-IF). This answers the localization question for IF/ICC; the paraffin-section IHC pattern is separately described as cytoplasmic (HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in a Leydig-cell reference section.The result conflicts with HPA's High Leydig-cell staining, but does not identify which workflow step failed (HPA tissue IHC; standard IHC practice).Confirm the expected cells are present, then review the antibody's documented IHC-P procedure, retrieval, detection reagents and control-section performance (standard IHC practice). Do not infer LDLR-specific fixation sensitivity from this result.
Only faint staining in a listed Medium tissue.HPA calls these cells Medium, and its tissue IHC has low consistency with RNA expression; a faint result alone is inconclusive (HPA tissue IHC).Compare the same run with a Leydig-cell reference and its negative control before changing scoring or workflow conditions (HPA tissue IHC; standard IHC practice).
Unexpected strong staining in adipocytes or another HPA Not detected cell type.The pattern disagrees with HPA's cell-level reference and may arise from cross-reactivity or endogenous detection activity (HPA tissue IHC; standard IHC practice).Inspect a no-primary control, assess endogenous detection background, and compare with the expected positive cells in the same run (standard IHC practice).
Diffuse color across the section, including tissue spaces.This does not match HPA's cell-associated cytoplasmic pattern and can obscure interpretable signal (HPA tissue IHC; standard IHC practice).Check the no-primary control, blocking, washes and detection development; score only staining that remains assignable to cells (standard IHC practice).
Predominantly nuclear color despite an otherwise visible section.A nuclear-dominant pattern is outside UniProt's listed LDLR locations and HPA's cytoplasmic tissue description (UniProt P01130 subcellular location; HPA tissue IHC).Compare the negative control and a positive reference; reassess specificity and counterstain or chromogen appearance before calling nuclei positive (standard IHC practice).
Membrane accentuation varies among cells that show cytoplasmic staining.LDLR occupies the cell surface and intracellular compartments and is rapidly endocytosed after ligand binding (UniProt P01130 subcellular location).Score the full cell-associated pattern in the HPA-listed cell type; do not require a continuous membrane rim when interpretable cytoplasmic staining is present (HPA tissue IHC; UniProt P01130 subcellular location).

Sample controls for LDLR IHC & IF

🧪Run testis first and confirm staining in Leydig cells (HPA: High in Leydig cells). Use adipose tissue adipocytes as the negative tissue (HPA: Not detected in adipocytes); cells used as internal negative comparators on the testis slide should show counterstain without specific chromogen deposition (standard IHC interpretation).
Positive control tissue: Testis (Leydig cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show LDLR in EFO-21, GAMG, U2OS, with annotated localisation: Vesicles (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and rabbit isotype controls matched to the catalog antibody’s clonality (hero caption: rabbit anti-LDLR), plus an LDLR knockout sample or validated peptide competition as a biological specificity control (standard IHC practice). For the testis slide, check endogenous peroxidase and biotin background when using the caption’s SABC/DAB detection method (hero caption: SABC/DAB; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence; the selected A00076-2 paraffin-section caption does not state a fixative (hero caption: fixative unreported). The caption uses heat retrieval in EDTA at pH 8.0, but does not establish that retrieval is required (hero caption: heat-mediated EDTA retrieval). The evidence does not establish that frozen sections or IF are easier; assess testis background from endogenous peroxidase or biotin if using SABC/DAB (hero caption: SABC/DAB; standard IHC practice).

HPA tissue IHC evidence for LDLR

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Testis Leydig cells High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Colon Glandular cells Medium Protein (IHC) HPA →
Duodenum Glandular cells Medium Protein (IHC) HPA →
Kidney Cells in tubules Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced LDLR IHC Tips

Troubleshoot LDLR staining in paraffin sections by checking retrieval, cell compartment, tissue context, and controls before comparing staining intensity.

What should I change if LDLR staining is weak after retrieval?
Start with heat-mediated retrieval in EDTA pH 8.0 for paraffin sections (datasheet A00076-2). The selected tissue IHC caption used this retrieval before overnight incubation at 4°C with 1 μg/mL catalog antibody, so keep those conditions together for an initial comparison (datasheet A00076-2). If staining remains weak, compare a second retrieval condition on adjacent sections while holding antibody concentration, detection, and development time constant (standard IHC practice). Include a liver section with hepatocytes as a reference, but expect only medium staining in the HPA profile (HPA: medium in liver hepatocytes). Record tissue preservation and background alongside signal because stronger retrieval can also expose nonspecific staining (standard IHC practice).
Could fixation explain weak or variable LDLR IHC?
The selected paraffin-section caption does not state a fixative, so LDLR-specific fixation sensitivity is unknown for this antibody (datasheet A00076-2). Record fixative, fixation duration, and processing history for every specimen before comparing staining across cases (standard IHC practice). If those variables differ, stain adjacent sections in the same run and compare preserved morphology and signal with a consistently processed reference section (standard IHC practice). Do not assign weak staining to LDLR epitope damage solely because its extracellular region spans residues 22–788; topology does not establish fixation sensitivity (UniProt P01130 topology). A no-primary control can help identify detection background, but cannot determine whether fixation concealed the epitope (standard IHC practice).
Should LDLR appear at the cell surface or in cytoplasmic puncta?
Assess both membrane-associated staining and intracellular puncta: LDLR is annotated at the cell membrane, coated pits, Golgi, endosomes, and lysosomes (UniProt P01130 subcellular). Its rapid ligand-associated endocytosis makes a purely continuous membrane outline an unnecessarily narrow expectation (UniProt P01130 function and subcellular). HPA reports cytoplasmic staining in several tissues and an approved vesicular location in cell imaging (HPA tissue IHC; HPA subcellular). In paraffin IHC, compare staining with cell boundaries and morphology on the counterstained section before calling diffuse chromogen cytoplasmic LDLR (standard IHC practice). Check whether the stained cells match the sampled tissue: hepatocytes in liver and macrophages in lung have medium HPA staining (HPA tissue IHC).
How could epitope location change my LDLR IHC result?
Ask for the catalog antibody's immunogen or mapped epitope before treating absent staining as absent LDLR (standard IHC practice). LDLR has 6 annotated isoforms, while the supplied record does not map this antibody to an isoform-specific sequence (UniProt P01130 isoforms; datasheet A00076-2). The receptor has an extracellular region at residues 22–788, a membrane segment at 789–810, and a cytoplasmic tail at 811–860 (UniProt P01130 topology). Five annotated glycosylation sites occur at residues 97, 156, 272, 515, and 657; their presence alone does not establish antibody masking in paraffin sections (UniProt P01130 glycosylation). Compare retrieval and a separately validated epitope where possible, without interpreting differences as proof of an isoform change (standard IHC practice).
How should I investigate an LDLR IHC pattern with IF?
Use IF as a follow-up localisation check, pairing LDLR with a marker that identifies the expected cell type in the specimen; choose the marker only after defining that population (standard IF practice). HPA identifies liver hepatocytes and lung macrophages as medium-staining IHC populations, while its cell imaging localises LDLR to vesicles (HPA tissue IHC; HPA subcellular). Select fluorophores in channels with low measured tissue autofluorescence, and acquire unstained and single-label controls before interpreting overlap (standard IF practice). If the antibody epitope is cytoplasmic, permeabilise appropriately; an extracellular epitope may be accessible without permeabilisation, but this antibody's epitope is unspecified (UniProt P01130 topology; datasheet A00076-2). Compare IF puncta with the chromogenic pattern in matched tissue regions, accounting for the different readouts (standard IF/IHC practice).
How can I reduce diffuse or granular background in LDLR sections?
First compare the stained section with a no-primary control and inspect edges, folds, damaged areas, and pigment under the same illumination (standard IHC practice). The selected caption used 10% goat serum blocking, a biotinylated secondary antibody, streptavidin–biotin detection, and DAB, providing specific steps to check during troubleshooting (datasheet A00076-2). For chromogenic peroxidase detection, include a peroxidase block and assess endogenous biotin-related signal with suitable controls for the chosen detection system (standard IHC practice). Reduce background by comparing antibody concentration or incubation time on adjacent sections while preserving the documented retrieval condition, EDTA pH 8.0 (datasheet A00076-2; standard IHC practice). Judge granular staining against cell morphology because LDLR can occupy intracellular vesicular compartments (UniProt P01130 subcellular; HPA subcellular).
How should I score LDLR staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and compartment before analysis, then use an H-score combining intensity and percentage of positive cells or report percentage positive separately (standard IHC practice). For spatial analyses, report positive-cell density per mm² of viable tissue and state whether membrane-associated and cytoplasmic staining were scored separately (standard IHC practice). Normalise counts to the relevant cell population or viable tissue area, and keep retrieval, antibody incubation, detection, and image settings consistent across cases (standard IHC practice). Record necrosis and section edges outside the analysis mask so they cannot inflate the score (standard IHC practice). Interpret modest staining against HPA's medium signal in liver hepatocytes and its low antibody–RNA consistency rating (HPA tissue IHC).
When is an LDLR-positive IHC pattern convincing?
A convincing pattern follows intact cell morphology and is reproducible across comparable sections, with little corresponding signal in a no-primary control (standard IHC practice). Membrane-associated or vesicular staining fits LDLR's annotated trafficking compartments, whereas uniform nuclear staining would need independent validation (UniProt P01130 subcellular; HPA subcellular). Check cell identity: HPA reports high staining in testis Leydig cells and medium staining in liver hepatocytes, but no detected staining in adipocytes in its sampled adipose tissue (HPA tissue IHC). Discount signal concentrated at cut edges, folds, or necrosis, and exclude endogenous enzyme staining through detection controls (standard IHC practice). Treat agreement with HPA as supportive rather than definitive because its tissue staining has low consistency with RNA expression (HPA tissue IHC reliability).
Boster reagents

Best LDLR / Low-density lipoprotein receptor IHC Antibodies

Anti-LDLR antibodies have IHC images from human liver, liver cancer, liver carcinoma and rectal cancer tissue; one also has a human liver IF image (catalog image captions).

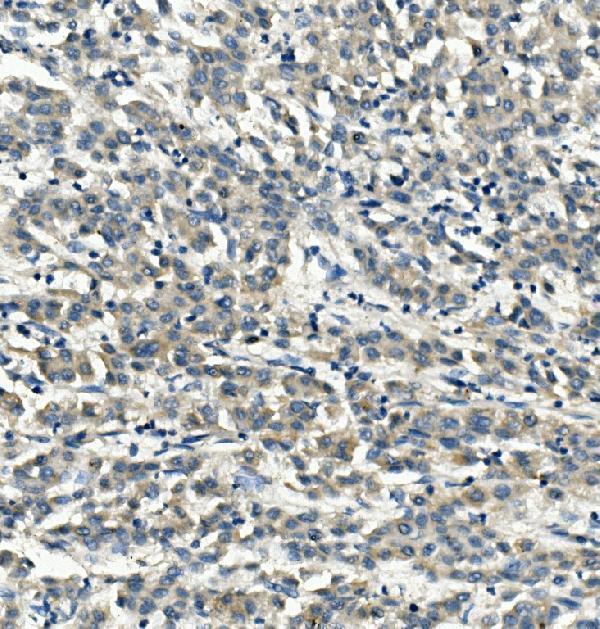
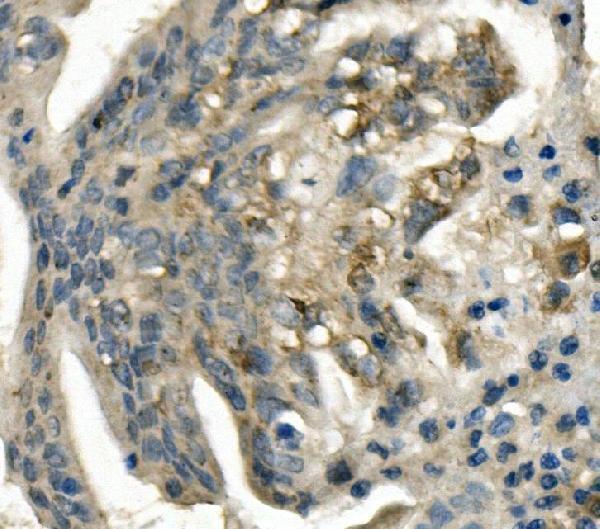
Real IHC data IHC analysis of LDLR using anti-LDLR antibody (A00076-2). LDLR was detected in paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-LDLR Antibody (A00076-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-LDL Receptor/LDLR Antibody ®
Cat # A00076-2
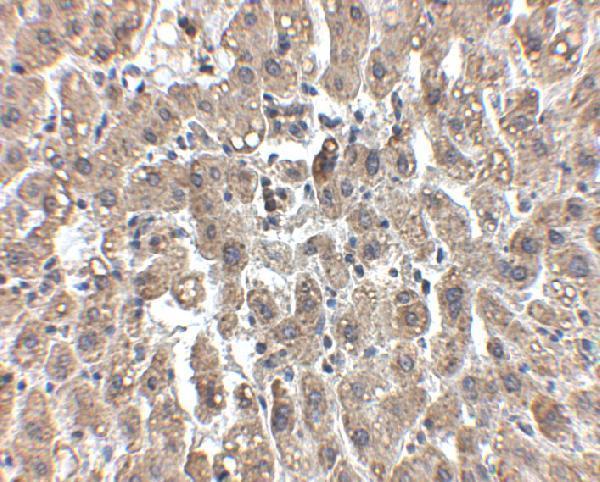
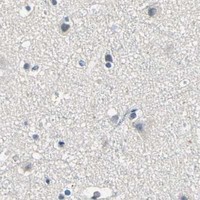
Real IHC data Immunohistochemistry of LDL-R in human liver tissue with LDL-R antibody at 2.5 μg/mL.
Anti-LDL-R Antibody
Cat # A00076
Real IHC data Immunohistochemical analysis of paraffin-embedded human liver carcinoma, using LDL Receptor Antibody .
Anti-LDL Receptor Rabbit Monoclonal Antibody
Cat # M00076

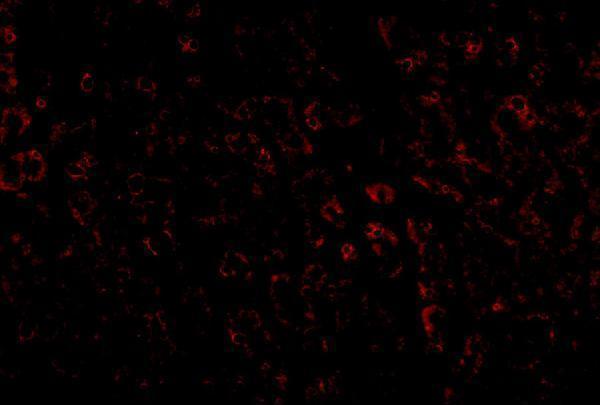
A00076 has human liver IHC and IF images (A00076 image captions); A00076-2 has paraffin-section IHC images from human liver and rectal cancer tissue (A00076-2 image captions). M00076 has a paraffin-section IHC image from human liver carcinoma (M00076 image caption).

Which to pick: For paraffin-section IHC, choose A00076-2 for its documented EDTA retrieval and chromogenic detection workflow (A00076-2 IHC image caption); its fixative is unreported (A00076-2 IHC image caption). For IF, choose A00076, which has a human liver IF image and a starting concentration of 20 μg/mL (A00076 IF image caption; datasheet: 20 μg/mL); ICC validation is unreported (A00076 applications). For work involving mouse or rat samples, A00076 lists reactivity with both, while A00076-2 lists rat and M00076 lists mouse; the supplied tissue images show human samples only (catalog reactivity; catalog image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P01130 (LDLR_HUMAN, Low-density lipoprotein receptor).
  2. Human Protein Atlas. LDLR tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. LDLR subcellular location (ICC-IF): Localized to vesicles..
  4. Human Protein Atlas. LDLR antibody validation summary (3 antibodies).
  5. Low Density Lipoprotein Receptor (LDLR) and 3-Hydroxy-3-Methylglutaryl Coenzyme a Reductase (HMGCR) Expression are Associated with Platinum-Resistance and Prognosis in Ovarian Carcinoma Patients. Cancer management and research 2021 — PMC8664653.
  6. Low-Density Lipoprotein Pathway Is a Ubiquitous Metabolic Vulnerability in High Grade Glioma Amenable for Nanotherapeutic Delivery. Pharmaceutics 2023 — PMC9958636.
  7. Can Carob-Fruit-Extract-Enriched Meat Improve the Lipoprotein Profile, VLDL-Oxidation, and LDL Receptor Levels Induced by an Atherogenic Diet in STZ-NAD-Diabetic Rats?. Nutrients 2019 — PMC6413123.
  8. Serum low-density lipoprotein and low-density lipoprotein expression level at diagnosis are favorable prognostic factors in patients with small-cell lung cancer (SCLC). BMC cancer 2017 — PMC5391547.
  9. PubMed PMID:6091915 — UniProt-cited evidence.
  10. PubMed PMID:2988123 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.