LHX6 / LIM/homeobox protein Lhx6 · IHC design guide

Design Immunohistochemistry for LHX6

Plan paraffin-section LHX6 IHC using the catalog antibody at 2–5 μg/ml (datasheet A07568-1). Compare tissue staining with the reported cytoplasmic profile, while accounting for its low consistency with RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for LHX6 (IHC for LHX6): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear location (UniProt), antibody A07568-1, validated IHC image, and IHC protocol steps
Printable LHX6 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear location (UniProt), antibody A07568-1, controls and protocol steps. Open the full LHX6 IHC guide →

LHX6 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); nuclear location (UniProt)
Staining pattern Cytoplasmic staining in most tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A07568-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Bone marrow+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining has low consistency with RNA data (HPA tissue IHC)
Regulation No staining-linked expression regulator annotated (UniProt)
Isoform / epitope 6 isoforms; epitope differences unspecified (UniProt)
Section 1

Recommended LHX6 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by published LHX6 IHC protocols for lung cancer specimens (PMC7605383; PMC5595086).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human thyroid cancer tissue; fixative not specified (datasheet A07568-1)
FixationImage fixative and duration unreported (datasheet A07568-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A07568-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A07568-1)
Primary antibodyRabbit anti-LHX6, 2-5 μg/ml (datasheet A07568-1)
Primary incubationOvernight at 4 °C (datasheet A07568-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A07568-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultLHX6-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval (datasheet: A07568-1); neither published lung IHC excerpt specifies retrieval (PMC7605383; PMC5595086).
Section 2

What Is the Expected LHX6 Staining Pattern?

LHX6 is a nuclear protein with no transmembrane segment (UniProt Q9UPM6: subcellular location and topology). In paraffin-section IHC, assess staining in HPA-reported positive cells, including colon glandular cells and esophageal squamous epithelial cells (HPA tissue IHC: High). Interpret compartment and intensity cautiously: HPA reports cytoplasmic staining in most tissues, and its IHC reliability is Approved with low consistency between staining and RNA data (HPA tissue IHC).

What am I looking at on my slide?
Defined nuclear staining in cells of a HPA-positive tissue.This fits the UniProt nuclear assignment (UniProt Q9UPM6: Nucleus). Check cell identity against HPA tissue IHC; a nuclear pattern alone does not establish antibody specificity, particularly given HPA's low staining–RNA consistency (HPA tissue IHC: Approved).
Predominantly cytoplasmic staining, with little or no nuclear signal.HPA reports cytoplasmic expression in most tissue IHC samples (HPA tissue IHC: profile), while UniProt assigns LHX6 to the nucleus (UniProt Q9UPM6: Nucleus). Treat this as a compartment discrepancy requiring corroboration, not automatic proof of either specific staining or artefact.
Strong staining in cells reported as negative, such as bone marrow hematopoietic cells.That conflicts with HPA's Not detected result for those cells (HPA tissue IHC: bone marrow). Consider cross-reactivity or endogenous chromogenic detection activity as possible explanations (general IHC practice); compare with a reagent control before assigning the signal to LHX6.
Diffuse stain covers cells and the surrounding section without clear boundaries.Poorly localized signal limits compartment and cell-type scoring (general IHC practice). Check a no-primary control for detection background, then review blocking and wash conditions (general IHC practice); diffuse color alone cannot confirm LHX6.
No stain in glandular cells of a nominated positive control, such as colon.HPA reports High staining in colon glandular cells (HPA tissue IHC: colon). Check the control section and detection run before interpreting a study sample as negative (general IHC practice); HPA's low staining–RNA consistency limits certainty that every section will reproduce its pattern (HPA tissue IHC).
💡Expected LHX6 appearanceA persuasive positive result is defined staining in HPA-reported positive cells, such as colon glandular cells (HPA tissue IHC: High), with nuclear localization consistent with UniProt (UniProt Q9UPM6: Nucleus); diffuse stain or color in HPA-reported negative cells warrants control-based review (HPA tissue IHC; general IHC practice).
How each factor affects the staining
Compartment evidenceUniProt assigns LHX6 to the nucleus (UniProt Q9UPM6: Nucleus), whereas HPA tissue IHC describes cytoplasmic expression in most tissues (HPA tissue IHC: profile). Score nuclear and cytoplasmic staining separately so this disagreement remains visible.
Tissue and cell selectionHPA reports High staining in colon glandular cells and esophageal squamous epithelial cells, but Not detected in bone marrow hematopoietic cells and ovarian stroma cells (HPA tissue IHC). Choose controls by the reported cell type, not tissue name alone.
Antibody validationHPA lists IHC as Approved for HPA047854 and gives its tissue IHC an Approved reliability rating with low staining–RNA consistency, pending external verification (HPA antibodies; HPA tissue IHC). Its status supports review of the observed pattern, not an Enhanced IHC claim.
IF/ICC cross-checkOn the separate IF/ICC guide, what pattern should be expected? HPA reports mainly nucleoplasmic localization with additional cytosol, both approved (HPA subcellular ICC-IF). This supports compartment comparison, but does not turn an ICC-IF observation into paraffin-section IHC validation.
Isoforms and processingUniProt lists six LHX6 isoforms, one chain spanning residues 1–363, no signal peptide, and no propeptide (UniProt Q9UPM6). Epitope coverage across isoforms is unspecified in the supplied evidence; do not infer isoform-specific staining or shedding from this record.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A high-staining reference tissue shows no chromogenic signal.The run may have a section, primary-antibody, or detection failure (general IHC practice); HPA reports High staining in several named cell types, including colon glandular cells (HPA tissue IHC).Confirm that the expected cells are present, inspect the run's positive control, and check primary-antibody and detection steps (general IHC practice). Do not infer LHX6 absence from a failed control.
Cytoplasmic color dominates, with no convincing nuclear staining.HPA tissue IHC describes broad cytoplasmic staining, while UniProt assigns nuclear localization (HPA tissue IHC: profile; UniProt Q9UPM6: Nucleus). The supplied sources do not resolve that discrepancy.Record both compartments separately and compare an independent specificity control where available (general IHC practice). Do not score cytoplasmic color alone as proof of the expected nuclear pattern.
Bone marrow hematopoietic cells stain strongly.HPA reports LHX6 as Not detected in those cells (HPA tissue IHC: bone marrow); cross-reactivity or endogenous detection activity is possible (general IHC practice).Compare with a no-primary control and assess whether color follows the expected cell boundaries (general IHC practice). Repeat with independent antibody evidence if assigning this unexpected signal to LHX6.
Color is widespread across cells and surrounding tissue.Diffuse chromogenic background can arise from detection or wash conditions (general IHC practice). It cannot be interpreted as a compartment-specific LHX6 pattern (UniProt Q9UPM6: Nucleus).Review the no-primary control, blocking, washes, and development time (general IHC practice); rescore only where individual cells and compartments can be distinguished.
A negative result is based on one tissue or a few cells.HPA levels vary by named cell population, from High in colon glandular cells to Not detected in ovarian stroma cells (HPA tissue IHC). Sampling the wrong population can mislead interpretation.Identify the evaluated cells and include an HPA-reported positive cell population in the same run (HPA tissue IHC; general IHC practice). Report a negative result for the sampled cells only.
An IF/ICC image and paraffin IHC section show different compartments.HPA ICC-IF reports mainly nucleoplasm plus cytosol, while its tissue IHC profile reports cytoplasmic expression in most tissues (HPA subcellular ICC-IF; HPA tissue IHC).Keep assay-specific observations distinct and review each assay's controls (general IHC practice). Use the separate IF/ICC guide for its interpretation; do not import an IF/ICC staining procedure into this IHC section.

Sample controls for LHX6 IHC & IF

🧪Run adrenal gland first: glandular cells should stain (HPA: High in adrenal gland glandular cells). Use bone marrow hematopoietic cells as the tissue negative (HPA: Not detected); on the adrenal slide, assess non-glandular cells for absence of specific nuclear staining against the negative controls (UniProt Q9UPM6: Nucleus).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Bone marrow (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show LHX6 in A-431, CACO-2, U2OS, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration-matched rabbit IgG isotype controls (selected-SKU caption: rabbit primary antibody), plus LHX6 knockout tissue as a biological negative where available. For adrenal sections, quench endogenous peroxidase and inspect background before interpreting DAB staining (selected-SKU caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported; the selected-SKU paraffin-section caption does not state the fixative. The caption uses heat retrieval in EDTA, pH 8.0, but does not establish whether retrieval is required (selected-SKU caption). ICC-IF images exist for A-431, CACO-2 and U2OS (HPA: subcellular images); whether IF or frozen sections are easier than paraffin IHC is unreported, and adrenal background should be checked with the peroxidase control (standard IHC practice).

HPA tissue IHC evidence for LHX6

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Endometrium Glandular cells Medium Protein (IHC) HPA →
Esophagus Squamous epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Section 3

Advanced LHX6 IHC Tips

Troubleshoot LHX6 chromogenic IHC in paraffin sections using the catalog antibody’s tissue image, the annotated cellular location, and independent staining controls.

Which retrieval conditions should I start with for LHX6 staining in paraffin sections?
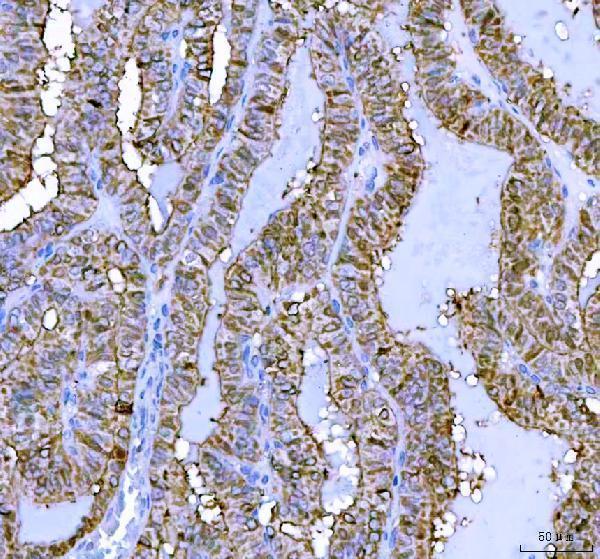
Start with heat-mediated antigen retrieval in EDTA buffer at pH 8.0 (datasheet A07568-1). The catalog antibody stained a paraffin section of human thyroid cancer after this retrieval, followed by 2 μg/ml primary antibody overnight at 4°C (caption A07568-1). Keep section thickness, heating, and cooling consistent across comparison slides so retrieval variation does not resemble biological variation (standard IHC practice). If staining remains weak, adjust heating duration on matched sections while checking morphology and background (standard IHC practice). Compare each change with the documented EDTA condition and a no-primary control before accepting additional signal (standard IHC practice).
How should I troubleshoot weak LHX6 staining when fixation history varies?
The catalog image identifies a paraffin section but does not report its fixative, so target-specific fixation sensitivity is unknown (caption A07568-1). Record fixative, fixation duration, and processing history for every case before comparing staining intensity across batches (standard IHC practice). On comparable sections, hold EDTA retrieval at pH 8.0 and primary antibody at 2 μg/ml constant while assessing preservation and signal (datasheet A07568-1; standard IHC practice). Excessive tissue damage or uneven morphology can confound interpretation, so inspect an adjacent routine-stained section (standard IHC practice). Do not assign weak staining to a particular fixative effect without matched, controlled specimens (standard IHC practice).
Should LHX6 staining be nuclear, cytoplasmic, or both?
Evaluate nuclear staining first because LHX6 is annotated as nuclear and the approved subcellular location is nucleoplasm (UniProt Q9UPM6; HPA subcellular). Record cytoplasmic staining separately: the subcellular dataset also reports cytosol, while tissue IHC describes cytoplasmic expression in most tissues (HPA subcellular; HPA tissue IHC). Use a light counterstain and examine intact cells at high magnification to distinguish chromogen within nuclei from adjacent cytoplasm (standard IHC practice). The protein has no transmembrane segment or signal peptide, so a crisp membrane-only pattern needs independent validation (UniProt Q9UPM6 topology and processing). Compare compartments against no-primary controls and tissue morphology before calling either pattern specific (standard IHC practice).
Could LHX6 isoforms or epitope accessibility explain variable staining?
LHX6 has 6 annotated isoforms, but the supplied antibody evidence does not identify its recognized epitope or isoform coverage (UniProt Q9UPM6; caption A07568-1). The annotated protein contains LIM zinc-binding domains at residues 70–122 and 131–184, which does not establish where this antibody binds (UniProt Q9UPM6). Compare staining under the documented EDTA pH 8.0 retrieval condition before attributing a difference to splice variants (datasheet A07568-1; standard IHC practice). If isoform specificity matters, obtain the antibody’s epitope information and test appropriate independently characterized material (standard antibody validation practice). Report unresolved compartment or intensity differences as staining observations, not isoform assignments (standard IHC practice).
How can I adapt LHX6 detection for multiplex immunofluorescence?
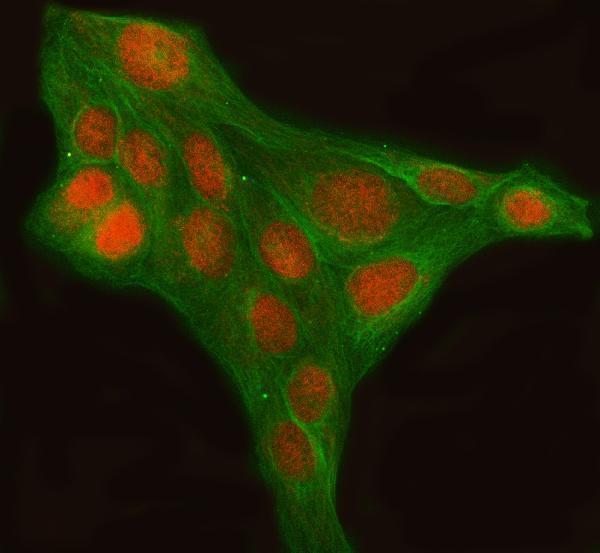
Treat IF with this catalog antibody as a separate validation exercise; its supplied tissue image documents chromogenic IHC in a paraffin section (caption A07568-1). Pair LHX6 with a marker of GABAergic interneurons where that cell population is under study, reflecting its annotated developmental role (UniProt Q9UPM6 function). Choose a spectrally separated, preferably far-red fluorophore after measuring tissue autofluorescence and single-label bleed-through (standard IF practice). Because LHX6 is nuclear with an additional cytosolic location and lacks a transmembrane segment, optimize permeabilisation for intracellular access after fixation (UniProt Q9UPM6; HPA subcellular; standard IF practice). Include single-label and no-primary controls, then score nuclear and cytosolic fluorescence separately (standard IF practice).
What controls help distinguish LHX6 signal from chromogenic background?
Begin with the documented 10% goat-serum block and 2 μg/ml primary antibody overnight at 4°C (caption A07568-1). Include a no-primary section, block endogenous peroxidase before HRP detection, and develop DAB for the same duration across matched slides (standard IHC practice). If diffuse staining persists, titrate the primary and review wash stringency while keeping EDTA retrieval at pH 8.0 fixed (datasheet A07568-1; standard IHC practice). Inspect tissue edges, folds, necrotic regions, and intrinsic pigment before treating brown deposits as cellular staining (standard IHC practice). Interpret any remaining cytoplasmic signal cautiously because tissue and subcellular datasets report that compartment (HPA tissue IHC; HPA subcellular).
How should I score LHX6 across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, since LHX6 is annotated in the nucleus and additionally in the cytosol (UniProt Q9UPM6; HPA subcellular). For chromogenic sections, report an H-score or the percentage of positive cells within morphologically defined regions, with nuclear and cytoplasmic scores separated (standard IHC practice). If counting positive cells per mm², normalize to measured viable tissue area and document the number of evaluable cells (standard IHC practice). Use identical retrieval, staining, imaging, and threshold settings across comparison groups (standard IHC practice). Include no-primary controls and assess section quality before comparing scores, especially because tissue staining has limited RNA concordance (HPA tissue IHC; standard IHC practice).
When should an apparent LHX6-positive cell be considered an artefact?
Give greatest weight to staining in intact nuclei, consistent with the annotated nuclear and approved nucleoplasmic locations (UniProt Q9UPM6; HPA subcellular). Cytoplasmic staining can be recorded, but its biological meaning needs controls because tissue IHC reports broad cytoplasmic expression with low staining–RNA consistency (HPA tissue IHC). Check whether signal follows viable cells rather than tissue edges, folds, necrosis, pigment, or deposits also visible without primary antibody (standard IHC practice). Exclude residual endogenous peroxidase activity with an appropriate control before interpreting DAB-positive structures (standard IHC practice). Compare cell identity and compartment across adjacent sections; the catalog’s thyroid cancer image alone cannot establish specificity in every tissue (caption A07568-1; standard IHC practice).
Boster reagents

Best LHX6 / LIM/homeobox protein Lhx6 IHC Antibodies

A07568-1 has IHC data from a human thyroid cancer paraffin section and IF/ICC data from U2OS cells (A07568-1 image captions); its listed reactivity is human (catalog: A07568-1).

Real IHC data IHC analysis of LHX6 using anti-LHX6 antibody (A07568-1). LHX6 was detected in a paraffin-embedded section of human thyroid cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-LHX6 Antibody (A07568-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-LHX6 Antibody ®
Cat # A07568-1

A07568-1 will render with its IHC figure from a human thyroid cancer paraffin section (A07568-1 IHC caption). The same SKU lists IF/ICC and has an IF image from U2OS cells (catalog: A07568-1 applications; A07568-1 IF caption).

Which to pick: Choose A07568-1 for human tissue IHC in paraffin sections: its own caption documents EDTA retrieval at pH 8.0 and primary antibody at 2 μg/ml (A07568-1 IHC caption); the fixative is unreported (A07568-1 IHC caption). For IF/ICC, A07568-1 is also listed for both applications and shown in U2OS cells (catalog: A07568-1 applications; A07568-1 IF caption). No cross-species choice is supported by this catalog payload, which lists human reactivity only; clonality is unreported (catalog: A07568-1 reactivity and clone).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9UPM6 (LHX6_HUMAN, LIM/homeobox protein Lhx6).
  2. Human Protein Atlas. LHX6 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. LHX6 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol..
  4. Human Protein Atlas. LHX6 antibody validation summary (2 antibodies).
  5. Lhx6-positive GABA-releasing neurons of the zona incerta promote sleep. Nature 2017 — PMC5958617.
  6. LHX6 Affects Erlotinib Resistance and Migration of EGFR-Mutant Non-Small-Cell Lung Cancer HCC827 Cells Through Suppressing Wnt/β-Catenin Signaling. OncoTargets and therapy 2020 — PMC7605383.
  7. UGT8/GalCer-dependent resistance of breast cancer cells to drug-induced apoptosis is potentially regulated by the LIM/homeobox protein LHX6. Scientific reports 2026 — PMC13068971.
  8. LHX6, An Independent Prognostic Factor, Inhibits Lung Adenocarcinoma Progression through Transcriptional Silencing of β-catenin. Journal of Cancer 2017 — PMC5595086.
  9. PubMed PMID:10393337 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15164053 — UniProt-cited evidence.