This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section LUC7L3 staining around its widespread nuclear tissue pattern (HPA tissue IHC). This guide covers fixation consistency, nuclear scoring, and epitope coverage across its 2 isoforms (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear staining (HPA tissue IHC); speckle localization (UniProt) | |
| Staining pattern | Widespread nuclear staining across tissue cell types (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A08633-3) | |
| Positive control | Adipose tissue+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Cisplatin can alter subnuclear localization (UniProt) | |
| Regulation | Broad expression; regulation unreported (UniProt) | |
| Isoform / epitope | 2 isoforms; confirm epitope coverage for both (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet A08633-3) is accompanied by one published LUC7L3 cell-block protocol (PMC12530123).
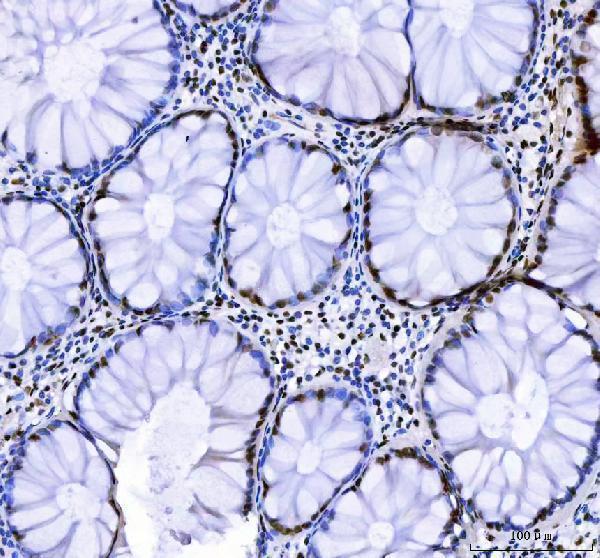
| Sample | Paraffin-embedded human highly differentiated adenocarcinoma of the colon tissue; fixative not specified (datasheet A08633-3) |
| Fixation | Image fixative and duration unreported (datasheet A08633-3); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A08633-3); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A08633-3) |
| Primary antibody | Rabbit anti-LUC7L3, 1-2 μg/ml (datasheet A08633-3) |
| Primary incubation | Overnight at 4 °C (datasheet A08633-3) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A08633-3) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | LUC7L3-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control. |
LUC7L3 should appear in nuclei across many tissue cell types (HPA: ubiquitous nuclear expression; Enhanced tissue IHC reliability). High staining is reported in adipocytes, glandular cells, hematopoietic cells, respiratory epithelial cells and selected brain cells (HPA: tissue IHC). Nuclear speckles are its more precise location (UniProt O95232: nucleus speckle); it has no transmembrane segment (UniProt O95232: topology).
| Nuclear chromogen appears in several cell populations, including the cell types reported as High in the chosen tissue (HPA: tissue IHC). | This fits the broad nuclear pattern (HPA: ubiquitous nuclear expression). Compare intensity within identifiable cells rather than requiring every nucleus to stain equally (general IHC interpretation); HPA's High calls describe observed populations, not a mandatory intensity threshold for every section. |
| Strong cytoplasmic or membrane staining dominates while nuclei are weak or clear. | That compartment conflicts with the nuclear tissue profile (HPA: ubiquitous nuclear expression) and the annotated nuclear speckle location (UniProt O95232: subcellular location). Review morphology and controls before calling it LUC7L3; a broad extranuclear deposit can reflect nonspecific staining or detection artefact (general IHC practice). |
| Signal is restricted to cells outside the population expected from the selected HPA tissue image. | Check cell identification first: LUC7L3 is widely expressed (UniProt O95232: tissue specificity), so an additional positive cell type alone does not prove cross-reactivity. If staining follows pigment, blood, or reagent-associated activity rather than nuclei, evaluate cross-reactivity and endogenous detection activity (general IHC practice). |
| A uniform haze obscures nuclei and tissue boundaries. | This is difficult to score as the reported nuclear pattern (HPA: tissue IHC profile). Review a reagent-only control, blocking, washes and chromogen development to locate nonspecific binding or detection background (general IHC practice); do not infer a target-specific fixation effect from this appearance. |
| No nuclei stain in an HPA-reported High population, such as cerebellar granular-layer cells (HPA: High). | Treat the result as technically unresolved before concluding that LUC7L3 is absent. Check section integrity, antibody and detection performance, and a matched positive control (general IHC practice). An HPA High observation supports a useful comparator, but does not guarantee staining in every specimen or run (HPA: tissue IHC). |
| Tissue and cell context | Expression is widespread (UniProt O95232: tissue specificity), and HPA reports High nuclear staining in several named cell populations (HPA: tissue IHC); use the chosen tissue's observed pattern as a comparator, not an exclusivity rule. |
| Subnuclear resolution | Nuclear speckles are supported by ICC-IF (HPA: enhanced nuclear speckles) and UniProt (O95232: nucleus speckle). In chromogenic sections, assess a nuclear result; apparent speckling depends on optical and tissue resolution (general IHC practice). |
| Antibody evidence | The listed HPA antibodies have Enhanced IHC status (HPA: HPA018475, HPA018484, HPA020017). This supports the reported pattern; it does not validate an unlisted antibody, its dilution, or a new tissue preparation (HPA: antibody validation summary). |
| Treatment context | UniProt reports that cisplatin affects subnuclear localization (UniProt O95232: subcellular-location note). Document treatment when comparing nuclear detail; the record supplies no direction, magnitude, or IHC-specific prediction for the change. |
| Molecular forms and target access | Two isoforms are listed (UniProt O95232: isoforms), with no signal peptide, propeptide, or transmembrane segment annotated (UniProt O95232: processing and topology). The payload gives no epitope map, so isoform detection and retrieval needs remain antibody dependent. |
| Target-specific fixation evidence | No fixation sensitivity is reported in the supplied UniProt or HPA records. Retrieval and section processing may be optimized as general IHC practice, but these records do not support a LUC7L3-specific fixation or epitope-masking claim. |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive comparator lacks nuclear staining. | The staining run or section may have failed; absence cannot be assigned to LUC7L3 from one slide (general IHC practice). | Check tissue integrity and positive-control nuclei, then verify antibody application and detection steps against the established IHC workflow (general IHC practice); compare with the selected HPA High cell population (HPA: tissue IHC). |
| Cytoplasmic colour overwhelms nuclear colour. | The result conflicts with the expected compartment (HPA: ubiquitous nuclear expression; UniProt O95232: nucleus speckle); nonspecific binding or chromogen background is possible (general IHC practice). | Compare with a reagent-only control and inspect whether colour tracks tissue edges or deposits; reassess blocking, washes and development (general IHC practice). |
| Unexpected cells stain while the HPA-listed cells remain clear. | Cell identity, variable biology, cross-reactivity, or endogenous detection activity may explain the mismatch (general IHC interpretation); HPA High calls are observations, not exclusive expression rules (HPA: tissue IHC). | Verify cell identity on the counterstained section, compare another HPA-listed positive population, and use appropriate detection controls (general IHC practice). |
| All compartments show faint colour. | Diffuse background prevents a reliable nuclear call (HPA: nuclear tissue profile); excess detection signal or incomplete washing may contribute (general IHC practice). | Review reagent-only control, wash performance and development endpoint; score only cell-associated nuclear colour above local background (general IHC practice). |
| Nuclear detail differs between treated and untreated samples. | Cisplatin can affect subnuclear localization (UniProt O95232: subcellular-location note), while section resolution can alter its appearance (general IHC practice). | Record treatment and compare matched sections using the same scoring approach; avoid assigning a specific redistribution without supporting images or controls (general IHC interpretation). |
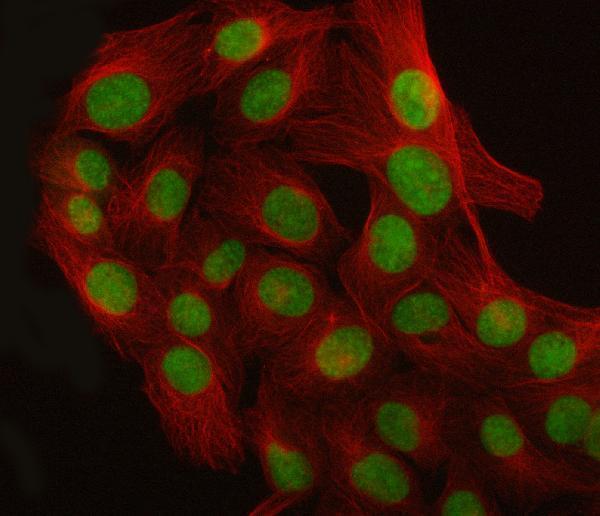
| Q: What should an IF/ICC image show? | The subcellular reference is mainly nuclear speckles (HPA: ICC-IF, enhanced nuclear speckles; UniProt O95232: nucleus speckle). | A: Look for nuclear speckle enrichment and compare with an appropriate nuclear counterstain (HPA: ICC-IF; general IF interpretation); use the separate IF/ICC guide for method details. |



Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Breast | Adipocytes | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: LUC7L3 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Use nuclear staining as the main readout for LUC7L3 in paraffin section IHC, with the catalog antibody’s documented conditions as the starting point.
A08633-3 has paraffin-section IHC images from human tissues and an IF/ICC image from U2OS cells (catalog image captions). Its listed reactivity covers human, mouse, and rat (catalog: reactivity).
A08633-3 is listed for IHC and has images from human paraffin sections of colon adenocarcinoma, colonic large B-cell lymphoma, liver cancer, and lung cancer (catalog: applications; IHC image captions). A08633-3 is also listed for IF/ICC, with an IF image from U2OS cells (catalog: applications; IF image caption).
Which to pick: For tissue IHC, choose A08633-3: its images document human paraffin sections with EDTA pH 8.0 retrieval and 2 μg/ml primary antibody; the fixative is unreported (catalog: IHC image captions). For IF/ICC, the same SKU has an image at 5 μg/ml in U2OS cells (catalog: IF image caption). For mouse or rat samples, A08633-3 lists reactivity with both species, although the supplied IHC and IF images show human samples (catalog: reactivity; image captions).