MAP3K8 / Mitogen-activated protein kinase kinase kinase 8 · IHC design guide

Design Immunohistochemistry for MAP3K8

Plan chromogenic MAP3K8 IHC in paraffin sections using bone marrow hematopoietic cells as a high-staining reference (HPA tissue IHC). Start the catalog antibody PB10007 at 0.5–1 μg/mL (datasheet PB10007), and assess cytoplasmic staining with attention to immune cell content (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
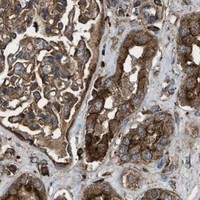
Immunohistochemistry protocol sheet for MAP3K8 (IHC for MAP3K8): expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody PB10007, validated IHC image, and IHC protocol steps
Printable MAP3K8 IHC protocol sheet — expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody PB10007, controls and protocol steps. Open the full MAP3K8 IHC guide →

MAP3K8 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC)
Staining pattern Cytoplasmic signal in most tissues, abundant in immune cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB10007)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Vagina
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections (standard IHC practice; not target-specific)
Caveat Immune-rich areas may dominate the signal (HPA tissue IHC)
Regulation LPS-linked degradation may lower signal (UniProt)
Isoform / epitope Two isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended MAP3K8 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: PB10007) is accompanied by two published MAP3K8 IHC protocols (PMC8733582; PMC9673241).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat brain tissue; fixative not specified (datasheet PB10007)
FixationImage fixative and duration unreported (datasheet PB10007); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB10007); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB10007)
Primary antibodyRabbit anti-MAP3K8, 0.5-1μg/ml (datasheet PB10007)
Primary incubationOvernight at 4 °C (datasheet PB10007)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB10007)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMAP3K8-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues, highly abundant in immune cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet: PB10007); sodium citrate and tris pH 8.5 are published alternatives (PMC8733582; PMC9673241).
Section 2

What Is the Expected MAP3K8 Staining Pattern?

MAP3K8 should appear mainly in the cytoplasm of stained cells: UniProt places it in the cytoplasm and reports no transmembrane segment (UniProt P41279); HPA reports cytoplasmic staining across most tissues, with particularly abundant staining in immune cells (HPA tissue IHC). The tissue IHC pattern is rated Supported, with medium consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining in bone marrow hematopoietic cells, potentially strong across many cells (HPA: High in bone marrow hematopoietic cells).This fits an expected positive pattern. Compare stained cells with their neighbors and the negative control before scoring intensity; cell composition affects the field-wide impression (HPA tissue IHC; general IHC practice).
Predominantly nuclear, sharply membranous, or extracellular staining in otherwise positive cells.These compartments do not match the reported cytoplasm/cytosol localization (UniProt P41279; HPA subcellular). Treat a dominant discordant pattern as possible nonspecific staining; review morphology and controls before assigning MAP3K8 positivity (general IHC practice).
Strong staining of vaginal squamous epithelium, especially if the negative control also develops color.HPA reports MAP3K8 as not detected in those cells (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity; the slide alone cannot distinguish them. Compare control sections and reassess the antibody and detection steps (general IHC practice).
Haze or precipitate spread across cells and surrounding tissue, with little cell-specific contrast.A diffuse signal is difficult to score as cytoplasmic MAP3K8 (UniProt P41279; HPA tissue IHC). Check the negative control, blocking, washes, chromogen development, and section condition as general chromogenic IHC checks (general IHC practice).
No staining in a bone marrow section that contains identifiable hematopoietic cells.That conflicts with the reported High staining in these cells (HPA tissue IHC), but does not by itself prove absence of MAP3K8. Verify section quality and a working positive control, then review retrieval, antibody dilution, and detection as general IHC variables (general IHC practice).
💡Expected MAP3K8 appearanceCall a result positive when identifiable cells show predominantly cytoplasmic staining, potentially strong in bone marrow hematopoietic cells (UniProt P41279; HPA: High in bone marrow); dominant nuclear or sharply membranous color warrants review (HPA subcellular; general IHC practice).
How each factor affects the staining
Compartment and topologyMAP3K8 is cytoplasmic and has no transmembrane segment (UniProt P41279); HPA independently reports supported cytosol localization (HPA subcellular). Score cell-associated cytoplasmic color, using morphology to distinguish it from surrounding deposit (general IHC practice).
Tissue and cell selectionHPA reports High staining in bone marrow hematopoietic cells and bronchial respiratory epithelial cells, but Low staining in muscle cells and no detection in vaginal squamous epithelium (HPA tissue IHC). Select and score the relevant cell population rather than treating a whole section as uniformly positive (general IHC practice).
IHC antibody evidenceHPA rates IHC staining Supported for HPA017962 and CAB005120 (HPA antibodies). The tissue profile has medium consistency with RNA expression (HPA tissue IHC); use controls and morphology when interpreting a surprising stain (general IHC practice).
Isoforms and epitopeUniProt lists two MAP3K8 isoforms and a kinase domain at residues 138–388 (UniProt P41279). The supplied sources give no antibody epitope, so they cannot establish which isoforms an IHC reagent detects or predict an epitope-specific staining difference.
Processing and modificationUniProt lists one chain spanning residues 1–467, with no signal peptide or propeptide, and reports phosphorylation sites (UniProt P41279). These annotations do not establish a distinct processed or phospho-specific IHC pattern without epitope evidence.
IF/ICC: what should appear?HPA reports supported cytosol localization by ICC-IF and Supported ICC validation for HPA017962 (HPA subcellular; HPA antibodies). That supports a cytosolic localization expectation; IF/ICC preparation and staining conditions belong to its separate guide.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive tissue is blank.A blank bone marrow hematopoietic population disagrees with HPA's High staining report (HPA tissue IHC); failed retrieval, antibody incubation, or detection are possibilities (general IHC practice).Confirm the relevant cells are present, inspect the positive control, and review retrieval, dilution, incubation, and chromogen steps one at a time (general IHC practice).
Color is mainly nuclear or outlines cell membranes.The distribution conflicts with cytoplasmic/cytosolic localization (UniProt P41279; HPA subcellular); nonspecific staining or misread tissue structure is possible (general IHC practice).Compare with morphology and the negative control, then reassess antibody and detection conditions before scoring the discordant compartment (general IHC practice).
Vaginal squamous cells appear strongly positive.HPA reports no detectable staining in that population (HPA tissue IHC). Cross-reactivity or endogenous detection activity is possible, particularly if controls also color (general IHC practice).Review the negative control and cell identity; check the detection system's endogenous-activity blocking and repeat with an independently validated IHC antibody if needed (general IHC practice; HPA antibodies).
All tissue compartments show uniform brown haze.A field-wide haze cannot be confidently assigned to cytoplasmic MAP3K8 (HPA tissue IHC). Incomplete washing, blocking, or excessive chromogen development are general possibilities (general IHC practice).Inspect a negative control and unstained areas; adjust washing, blocking, or development only after identifying which step contributes background (general IHC practice).
A mixed tissue looks negative at low magnification.HPA reports cell-specific levels, including Low staining in muscle cells and High staining in selected glandular or immune cells (HPA tissue IHC). Abundant low-signal cells may dominate the field.Identify and score each relevant cell population at higher magnification; compare its cytoplasmic signal with a suitable positive control (general IHC practice).
A positive section stains weakly on repeat runs.Target-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.Run comparable positive and negative controls with the section; document retrieval, antibody dilution, detection, and development conditions before changing one variable (general IHC practice).

Sample controls for MAP3K8 IHC & IF

🧪Run bone marrow first: hematopoietic cells should stain (HPA: High in bone marrow hematopoietic cells). Run vagina as the negative tissue (HPA: Not detected in vaginal squamous epithelial cells); any independently verified target-negative cells within the bone marrow slide should show only counterstain or background, since the supplied HPA rows identify no internal-negative cell type.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Vagina (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MAP3K8 in A-431, U-251MG, U2OS, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only), host- and clonality-matched rabbit IgG isotype, and MAP3K8 knockout or antigen-peptide competition controls (caption: rabbit anti-MAP3K8). For bone marrow DAB staining, quench endogenous peroxidase and check for endogenous biotin background when using the caption’s biotin-based detection system (caption: biotinylated secondary and SABC/DAB).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported; the selected PB10007 paraffin-section caption also leaves the fixative unreported. The caption uses heat retrieval in EDTA at pH 8.0 for rat brain, but does not establish whether retrieval is required in bone marrow. There is no supplied comparison showing that frozen sections or IF are easier; endogenous peroxidase in bone marrow can complicate chromogenic scoring, while HPA supports cytosolic localisation for ICC-IF interpretation (HPA: Cytosol supported).

HPA tissue IHC evidence for MAP3K8

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Cerebellum Cells in granular layer High Protein (IHC) HPA →
Cerebral cortex Neuropil High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Vagina Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced MAP3K8 IHC Tips

Troubleshoot MAP3K8 staining in paraffin sections by checking retrieval, compartment, cell type and controls before comparing chromogenic signal.

What retrieval should I try first if MAP3K8 staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet PB10007). The selected tissue image used this retrieval before 1 μg/ml primary antibody overnight at 4°C, so repeat those conditions when comparing results (datasheet PB10007). Keep section thickness, heating and cooling consistent across test and control slides, since uneven retrieval can change chromogenic intensity (standard IHC practice). If staining remains weak, test another retrieval condition on matched sections while retaining the EDTA slide as a reference (standard IHC practice). Check morphology and no-primary controls before treating stronger DAB deposition as improved MAP3K8 detection (standard IHC practice).
Can fixation explain weak or uneven MAP3K8 staining?
The selected paraffin-section caption does not state a fixative, so MAP3K8-specific fixation sensitivity is unknown for this antibody (datasheet PB10007). Record the fixative, fixation duration and tissue processing history for every comparison, because these variables can alter epitope accessibility in IHC (standard IHC practice). When troubleshooting, compare sections processed together and keep the documented EDTA pH 8.0 retrieval constant (datasheet PB10007; standard IHC practice). Assess tissue preservation alongside signal: disrupted architecture or uneven staining can confound cell-level scoring (standard IHC practice). Do not infer fixation tolerance from the reported tissue staining pattern or MAP3K8 protein features (HPA: tissue IHC; UniProt P41279).
Where should convincing MAP3K8 staining appear in a paraffin section?
Expect mainly cytoplasmic staining: MAP3K8 is annotated in the cytoplasm, and tissue staining is reported as cytoplasmic in most tissues (UniProt P41279; HPA: tissue IHC). Its supported cellular location is the cytosol, and the protein has no transmembrane segment (HPA: subcellular; UniProt P41279 topology). Compare cell types within the same section rather than treating all brown deposits as equivalent (standard IHC practice). Hematopoietic cells in bone marrow provide a reported high-expression reference, while squamous epithelial cells in vagina are reported as not detected (HPA: tissue IHC). Strong membrane-only or nuclear-only signal warrants review with controls before assignment to MAP3K8 (HPA: subcellular; standard IHC practice).
Could isoforms or epitope accessibility change my IHC result?
MAP3K8 has 2 annotated isoforms, but the supplied antibody evidence does not identify which isoforms its epitope recognizes (UniProt P41279; datasheet PB10007). The protein contains a kinase domain at residues 138–388 and several annotated phosphorylation sites, including residues 141 and 400 (UniProt P41279). Without an epitope map, staining differences cannot be assigned to an isoform or modification (standard IHC interpretation). Compare serial sections with a separate, characterized antibody if isoform recognition matters, while documenting each antibody's validation independently (standard IHC practice). Use the same EDTA pH 8.0 retrieval across that comparison so processing is less likely to explain discordance (datasheet PB10007; standard IHC practice).
How should I investigate MAP3K8 localisation by IF after chromogenic IHC?
Use IF as a separate validation experiment and check whether the chosen antibody has IF/ICC evidence; the selected PB10007 caption documents paraffin-section IHC (datasheet PB10007). Multiplex MAP3K8 with a marker identifying the cell population under study, then assess overlap at the cell level (standard IF practice). MAP3K8 is cytosolic and lacks a transmembrane segment, so use permeabilisation appropriate for access to an intracellular epitope (HPA: subcellular; UniProt P41279 topology; standard IF practice). Choose fluorophores after inspecting tissue autofluorescence in unstained sections, and include single-stain controls for channel separation (standard IF practice). Compare the IF distribution with cytoplasmic chromogenic staining without assuming identical assay sensitivity (HPA: tissue IHC; standard IF practice).
How can I distinguish MAP3K8 signal from chromogenic background?
The selected workflow used 10% goat serum blocking, a biotinylated secondary antibody and streptavidin-biotin detection with DAB (datasheet PB10007). Include no-primary and detection-only controls to identify secondary binding or staining from the detection system (standard IHC practice). Apply a peroxidase block before DAB development where needed, and evaluate endogenous biotin if using the documented biotin-based system (standard IHC practice; datasheet PB10007). Compare staining at section edges, folds and damaged regions with intact tissue before calling diffuse brown signal positive (standard IHC practice). If background persists, optimise blocking and washing while holding retrieval and primary concentration at their documented reference conditions (datasheet PB10007; standard IHC practice).
How should I score MAP3K8 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored cell population and cytoplasmic compartment before reviewing outcomes, consistent with MAP3K8 localisation (UniProt P41279; HPA: tissue IHC). For cell-level intensity, report the percentage at each staining grade or an H-score from 0–300, with the grading rule specified (standard IHC practice). For infiltrating populations, report positive-cell density per mm² of viable tissue or per defined region (standard IHC practice). Normalise counts to the number of evaluable cells or measured viable area, and exclude folds, edges and necrotic regions consistently (standard IHC practice). Keep retrieval, detection and image-analysis thresholds fixed across groups, and score matched controls alongside them (standard IHC practice).
Which patterns would make a MAP3K8-positive result doubtful?
A cytoplasmic pattern in the expected cell population is more credible than isolated nuclear or membrane-only deposits, given the supported cytosolic localisation (HPA: subcellular; UniProt P41279). Bone marrow hematopoietic cells are reported high, whereas vaginal squamous epithelial cells are reported as not detected; use those patterns as context, not universal controls (HPA: tissue IHC). Review edge staining, folds and necrotic areas for processing artefacts before assigning positive cells (standard IHC practice). Check no-primary and detection-only slides for endogenous enzyme activity or detection-system background, especially with DAB and biotin-based detection (standard IHC practice; datasheet PB10007). Treat unexpected patterns cautiously because the tissue IHC profile has supported, medium consistency with RNA data (HPA: tissue IHC).
Boster reagents

Best MAP3K8 / Mitogen-activated protein kinase kinase kinase 8 IHC Antibodies

PB10007 has IHC images from paraffin sections of rat and mouse brain and human lung and pancreatic cancer, plus an IF/ICC image of HepG2 cells (catalog: image captions).

Real IHC data IHC analysis of MAP3K8 using anti-MAP3K8 antibody (PB10007). MAP3K8 was detected in paraffin-embedded section of rat brain tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-MAP3K8 Antibody (PB10007) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-MAP3K8 Antibody ®
Cat # PB10007

PB10007 is the sole SKU; it lists IHC, IF and ICC applications and Human and Rat reactivity (catalog: applications and reactivity). Its images show paraffin-section IHC in rat and mouse brain and human lung and pancreatic cancer, plus IF/ICC in HepG2 cells (PB10007: image captions).

Which to pick: For tissue IHC, choose PB10007 for paraffin sections: its rat brain caption documents EDTA pH 8 retrieval and 1 μg/ml primary antibody; the fixative is unreported (PB10007: IHC image caption). For IF/ICC, PB10007 has a HepG2-cell image using 5 μg/ml primary antibody (PB10007: IF image caption). For cross-species planning, PB10007 lists Human and Rat reactivity, while an IHC caption also shows mouse brain; clonality is unreported (catalog: reactivity and clone; PB10007: IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P41279 (M3K8_HUMAN, Mitogen-activated protein kinase kinase kinase 8).
  2. Human Protein Atlas. MAP3K8 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. MAP3K8 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. MAP3K8 antibody validation summary (2 antibodies).
  5. MAP3K8 Is a Prognostic Biomarker and Correlated With Immune Response in Glioma. Frontiers in molecular biosciences 2021 — PMC8733582.
  6. Clinical genome sequencing uncovers potentially targetable truncations and fusions of MAP3K8 in spitzoid and other melanomas. Nature medicine 2019 — PMC9673241.
  7. Role of Targeted Sequencing in Routine Diagnostics of Spitz Melanocytic Neoplasms-An Analysis of 70 Cases. Journal of cutaneous pathology 2025 — PMC11710898.
  8. Melanoma pathology: new approaches and classification. The British journal of dermatology 2021 — PMC9292921.
  9. PubMed PMID:2072910 — UniProt-cited evidence.
  10. PubMed PMID:8226782 — UniProt-cited evidence.
  11. PubMed PMID:8479752 — UniProt-cited evidence.