MAST4 / Microtubule-associated serine/threonine-protein kinase 4 · IHC design guide

Design Immunohistochemistry for MAST4

Plan MAST4 paraffin IHC around mainly cytoplasmic staining, with high signal in esophageal squamous and bladder urothelial cells (HPA tissue IHC). Start with the catalog antibody’s 1:100–1:300 IHC dilution range (datasheet) and interpret staining in light of its low consistency with RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MAST4 (IHC for MAST4): expected localisation Mainly cytoplasmic staining in several tissues (HPA tissue IHC), antibody A11085-1, validated IHC image, and IHC protocol steps
Printable MAST4 IHC protocol sheet — expected localisation Mainly cytoplasmic staining in several tissues (HPA tissue IHC), antibody A11085-1, controls and protocol steps. Open the full MAST4 IHC guide →

MAST4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Mainly cytoplasmic staining in several tissues (HPA tissue IHC)
Staining pattern High cytoplasmic staining in esophageal and bladder epithelia (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Esophagus+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Antibody staining has low consistency with RNA expression (HPA tissue IHC)
Regulation Expression regulation is not established (UniProt)
Isoform / epitope 5 isoforms; epitope coverage is unspecified (UniProt; datasheet)
Section 1

Recommended MAST4 IHC & IF Protocols

The catalog antibody has an IHC-P protocol; the following published MAST4 IHC methods provide additional conditions for tissue sections (PMC11012408; PMC4636393; PMC11981763).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human testis tissue; fixative not specified (datasheet A11085-1)
FixationImage fixative and duration unreported (datasheet A11085-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-MAST4, 1:100 - 1:300 (datasheet A11085-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMAST4-positive staining in squamous epithelial cells of esophagus (HPA tissue IHC: High). HPA tissue profile: Mainly cytoplasmic expression in several tissues, high in esophagus and urinary bladder. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page antigen-retrieval rule); the breast-tissue protocol reports boiling citrate for 30 min (PMC4636393 methods).
Section 2

What Is the Expected MAST4 Staining Pattern?

MAST4 is annotated as cytoplasmic and has no transmembrane segment (UniProt O15021 topology). In paraffin tissue sections, expect mainly cytoplasmic staining, with high signal reported in esophageal squamous epithelial cells and urinary bladder urothelial cells (HPA tissue IHC). HPA rates the tissue profile Approved but reports low consistency between antibody staining and RNA expression, so treat the pattern as a reference for comparison (HPA tissue IHC).

What am I looking at on my slide?
Strong cytoplasmic staining in esophageal squamous epithelium or bladder urothelium.This matches HPA's High staining in those cell types and its mainly cytoplasmic tissue profile (HPA tissue IHC).
Predominantly nuclear staining in a tissue section.Assess cautiously: tissue IHC is mainly cytoplasmic, while ICC-IF also places MAST4 in the nucleoplasm (HPA tissue IHC; HPA subcellular ICC-IF).
Strong staining confined to cells outside the reported positive cell types.Compare cell identity and controls before assigning MAST4; cross-reactivity or endogenous detection activity can mimic cell-specific signal (general IHC practice; HPA tissue IHC).
Diffuse staining across cells and surrounding tissue, with poor compartment definition.This is less consistent with HPA's mainly cytoplasmic profile; assess background with an appropriate no-primary control (HPA tissue IHC; general IHC practice).
No staining in esophageal squamous epithelium or bladder urothelium.HPA reports High staining in both; check assay performance, while allowing for its reported antibody–RNA inconsistency (HPA tissue IHC).
💡Expected MAST4 appearanceA convincing positive is clear cytoplasmic signal in esophageal squamous epithelial cells or bladder urothelial cells, where HPA reports High staining; widespread poorly defined signal or dominant membrane staining warrants review (HPA tissue IHC; UniProt O15021 topology).
How each factor affects the staining
Tissue and cell choiceUse esophageal squamous epithelium or bladder urothelium as positive-pattern references; both are High in HPA tissue IHC.
Comparison cellsAdipocytes and bronchial respiratory epithelial cells are reported Not detected; compare only the named cells (HPA tissue IHC).
CompartmentUniProt lists cytoplasm and no transmembrane segment; HPA tissue IHC describes mainly cytoplasmic signal (UniProt O15021; HPA tissue IHC).
Confidence in tissue callsHPA rates tissue IHC Approved but notes low antibody–RNA consistency; a tissue result alone needs cautious interpretation (HPA tissue IHC).
Testis exceptionHPA reports High pachytene spermatocyte staining, although UniProt lists testis as an expression exception (HPA tissue IHC; UniProt O15021).
Does ICC-IF predict the IHC pattern?Only partly: ICC-IF reports approved nucleoplasm and cytosol localization; tissue IHC reports mainly cytoplasmic staining (HPA subcellular ICC-IF; HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in an HPA high-staining reference tissue.The run may lack detectable signal; HPA also reports low antibody–RNA consistency (general IHC practice; HPA tissue IHC).Confirm the expected cells are present, then review the validated IHC-P dilution, detection reagents and positive control (general IHC practice).
Weak cytoplasmic signal in expected cells.Low signal can reflect staining conditions; intensity should be judged against the reported cell-specific pattern (general IHC practice; HPA tissue IHC).Compare with an on-run positive control and check the antibody dilution and retrieval conditions specified for the assay (general IHC practice).
Widespread brown staining with little cell definition.Background or endogenous detection activity may obscure the mainly cytoplasmic pattern (general IHC practice; HPA tissue IHC).Inspect a no-primary control; review blocking, washes and endogenous peroxidase control for chromogenic IHC (general IHC practice).
Predominantly membrane or extracellular staining.That distribution conflicts with the cytoplasmic annotation and absence of a transmembrane segment (UniProt O15021 topology).Check the section and controls, then reassess antibody specificity before scoring it as MAST4 (general IHC practice).
Nuclear staining is stronger than cytoplasmic staining.ICC-IF includes nucleoplasm, but HPA describes tissue IHC as mainly cytoplasmic (HPA subcellular ICC-IF; HPA tissue IHC).Record both compartments separately and compare the nuclear pattern with controls; avoid treating ICC-IF as an IHC intensity standard (general IHC practice).
Testis staining conflicts with an expression summary.HPA reports High pachytene spermatocyte staining; UniProt names testis as an expression exception (HPA tissue IHC; UniProt O15021).Score pachytene spermatocytes specifically and report the source discrepancy alongside the observed slide pattern (HPA tissue IHC; UniProt O15021).

Sample controls for MAST4 IHC & IF

🧪Run esophagus first: squamous epithelial cells should stain (HPA: High in esophageal squamous epithelial cells). Use adipose tissue as a biological comparison (HPA: Not detected in adipocytes); on the esophagus slide, cells without specific staining should show only background chromogen, but their MAST4-negative status requires independent validation.
Positive control tissue: Esophagus (Squamous epithelial cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MAST4 in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (approved), Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a concentration-matched isotype control matched to the primary antibody’s host species and clonality, and a knockout specimen or peptide-blocked primary antibody; peptide blocking is documented for the catalog antibody A11085-1 in testis (selected tissue-IHC caption). Quench endogenous peroxidase and assess background staining on the positive section (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window, fixation effect, and antigen-retrieval dependency are unreported in the supplied evidence; the fixative is also unreported in the selected A11085-1 paraffin-section caption (selected tissue-IHC caption). Optimize retrieval on paraffin sections empirically (standard IHC practice). The evidence does not establish that frozen sections or IF are easier, or identify a tissue-specific artefact; HPA ICC-IF reports nucleoplasm and cytosol staining in A-431, U-251MG, and U2OS (HPA subcellular).

HPA tissue IHC evidence for MAST4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Esophagus Squamous epithelial cells High Protein (IHC) HPA →
Testis Pachytene spermatocytes High Protein (IHC) HPA →
Urinary bladder Urothelial cells High Protein (IHC) HPA →
Cerebellum Purkinje cells Medium Protein (IHC) HPA →
Cerebral cortex Glial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Colon Endothelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced MAST4 IHC Tips

Troubleshoot MAST4 staining in paraffin section IHC using compartment, cell type and antibody controls; IF considerations appear in one dedicated entry.

How should I adjust retrieval when MAST4 staining is weak?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 min (page retrieval setting). Allow slides to cool in retrieval buffer, then compare stained sections with a no-primary control processed through the same heat cycle (standard IHC practice). MAST4 is annotated as cytoplasmic and lacks a transmembrane segment, but those features do not establish which retrieval condition best exposes this antibody’s epitope (UniProt O15021). If staining remains weak, test EDTA at pH 9.0 on an adjacent section as a fallback, keeping detection conditions constant (standard IHC practice). Compare cytoplasmic signal and tissue preservation in esophageal squamous cells or urothelial cells, both reported as high in tissue IHC (HPA tissue IHC).
Could fixation explain absent MAST4 staining in paraffin sections?
MAST4-specific sensitivity to fixation is unknown: the selected antibody caption identifies paraffin-embedded testis but does not state a fixative (caption A11085-1). Record the fixative, fixation duration and processing history for each specimen before attributing a weak result to antigen loss (standard IHC practice). Compare sections with similar handling and run the same citrate pH 6.0 retrieval for 20 min across the comparison (page retrieval setting). If the signal differs, vary one processing factor at a time while holding antibody incubation and chromogenic development constant (standard IHC practice). Do not infer fixation tolerance from MAST4 phosphorylation sites or tissue expression patterns; neither directly tests fixation sensitivity (UniProt O15021; HPA tissue IHC).
Which staining compartment should I expect for MAST4?
In chromogenic tissue IHC, expect mainly cytoplasmic staining across several tissues, including high staining in esophagus and urinary bladder (HPA tissue IHC). UniProt annotates MAST4 as cytoplasmic and reports no transmembrane segment, so isolated crisp membrane staining deserves scrutiny (UniProt O15021). HPA cell imaging additionally reports approved nucleoplasmic and cytosolic locations; evaluate any nuclear tissue signal alongside cell identity and controls (HPA subcellular; standard IHC practice). Examine esophageal squamous epithelial cells or urothelial cells with matched counterstaining, and note whether signal tracks intact cells rather than section folds (HPA tissue IHC; standard IHC practice). Score nuclear and cytoplasmic compartments separately if both persist after matched no-primary and peptide-block comparisons (standard IHC practice; caption A11085-1).
How can isoforms and epitope location complicate MAST4 IHC?
MAST4 has 5 listed isoforms, but the supplied antibody caption does not locate its epitope within any isoform (UniProt O15021; caption A11085-1). The protein contains a kinase domain at residues 570–843 and a PDZ domain at 1141–1229; these coordinates alone cannot establish antibody coverage (UniProt O15021). Request the immunogen sequence or epitope map for the catalog antibody, then check its presence in the isoforms relevant to the specimen (standard IHC practice). MAST4 also has annotated phosphoserines, including residues 206 and 914, so avoid interpreting staining differences as phosphorylation changes without epitope-specific validation (UniProt O15021; standard IHC practice). The peptide-blocked testis image supports competition for that photographed staining pattern, but does not identify every stained isoform (caption A11085-1).
How should I investigate MAST4 localisation by multiplex IF?
On its separate IF/ICC guide, pair MAST4 with a validated marker for the expected cell population, such as a squamous epithelial marker when examining esophageal cells (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores and assign the suspected weaker channel to a bright dye outside the specimen’s strongest autofluorescence range (standard IF practice). Because MAST4 has no transmembrane segment and is annotated as cytoplasmic, use permeabilisation appropriate for intracellular access, then check its effect on the companion marker (UniProt O15021; standard IF practice). Assess cytosolic and nucleoplasmic signals separately because both are approved locations in HPA cell imaging (HPA subcellular). Include single-stain and no-primary controls to distinguish bleed-through and autofluorescence from specific colocalisation (standard IF practice).
What should I check when MAST4 chromogenic staining is diffuse?
First compare the stained section with a matched no-primary control to locate signal produced by the detection system rather than antibody binding (standard IHC practice). For peroxidase detection, apply an endogenous peroxidase block before the detection reagent and inspect whether residual pigment or enzyme activity resembles the DAB signal (standard IHC practice). Use an appropriate protein block, wash between steps and compare a shorter chromogen development on adjacent sections without changing retrieval (standard IHC practice). The selected paraffin testis image includes a synthesized-peptide block, which can help assess competition for this antibody in that image (caption A11085-1). Examine intact cell outlines and expected cytoplasmic distribution before accepting diffuse deposits as MAST4 staining (HPA tissue IHC; standard IHC practice).
How should I quantify heterogeneous MAST4 staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring: HPA reports high staining in esophageal squamous epithelial cells and urothelial cells, with mainly cytoplasmic tissue expression (HPA tissue IHC). Use an H-score from 0–300, calculated from the percentages of cells at intensity grades 0–3, or report the percentage of positive target cells (standard IHC practice). Keep exposure-independent chromogen development, section handling and counterstain conditions consistent across the comparison (standard IHC practice). Normalise positive counts to the number of evaluable cells in the specified compartment; for spatial counts, report positive cells per mm² of viable annotated tissue (standard IHC practice). State the scoring threshold and exclude folds, necrosis and edge deposits before comparing specimens (standard IHC practice).
How can I distinguish true MAST4 staining from artefact?
Look for reproducible signal in intact esophageal squamous epithelial cells or urothelial cells, which HPA reports as high, and assess cytoplasmic distribution (HPA tissue IHC). Nuclear staining needs separate scrutiny because HPA cell imaging also approves nucleoplasmic localisation, while tissue IHC is described as mainly cytoplasmic (HPA subcellular; HPA tissue IHC). Treat staining confined to section edges, folds or necrotic regions as suspect, and compare it with matched no-primary and peroxidase controls (standard IHC practice). The selected testis paraffin image includes synthesized-peptide blocking, which supports a competition check for that pictured staining pattern (caption A11085-1). Interpret discordant cells cautiously because the HPA tissue IHC record is Approved yet reports low consistency between antibody staining and RNA expression (HPA tissue IHC).
Boster reagents

Best MAST4 / Microtubule-associated serine/threonine-protein kinase 4 IHC Antibodies

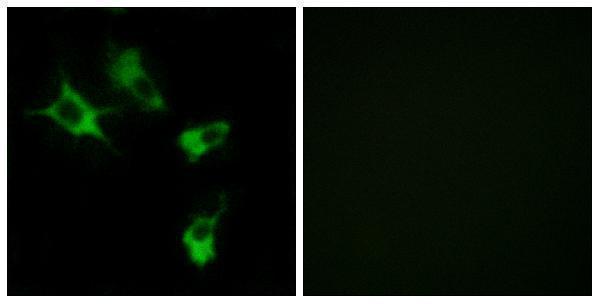
The anti-MAST4 catalog antibody has IHC data from paraffin-embedded human testis and IF data from COS7 cells (catalog image captions); listed reactivity covers human and mouse (catalog reactivity).

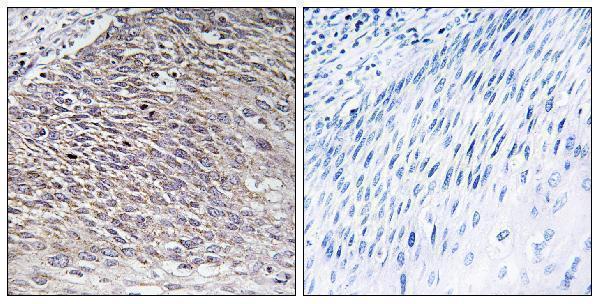
Real IHC data Immunohistochemistry analysis of paraffin-embedded human testis tissue, using MAST4 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-MAST4 Antibody
Cat # A11085-1

A11085-1 lists IHC, IF and ICC applications and human and mouse reactivity (catalog applications; catalog reactivity). Its IHC image shows paraffin-embedded human testis, and its IF image shows COS7 cells; both include peptide-blocked comparisons (catalog image captions).

Which to pick: For tissue IHC, choose A11085-1: its own image shows paraffin-embedded human testis, but does not report the fixative (catalog IHC image caption). For IF/ICC, the same rabbit polyclonal antibody lists both applications and has a COS7-cell IF image (catalog host; catalog dilution_raw; catalog applications; catalog IF image caption). For human or mouse samples, its reactivity list covers both species, while the supplied tissue IHC image documents human tissue only (catalog reactivity; catalog IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O15021 (MAST4_HUMAN, Microtubule-associated serine/threonine-protein kinase 4).
  2. Human Protein Atlas. MAST4 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. MAST4 subcellular location (ICC-IF): Localized to the nucleoplasm and cytosol..
  4. Human Protein Atlas. MAST4 antibody validation summary (1 antibodies).
  5. Nuclear MAST4 Suppresses FOXO3 through Interaction with AKT3 and Induces Chemoresistance in Pancreatic Ductal Carcinoma. International journal of molecular sciences 2024 — PMC11012408.
  6. Proteomic Analysis of Urine to Identify Breast Cancer Biomarker Candidates Using a Label-Free LC-MS/MS Approach. PloS one 2015 — PMC4636393.
  7. Integrating single-cell sequencing and clinical insights to explore malignant transformation in odontogenic keratocyst. Computational and structural biotechnology journal 2025 — PMC11981763.
  8. Mast4 determines the cell fate of MSCs for bone and cartilage development. Nature communications 2022 — PMC9270402.
  9. PubMed PMID:17086981 — UniProt-cited evidence.
  10. PubMed PMID:15372022 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.