MED1 / Mediator of RNA polymerase II transcription subunit 1 · IHC design guide

Design Immunohistochemistry for MED1

Plan chromogenic MED1 IHC in paraffin sections using the nuclear tissue pattern as a reference (HPA tissue IHC). Breast glandular cells show high staining (HPA tissue IHC); optimize the catalog antibody within its 1:50–1:200 IHC dilution range (datasheet).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MED1 (IHC for MED1): expected localisation Nuclear staining in most tissues (HPA tissue IHC), antibody A00550-1, validated IHC image, and IHC protocol steps
Printable MED1 IHC protocol sheet — expected localisation Nuclear staining in most tissues (HPA tissue IHC), antibody A00550-1, controls and protocol steps. Open the full MED1 IHC guide →

MED1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in most tissues (HPA tissue IHC)
Staining pattern Nuclear staining across most tissues (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Low agreement between staining and RNA expression (HPA tissue IHC)
Regulation Ubiquitously expressed (UniProt)
Isoform / epitope 2 isoforms; epitope impact undetermined (UniProt)
Section 1

Recommended MED1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is followed by published MED1 staining protocols for bladder, liver, prostate, and heart sections (PMC5355444; PMC2812575; PMC5838364; PMC4993490).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast carcinoma tissue; fixative not specified (datasheet A00550-1)
FixationImage fixative and duration unreported (datasheet A00550-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-MED1, 1:50-1:200 (datasheet A00550-1)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMED1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with the page’s Tris-EDTA pH 9.0 retrieval at 95–98 °C for 20 min for this nuclear target (UniProt Q15648: nucleus); optimize against the published samples.
Section 2

What Is the Expected MED1 Staining Pattern?

MED1 staining should be predominantly nuclear in most tissues, with strong staining reported in several glandular and epithelial cell populations (HPA tissue IHC: nuclear expression in most tissues; High in breast glandular cells and esophageal squamous epithelial cells). MED1 is a nuclear protein with no transmembrane segment (UniProt Q15648: subcellular location and topology). Interpret intensity with care: HPA rates its tissue IHC profile Approved but reports low consistency between antibody staining and RNA expression data (HPA tissue IHC).

What am I looking at on my slide?
Nuclear staining in glandular cells of breast, colon, or duodenum, or in esophageal squamous epithelial cells.This fits the expected distribution; HPA reports High staining in each of these cell populations (HPA tissue IHC). Judge the compartment within the named cells rather than treating every stained structure in the section as equivalent (UniProt Q15648: nucleus).
Predominantly cytoplasmic or membrane outlined staining, with little nuclear signal.Treat this as a compartment mismatch requiring investigation: MED1 is nuclear and has no transmembrane segment (UniProt Q15648). A minority nucleolar pool is possible after MAPK1 or MAPK3 phosphorylation, but that does not explain a dominant membrane pattern (UniProt Q15648: subcellular location).
Strong staining in adipocytes, hippocampal glial cells, or liver cholangiocytes.These cell populations are reported as Not detected in HPA tissue IHC (HPA tissue IHC). Check whether the signal reflects nonspecific antibody binding or endogenous chromogenic activity (general IHC practice). Their HPA status is an observed pattern, not proof that every specimen must be negative.
Diffuse staining across nuclei, cytoplasm, and spaces without clear cell boundaries.The distribution is difficult to score as MED1: the expected tissue profile is predominantly nuclear (HPA tissue IHC; UniProt Q15648: nucleus). Compare with a no primary antibody control and review blocking, washing, and chromogen development as general IHC checks (general IHC practice).
No nuclear staining in an otherwise interpretable section containing colon or breast glandular cells.A technical false negative is possible because HPA reports High staining in these cells (HPA tissue IHC). First confirm that the expected cells are present and preserved; then review the validated IHC conditions and detection controls (general IHC practice). HPA’s low RNA–staining consistency limits claims about any single specimen (HPA tissue IHC).
💡Expected MED1 appearanceCall the result consistent with MED1 when staining is predominantly nuclear in the relevant cells, including High signal in HPA positive glandular or epithelial populations; dominant cytoplasmic or membrane staining, or strong signal in HPA Not detected cell populations, warrants review (HPA tissue IHC; UniProt Q15648: nucleus and topology).
How each factor affects the staining
Tissue and cell selection (HPA tissue IHC).HPA reports High staining in breast, colon, and duodenal glandular cells, among other populations, while adipocytes and liver cholangiocytes are Not detected (HPA tissue IHC). Use the named cell population when comparing sections; a tissue name alone is an incomplete scoring unit.
Evidence strength for tissue interpretation (HPA tissue IHC).The tissue IHC profile is Approved, with low consistency between antibody staining and RNA expression data (HPA tissue IHC). Use its positive and negative examples as observed reference patterns; do not infer that RNA abundance predicts staining intensity in an individual section.
Antibody validation by application (HPA antibodies).CAB017696 is listed as Approved for IHC, whereas HPA052818 is listed as Supported for ICC and has no IHC status in the supplied record (HPA antibodies). Match the antibody’s validation to the application when weighing an unexpected result.
Nucleolar and vesicular signals (UniProt Q15648; HPA subcellular).UniProt allows a nucleolar subset after MAPK1 or MAPK3 phosphorylation (UniProt Q15648: subcellular location). HPA ICC-IF supports nucleoplasmic localization but marks additional vesicular localization uncertain (HPA subcellular). Neither observation makes dominant nonnuclear chromogenic tissue staining the expected IHC result.
Isoforms and antigen identity (UniProt Q15648).UniProt lists 2 MED1 isoforms and one annotated protein chain spanning residues 1–1581, with no signal peptide, propeptide, or transmembrane segment (UniProt Q15648). The supplied record gives no antibody epitope, so it cannot establish isoform coverage or epitope specific retrieval behavior.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive reference cells are blank in IHC.The expected nuclear signal is absent from a cell population reported High, such as colon glandular cells (HPA tissue IHC); the specific technical cause is undetermined.Verify cell identity and section integrity, then check the IHC validated antibody conditions, detection reagents, and a positive control in the same run (general IHC practice). Avoid assigning MED1 specific fixation sensitivity; none is supplied.
Only cytoplasmic or membrane staining appears.The dominant compartment conflicts with nuclear MED1 and its lack of a transmembrane segment (UniProt Q15648: subcellular location and topology).Check the counterstain and cell boundaries, then compare with a no primary antibody control and the antibody’s IHC validation status (general IHC practice; HPA antibodies: CAB017696 IHC Approved).
Adipocytes or cholangiocytes stain strongly.These cells are Not detected in the HPA tissue IHC profile (HPA tissue IHC); nonspecific binding or endogenous detection activity may contribute (general IHC practice).Review the staining pattern against neighboring cell types and appropriate background controls; check blocking and endogenous activity controls suited to the detection chemistry (general IHC practice).
Brown signal is widespread and obscures nuclei.Excess background or endogenous chromogenic activity can prevent compartment scoring (general IHC practice); the reference MED1 pattern is predominantly nuclear (HPA tissue IHC).Inspect a no primary antibody control, then review washing, blocking, detection, and development time under the assay’s general IHC workflow (general IHC practice). Score MED1 only where cell boundaries and nuclei remain interpretable.
A small nucleolar signal accompanies nuclear staining.A MED1 subset may enter the nucleolus after MAPK1 or MAPK3 phosphorylation (UniProt Q15648: subcellular location).Record the nucleolar component separately from the dominant nuclear pattern; compare replicate fields and controls before treating it as specific (general IHC practice). The supplied sources do not establish its frequency in paraffin tissue sections.
What pattern should IF/ICC show?HPA supports a mainly nucleoplasmic location and labels additional vesicular localization uncertain (HPA subcellular); UniProt also lists MED1 in the nucleus (UniProt Q15648).Expect predominantly nucleoplasmic signal and interpret vesicular signal cautiously (HPA subcellular). This is an interpretation cue for IF/ICC; use its separate guide for application specific procedure.

Sample controls for MED1 IHC & IF

🧪Run breast first: glandular cells should show nuclear staining (HPA: High in breast glandular cells; UniProt Q15648: nucleus). Run adipose tissue as a negative comparator because adipocytes are listed as not detected (HPA: Not detected in adipocytes); on the breast slide, non-glandular cells without nuclear chromogen can serve as an internal background reference, but their MED1 status is not established by the supplied HPA row.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MED1 in CACO-2, HeLa, U2OS, KOLF2.1J, NIH 3T3, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; an irrelevant IgG control matched to the primary antibody’s host and class or clonality; and MED1-knockout material as a biological negative. For chromogenic breast IHC, check endogenous peroxidase after quenching so residual activity is not scored as MED1 staining (standard IHC practice).
⚠️Feasibility: A target-specific fixation window and retrieval requirement are unreported; the selected A00550-1 paraffin-section breast carcinoma caption gives a dilution of 1:100 but does not report the fixative (selected IHC caption). Optimize antigen retrieval empirically for paraffin IHC; frozen-section performance is unreported, and HPA ICC-IF images support nucleoplasmic localisation but do not establish that tissue IF is easier (HPA: nucleoplasm supported; HPA: ICC-IF cell-line images). In breast sections, score nuclear staining in glandular cells and distinguish it from luminal deposits or stromal background (HPA: High in breast glandular cells; UniProt Q15648: nucleus).

HPA tissue IHC evidence for MED1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Cerebellum Cells in granular layer High Protein (IHC) HPA →
Cerebral cortex Neuropil High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Hippocampus Glial cells Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Section 3

Advanced MED1 IHC Tips

Use nuclear staining, cell identity and matched controls to troubleshoot MED1 chromogenic IHC in paraffin sections (UniProt Q15648 localisation; HPA tissue IHC profile).

How should I retrieve MED1 when nuclear staining is weak in paraffin sections?
Start with Tris-EDTA, pH 9.0, heat-induced epitope retrieval at 95–98 °C for 20 min (page retrieval specification: nuclear antigen). Allow sections to cool in retrieval buffer, then compare the same IHC-validated antibody dilution across a matched positive section and the weak section; the selected A00550-1 image uses 1:100 in paraffin-embedded human breast carcinoma (A00550-1 tissue-IHC caption). If staining remains weak, test a gentler heating interval or citrate pH 6 as a documented fallback while holding detection conditions constant (standard IHC optimisation practice). Score nuclear signal against morphology and background, since MED1 is chiefly nuclear (UniProt Q15648 localisation; HPA tissue IHC profile).
Could fixation explain weak or patchy MED1 staining?
MED1-specific fixation sensitivity is unknown from the supplied evidence; the selected paraffin-section caption does not state its fixative (A00550-1 tissue-IHC caption). Record fixative, fixation duration, section age and processing history for each specimen, then compare sections processed together before attributing weak nuclear staining to antigen loss (standard IHC practice; UniProt Q15648 localisation). Keep retrieval at Tris-EDTA pH 9.0, 95–98 °C for 20 min during that comparison so fixation is the main variable (page retrieval specification: nuclear antigen). Use an established positive section and a no-primary control; tissue staining patterns and MED1 phosphorylation do not establish fixation sensitivity (HPA tissue IHC profile; UniProt Q15648 modified residues).
What MED1 staining pattern should count as plausible in chromogenic IHC?
Prioritise staining within morphologically intact nuclei: MED1 is assigned to the nucleus, and HPA describes nuclear expression in most tissues (UniProt Q15648 localisation; HPA tissue IHC profile). HPA supports nucleoplasmic localisation in ICC/IF, while its additional vesicle assignment is uncertain; these observations alone do not validate vesicular DAB staining in paraffin sections (HPA subcellular profile). A subset may enter the nucleolus after MAPK1 or MAPK3 phosphorylation, so a punctate nuclear pattern warrants comparison with a nuclear counterstain and matched controls (UniProt Q15648 localisation; standard IHC practice). Treat diffuse cytoplasmic colour as unresolved background until it survives detection controls and repeats with preserved morphology (standard IHC practice).
Can isoforms or phosphorylation change what this MED1 antibody detects?
MED1 has 2 listed isoforms and multiple modified residues, including phosphoserines at 588, 664 and 795 (UniProt Q15648 isoforms and modified residues). The supplied evidence gives no epitope map for A00550-1, so neither isoform coverage nor sensitivity to those modifications can be assigned to its IHC signal (A00550-1 tissue-IHC caption; UniProt Q15648 record). Consult the antibody's documented immunogen before interpreting staining differences as isoform-specific, and compare matched sections under identical retrieval and detection conditions (standard IHC validation practice). MED1 has no annotated transmembrane segment, but that topology does not identify an accessible antibody epitope in a processed section (UniProt Q15648 topology).
How can IF help resolve ambiguous MED1 IHC localisation?
Use IF/ICC as a separate localisation check alongside chromogenic IHC, and multiplex MED1 with a marker for the cell type being evaluated in the section (standard IF practice). Expect chiefly nucleoplasmic signal, while treating the reported vesicle signal as uncertain; compare both channels with a nuclear counterstain (HPA subcellular profile). Choose fluorophores after checking tissue autofluorescence and single-colour controls, and keep channel exposure within the detector's linear range (standard IF practice). MED1 lacks a transmembrane segment and is mainly nuclear, so permeabilisation must permit access to an intracellular nuclear epitope; optimise it for the IF antibody and specimen rather than transferring the A00550-1 paraffin caption to IF (UniProt Q15648 topology and localisation; A00550-1 tissue-IHC caption).
How do I reduce diffuse brown background without losing nuclear MED1 signal?
First compare a no-primary section with the stained section, then inspect whether brown colour tracks nuclei or spreads across stroma, damaged edges and debris (standard chromogenic IHC practice; UniProt Q15648 localisation). Quench endogenous peroxidase before DAB development, apply an appropriate protein block and wash thoroughly; these are general detection steps, not MED1-specific validation (standard chromogenic IHC practice). If background persists, shorten chromogen development or titrate the primary around the documented 1:100 image condition while keeping retrieval constant (A00550-1 tissue-IHC caption; standard IHC optimisation practice). Judge improvement by retained nuclear contrast in a matched positive section, because broad nuclear expression is reported across most tissues (HPA tissue IHC profile).
How should I score heterogeneous nuclear MED1 staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and viable tissue area before scoring, then record the percentage of positive nuclei and nuclear intensity using a prespecified scale (standard IHC scoring practice; UniProt Q15648 localisation). An H-score can combine intensity categories 0–3 with their percentages to yield 0–300; report the threshold and any excluded necrotic or edge regions (standard IHC scoring practice). Normalise counts to the number of evaluable nuclei, or report positive-cell density per mm² when tissue area is the denominator (standard image-analysis practice). Keep retrieval, detection time and image settings matched, and avoid treating HPA's approved profile as a quantitative reference because staining and RNA show low consistency (HPA tissue IHC reliability).
When is a MED1-positive area convincing rather than an artefact?
A convincing result is reproducible nuclear staining in intact, identifiable cells with low signal in the no-primary control (UniProt Q15648 localisation; standard IHC validation practice). HPA reports high staining in breast glandular cells and no detection in adipocytes, but its tissue profile has low consistency with RNA expression, so these are comparison points rather than absolute pass criteria (HPA tissue IHC profile and reliability). Recheck apparent cytoplasmic-only staining, staining restricted to section edges or necrosis, and brown deposits that persist without primary antibody (standard chromogenic IHC practice; UniProt Q15648 localisation). Distinguish cell identity with morphology and a suitable marker before linking an intensity difference to MED1 biology or transcriptional activity (standard IHC interpretation practice; UniProt Q15648 function).
Boster reagents

Best MED1 / Mediator of RNA polymerase II transcription subunit 1 IHC Antibodies

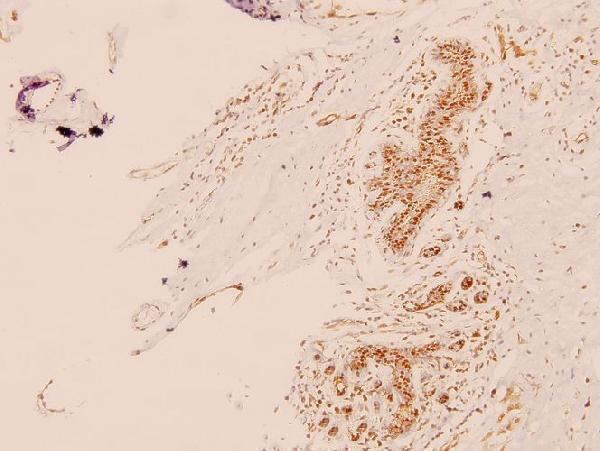
A00550-1 has an IHC image from paraffin-embedded human breast carcinoma (catalog image caption); listed reactivity covers human, mouse and rat (catalog: reactivity). No IF data are supplied (catalog: applications and images).

Real IHC data Immunohistochemistry (IHC) analyzes of TRAP220 (P697) pAb in paraffin-embedded human breast carcinoma tissue at 1:100.
Anti-TRAP220 (P697) MED1 Antibody
Cat # A00550-1

A00550-1 will render with an IHC image from paraffin-embedded human breast carcinoma at 1:100 (catalog image caption). Its listed applications are IHC and WB, and its listed reactivity is human, mouse and rat (catalog: applications and reactivity).

Which to pick: Choose A00550-1 for tissue IHC: its own image shows paraffin-embedded human breast carcinoma (catalog image caption), and its listed IHC dilution is 1:50–1:200 (catalog: dilution). The caption does not report the fixative (catalog image caption). For cross-species planning, A00550-1 lists mouse and rat reactivity, although its IHC image shows human tissue only (catalog: reactivity; catalog image caption); no IF/ICC application or image is supplied for it (catalog: applications and images).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q15648 (MED1_HUMAN, Mediator of RNA polymerase II transcription subunit 1).
  2. Human Protein Atlas. MED1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. MED1 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to vesicles..
  4. Human Protein Atlas. MED1 antibody validation summary (2 antibodies).
  5. Mediator Complex Subunit MED1 Protein Expression Is Decreased during Bladder Cancer Progression. Frontiers in medicine 2017 — PMC5355444.
  6. Transcription coactivator PBP/MED1-deficient hepatocytes are not susceptible to diethylnitrosamine-induced hepatocarcinogenesis in the mouse. Carcinogenesis 2010 — PMC2812575.
  7. ERK and AKT signaling drive MED1 overexpression in prostate cancer in association with elevated proliferation and tumorigenicity. Molecular cancer research : MCR 2013 — PMC5838364.
  8. Cardiomyocyte-Specific Ablation of Med1 Subunit of the Mediator Complex Causes Lethal Dilated Cardiomyopathy in Mice. PloS one 2016 — PMC4993490.
  9. PubMed PMID:9444950 — UniProt-cited evidence.
  10. PubMed PMID:9653119 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.