This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic MEN1 IHC in paraffin sections using the catalog antibody’s documented workflow (datasheet A00331-1). Assess nuclear staining with matched controls, bearing in mind that tissue-IHC reliability is uncertain (HPA tissue IHC; standard IHC practice).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear tissue staining; reliability uncertain (HPA tissue IHC) | |
| Staining pattern | Nuclear staining in several tissues (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A00331-1) | |
| Positive control | Adipose tissue+4 more · see all | |
| Negative control | Bronchus+4 more · see all |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Cytoplasmic staining was disregarded (HPA tissue IHC) | |
| Regulation | Ubiquitous expression (UniProt) | |
| Isoform / epitope | 3 isoforms; verify epitope coverage (UniProt) |
The catalog antibody uses EDTA pH 8.0 retrieval (datasheet A00331-1). The published IHC protocols below cover parathyroid tumors and pancreatic neuroendocrine tumors (PMC10270278; PMC11106174; PMC5564808).
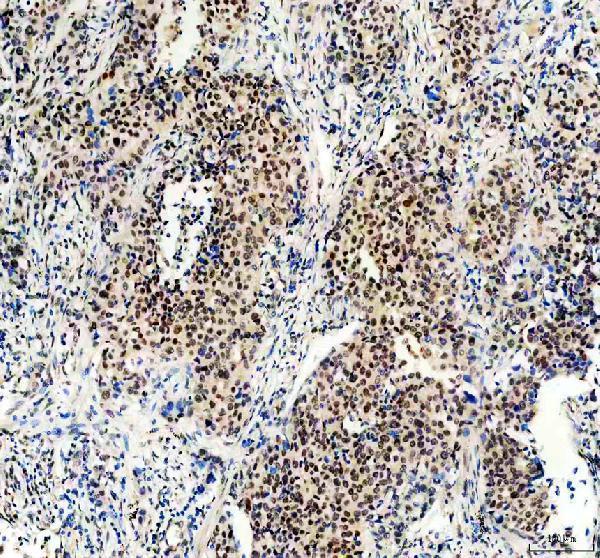
| Sample | Paraffin-embedded human lung cancer tissue; fixative not specified (datasheet A00331-1) |
| Fixation | Image fixative and duration unreported (datasheet A00331-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A00331-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A00331-1) |
| Primary antibody | Rabbit anti-MEN1, 2-5μg/ml (datasheet A00331-1) |
| Primary incubation | Overnight at 4 °C (datasheet A00331-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A00331-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | MEN1-positive staining in adipocytes of adipose tissue (HPA tissue IHC: Medium). HPA tissue profile: Nuclear expression in several tissues. No signal in the no-primary control. |
MEN1 is a nuclear protein without a transmembrane segment (UniProt O00255: subcellular location; topology). In paraffin-section IHC, expect nuclear staining in the cell types reported by HPA, including adipocytes, adrenal glandular cells and cerebral cortical glial cells (HPA tissue IHC). Use these as provisional references: HPA rates the tissue IHC pattern Uncertain because staining and RNA expression show low consistency, and it disregards observed cytoplasmic staining (HPA tissue IHC).
| Defined nuclear staining in adrenal glandular cells, adipocytes or cerebral cortical glial cells. | This matches MEN1's nuclear location (UniProt O00255: subcellular location) and HPA's Medium staining in these cells (HPA tissue IHC). Assess nuclei against the counterstain and nearby unstained structures (general IHC practice). A matching pattern supports interpretation, but HPA's tissue IHC reliability remains Uncertain (HPA tissue IHC). |
| Strong cytoplasmic staining with weak or absent nuclear staining. | Treat this as a compartment mismatch for paraffin-section IHC: MEN1 is nuclear (UniProt O00255: subcellular location), and HPA disregarded observed cytoplasmic tissue staining (HPA tissue IHC). Consider nonspecific antibody binding or detection background (general IHC practice). Cytosol reported by HPA ICC-IF is Uncertain and does not validate a cytoplasmic IHC result (HPA subcellular ICC-IF). |
| Prominent staining in bronchial respiratory epithelium while reference nuclei are unstained. | HPA reports bronchial respiratory epithelial cells as Not detected, so this pattern warrants a specificity check (HPA tissue IHC). Possible explanations include cross-reactivity or endogenous chromogenic detection activity (general IHC practice). HPA's uncertain tissue reliability means the bronchus result is a comparator, not an absolute exclusion rule (HPA tissue IHC). |
| A diffuse chromogen haze covers nuclei and surrounding tissue. | The haze prevents a confident nuclear call (general IHC practice; UniProt O00255: subcellular location). Review blocking, washes, primary-antibody concentration and the detection-only control as general IHC checks (general IHC practice). Do not score the haze as MEN1 expression solely because the section includes an HPA-listed positive cell type (HPA tissue IHC). |
| No nuclear signal in adrenal glandular cells or adipocytes. | Both cell types have Medium staining in HPA's tissue IHC observations (HPA tissue IHC). First check section quality, retrieval conditions, antibody and detection controls as general IHC practice. A negative result alone cannot establish absent MEN1: HPA rates its tissue IHC evidence Uncertain (HPA tissue IHC). |
| Nuclear location and topology (UniProt O00255) | Menin is nuclear, can concentrate in nuclear body-like structures, and has no transmembrane segment (UniProt O00255: subcellular location; topology). Score nuclear staining; do not infer a membrane pattern from this record. |
| Tissue and cell-type variation (HPA tissue IHC) | HPA reports Medium staining in selected adipocytes, glandular cells, glia and colon endothelial cells, but Not detected in selected bronchial epithelium and lung alveolar cells (HPA tissue IHC). Compare the specified cell types, rather than treating an entire organ as uniformly positive or negative. |
| Strength of IHC evidence (HPA tissue IHC; HPA antibodies) | The tissue profile is Uncertain; antibody HPA030342 is also rated Uncertain for IHC (HPA tissue IHC; HPA antibodies). Reproducible nuclear staining and appropriate controls increase confidence in an experiment, but these source ratings do not establish a validated positive tissue. |
| Isoforms and processing (UniProt O00255) | UniProt lists 3 isoforms and a Menin chain spanning residues 1–610, with no annotated signal peptide or propeptide (UniProt O00255: isoforms; processing). The payload gives no antibody epitope, so it cannot establish which isoforms an IHC reagent detects. |
| Does ICC-IF predict this IHC pattern? (HPA subcellular ICC-IF) | HPA supports nucleoplasmic ICC-IF staining and marks additional cytosol localization Uncertain (HPA subcellular ICC-IF). Use that result as context for nuclear localization; judge paraffin-section chromogenic staining against HPA tissue IHC, which disregards cytoplasmic staining (HPA tissue IHC). |
| Situation | Likely cause | Next action |
|---|---|---|
| No signal in an HPA-listed Medium cell type (HPA tissue IHC). | The workflow may have failed, or this specimen may differ from HPA's observation; the reference pattern is Uncertain (general IHC practice; HPA tissue IHC). | Check section integrity and run appropriate positive and detection controls; review retrieval, primary-antibody dilution and detection according to the assay instructions (general IHC practice). |
| Cytoplasmic color dominates the slide. | The pattern conflicts with the nuclear tissue-IHC expectation and may reflect nonspecific staining or background (UniProt O00255: subcellular location; HPA tissue IHC; general IHC practice). | Compare a detection-only control, review blocking and washes, and score nuclear staining separately; do not use uncertain ICC-IF cytosol localization to validate tissue IHC (general IHC practice; HPA subcellular ICC-IF). |
| Bronchial respiratory epithelium stains strongly. | HPA reports this cell type as Not detected; cross-reactivity or endogenous detection activity is possible (HPA tissue IHC; general IHC practice). | Inspect the detection-only control and an HPA-listed nuclear reference on the same run; interpret the mismatch cautiously because HPA tissue IHC reliability is Uncertain (general IHC practice; HPA tissue IHC). |
| Chromogen obscures nuclear boundaries. | High background or excessive signal can prevent compartment scoring (general IHC practice). | Review primary-antibody concentration, detection development, blocking and washes; use the counterstain to judge whether color is truly nuclear (general IHC practice). |
| Adrenal glandular cells and adipocytes give different results. | HPA lists Medium staining in both, but its tissue profile has low consistency with RNA data and is rated Uncertain (HPA tissue IHC). | Record the cell type, nuclear fraction and intensity in each section; check controls before treating one discordant specimen as proof of absent or present MEN1 (general IHC practice; HPA tissue IHC). |
| An IF image shows cytosolic signal alongside nuclear signal. | HPA supports nucleoplasmic ICC-IF localization but rates additional cytosol localization Uncertain (HPA subcellular ICC-IF). | Assess the nuclear signal and IF controls within the separate IF/ICC workflow; for this chromogenic IHC guide, retain the HPA tissue-IHC nuclear criterion (general IF practice; HPA tissue IHC). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. Cytoplasmic staining was viewed as observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Medium | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Caudate | Glial cells | Medium | Protein (IHC) | HPA → |
| Cerebral cortex | Glial cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bronchus | Respiratory epithelial cells | Not detected | Protein (IHC) | HPA → |
| Cervix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Endometrium | Cells in endometrial stroma | Not detected | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | Not detected | Protein (IHC) | HPA → |
Use nuclear localisation and matched controls to troubleshoot MEN1 staining in paraffin sections; assess IF/ICC separately.
A00331-1 has a real human paraffin-section IHC figure (catalog image caption); M00331 lists human IHC and IF/ICC applications, with no IF figure supplied (catalog applications; image payload).
A00331-1 will render with IHC staining shown in human lung cancer paraffin sections; its listed reactivity is human, mouse and rat (catalog image caption; catalog reactivity). M00331 will render with human IHC and IF/ICC listed, but no IHC or IF image caption was supplied (catalog applications; image payload).
Which to pick: For tissue IHC, choose A00331-1: its own caption documents EDTA pH 8.0 retrieval and staining at 2 μg/ml in a human lung cancer paraffin section; the fixative is unreported (catalog image caption). For IF/ICC, M00331 is the listed option, a rabbit monoclonal clone ACBA-13 with human reactivity and a 1:50 IF dilution; no IF image is supplied (catalog clone, reactivity, dilution and image payload). For mouse or rat IHC, choose A00331-1 based on its listed reactivity and IHC application; its supplied images show human tissue only (catalog reactivity and applications; catalog image captions).