MGME1 / Mitochondrial genome maintenance exonuclease 1 · IHC design guide

Design Immunohistochemistry for MGME1

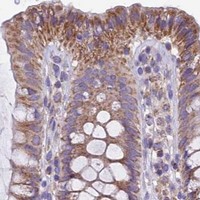
Plan paraffin-section MGME1 staining with the IHC-validated antibody at 2–5 μg/ml (datasheet A09360-1). Assess granular cytoplasmic staining, using colon glandular cells as a high-staining reference while accounting for medium consistency between staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MGME1 (IHC for MGME1): expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrion (UniProt), antibody A09360-1, validated IHC image, and IHC protocol steps
Printable MGME1 IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrion (UniProt), antibody A09360-1, controls and protocol steps. Open the full MGME1 IHC guide →

MGME1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrion (UniProt)
Staining pattern Most cell types show granular cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A09360-1)
Positive control ⓘ Colon+4 more · see all
Negative control ⓘ Adipose tissue+3 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A09360-1)
Caveat IHC and RNA show medium consistency; verification is pending (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope No isoforms annotated; one 1–344 chain (UniProt)
Section 1

Recommended MGME1 IHC & IF Protocols

The catalog antibody protocol is paired with one published MGME1 IHC protocol using formalin-fixed, paraffin-embedded tissue specimens (PMC11467307).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human thyroid cancer tissue; fixative not specified (datasheet A09360-1)
FixationImage fixative and duration unreported (datasheet A09360-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A09360-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A09360-1)
Primary antibodyRabbit anti-MGME1, 2-5 μg/ml (datasheet A09360-1)
Primary incubationOvernight at 4 °C (datasheet A09360-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A09360-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMGME1-positive staining in glandular cells of colon (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression with a granular pattern in most cell types. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval (datasheet A09360-1); compare citrate pH 6 retrieval used in the published protocol (PMC11467307).
Section 2

What Is the Expected MGME1 Staining Pattern?

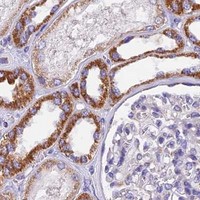
MGME1 localizes to mitochondria (UniProt Q9BQP7; HPA: supported ICC-IF). In paraffin sections, expect granular cytoplasmic staining in many cell types, including colon glandular cells and kidney tubule cells with High HPA staining (HPA: tissue IHC). HPA rates its tissue IHC profile Approved, with medium consistency between staining and RNA data and external verification pending (HPA: tissue IHC). No transmembrane segment is annotated (UniProt Q9BQP7 topology).

What am I looking at on my slide?
Granular cytoplasmic stain in glandular or tubular cells.This fits the reported tissue pattern and mitochondrial localization (HPA: tissue IHC; HPA: supported ICC-IF; UniProt Q9BQP7). Assess granules within identifiable cells against the counterstain; a uniformly colored cell or section is less persuasive as a compartment-specific result (general IHC practice).
Predominantly nuclear, membranous, or extracellular stain.Treat this as a compartment mismatch: MGME1 is mitochondrial, and HPA describes granular cytoplasmic tissue staining (UniProt Q9BQP7; HPA: tissue IHC). Review morphology and a control slide before calling it specific; the compartment mismatch alone does not identify the technical cause (general IHC practice).
Strong stain in adipocytes, follicle cells, smooth muscle cells, or chondrocytes.HPA reports MGME1 as Not detected in these sampled cell types, so strong staining warrants scrutiny for cross-reactivity or endogenous detection activity (HPA: tissue IHC; general IHC practice). A Not detected reference result is a comparison point, not proof that every cell in those tissues must be blank (HPA: tissue IHC).
Diffuse color over cells, stroma, and empty spaces.This does not match the granular cytoplasmic profile (HPA: tissue IHC). Compare a section processed without primary antibody and inspect wash and blocking steps to assess nonspecific deposition or endogenous detection activity; these are general IHC checks, not documented MGME1-specific effects (general IHC practice).
No stain in morphologically intact colon glands or kidney tubules.These are useful positive references because HPA reports High staining in colon glandular cells and kidney tubule cells (HPA: tissue IHC). Check the control and detection workflow before interpreting absence in a study specimen; HPA's Approved profile has only medium RNA–staining consistency and awaits external verification (HPA: tissue IHC).
💡Expected MGME1 appearanceCall a positive result when identifiable glandular or tubular cells show clear granular cytoplasmic staining, potentially High in colon glands or kidney tubules; predominant nuclear staining or diffuse section-wide color is suspect (HPA: tissue IHC; UniProt Q9BQP7; general IHC practice).
How each factor affects the staining
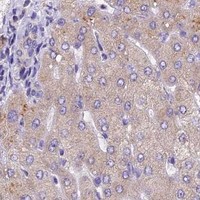
Compartment and tissue context (UniProt Q9BQP7; HPA: tissue IHC).Mitochondrial localization supports a granular cytoplasmic readout; HPA reports Low staining in hepatocytes and lung macrophages, so compare like cell types when judging intensity (UniProt Q9BQP7; HPA: tissue IHC).
Strength of the reference evidence (HPA: tissue IHC; HPA: antibody validation).The tissue profile is Approved, with medium RNA–staining consistency and external verification pending; HPA040913 is Approved for IHC, which supports use of the pattern as a reference without making every discrepant result an artefact (HPA: tissue IHC; HPA: antibody validation).
Detection background (general IHC practice).Endogenous enzyme activity or nonspecific detection can create chromogenic color outside the expected cells; a no-primary control helps distinguish that background from antibody-dependent signal (general IHC practice; HPA: tissue IHC pattern).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The positive-reference section is blank.Colon glandular cells and kidney tubules are reported High, so a blank reference raises concern about the staining run, while biological or sampling differences remain possible (HPA: tissue IHC; general IHC practice).Confirm the expected cell type is present, then review antibody dilution, retrieval conditions, detection reagents, and run controls using the established IHC workflow; these are general checks, not MGME1-specific retrieval claims (general IHC practice).
Color is diffuse across the section.Diffuse color conflicts with HPA's granular cytoplasmic profile and may reflect nonspecific deposition or endogenous detection activity (HPA: tissue IHC; general IHC practice).Compare the no-primary control, inspect reagent background, and review blocking and washes before scoring cellular stain (general IHC practice).
Nuclei dominate the signal.Nuclear dominance conflicts with mitochondrial localization and the reported cytoplasmic pattern (UniProt Q9BQP7; HPA: tissue IHC).Check cell boundaries against the counterstain and compare a positive-reference section; withhold a specific MGME1 call if the compartment mismatch persists (general IHC practice; HPA: tissue IHC).
A reported Not detected cell type stains strongly.The result differs from HPA observations for adipocytes, follicle cells, smooth muscle cells, or chondrocytes; cross-reactivity or endogenous activity is possible (HPA: tissue IHC; general IHC practice).Verify the cell identity and compare no-primary and positive-reference sections. Treat the HPA result as a reference observation rather than an absolute exclusion (HPA: tissue IHC; general IHC practice).
Only weak signal appears in a study tissue.Intensity varies by cell type: HPA reports Low staining in hepatocytes, lung macrophages, and several glandular populations (HPA: tissue IHC).Score the identified cell population against an appropriate reference and background control; do not interpret a weak result solely by comparison with High-staining colon glands (HPA: tissue IHC; general IHC practice).
Q: What should IF/ICC show?A: Mitochondrial localization is supported in HPA ICC-IF images; this agrees with UniProt localization (HPA: supported ICC-IF; UniProt Q9BQP7).Use the separate IF/ICC guide for that application. Here, judge paraffin-section results against the HPA granular cytoplasmic IHC profile (HPA: tissue IHC).

Sample controls for MGME1 IHC & IF

🧪Run colon first and score its glandular cells for MGME1 staining (HPA: colon glandular cells High). Use adipose tissue as the negative tissue, with adipocytes expected to lack detectable staining (HPA: adipocytes Not detected); on the colon slide, use adjacent nonglandular areas to assess background, without treating them as established MGME1-negative cells (HPA: no colon internal negative listed).
Positive control tissue: Colon (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MGME1 in A-431, U-251MG, U2OS, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a rabbit IgG isotype control matched to the primary antibody’s clonality; and an MGME1 knockout sample or a peptide-block control if the immunizing peptide is available (hero caption: rabbit anti-MGME1). Quench endogenous peroxidase and check for background DAB staining in colon tissue before scoring (hero caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A09360-1 tissue-IHC caption does not report a fixative (hero caption: fixative not stated). The paraffin-section example used heat retrieval in EDTA at pH 8.0, but it does not establish whether retrieval is required for every specimen (hero caption: EDTA retrieval, pH 8.0). There is no matched evidence that frozen sections or IF are easier; IF could assess mitochondrial localization with a mitochondrial marker (HPA: mitochondria supported), while colon gland contents and endogenous peroxidase warrant background checks in chromogenic IHC (standard IHC practice).

HPA tissue IHC evidence for MGME1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Esophagus Squamous epithelial cells High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →
Rectum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Ovary Follicle cells Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Soft tissue Chondrocytes Not detected Protein (IHC) HPA →
Section 3

Advanced MGME1 IHC Tips

Troubleshoot chromogenic MGME1 IHC in paraffin sections using the catalog antibody’s tissue image and the reported localisation evidence.

What retrieval should I try first if MGME1 staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A09360-1). The selected paraffin-section image used that retrieval, followed by 2 μg/ml catalog antibody overnight at 4°C (datasheet A09360-1). If staining remains weak, compare a second retrieval condition on adjacent sections while holding antibody concentration and DAB development constant (standard IHC practice). Record heating and cooling times for each run, because retrieval intensity can change staining and tissue preservation (standard IHC practice). Judge improvement by a granular cytoplasmic pattern in appropriate cells, rather than a general rise in brown signal (HPA: tissue IHC profile; standard IHC practice).
How should I troubleshoot a possible fixation effect on MGME1 staining?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative (datasheet A09360-1). Record each specimen’s fixative, fixation interval and processing history before comparing MGME1 intensity across cases (standard IHC practice). For a controlled comparison, stain adjacent sections together using EDTA retrieval at pH 8.0 and 2 μg/ml catalog antibody (datasheet A09360-1; standard IHC practice). If one processing group stains poorly, assess tissue morphology and a suitable control before attributing the difference to MGME1 abundance (standard IHC practice). Neither its mitochondrial localisation nor its annotated phosphoserine at residue 343 establishes a fixation effect (UniProt Q9BQP7).
What staining pattern should count as correctly localised MGME1 in IHC?
Look for cytoplasmic staining with a granular pattern in well-preserved cells (HPA: tissue IHC profile). That expectation is consistent with MGME1’s mitochondrial localisation, although chromogenic IHC alone cannot prove organelle-level colocalisation (UniProt Q9BQP7; HPA: subcellular localisation; standard IHC practice). Compare the pattern with reported high staining in kidney tubular cells or colon glandular cells on a suitable control section (HPA: kidney and colon tissue IHC). Treat exclusively nuclear or diffuse extracellular DAB as a specificity concern and inspect a no-primary control (standard IHC practice). MGME1 has no annotated transmembrane segment, so a crisp plasma-membrane rim would need independent validation (UniProt Q9BQP7).
Could an isoform or hidden epitope explain inconsistent paraffin-section staining?
The supplied record lists 0 isoforms and one annotated chain spanning residues 1–344 (UniProt Q9BQP7). It does not map the catalog antibody’s epitope, so epitope accessibility in processed sections remains uncertain (datasheet A09360-1; UniProt Q9BQP7). Start with its documented EDTA retrieval at pH 8.0, then compare adjacent sections under matched staining conditions if signal varies (datasheet A09360-1; standard IHC practice). MGME1 has no annotated transmembrane segment or glycosylation sites, while phosphoserine is annotated at residue 343 (UniProt Q9BQP7). Those annotations do not establish what this antibody recognises; require appropriate tissue and no-primary controls before assigning an epitope-specific cause (standard IHC practice).
How can IF help check an ambiguous MGME1 IHC pattern?
Use IF as a separate localisation check when paraffin-section DAB staining lacks a convincing granular cytoplasmic pattern (HPA: tissue IHC profile; standard IF practice). Multiplex MGME1 with a validated marker for the expected cell type, and assess mitochondrial overlap separately from cell identity (HPA: subcellular localisation; standard IF practice). Choose a fluorophore channel with low measured tissue autofluorescence, then inspect single-channel images and appropriate controls before interpreting overlap (standard IF practice). Because MGME1 lacks an annotated transmembrane segment and the antibody epitope is unmapped, its membrane-facing accessibility cannot be assigned from the record (UniProt Q9BQP7; datasheet A09360-1). Optimise permeabilisation for epitope access empirically in IF rather than transferring the paraffin-section retrieval condition (standard IF practice).
How do I separate MGME1 staining from diffuse DAB background?
First compare the stained section with a no-primary control and inspect whether DAB follows tissue edges, folds or damaged areas (standard IHC practice). The documented tissue image used 10% goat-serum blocking, 2 μg/ml primary antibody overnight at 4°C, and peroxidase-based DAB detection (datasheet A09360-1). If background is widespread, verify the peroxidase block, washing, secondary-only signal and DAB development time in matched sections (standard IHC practice). Assess the expected granular cytoplasmic pattern separately from uniform haze or deposits outside cells (HPA: tissue IHC profile; standard IHC practice). Titrate detection conditions while preserving a positive tissue control, so loss of background is not mistaken for assay success (standard IHC practice).
How should I score MGME1 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and exclusion rules before scoring, and keep retrieval, detection and imaging conditions matched across sections (standard IHC practice). For chromogenic MGME1 IHC, report an H-score from staining intensity and percentage of positive cells, or report percentage positive with intensity as separate fields (standard IHC practice). If counting positive cells per mm², normalise to the area of viable, evaluable tissue and report the number of cells assessed (standard IHC practice). Score granular cytoplasmic staining within the selected cells rather than all brown pixels, using the reported pattern as a reference (HPA: tissue IHC profile). Record control performance and batch with each result because the HPA tissue assessment is Approved with medium staining-to-RNA consistency (HPA: reliability description).
When should a strong MGME1 signal be considered artefactual?
A credible positive signal should be cellular and granular within cytoplasm, consistent with reported tissue staining and mitochondrial localisation (HPA: tissue IHC profile; HPA: subcellular localisation). Check cell identity: high staining is reported in kidney tubular cells, whereas smooth-muscle cells were reported as not detected (HPA: kidney and smooth-muscle tissue IHC). Treat signal restricted to cut edges, necrotic areas or extracellular deposits as suspect, and compare it with a no-primary control (standard IHC practice). Residual endogenous peroxidase can produce DAB signal, so check the peroxidase block when staining is broad or compartmentally implausible (standard IHC practice). Interpret differences cautiously because the HPA tissue assessment has medium consistency with RNA expression and awaits external verification (HPA: reliability description).
Boster reagents

Best MGME1 / Mitochondrial genome maintenance exonuclease 1 IHC Antibodies

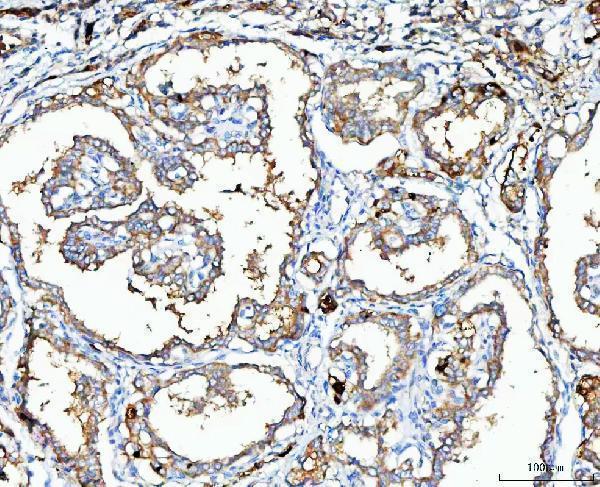
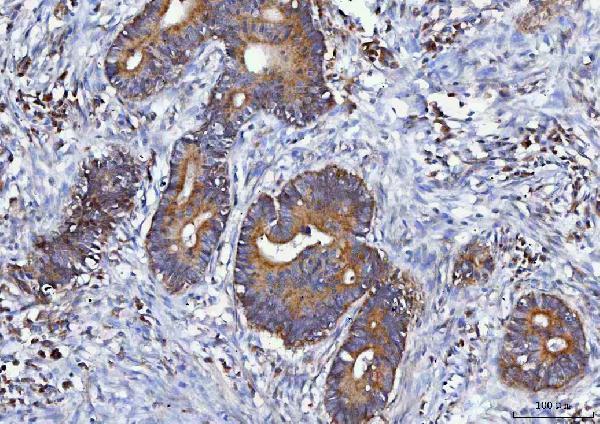
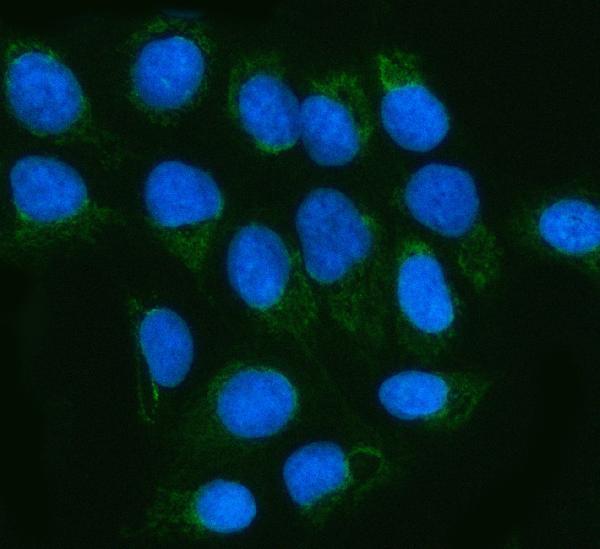
A09360-1 has IHC images from human paraffin sections of thyroid cancer, colorectal adenocarcinoma and testicular germ cell tumors, plus IF data in U2OS cells (catalog image captions).

Real IHC data IHC analysis of MGME1 using anti-MGME1 antibody (A09360-1). MGME1 was detected in a paraffin-embedded section of human thyroid cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-MGME1 Antibody (A09360-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-MGME1 Antibody ®
Cat # A09360-1

A09360-1 was tested for human IHC on paraffin sections of thyroid cancer, colorectal adenocarcinoma and testicular germ cell tumors (A09360-1 IHC captions). The same SKU was tested for IF/ICC in U2OS cells (A09360-1 IF caption; catalog applications).

Which to pick: Choose A09360-1 for human paraffin-section IHC; its own caption documents EDTA pH 8 retrieval and 2 μg/ml primary antibody, but does not report the fixative (A09360-1 IHC caption). For IF/ICC, the same SKU has a U2OS cell image at 5 μg/ml; clonality is unreported (A09360-1 IF caption; catalog clone field). No cross-species choice is supported here because the catalog lists Human as the only reactive species (catalog: A09360-1 reactivity).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9BQP7 (MGME1_HUMAN, Mitochondrial genome maintenance exonuclease 1).
  2. Human Protein Atlas. MGME1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. MGME1 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. MGME1 antibody validation summary (1 antibodies).
  5. Integrative multi-omics analysis unveils the connection between transcriptomic characteristics associated with mitochondria and the tumor immune microenvironment in lower-grade gliomas. Scientific reports 2024 — PMC11467307.
  6. Loss-of-function mutations in MGME1 impair mtDNA replication and cause multisystemic mitochondrial disease. Nature genetics 2013 — PMC3678843.
  7. PubMed PMID:14702039 — UniProt-cited evidence.
  8. PubMed PMID:11780052 — UniProt-cited evidence.
  9. PubMed PMID:15489334 — UniProt-cited evidence.