MINPP1 / Multiple inositol polyphosphate phosphatase 1 · IHC design guide

Design Immunohistochemistry for MINPP1

Plan chromogenic MINPP1 IHC on paraffin sections using conditions documented for the catalog antibody (datasheet A08462-3). Assess cytoplasmic staining against the tissue profile and use matched controls to judge background (HPA tissue IHC; standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MINPP1 (IHC for MINPP1): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); ER lumen (UniProt), antibody A08462-3, validated IHC image, and IHC protocol steps
Printable MINPP1 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); ER lumen (UniProt), antibody A08462-3, controls and protocol steps. Open the full MINPP1 IHC guide →

MINPP1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); ER lumen (UniProt)
Staining pattern Cytoplasmic staining in several tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A08462-3)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat A secreted variant may shift protein away from its RNA source (HPA tissue IHC)
Regulation Low tissue specificity (HPA tissue RNA)
Isoform / epitope 4 isoforms; map the epitope to mature residues 31–487 (UniProt)
Section 1

Recommended MINPP1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with 3 published MINPP1 IHC protocols (PMC7145417; PMC12648906; PMC7779247).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat kidney tissue; fixative not specified (datasheet A08462-3)
FixationImage fixative and duration unreported (datasheet A08462-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A08462-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A08462-3)
Primary antibodyRabbit anti-MINPP1, 2-5 μg/ml (datasheet A08462-3)
Primary incubationOvernight at 4 °C (datasheet A08462-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A08462-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMINPP1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in several tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet: A08462-3); compare Tris/EDTA at pH 9.0 if needed (PMC7145417).
Section 2

What Is the Expected MINPP1 Staining Pattern?

MINPP1 is annotated in the endoplasmic reticulum lumen and as secreted, with no transmembrane segment (UniProt Q9UNW1 topology). In paraffin section IHC, expect cytoplasmic staining in several tissues, including glandular cells of the appendix and respiratory epithelial cells of the bronchus (HPA: tissue IHC, Medium). HPA rates the tissue profile Approved, with medium consistency between antibody staining and RNA expression (HPA: tissue IHC reliability).

What am I looking at on my slide?
Cytoplasmic chromogenic signal in appendix glandular cells or bronchial respiratory epithelial cells (HPA: Medium in each).This matches the reported tissue and cell pattern (HPA: tissue IHC). Score the named cells separately from neighboring cells and record intensity; a cytoplasmic deposit cannot resolve the ER lumen by light microscopy (UniProt Q9UNW1: ER lumen; standard IHC interpretation).
Predominantly nuclear staining, with little cytoplasmic signal in a reported positive cell population (HPA: cytoplasmic profile).The compartment conflicts with the reported IHC pattern (HPA: cytoplasmic expression). Treat it as suspect staining; compare with a no-primary control and another reported positive tissue before assigning it to MINPP1 (standard IHC practice).
Prominent staining in adipocytes or skeletal myocytes (HPA: Not detected in these cell populations).This is discordant with the sampled HPA observations and may reflect cross-reactivity or endogenous chromogenic activity (HPA: tissue IHC; standard IHC interpretation). Check staining in the no-primary control; 'Not detected' in HPA does not prove absence in every specimen.
Color spread across stroma, tissue edges, or many unrelated cell types without a clear cellular pattern.Diffuse deposit is difficult to score as MINPP1 because HPA describes cytoplasmic expression in several tissues (HPA: tissue IHC). Review no-primary and background controls, washing, and detection conditions before interpreting a weak cellular signal (standard IHC practice).
No signal in appendix glandular cells or bronchial respiratory epithelial cells (HPA: Medium in each).The result misses a reported positive pattern, but one negative section cannot identify the cause (HPA: tissue IHC; standard IHC interpretation). Check tissue preservation, retrieval and detection controls, then repeat with a validated positive section; HPA reports only medium staining–RNA consistency.
💡Expected MINPP1 appearanceA credible positive is Medium cytoplasmic staining in reported cell populations such as appendix glandular cells or bronchial respiratory epithelial cells (HPA: tissue IHC); dominant nuclear staining or broad acellular color is suspect (HPA: cytoplasmic profile; standard IHC interpretation).
How each factor affects the staining
Cellular compartmentER-lumen and secreted annotations support intracellular cytoplasmic staining but do not predict a resolvable ER pattern in chromogenic sections (UniProt Q9UNW1; standard IHC interpretation). Erythrocyte plasma-membrane association is separately noted (UniProt Q9UNW1).
Processing and secretionMINPP1 has a signal peptide at residues 1–30 and a mature chain at 31–487 (UniProt Q9UNW1). At least one variant is secreted, so tissue RNA and protein locations may differ (HPA: reliability description); extracellular color alone is not a definitive positive.
Variants and antibody evidenceFour isoforms are listed (UniProt Q9UNW1), but the supplied record gives no antibody epitope or variant coverage. HPA026859 is Approved for IHC, with no Enhanced designation supplied (HPA: antibody validation); avoid assuming all variants stain equally.
Tissue selectionHPA reports Medium staining in several named cell populations and 'Not detected' in others (HPA: tissue IHC). UniProt describes highest expression in kidney, liver, cerebellum and placenta, while HPA finds cerebellar granular-layer cells Not detected; match controls to the specific cell population.
IF/ICC evidenceHPA lists MINPP1 as secreted but provides no main subcellular location or ICC-IF image cell lines (HPA: subcellular record). These data cannot confirm an IF compartment pattern; assess IF/ICC on its separate guide page.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Reported positive cells show no or weak chromogenic signal (HPA: Medium in appendix glandular cells).Possible section, retrieval, antibody-incubation, or detection failure (standard IHC practice); no MINPP1-specific fixation or retrieval sensitivity is supplied.Verify the positive section and detection controls, then check the documented IHC conditions and repeat the run (standard IHC practice). Do not infer a target-specific fixation effect from this result.
Nuclear staining dominates the section (HPA: cytoplasmic tissue profile).A nonspecific or detection-related signal is possible (standard IHC interpretation); UniProt places MINPP1 in the ER lumen and also annotates secretion (UniProt Q9UNW1).Compare no-primary and reported positive-tissue controls, and score nuclear and cytoplasmic deposits separately (standard IHC practice). Treat nuclear-only staining as discordant.
Adipocytes or skeletal myocytes stain strongly (HPA: Not detected in those populations).Cross-reactivity or endogenous detection activity may produce an unexpected signal (standard IHC interpretation); HPA's negative observations are cell-specific.Inspect a no-primary control and the tissue's morphology; investigate endogenous chromogenic activity using appropriate detection controls (standard IHC practice).
Diffuse color obscures cell boundaries and cytoplasmic scoring.Background from detection conditions or insufficient washing is possible (standard IHC practice); HPA reports a cellular cytoplasmic pattern (HPA: tissue IHC).Review no-primary staining, blocking, wash steps and chromogen development; rescore only when the cellular deposit is distinguishable (standard IHC practice).
Cerebellar granular-layer cells are negative despite the UniProt tissue-expression summary.UniProt lists cerebellum among tissues with highest expression, while HPA reports these cells Not detected by IHC (UniProt Q9UNW1; HPA: tissue IHC).Use an HPA-reported Medium-staining cell population to check the IHC run; report the cerebellar finding by cell type and assay (HPA: tissue IHC; standard IHC interpretation).
Can an IF/ICC image establish the expected MINPP1 compartment?The supplied HPA subcellular record has no ICC-IF image cell lines or main location (HPA: subcellular record).Use this page's cytoplasmic tissue-IHC pattern for section interpretation (HPA: tissue IHC); consult the separate IF/ICC guide for that application.

Sample controls for MINPP1 IHC & IF

🧪Run breast first and look for medium MINPP1 staining in glandular cells (HPA: breast glandular cells, Medium). Use adipose tissue as the negative tissue (HPA: adipocytes, Not detected); adipocytes within the breast section, if present, should show little or no specific staining by comparison (HPA: adipocytes, Not detected).
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for MINPP1; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control, a rabbit IgG isotype control matched to the primary antibody where possible (selected-SKU caption: rabbit anti-MINPP1), and MINPP1 knockout tissue as a biological negative. Check for endogenous peroxidase background before interpreting DAB staining in breast tissue (standard chromogenic IHC practice).
⚠️Feasibility: The selected-SKU paraffin-section caption reports heat retrieval in EDTA, pH 8.0, for rat kidney; it does not report a fixative, a target-specific fixation window, or the effect of fixation on staining (selected-SKU tissue-IHC caption). Use that retrieval condition as a starting point for IHC optimization; its necessity in breast tissue is unreported (selected-SKU tissue-IHC caption; HPA: breast glandular cells, Medium). Frozen-section or IF/ICC staining cannot be judged easier from the supplied evidence, and breast adipose areas may contribute autofluorescence if IF is tested (HPA: ICC-IF image cell lines, none; standard IF practice).

HPA tissue IHC evidence for MINPP1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Epididymis Glandular cells Not detected Protein (IHC) HPA →
Fallopian tube Glandular cells Not detected Protein (IHC) HPA →
Ovary Follicle cells Not detected Protein (IHC) HPA →
Section 3

Advanced MINPP1 IHC Tips

Troubleshoot MINPP1 staining in paraffin sections using the catalog antibody’s documented conditions, tissue patterns, and subcellular annotations.

Which retrieval conditions should I use for MINPP1 paraffin-section IHC?
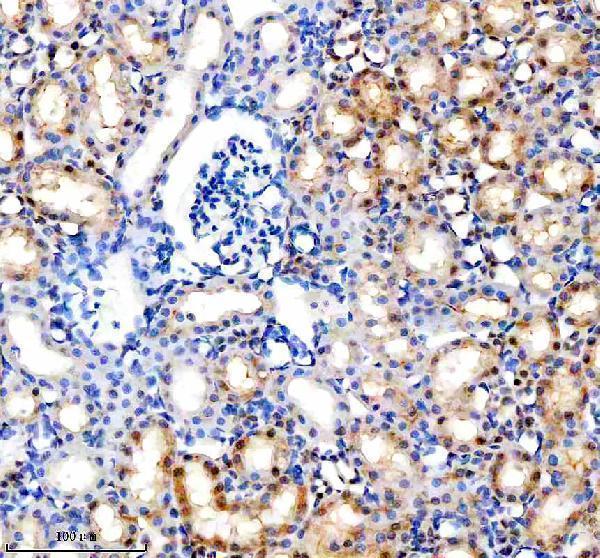
Use heat-mediated EDTA retrieval at pH 8.0 for MINPP1 paraffin-section IHC (datasheet A08462-3). The selected rat kidney image used this retrieval, 2 μg/ml primary overnight at 4°C, and DAB development (datasheet A08462-3). If staining is weak, check heating consistency, then titrate retrieval duration on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Excessive heating can damage morphology and produce apparent edge staining, so evaluate signal only where cellular detail remains intact (standard IHC practice). Record heating time and temperature; the caption supplies the buffer and pH but neither heating setting (datasheet A08462-3).
How should fixation be controlled when MINPP1 staining varies between paraffin blocks?
Target-specific sensitivity to fixation is unknown: the selected paraffin-section caption does not state a fixative (datasheet A08462-3). Record fixative, immersion delay, duration, and tissue thickness for every block, and compare matched regions processed together (standard IHC practice). Keep EDTA retrieval at pH 8.0 and primary concentration at 2 μg/ml while evaluating variation between blocks (datasheet A08462-3; standard IHC practice). Assess tissue preservation and an internal reference section before changing retrieval or antibody dose (standard IHC practice). Neither HPA tissue patterns nor ER luminal location establish how fixation changes epitope access for this antibody (HPA tissue IHC; UniProt Q9UNW1 localisation).
Why does MINPP1 appear cytoplasmic rather than nuclear in tissue sections?
Expect cytoplasmic staining in several tissues because that is the reported tissue IHC pattern (HPA tissue IHC). MINPP1 is annotated in the ER lumen, with secreted and cell-membrane locations also listed; erythrocyte plasma-membrane association is specifically noted (UniProt Q9UNW1 localisation). Score cytoplasmic signal in morphologically intact cells, and compare it with stromal and extracellular staining on the same section (standard IHC practice; UniProt Q9UNW1 localisation). Do not assign a secreted or membrane pool from DAB distribution alone; check compartment assignments with an appropriate marker or independent assay, particularly when staining crosses cell boundaries (standard IHC practice).
Could MINPP1 isoforms or processing explain different staining patterns?
MINPP1 has 4 annotated isoforms; its 487-residue precursor has a 1–30 signal peptide and a 31–487 mature chain (UniProt Q9UNW1 processing/isoforms). Glycosylation is annotated at residues 242 and 481, but the catalog antibody’s exact epitope is unspecified (UniProt Q9UNW1 glycosylation; datasheet A08462-3). Check its immunogen or epitope map before attributing a negative stain to an isoform, particularly if variants differ in the recognized region (standard IHC practice; UniProt Q9UNW1 isoforms). Compare adjacent sections under identical retrieval and detection conditions, then use independent evidence to test any proposed isoform-specific interpretation (standard IHC practice).
How can MINPP1 IF help check the chromogenic cell pattern?
Pair MINPP1 with a marker of the expected cell type, such as a glandular-cell marker in HPA-positive glandular regions (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores and place the weaker signal in a channel with low tissue autofluorescence; inspect single-stain and unstained controls (standard IF practice). MINPP1 is annotated in the ER lumen without a transmembrane segment, so permeabilize fixed cells when testing an intracellular luminal epitope; this antibody’s epitope is unspecified (UniProt Q9UNW1 topology/localisation; datasheet A08462-3). Compare cellular distribution with the paraffin-section DAB result and document the IF conditions separately (datasheet A08462-3; standard IF practice).
How should high diffuse DAB background be reduced?
Start with the documented 10% goat-serum block, 2 μg/ml primary overnight at 4°C, and peroxidase-conjugated secondary for 30 minutes at 37°C (datasheet A08462-3). Block endogenous peroxidase before DAB, include a no-primary section, and check whether the secondary alone stains the same structures (standard IHC practice). If background persists, titrate primary concentration and secondary exposure separately while keeping retrieval and DAB development consistent across comparison sections (standard IHC practice). Interpret brown material at damaged edges or in extracellular spaces cautiously, given MINPP1’s secreted annotation and possible endogenous pigment or enzyme activity (UniProt Q9UNW1 localisation; standard IHC practice).
How should MINPP1 chromogenic signal be quantified across tissues? ⚠ ANSWER MARKED FOR VERIFICATION
Define compartments and cell populations before scoring, because HPA reports cytoplasmic expression in several tissues and different staining levels across cell types (HPA tissue IHC). Score percentage of positive cells and intensity using a prespecified H-score, or report positive-cell density per mm² when segmentation is reliable (standard IHC practice). Normalize counts to viable tissue area and eligible cells within each annotated compartment, excluding necrosis, folds, and section edges (standard IHC practice). Keep retrieval, DAB development, illumination, and threshold settings matched; report the scorer, region selection, and negative-control threshold alongside results (standard IHC practice).
How can a true MINPP1 positive be distinguished from artefact?
Favor reproducible cytoplasmic staining in intact cells, consistent with HPA tissue IHC and MINPP1’s ER luminal annotation (HPA tissue IHC; UniProt Q9UNW1 localisation). Use rat kidney as a reference for the catalog antibody’s documented tissue image, and verify specificity independently (datasheet A08462-3; standard IHC practice). Flag isolated nuclear-only staining, edge enhancement, necrotic regions, and signal persisting without primary antibody as possible artefacts (UniProt Q9UNW1 localisation; standard IHC practice). Interpret cerebellar granular-layer negatives cautiously: HPA reports no detection there, while UniProt lists cerebellum among higher-expression tissues; secreted variants can complicate RNA–protein concordance (HPA tissue IHC; UniProt Q9UNW1 tissue specificity).
Boster reagents

Best MINPP1 / Multiple inositol polyphosphate phosphatase 1 IHC Antibodies

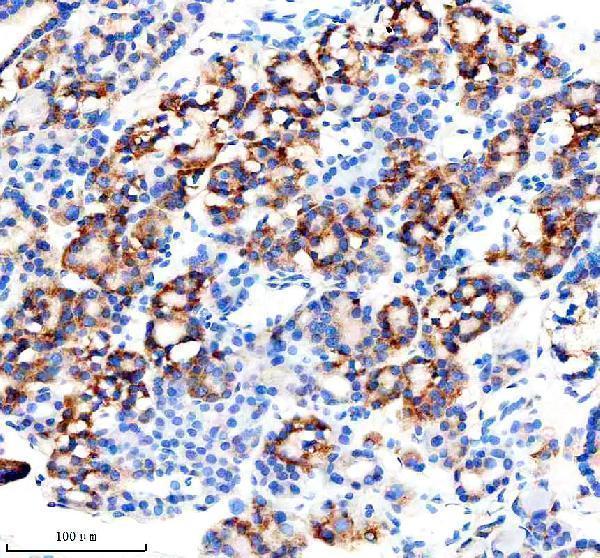
A08462-3 has real IHC images from paraffin sections of rat kidney and human thyroid cancer (catalog image captions). No IF/ICC data are listed (catalog applications; IF image list).

Real IHC data IHC analysis of MINPP1 using anti-MINPP1 antibody (A08462-3). MINPP1 was detected in a paraffin-embedded section of rat kidney tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-MINPP1 Antibody (A08462-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-MINPP1 Antibody ®
Cat # A08462-3

A08462-3 is listed for IHC and for human, mouse and rat reactivity (catalog applications; reactivity). Its IHC images show paraffin sections of rat kidney and human thyroid cancer stained with 2 μg/ml primary antibody (A08462-3 IHC image captions).

Which to pick: Choose A08462-3 for paraffin-section IHC: its images document EDTA retrieval at pH 8.0 in rat kidney and human thyroid cancer; the fixative is unreported (A08462-3 IHC image captions). For work across species, A08462-3 lists human, mouse and rat reactivity, but its IHC-specific listing covers human and rat, and its IHC images show those two species (catalog reactivity; dilution listing; A08462-3 IHC image captions). There is no supported IF/ICC pick because A08462-3 has neither IF/ICC in its application list nor an IF image (catalog applications; IF image list).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9UNW1 (MINP1_HUMAN, Multiple inositol polyphosphate phosphatase 1).
  2. Human Protein Atlas. MINPP1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. MINPP1 subcellular location (ICC-IF): Secreted.
  4. Human Protein Atlas. MINPP1 antibody validation summary (1 antibodies).
  5. MINPP1 promotes ferroptosis in HBV-related hepatocellular carcinoma by regulating CTSB K33-linked deubiquitination via ZRANB1. Biology direct 2025 — PMC12487252.
  6. High-phytate/low-calcium diet is a risk factor for crystal nephropathies, renal phosphate wasting, and bone loss. eLife 2020 — PMC7145417.
  7. Activation of WDHD1 by DNA demethylases promotes MINPP1 transcription and glycolysis in lung adenocarcinoma progression. Respiratory research 2025 — PMC12648906.
  8. Hepatitis B virus P protein initiates glycolytic bypass in HBV-related hepatocellular carcinoma via a FOXO3/miRNA-30b-5p/MINPP1 axis. Journal of experimental & clinical cancer research : CR 2021 — PMC7779247.
  9. PubMed PMID:9923613 — UniProt-cited evidence.
  10. PubMed PMID:10087200 — UniProt-cited evidence.
  11. PubMed PMID:11230166 — UniProt-cited evidence.