This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan MLIP staining in paraffin sections using heart and skeletal muscle as positive tissues (HPA tissue IHC). The guide covers fixation consistency, antibody setup and interpretation of predominantly cytoplasmic muscle staining (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Muscle cytoplasm (HPA tissue IHC); nuclear sites (UniProt) | |
| Staining pattern | High cytoplasmic staining in cardiomyocytes and skeletal myocytes (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Heart muscle+2 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | IHC/RNA concordance is medium; verify with controls (HPA tissue IHC) | |
| Regulation | Heart and skeletal muscle enriched (UniProt) | |
| Isoform / epitope | 4 isoforms; confirm antibody epitope coverage (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by 1 published MLIP staining protocol (PMC3103349).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A12261); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-MLIP, 5 μg/mL (datasheet A12261) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
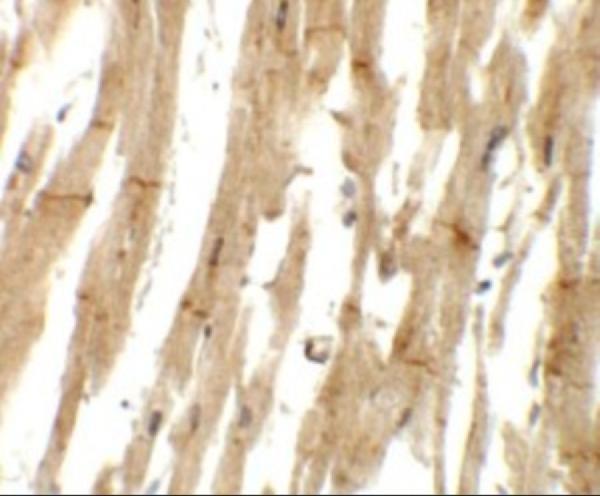
| Expected result | MLIP-positive staining in cardiomyocytes of heart muscle (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression mainly in skeletal and heart muscle. No signal in the no-primary control. |
In paraffin-section IHC, expect mainly cytoplasmic MLIP staining in cardiomyocytes and skeletal myocytes, with weaker staining possible in smooth muscle cells (HPA tissue IHC: High, High and Medium, respectively). MLIP is also annotated at the nucleus, nuclear envelope and sarcolemma; it has no transmembrane segment (UniProt Q5VWP3). HPA rates the tissue IHC profile Approved, with medium consistency between staining and RNA data and external verification pending (HPA tissue IHC).
| Strong cytoplasmic staining in cardiomyocytes or skeletal myocytes, with weaker staining in smooth muscle cells. | This matches the reported IHC distribution: High in heart and skeletal muscle cells, Medium in smooth muscle cells, and mainly cytoplasmic overall (HPA tissue IHC). Assess intensity in the identified cells rather than averaging the whole section (general IHC practice). |
| Staining is confined to extracellular material, a lumen or granular deposits, without a convincing cellular pattern. | These locations do not match the reported predominantly cytoplasmic muscle-cell pattern (HPA tissue IHC). Inspect the section and detection controls for deposits or background before assigning the signal to MLIP (general IHC practice). Nuclear or membrane-associated signal alone should not be dismissed: those locations have separate support (UniProt Q5VWP3; HPA subcellular ICC-IF). |
| Strong staining appears in adipocytes or other cells reported as undetected, while muscle cells show little signal. | Adipocytes are reported as Not detected in adipose tissue and breast (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity; compare with an appropriate no-primary control and known-positive muscle section (general IHC practice; HPA tissue IHC). A low-level signal elsewhere is less decisive because several epithelial and neuronal cell types are reported Low (HPA tissue IHC). |
| Diffuse chromogen obscures cell boundaries or covers both expected positive and negative areas. | The distribution cannot be scored reliably against the reported muscle-cell pattern (HPA tissue IHC). Check the no-primary control and review blocking, washes and detection conditions as general IHC troubleshooting steps; this appearance alone does not establish an MLIP-specific cause (general IHC practice). |
| A heart or skeletal muscle section shows no convincing signal in its expected positive cells. | Those cells are reported High, so first confirm tissue identity and the assay controls (HPA tissue IHC; general IHC practice). Review the antibody's IHC-P instructions, detection reagents and retrieval settings if applicable (general IHC practice). The supplied sources do not establish MLIP-specific fixation or retrieval sensitivity. |
| Tissue and cell selection | Heart cardiomyocytes and skeletal myocytes offer reported High signal; smooth muscle cells are Medium (HPA tissue IHC). Adipocytes in adipose tissue are a reported Not detected comparison (HPA tissue IHC). Compare identified cell types, because mixed tissue can obscure which cells carry chromogen (general IHC practice). |
| Compartment used for scoring | HPA describes tissue staining as mainly cytoplasmic, while UniProt also annotates nucleus, nuclear envelope, PML body, cytosol and sarcolemma (HPA tissue IHC; UniProt Q5VWP3). Record compartment and cell type together; do not treat every departure from purely cytoplasmic staining as an artifact. |
| Topology and processing | MLIP has no transmembrane segment, signal peptide or propeptide, and its annotated chain spans residues 1–993 (UniProt Q5VWP3). Sarcolemma localization therefore does not by itself imply a membrane-spanning staining pattern (UniProt Q5VWP3 topology and localization). No tissue IHC effect of processing is established by these annotations. |
| Isoforms and epitope coverage | Four isoforms are listed (UniProt Q5VWP3). If a stain differs between tissues, check whether the antibody's documented epitope is shared across the isoforms before attributing the difference to expression (general IHC practice; UniProt Q5VWP3 isoforms). The supplied record gives no epitope map or isoform-specific tissue staining. |
| Strength of IHC evidence | HPA calls its tissue IHC profile Approved but notes medium staining–RNA consistency and pending external verification (HPA tissue IHC). HPA029252 has IHC Approved status (HPA antibodies). Use the reported pattern as a benchmark while interpreting unexpected staining with controls, rather than treating approval as proof of every signal's specificity (general IHC practice). |
| IF/ICC Q&A: should its pattern match tissue IHC exactly? | No exact match is established: HPA reports approved nucleoplasm and plasma-membrane localization, plus vesicles, in ICC-IF; tissue IHC is mainly cytoplasmic (HPA subcellular ICC-IF; HPA tissue IHC). UniProt also annotates nuclear and sarcolemma locations (UniProt Q5VWP3). Interpret each application against its own evidence. |
| Situation | Likely cause | Next action |
|---|---|---|
| No staining in cardiomyocytes or skeletal myocytes. | A failed staining run is possible; these cells are reported High, but the sources give no MLIP-specific fixation-effect finding (HPA tissue IHC). | Confirm section identity and assay controls, then check the antibody's IHC-P instructions, detection reagents and retrieval settings where applicable (general IHC practice). |
| Strong color appears in adipocytes. | This conflicts with reported Not detected adipocytes and could reflect cross-reactivity or endogenous detection activity (HPA tissue IHC; general IHC practice). | Compare a no-primary control and a known-positive muscle section; localize color to specific cells before scoring it as MLIP (general IHC practice; HPA tissue IHC). |
| Background is widespread and cell boundaries are unclear. | Diffuse color prevents comparison with the mainly cytoplasmic muscle-cell profile; the image alone cannot identify its cause (HPA tissue IHC; general IHC practice). | Review the no-primary control, blocking, washes and chromogen development, then reassess the cellular pattern (general IHC practice). |
| The only apparent positive signal is extracellular or particulate. | That appearance does not fit the reported muscle-cell staining and may represent a deposit or nonspecific signal (HPA tissue IHC; general IHC practice). | Inspect the deposits and detection controls; require a reproducible cellular pattern in an expected positive tissue before calling it MLIP (general IHC practice; HPA tissue IHC). |
| Nuclear or membrane-associated color accompanies muscle-cell staining. | UniProt lists nuclear, nuclear-envelope and sarcolemma locations, while HPA tissue IHC emphasizes cytoplasm (UniProt Q5VWP3; HPA tissue IHC). | Document the separate compartments and compare their cell distribution with controls; do not reject the stain solely because it is not exclusively cytoplasmic (general IHC practice; UniProt Q5VWP3). |
| Weak staining is seen outside heart and skeletal muscle. | Some nonmuscle cell types are reported Low, so weak staining outside the principal positive tissues is not automatically contradictory (HPA tissue IHC). | Identify the stained cell type and compare its reported HPA level; weigh weak signal against controls and the stronger expected muscle-cell pattern (HPA tissue IHC; general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Heart muscle | Cardiomyocytes | High | Protein (IHC) | HPA → |
| Skeletal muscle | Myocytes | High | Protein (IHC) | HPA → |
| Smooth muscle | Smooth muscle cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Caudate | Glial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot MLIP staining in paraffin sections by checking retrieval, compartment and cell type before comparing chromogenic IHC results with IF.
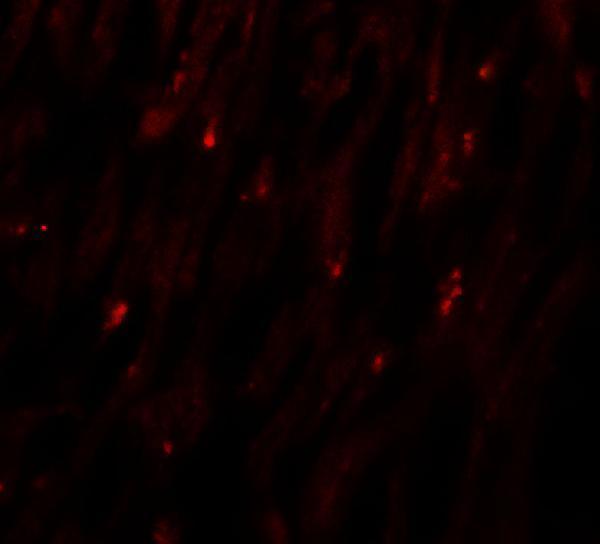
A12261 is a human-reactive anti-MLIP antibody with IHC and IF images from human heart tissue (catalog reactivity; A12261 image captions).
A12261 lists IHC-P and IF for human samples (catalog applications; catalog reactivity). Its IHC and IF images each show human heart tissue (A12261 image captions).
Which to pick: For tissue IHC, choose A12261 for human paraffin sections: IHC-P is listed, and its own IHC caption shows human heart tissue at 5 μg/mL; the fixative is unreported (catalog applications; A12261 IHC image caption). For IF, A12261 has a human-heart image at 20 μg/mL; ICC validation and clonality are unreported (catalog applications; A12261 IF image caption; catalog clone). No cross-species option is documented because A12261 lists human reactivity only (catalog reactivity).