This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section MTERF1 IHC with the IHC-validated antibody at 1:100–1:300 (datasheet). Assess cytoplasmic staining (HPA tissue IHC), keeping in mind its low agreement with RNA expression (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining (HPA tissue IHC); mitochondrion (UniProt) | |
| Staining pattern | Cytoplasmic staining in most tissues; intensity varies (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Staining has low agreement with RNA expression (HPA tissue IHC) | |
| Regulation | RNA has low tissue specificity (HPA tissue RNA) | |
| Isoform / epitope | No isoforms annotated; mature chain 58–399; epitope unknown (UniProt) |
The catalog antibody's IHC-P protocol (datasheet) is accompanied by one published MTERF1 IHC protocol covering colorectal tissue and xenograft samples (PMC9604058).
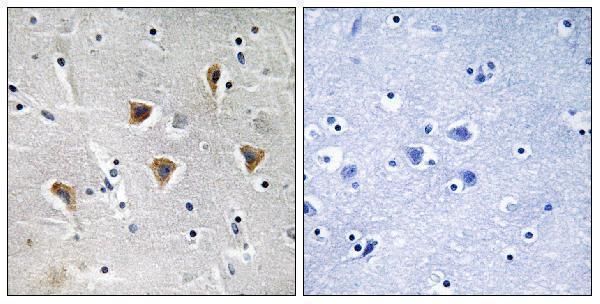
| Sample | Paraffin-embedded human brain tissue; fixative not specified (datasheet A30769) |
| Fixation | Image fixative and duration unreported (datasheet A30769); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-MTERF1, 1:100 - 1:300 (datasheet A30769) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | MTERF1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
MTERF1 localizes to mitochondria (UniProt Q99551; HPA: supported ICC/IF location) and has no transmembrane segment (UniProt Q99551 topology). In paraffin-section IHC, expect cytoplasmic staining in selected glandular, respiratory epithelial, hematopoietic, and neuronal cells reported at medium intensity (HPA: tissue IHC). Treat that expectation cautiously: HPA calls its tissue IHC reliability uncertain because antibody staining and RNA expression have low consistency (HPA: tissue IHC reliability).
| Cytoplasmic, possibly granular staining in colon glandular cells or bronchial respiratory epithelial cells. | This fits the reported medium staining in those cells (HPA: tissue IHC) and mitochondrial localization (UniProt Q99551; HPA: supported ICC/IF). Chromogenic IHC may not resolve individual mitochondria (general IHC practice). |
| Predominantly nuclear, membrane-rim, or extracellular staining with little cytoplasmic signal. | This conflicts with mitochondrial localization and the absence of a transmembrane segment (UniProt Q99551 topology; HPA: supported ICC/IF). Review morphology and controls before interpreting it as MTERF1 (general IHC practice). |
| Strong staining in adipocytes or lymph-node germinal center cells. | HPA reports MTERF1 as not detected in those cell types (HPA: tissue IHC). Consider antibody cross-reactivity or chromogenic endogenous activity; HPA's uncertain IHC reliability prevents treating either explanation as proven (HPA: tissue IHC reliability; general IHC practice). |
| Uniform haze across cells, stroma, and slide background. | This is poorly matched to cell-associated cytoplasmic staining (HPA: tissue IHC). Review background controls, blocking, antibody concentration, and chromogen development as general IHC variables; the supplied sources identify no MTERF1-specific cause (general IHC practice). |
| No staining in colon glandular cells while assay controls develop normally. | Colon glandular cells show medium staining in HPA images (HPA: tissue IHC), so first check the sampled cells, staining run, and antibody performance (general IHC practice). The HPA result is an uncertain benchmark, not proof that every section must stain (HPA: tissue IHC reliability). |
| Compartment and topology | Mitochondrial localization supports a cytoplasmic pattern (UniProt Q99551; HPA: supported ICC/IF); no transmembrane segment supports scrutiny of dominant membrane-rim staining (UniProt Q99551 topology). |
| Tissue and cell selection | HPA reports medium staining in several glandular, respiratory epithelial, hematopoietic, and neuronal populations, but not-detected results in selected other cells (HPA: tissue IHC). Match the exact cell type when comparing sections. |
| Strength of IHC evidence | HPA rates tissue IHC uncertain because staining and RNA expression have low consistency; its IHC antibody HPA044894 is also rated uncertain (HPA: tissue IHC reliability; HPA: antibodies). Interpret intensity as an observation, not validation. |
| Mature protein and epitope | UniProt annotates a mature chain at residues 58–399 and no isoforms or glycosylation sites (UniProt Q99551). The supplied record gives no antibody epitope, so these annotations cannot predict its staining performance. |
| Can ICC/IF confirm the compartment? | HPA supports mitochondrial ICC/IF localization and rates antibody HPA069560 supported for ICC (HPA: subcellular; HPA: antibodies). That supports a compartment comparison; it does not resolve the uncertain tissue IHC rating (HPA: tissue IHC reliability). |
| Situation | Likely cause | Next action |
|---|---|---|
| A reported medium-staining cell population appears blank. | The chosen field may lack the relevant cells, or an IHC run variable may have failed (HPA: tissue IHC; general IHC practice). | Confirm cell identity and inspect run controls; review the IHC antibody's validated dilution and retrieval conditions before changing them (general IHC practice). Do not infer MTERF1-specific fixation sensitivity from these sources. |
| Signal is mostly nuclear or outlines plasma membranes. | That distribution conflicts with the mitochondrial location and lack of a transmembrane segment (UniProt Q99551; HPA: supported ICC/IF). | Check morphology and controls, then reassess antibody specificity and chromogen development (general IHC practice). Do not score the discordant compartment as a positive MTERF1 result. |
| Adipocytes or germinal center cells stain strongly. | HPA lists both as not detected; cross-reactivity or endogenous chromogenic activity is possible, not established (HPA: tissue IHC; general IHC practice). | Compare adjacent cell types and controls, including a no-primary control and appropriate endogenous-activity blocking for the detection system (general IHC practice). |
| A widespread brown haze obscures cell boundaries. | Nonspecific binding, excessive reagent concentration, or overdevelopment can raise chromogenic background (general IHC practice). | Inspect the no-primary control, blocking, washes, antibody dilution, and development time; adjust only the implicated step (general IHC practice). HPA provides no MTERF1-specific background mechanism. |
| Signal appears in expected cells but lacks visible puncta. | Mitochondria may not resolve as separate structures in chromogenic paraffin-section IHC (general IHC practice). | Judge the cell-associated cytoplasmic pattern alongside morphology and controls (HPA: tissue IHC; general IHC practice). Avoid requiring discrete puncta to call every IHC field plausible. |
| IHC and ICC/IF results seem inconsistent. | HPA supports mitochondrial ICC/IF yet rates tissue IHC uncertain; these are separate assay assessments (HPA: subcellular; HPA: tissue IHC reliability). | Compare compartment-level findings and each assay's own controls; keep the tissue IHC uncertainty in the interpretation (HPA: subcellular; HPA: tissue IHC reliability; general IHC practice). |
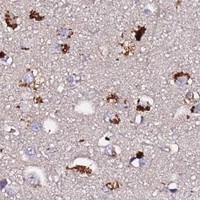
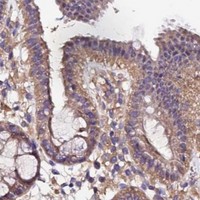


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Lymph node | Germinal center cells | Not detected | Protein (IHC) | HPA → |
| Oral mucosa | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Ovary | Ovarian stroma cells | Not detected | Protein (IHC) | HPA → |
| Parathyroid gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot MTERF1 staining in paraffin sections by checking retrieval, compartment, controls, and scoring before interpreting chromogenic signal.
A30769 is listed for IHC and IF/ICC in human, mouse and rat (catalog: applications and reactivity); its supplied image shows paraffin-section human-brain IHC (A30769 image caption).
A30769 has an IHC image of paraffin-embedded human brain with a peptide-blocked comparison (A30769 image caption). It is listed for IHC and IF/ICC in human, mouse and rat (catalog: applications and reactivity), but no IF image is supplied (catalog: IF image alts).
Which to pick: For tissue IHC, choose A30769 at the listed 1:100–1:300 dilution (datasheet: IHC dilution); its own image shows paraffin-embedded human brain, and the fixative is unreported (A30769 image caption). For IF/ICC, A30769 is listed for both applications (catalog: applications), though no IF image is supplied (catalog: IF image alts). For human, mouse or rat work, A30769 is the listed rabbit polyclonal option (catalog: reactivity, host and dilution_raw).