MTMR3 / Phosphatidylinositol-3,5-bisphosphate 3-phosphatase MTMR3 · IHC design guide

Design Immunohistochemistry for MTMR3

Plan paraffin-section MTMR3 IHC around cytoplasmic staining, most abundant in seminiferous duct basal cells (HPA tissue IHC). Start with 2–5 μg/ml of catalog antibody A05937-1 (datasheet A05937-1), and compare cell-specific staining with a no-primary control (standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MTMR3 (IHC for MTMR3): expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody A05937-1, validated IHC image, and IHC protocol steps
Printable MTMR3 IHC protocol sheet — expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody A05937-1, controls and protocol steps. Open the full MTMR3 IHC guide →

MTMR3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC)
Staining pattern Cytoplasmic in most tissues; strongest in seminiferous duct basal cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A05937-1)
Positive control ⓘ Breast+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet A05937-1); verify before use.
Caveat Tissue staining has uncertain concordance with RNA expression (HPA tissue IHC)
Regulation Bone marrow RNA is tissue enhanced (HPA tissue IHC)
Isoform / epitope 3 isoforms; epitope coverage unknown; no transmembrane segment (UniProt)
Section 1

Recommended MTMR3 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A05937-1) is accompanied by published protocols for breast tumors (PMC6775797) and gastric cancer patient and mouse tumor samples (PMC7670601).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A05937-1)
FixationImage fixative and duration unreported (datasheet A05937-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A05937-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A05937-1)
Primary antibodyRabbit anti-MTMR3, 2-5 μg/ml (datasheet A05937-1)
Primary incubationOvernight at 4 °C (datasheet A05937-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A05937-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMTMR3-positive staining in myoepithelial cells of breast (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues, most abundant in basal cells in seminiferous ducts. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A05937-1); use citrate retrieval when reproducing the breast tumor protocol (PMC6775797).
Section 2

What Is the Expected MTMR3 Staining Pattern?

MTMR3 is reported in the cytosol and at membranes, with no transmembrane segment (UniProt Q13615: subcellular location and topology). In tissue sections, expect mainly cytoplasmic staining; HPA reports high staining in cells of seminiferous ducts, bronchial respiratory epithelium and breast myoepithelium (HPA: tissue IHC). Treat this as a provisional pattern because HPA rates the tissue IHC profile uncertain (HPA: tissue IHC reliability).

What am I looking at on my slide?
Cytoplasmic staining in basal cells of seminiferous ducts, respiratory epithelial cells or breast myoepithelial cells (HPA: tissue IHC).This matches the reported tissue pattern; compare the named cell population with nearby cells, rather than scoring the entire section as uniformly positive (HPA: tissue IHC; general IHC practice).
A sharp membrane-only rim or exclusively nuclear chromogenic signal, with no discernible cytoplasmic staining (HPA: tissue IHC; UniProt Q13615: topology).This is discordant with the reported IHC pattern and warrants an artefact check (HPA: tissue IHC; general IHC practice). Membrane association is possible, but UniProt reports no transmembrane segment (UniProt Q13615: subcellular location and topology).
Strong staining in adipocytes or liver cholangiocytes (HPA: not detected in those cell types).This conflicts with the listed HPA observations for those specific cells. Check antibody specificity or endogenous detection activity before calling it MTMR3; neither observation makes its whole tissue a negative control (HPA: tissue IHC; general IHC practice).
Diffuse colour across cells and surrounding tissue, without recognizable cell boundaries (general IHC practice).A diffuse deposit is difficult to score as a cellular pattern. Review blocking, washing, antibody concentration and chromogen development alongside a reagent control (general IHC practice).
No staining in cells of seminiferous ducts, bronchial respiratory epithelium or breast myoepithelium (HPA: high in these cell populations).Check whether the expected cells are present, then assess section quality, retrieval and detection with appropriate controls (general IHC practice). HPA's uncertain IHC reliability limits what one negative section proves (HPA: tissue IHC reliability).
💡Expected MTMR3 appearanceCall a positive result when identifiable expected cells show cytoplasmic chromogenic staining, especially HPA's high-staining seminiferous-duct, respiratory epithelial or myoepithelial populations; diffuse deposit or isolated staining in an HPA-listed undetected cell type is suspect (HPA: tissue IHC; general IHC practice).
How each factor affects the staining
How firm is the reference pattern? (HPA: tissue IHC reliability)HPA rates tissue IHC reliability uncertain, describing medium consistency between antibody staining and RNA expression; its two listed antibodies, HPA034515 and HPA034516, each have uncertain IHC validation (HPA: tissue IHC and antibody validation).
What compartment should guide scoring? (UniProt Q13615: subcellular location and topology)UniProt lists cytosol and membrane and no transmembrane segment; HPA describes predominantly cytoplasmic tissue staining. Score the observed cellular distribution rather than requiring a continuous membrane outline (UniProt Q13615: subcellular location and topology; HPA: tissue IHC).
Can RNA abundance choose the strongest protein control? (HPA: tissue IHC)HPA calls RNA expression tissue enhanced in bone marrow, yet lists bone-marrow hematopoietic cells at medium protein staining. Choose a positive cell population from the IHC observations, and keep RNA and protein readouts distinct (HPA: tissue IHC).
Do isoforms change the interpretation? (UniProt Q13615: isoforms)UniProt lists 3 isoforms, B, A and C. The supplied sources give no antibody epitope mapping or isoform-specific tissue pattern, so these records cannot assign a staining difference to one isoform (UniProt Q13615: isoforms; HPA: antibody validation).
Q: Should IF/ICC show the same compartment as tissue IHC? (HPA: tissue IHC and subcellular ICC-IF)A: HPA lists nucleoplasm as the main ICC-IF location with uncertain support, and cytosol as an additional supported location. Interpret that assay-specific observation separately from HPA's cytoplasmic tissue IHC pattern (HPA: subcellular ICC-IF and tissue IHC).
Could the detection system create colour? (general IHC practice)Endogenous enzyme activity or nonspecific reagent binding can mimic chromogenic staining. Appropriate reagent controls help distinguish detection artefact from a cell-specific antibody signal (general IHC practice).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive cells are absent from the section (HPA: tissue IHC).The selected field may lack the named cell population; tissue-wide labels alone do not identify positive cells (HPA: tissue IHC; general IHC practice).Locate the relevant cells on a counterstained section before interpreting a negative result; use HPA's named cell populations to select the field (HPA: tissue IHC; general IHC practice).
Expected cells are present but show no chromogenic signal (HPA: tissue IHC).Retrieval or detection may have failed, or the specimen may differ from HPA's uncertain reference pattern (general IHC practice; HPA: tissue IHC reliability).Check a positive control and detection reagents; optimize retrieval and antibody concentration as general IHC variables, without assuming MTMR3-specific fixation sensitivity (general IHC practice).
Signal is diffuse throughout the section (general IHC practice).Excess antibody, insufficient washing or prolonged chromogen development can raise background (general IHC practice).Compare with a reagent control, then adjust concentration, washes or development time one variable at a time (general IHC practice).
Undetected reference cells stain strongly, such as adipocytes or cholangiocytes (HPA: tissue IHC).Cross-reactivity or endogenous detection activity is possible; the HPA observations alone cannot identify which caused the signal (HPA: tissue IHC; general IHC practice).Inspect reagent controls and the spatial pattern, then compare with an independent specificity control before assigning the signal to MTMR3 (general IHC practice).
Only a sharp membrane outline is visible (UniProt Q13615: topology; HPA: tissue IHC).UniProt allows membrane association, but HPA describes a cytoplasmic tissue pattern; an outline alone is inconclusive (UniProt Q13615: subcellular location and topology; HPA: tissue IHC).Recheck cellular boundaries and background, then compare the named positive cells with controls before scoring the outline as MTMR3 (HPA: tissue IHC; general IHC practice).
Nuclear signal dominates a chromogenic tissue section (HPA: tissue IHC).That differs from HPA's cytoplasmic tissue description; HPA's uncertain nucleoplasmic observation comes from ICC-IF (HPA: tissue IHC and subcellular ICC-IF).Assess counterstain overlap and reagent controls, and record the nuclear pattern as discordant with tissue IHC pending specificity assessment (general IHC practice; HPA: tissue IHC).

Sample controls for MTMR3 IHC & IF

🧪Run breast first and require staining in its myoepithelial cells (HPA: Breast, myoepithelial cells, High); use adipose tissue as the negative tissue and assess its adipocytes (HPA: Adipose tissue, adipocytes, Not detected). On the breast slide, use neighboring cells outside the myoepithelial compartment as candidate internal negatives, expecting background only after confirming that those cells lack specific staining.
Positive control tissue: Breast (Myoepithelial cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MTMR3 in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (uncertain) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a matched rabbit IgG isotype control (selected A05937-1 tissue-IHC caption: rabbit primary), and a biological negative such as MTMR3 knockout material or peptide competition if available. Quench endogenous peroxidase before HRP/DAB detection, particularly where blood cells are present (standard IHC practice; selected A05937-1 tissue-IHC caption: HRP/DAB detection).
⚠️Feasibility: The selected paraffin-section caption uses heat retrieval in EDTA at pH 8.0 and 2 μg/ml primary antibody overnight at 4°C; it does not report the fixative (selected A05937-1 tissue-IHC caption). A target-specific fixation window, fixation effect, and requirement for EDTA retrieval are unreported, and the supplied evidence does not establish whether frozen sections or IF are easier. In breast sections, adipocytes should not be mistaken for failed positive-control staining (HPA: Adipose tissue, adipocytes, Not detected).

HPA tissue IHC evidence for MTMR3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Breast Myoepithelial cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Testis Cells in seminiferous ducts High Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Hippocampus Glial cells Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced MTMR3 IHC Tips

Use the catalog antibody’s paraffin-section workflow as the starting point, then assess MTMR3 staining by cell type and compartment.

How should I retrieve MTMR3 in paraffin sections when staining is weak?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 (datasheet A05937-1). The illustrated paraffin section was subsequently incubated with 2 μg/mL catalog antibody overnight at 4°C, so keep antibody concentration and incubation consistent while assessing retrieval (caption A05937-1). Run a known positive section alongside the test section and compare cytoplasmic staining in the expected cells rather than judging total tissue darkness (HPA tissue IHC; standard IHC practice). If staining remains weak, optimize heating and cooling on replicate sections before changing antibody concentration; excessive retrieval can damage morphology and make compartment assignment unreliable (standard IHC practice).
Could fixation explain weak or patchy MTMR3 staining in my paraffin sections?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative (caption A05937-1). Record the actual fixative, fixation duration, tissue thickness, and processing history for each specimen, then compare sections processed together under the same retrieval and detection conditions (standard IHC practice). Use the documented EDTA pH 8.0 retrieval and 2 μg/mL overnight antibody incubation as the starting conditions when evaluating a processing difference (datasheet A05937-1; caption A05937-1). Include a concurrently processed positive tissue control; a uniform loss across test and control sections suggests a shared processing or staining problem rather than evidence of absent MTMR3 (standard IHC practice).
Should MTMR3 staining be cytoplasmic, membranous, or nuclear in tissue?
Assess cytoplasmic staining first: the tissue profile describes cytoplasmic expression in most tissues, while UniProt lists cytosol and membrane localisation (HPA tissue IHC; UniProt Q13615 subcellular). MTMR3 has no transmembrane segment, so a crisp plasma-membrane outline alone needs independent validation before being scored as specific staining (UniProt Q13615 topology; standard IHC practice). A separate cell-imaging record reports supported cytosol localisation and uncertain nucleoplasm localisation; it does not establish a nuclear pattern for this chromogenic tissue assay (HPA subcellular). Compare staining within morphologically identified cells and across a matched negative control, especially when nuclear counterstain or diffuse DAB makes the compartment difficult to distinguish (standard IHC practice).
Can this antibody distinguish MTMR3 isoforms or phosphorylation states in tissue?
Do not assign staining to a particular isoform until the catalog antibody’s immunogen and epitope are mapped against isoforms A, B, and C (UniProt Q13615 isoforms; standard IHC practice). MTMR3 contains a myotubularin phosphatase domain at residues 155–576 and annotated phosphoserines including positions 8 and 613, but those annotations do not establish this antibody’s epitope or phosphorylation preference (UniProt Q13615 domains and modified residues). If isoform specificity matters, compare epitope-bearing sequences and validate staining with an orthogonal, isoform-aware assay (standard IHC practice). Report the result as MTMR3 immunoreactivity until that validation is available, and apply the same scoring rule across specimens (standard IHC practice).
How should I adapt MTMR3 assessment to multiplex immunofluorescence?
For IF/ICC, include a marker that identifies the expected cell population, such as a validated myoepithelial marker when examining breast tissue, and judge MTMR3 signal within that population (HPA tissue IHC: high in breast myoepithelial cells; standard IF practice). Select fluorophores after imaging unstained tissue, placing the weaker signal in a channel with low autofluorescence and checking each single-color control for bleed-through (standard IF practice). MTMR3 is reported in cytosol and at membranes without a transmembrane segment, so optimize permeabilisation for access to intracellular epitopes once the antibody epitope is known (UniProt Q13615 subcellular and topology; standard IF practice). Keep IF fixation and permeabilisation conditions documented independently of the paraffin-section IHC caption (caption A05937-1; standard IF practice).
What should I check when MTMR3 DAB staining is diffuse or widespread?
Compare the test with a no-primary control and inspect whether color follows tissue structures, section edges, or sites of damaged morphology (standard IHC practice). The illustrated workflow used 10% goat serum, a peroxidase-conjugated secondary antibody, and DAB; reproduce its blocking and detection conditions before troubleshooting deviations (caption A05937-1). Block endogenous peroxidase as a general chromogenic IHC step, and check secondary-only staining to separate detection background from antibody-dependent signal (standard IHC practice). Because the reported tissue pattern is largely cytoplasmic, diffuse color that obscures cell boundaries should not be counted as MTMR3-positive cells without a clean control and interpretable morphology (HPA tissue IHC; standard IHC practice).
How can I compare MTMR3 IHC across specimens with different cell composition? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring; for example, score morphologically identified breast myoepithelial cells separately from neighboring cells (HPA tissue IHC: high in breast myoepithelial cells; standard IHC practice). An H-score combines the percentage of cells at each staining intensity, while percentage-positive scoring requires a prespecified positivity threshold (standard IHC practice). Normalize cell counts to the number of eligible cells, or report positive-cell density per mm² of viable, annotated tissue when area is the denominator (standard IHC practice). Use the same imaging, counterstain, threshold, and exclusion rules across slides, and report the HPA tissue-IHC reliability as uncertain when using its pattern as a reference (standard IHC practice; HPA tissue IHC).
How do I distinguish genuine MTMR3 staining from tissue artefact?
Look for a reproducible cellular pattern: the tissue reference describes mainly cytoplasmic expression, including high staining in breast myoepithelial cells, respiratory epithelial cells, and cells in seminiferous ducts (HPA tissue IHC). Treat a nuclear-only pattern cautiously because nucleoplasm localisation is labeled uncertain in cell imaging, whereas cytosol localisation is supported (HPA subcellular). Exclude staining confined to cut edges, folds, necrotic regions, or areas with poor morphology, and use a no-primary control to assess endogenous enzyme and detection background (standard IHC practice). Interpret disagreement with the tissue reference conservatively because its antibody staining and RNA agreement is rated uncertain, with medium consistency (HPA tissue IHC).
Boster reagents

Best MTMR3 / Phosphatidylinositol-3,5-bisphosphate 3-phosphatase MTMR3 IHC Antibodies

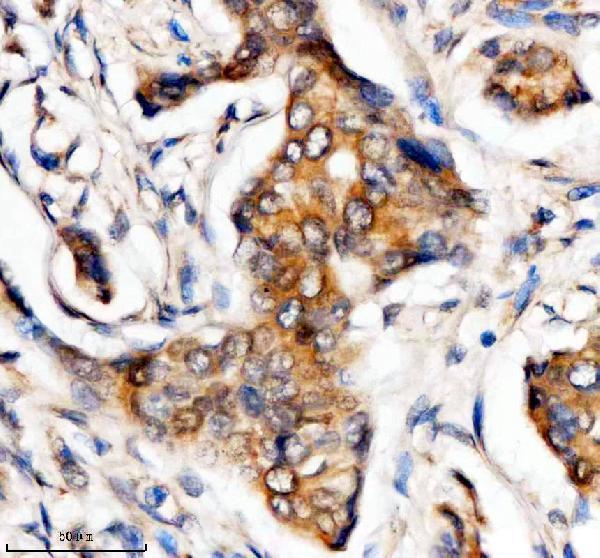
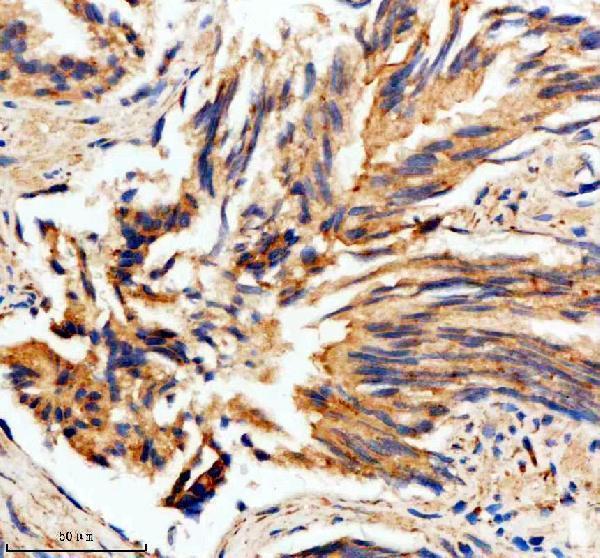
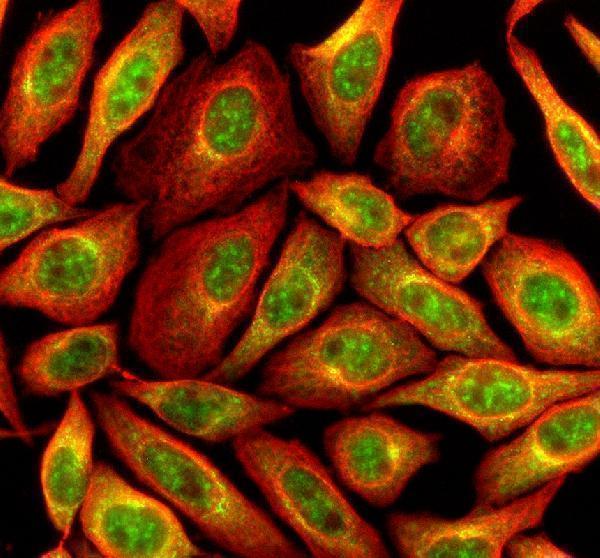
Anti-MTMR3 A05937-1 has IHC images of human paraffin breast and prostate cancer sections and IF images of SIHA cells and human paraffin breast cancer sections (catalog image captions).

Real IHC data IHC analysis of MTMR3 using anti-MTMR3 antibody (A05937-1). MTMR3 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-MTMR3 Antibody (A05937-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-MTMR3 Antibody ®
Cat # A05937-1

A05937-1 is the only SKU shown and is listed for human IHC and IF/ICC (catalog applications and reactivity). Its IHC captions show paraffin human breast and prostate cancer sections; its IF captions show SIHA cells and paraffin human breast cancer tissue (catalog image captions).

Which to pick: Choose A05937-1 for human paraffin-section IHC: its own IHC captions document EDTA pH 8.0 retrieval and 2 μg/ml primary antibody in breast and prostate cancer sections (catalog IHC captions). The same SKU is listed for IF/ICC and has IF images of SIHA cells and human paraffin breast cancer tissue; no cross-species choice is supported by the Human-only reactivity listing (catalog applications, reactivity and IF captions). Fixative and clonality are unreported (catalog IHC captions; catalog clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q13615 (MTMR3_HUMAN, Phosphatidylinositol-3,5-bisphosphate 3-phosphatase MTMR3).
  2. Human Protein Atlas. MTMR3 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. MTMR3 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol..
  4. Human Protein Atlas. MTMR3 antibody validation summary (2 antibodies).
  5. MTMR3 is upregulated in patients with breast cancer and regulates proliferation, cell cycle progression and autophagy in breast cancer cells. Oncology reports 2019 — PMC6775797.
  6. miR-100-5p Promotes Epidermal Stem Cell Proliferation through Targeting MTMR3 to Activate PIP3/AKT and ERK Signaling Pathways. Stem cells international 2022 — PMC9421352.
  7. Circular RNA MCTP2 inhibits cisplatin resistance in gastric cancer by miR-99a-5p-mediated induction of MTMR3 expression. Journal of experimental & clinical cancer research : CR 2020 — PMC7670601.
  8. PubMed PMID:10733931 — UniProt-cited evidence.
  9. PubMed PMID:9205841 — UniProt-cited evidence.
  10. PubMed PMID:15461802 — UniProt-cited evidence.