MYCBP / c-Myc-binding protein · IHC design guide

Design Immunohistochemistry for MYCBP

Plan chromogenic MYCBP IHC in paraffin sections using the catalog antibody's IHC protocol (datasheet A06216-2). Compare staining with HPA tissue benchmarks, including high staining in adrenal glandular cells and no detection in adipocytes, while accounting for the antibody specificity caveat (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
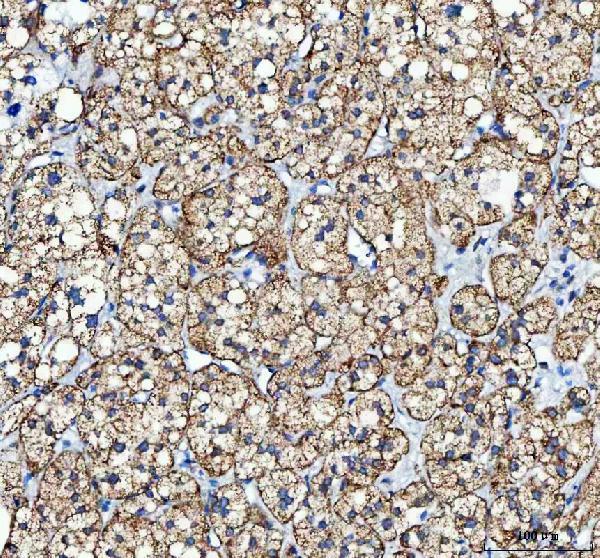
Immunohistochemistry protocol sheet for MYCBP (IHC for MYCBP): expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody A06216-2, validated IHC image, and IHC protocol steps
Printable MYCBP IHC protocol sheet — expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody A06216-2, controls and protocol steps. Open the full MYCBP IHC guide →

MYCBP Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Cytoplasmic staining in glandular cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A06216-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat Antibody may detect proteins from more than one gene (HPA tissue IHC)
Regulation MYC rise in S phase drives nuclear entry (UniProt)
Isoform / epitope No annotated isoforms; mature chain spans residues 2–103 (UniProt)
Section 1

Recommended MYCBP IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet A06216-2) with published MYCBP staining protocols for human HCC (PMC6778622) and osteosarcoma paraffin sections (PMC10988859).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human adrenal adenomas tissue; fixative not specified (datasheet A06216-2)
FixationImage fixative and duration unreported (datasheet A06216-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A06216-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A06216-2)
Primary antibodyRabbit anti-MYCBP, 2-5 μg/ml (datasheet A06216-2)
Primary incubationOvernight at 4 °C (datasheet A06216-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A06216-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMYCBP-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet A06216-2); neither emitted article specifies retrieval conditions (PMC6778622; PMC10988859).
Section 2

What Is the Expected MYCBP Staining Pattern?

In paraffin IHC, expect mainly cytoplasmic MYCBP staining in glandular or epithelial cells, including adrenal glandular and bronchial respiratory epithelial cells (HPA: general cytoplasmic expression; High in both). Nuclear and mitochondrial localisation is biologically plausible (UniProt Q99417: cytoplasm, nucleus, mitochondrion; no transmembrane segment). Interpret staining cautiously: HPA rates tissue IHC as Supported, reports medium agreement with RNA, and warns that the assessed staining may include proteins from more than one gene (HPA: tissue IHC reliability).

What am I looking at on my slide?
Cytoplasmic staining in adrenal glandular or bronchial respiratory epithelial cells (HPA: High in both).This matches the reported paraffin tissue pattern (HPA: general cytoplasmic expression). Compare cells within the same section and a matched control before judging intensity; processing and detection can alter apparent strength (general IHC practice).
Predominantly membrane, luminal, or extracellular staining, without the expected cytoplasmic pattern (HPA: general cytoplasmic expression).Treat this as suspect localisation: MYCBP has no transmembrane segment (UniProt Q99417: topology). Check morphology and controls for nonspecific signal (general IHC practice). Nuclear staining alone needs context because MYCBP can enter the nucleus in S phase (UniProt Q99417: subcellular note).
Strong signal in adipocytes or cardiomyocytes, where HPA reports no detection (HPA: adipocytes and cardiomyocytes, Not detected).Cross-reactivity or endogenous detection activity is possible (general IHC practice). These cells are comparison controls, not absolute exclusions: UniProt reports high heart expression, while HPA reports no cardiomyocyte staining (UniProt Q99417: tissue specificity; HPA: heart muscle).
Diffuse colour across cells and tissue spaces, with little cellular definition (general IHC practice).This is compatible with background from detection reagents, inadequate blocking, or excessive primary antibody (general IHC practice). It does not establish MYCBP localisation; compare a no-primary control and a known positive section (general IHC practice).
No signal in adrenal glandular or bronchial respiratory epithelial cells (HPA: High in both).First investigate a technical failure or sample-specific loss of signal (general IHC practice). HPA's Supported rating and multi-gene warning limit what one negative slide proves about MYCBP itself (HPA: tissue IHC reliability).
💡Expected MYCBP appearanceCall a positive result when defined cytoplasmic staining is evident in HPA High glandular or respiratory epithelial cells; diffuse background or isolated membrane/luminal colour is suspect (HPA: tissue IHC profile and levels; UniProt Q99417: topology; general IHC practice).
How each factor affects the staining
Which paraffin tissue gives a useful positive comparison?Adrenal glandular, appendix glandular, colon glandular, and bronchial respiratory epithelial cells are reported High (HPA: tissue IHC). Use their cell-specific pattern as a comparison; the HPA rating is Supported and carries a multi-gene caution (HPA: tissue IHC reliability).
How should heart and skeletal muscle be interpreted?UniProt reports high expression in both tissues, but HPA reports cardiomyocytes Not detected and skeletal myocytes Low by IHC (UniProt Q99417: tissue specificity; HPA: tissue IHC). Do not use either as the sole slide-level positive benchmark.
Does nuclear or mitochondrial staining fit MYCBP biology?Yes: UniProt lists nucleus and mitochondrion, with nuclear entry in S phase and mitochondrial association with AKAP1 (UniProt Q99417: subcellular notes). HPA tissue IHC nevertheless describes a general cytoplasmic pattern (HPA: tissue IHC profile). Judge focal organelle-like signal against controls.
How strong is the antibody-based localisation evidence?The reported tissue IHC antibody is Supported, while a separate ICC antibody is Supported (HPA: HPA041188 IHC; HPA078331 ICC). These statuses do not prove that every signal comes from MYCBP; HPA warns that the assessed staining may include proteins from more than one gene (HPA: tissue IHC and subcellular cautions).
What should an IF/ICC image show?HPA describes mainly nucleoplasmic signal with additional mitochondrial localisation and lists PC-3, Rh30, and U2OS images (HPA: subcellular ICC-IF). That IF/ICC observation belongs to a different assay context; the paraffin IHC comparison remains HPA's general cytoplasmic tissue pattern (HPA: tissue IHC profile).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known positive glandular or respiratory epithelial cells remain blank (HPA: High in adrenal glandular and bronchial epithelial cells).The run may have failed, or the section may have lost detectable signal (general IHC practice). HPA's Supported pattern does not guarantee signal in every specimen (HPA: tissue IHC reliability).Check section integrity, retrieval, primary antibody application, detection reagents, and a concurrently stained positive section (general IHC practice). Record the conditions before changing more than one variable.
Most tissue compartments show uniform colour with poor cell boundaries (general IHC practice).Background from reagent binding or detection chemistry may dominate the specific cellular pattern (general IHC practice).Compare no-primary and positive controls; review blocking, washing, primary antibody concentration, and chromogen development (general IHC practice). Reassess whether cytoplasm in the expected cells remains distinguishable (HPA: general cytoplasmic expression).
Membranes or gland lumens stain more strongly than cell cytoplasm (HPA: general cytoplasmic expression).Nonspecific deposition or trapped detection reagent is possible (general IHC practice); MYCBP has no transmembrane segment (UniProt Q99417: topology).Inspect adjacent morphology and the no-primary control; adjust washing or detection conditions if those controls show matching colour (general IHC practice). Do not score isolated luminal colour as MYCBP positivity.
Adipocytes or splenic red-pulp cells appear strongly positive (HPA: Not detected in these cells).Cross-reactivity or endogenous detection activity is possible (general IHC practice). HPA also cautions that the assessed staining may involve proteins from more than one gene (HPA: tissue IHC reliability).Review a no-primary control and the staining distribution; use cell-specific positive tissue on the same run (general IHC practice; HPA: High in adrenal glandular cells). Report the discrepancy instead of assigning it to MYCBP alone.
Brown deposits persist in the no-primary control (general IHC practice).Endogenous peroxidase activity or nonspecific detection chemistry can create chromogenic signal without primary antibody (general IHC practice).Review the detection system and its endogenous activity block; repeat the control alongside the test section after correcting the workflow (general IHC practice). Do not count control-matched deposits as target staining.
A nuclear signal conflicts with an otherwise weak cytoplasmic IHC result (HPA: general cytoplasmic expression).Nuclear MYCBP is plausible during S phase, but background or antibody cross-reactivity also needs consideration (UniProt Q99417: subcellular note; HPA: multi-gene caution).Check whether the nuclear signal follows cell boundaries and disappears in a no-primary control (general IHC practice). Describe nuclear and cytoplasmic findings separately; compare with HPA's tissue IHC and ICC-IF patterns (HPA: tissue IHC; subcellular ICC-IF).

Sample controls for MYCBP IHC & IF

🧪Run adrenal gland first: glandular cells should stain strongly (HPA: High in adrenal gland glandular cells). Use adipose tissue adipocytes as the negative tissue (HPA: Not detected in adipocytes); on the adrenal slide, adjacent nonglandular cells should show only background signal to serve as internal comparators, though their MYCBP status is unreported (HPA: adrenal gland glandular-cell entry).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MYCBP in PC-3, Rh30, U2OS, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide, a concentration-matched rabbit IgG isotype control, and MYCBP knockout tissue as a biological negative (caption: rabbit anti-MYCBP primary and peroxidase-conjugated goat anti-rabbit secondary). Quench endogenous peroxidase before chromogenic detection and assess background on the adrenal section (caption: HRP/DAB detection in adrenal adenoma tissue).
⚠️Feasibility: A target-specific fixation window and fixation effect are unreported, and the selected A06216-2 paraffin-section caption does not state the fixative (caption: fixative not stated). The demonstrated paraffin-section procedure used heat retrieval in EDTA at pH 8.0, but the evidence does not establish that retrieval is required or that frozen sections or IF are easier (caption: heat-mediated EDTA retrieval; HPA: ICC-IF images in PC-3, Rh30 and U2OS). Check adrenal sections for endogenous peroxidase background when interpreting DAB staining (caption: adrenal adenoma section with HRP/DAB detection).

HPA tissue IHC evidence for MYCBP

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Spleen Cells in red pulp Not detected Protein (IHC) HPA →
Section 3

Advanced MYCBP IHC Tips

Troubleshoot MYCBP staining in paraffin sections by tracking retrieval, cell type, compartment, and antibody specificity alongside each control.

Which retrieval conditions should I start with for MYCBP in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A06216-2). The documented image used this retrieval before 10% goat serum blocking and 2 μg/ml primary antibody overnight at 4°C (datasheet A06216-2). If staining is weak, compare a second retrieval condition on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Score signal and tissue damage together, because stronger chromogen alone does not establish improved specificity (standard IHC practice). Include a glandular reference section when available, while treating its expected staining as provisional given the antibody cross-target caution (HPA tissue IHC: Supported; targets proteins from more than one gene).
How should I troubleshoot weak MYCBP staining when fixation records vary?
The catalog image documents a paraffin-embedded adrenal adenoma section but does not report its fixative (datasheet A06216-2). Target-specific sensitivity to fixative type or fixation duration is therefore unknown from the supplied evidence (datasheet A06216-2). Record the fixative and exposure time for each specimen, then compare matched sections processed with the same EDTA pH 8.0 retrieval and detection steps (standard IHC practice; datasheet A06216-2). Check morphology and staining in an internal reference population before changing antibody concentration, since poorly preserved tissue complicates interpretation (standard IHC practice). Do not use the HPA staining pattern to assign a fixation effect to MYCBP (HPA tissue IHC: Supported, with cross-target caution).
Should MYCBP staining be cytoplasmic, nuclear, or mitochondrial?
Assess cytoplasmic staining first in chromogenic sections, because the tissue profile describes general cytoplasmic expression (HPA tissue IHC). Nuclear signal remains biologically plausible: MYCBP can move into the nucleus during S phase when MYC expression increases (UniProt Q99417: subcellular location). Mitochondrial association is also reported when MYCBP associates with AKAP1, although DAB staining alone cannot resolve individual mitochondria reliably (UniProt Q99417: subcellular location; standard IHC practice). Score nuclear and cytoplasmic compartments separately within identified cell populations, using the same threshold across sections (standard IHC practice). Treat compartment assignments cautiously because HPA subcellular images carry an antibody cross-target warning (HPA subcellular: approved locations, cross-target caution).
Could isoforms or epitope accessibility explain discrepant MYCBP staining?
The supplied record lists 0 annotated isoforms and no transmembrane segment for MYCBP (UniProt Q99417: isoforms and topology). It also lists no glycosylation sites or modified residues, so those annotations do not identify a specific retrieval-sensitive epitope (UniProt Q99417: processing and modifications). The MYC-binding interaction uses MYCBP’s C-terminal region, but the catalog antibody’s epitope is unspecified here (UniProt Q99417: subunit; datasheet A06216-2). Compare serial sections under identical retrieval and detection conditions before attributing different staining to an isoform (standard IHC practice). If epitope identity is critical, seek direct antibody mapping or an independent specificity control before interpreting compartment differences (standard IHC practice; HPA tissue IHC: cross-target caution).
How can IF help assess an ambiguous MYCBP IHC pattern?
Use IF as a separate, validated experiment and multiplex MYCBP with a marker for the cell population being evaluated in the IHC section (standard IF practice). Choose spectrally separated fluorophores and place a strong expected signal away from prominent tissue autofluorescence, using single-stain controls to check bleed-through (standard IF practice). MYCBP has no transmembrane segment, so permeabilise sufficiently for an intracellular epitope, while checking whether the chosen conditions preserve nuclear and mitochondrial structure (UniProt Q99417: topology and subcellular location; standard IF practice). HPA reports nucleoplasmic and mitochondrial IF locations, with a warning that its antibodies target proteins from multiple genes (HPA subcellular). Compare IF compartment patterns with chromogenic IHC only after confirming each assay’s antibody specificity (standard IHC and IF practice).
What should I check when MYCBP DAB staining looks diffuse?
First inspect the no-primary control for secondary reagent binding, endogenous peroxidase, and chromogen deposition unrelated to the primary antibody (standard IHC practice). Include a peroxidase block before HRP detection and keep DAB development consistent across comparison sections (standard IHC practice). The documented paraffin-section workflow used 10% goat serum, 2 μg/ml primary antibody, an HRP-linked secondary, and DAB (datasheet A06216-2). Compare background within the same tissue compartment and around section edges before adjusting primary concentration or wash conditions (standard IHC practice). Apparent widespread cytoplasmic signal needs particular scrutiny because HPA reports general cytoplasmic staining but warns of antibody cross-targeting (HPA tissue IHC).
How should I quantify MYCBP across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, then use the same segmentation and positivity threshold for every section (standard IHC practice). Report either percentage of positive cells with intensity as an H-score, or positive-cell density per mm² of viable tissue (standard IHC practice). For glandular comparisons, normalise positive counts to the number of evaluable glandular cells; for area-based comparisons, normalise to viable tissue area (standard IHC practice). Record nuclear and cytoplasmic results separately because both locations are biologically plausible for MYCBP (UniProt Q99417: subcellular location). Exclude folds, damaged edges, and necrosis consistently, and describe antibody cross-target uncertainty when interpreting between-tissue differences (standard IHC practice; HPA tissue IHC: cross-target caution).
How do I distinguish plausible MYCBP staining from artefact?
Check whether staining follows intact cells and a plausible compartment: cytoplasm is common in tissue IHC, while nuclear localisation is condition dependent (HPA tissue IHC; UniProt Q99417: subcellular location). Glandular staining in adrenal gland or colon is a useful reference pattern, whereas adipocytes were reported as undetected in the supplied tissue profile (HPA tissue IHC). Edge-only signal, staining over necrosis, and signal in a no-primary control favor processing or detection artefact (standard IHC practice). Evaluate endogenous peroxidase with the control before assigning unexpected DAB deposits to MYCBP (standard IHC practice). Even a plausible pattern is provisional because the HPA tissue antibody carries a warning about proteins from more than one gene (HPA tissue IHC).
Boster reagents

Best MYCBP / c-Myc-binding protein IHC Antibodies

The IHC-validated anti-MYCBP antibody has real images from human paraffin sections (catalog IHC captions). Human, mouse and rat reactivity is listed, but no IF/ICC data is supplied (catalog).

Real IHC data IHC analysis of MYCBP using anti-MYCBP antibody (A06216-2). MYCBP was detected in a paraffin-embedded section of human adrenal adenomas tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-MYCBP Antibody (A06216-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-MYCBP Antibody ®
Cat # A06216-2

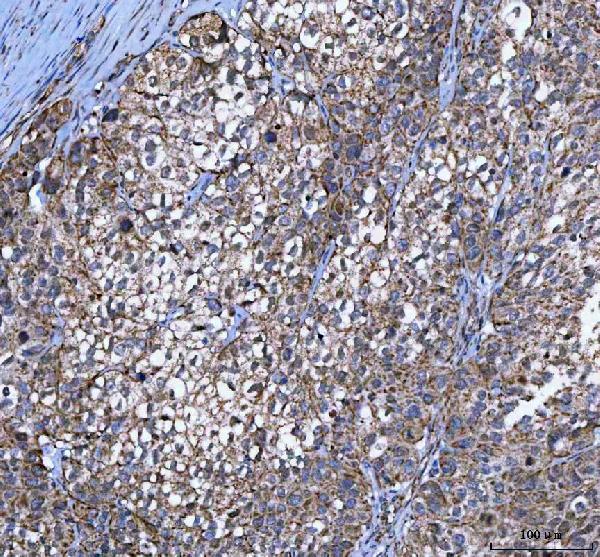
A06216-2 has IHC images from human adrenal adenoma, bladder urothelial carcinoma, placenta and testicular germ cell tumor paraffin sections (catalog IHC captions). Its listed applications include IHC and its listed reactivity covers human, mouse and rat; the payload supplies no IF/ICC image (catalog).

Which to pick: Choose A06216-2 for human paraffin-section IHC: its caption documents EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody, while the fixative is unreported (A06216-2 IHC caption). No listed SKU has IF/ICC validation, so there is no supported IF/ICC pick here (catalog applications; IF image list). A06216-2 lists mouse and rat reactivity, but its IHC images and stated IHC dilution cover human samples only; clone information is unreported (catalog).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q99417 (MYCBP_HUMAN, c-Myc-binding protein).
  2. Human Protein Atlas. MYCBP tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. MYCBP subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the mitochondria. Caution: Based on antibodies targeting proteins from multiple genes..
  4. Human Protein Atlas. MYCBP antibody validation summary (2 antibodies).
  5. SPAG5 upregulation contributes to enhanced c-MYC transcriptional activity via interaction with c-MYC binding protein in triple-negative breast cancer. Journal of hematology & oncology 2019 — PMC6367803.
  6. EYA4 inhibits hepatocellular carcinoma by repressing MYCBP by dephosphorylating β-catenin at Ser552. Cancer science 2019 — PMC6778622.
  7. Circ_0002669 promotes osteosarcoma tumorigenesis through directly binding to MYCBP and sponging miR-889-3p. Biology direct 2024 — PMC10988859.
  8. USP25-driven KIFC1 regulates MYCBP expression and promotes the progression of cervical cancer. Cell death & disease 2025 — PMC12084419.
  9. PubMed PMID:9797456 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:19054851 — UniProt-cited evidence.