MYH14 / Myosin-14 · IHC design guide

Design Immunohistochemistry for MYH14

Plan MYH14 staining in paraffin sections using the IHC-validated antibody and human colon as a positive control (datasheet A04528-3). Compare cytoplasmic and membranous staining with the tissue and cell patterns reported for MYH14 (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for MYH14 (IHC for MYH14): expected localisation General cytoplasmic and membranous staining (HPA tissue IHC), antibody A04528-3, validated IHC image, and IHC protocol steps
Printable MYH14 IHC protocol sheet — expected localisation General cytoplasmic and membranous staining (HPA tissue IHC), antibody A04528-3, controls and protocol steps. Open the full MYH14 IHC guide →

MYH14 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic and membranous staining (HPA tissue IHC)
Staining pattern Glandular cells show cytoplasmic and membranous staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04528-3)
Positive control ⓘ Bronchus+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A04528-3)
Caveat Kidney expression is high, but tubular staining is low (UniProt; HPA tissue IHC)
Regulation Expression varies by tissue (UniProt)
Isoform / epitope 5 isoforms; epitope coverage needs verification (UniProt)
Section 1

Recommended MYH14 IHC & IF Protocols

The catalog antibody has an IHC-P protocol (datasheet: A04528-3). The published mouse kidney paraffin-section protocol uses fluorescent detection (PMC5727274).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon tissue; fixative not specified (datasheet A04528-3)
FixationImage fixative and duration unreported (datasheet A04528-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04528-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04528-3)
Primary antibodyRabbit anti-MYH14, 2-5 μg/ml (datasheet A04528-3)
Primary incubationOvernight at 4 °C (datasheet A04528-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A04528-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultMYH14-positive staining in respiratory epithelial cells of bronchus (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic and membranous expression, most abundant in gastrointestinal mucosa. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA at pH 8.0 for the catalog antibody (datasheet: A04528-3). The published kidney protocol used Triology retrieval (PMC5727274).
Section 2

What Is the Expected MYH14 Staining Pattern?

For paraffin-section IHC, expect MYH14 mainly in the cytoplasm and along cell borders, especially in gastrointestinal glandular cells and respiratory epithelium (HPA: tissue IHC). The protein has no transmembrane segment, so border staining does not establish membrane insertion (UniProt Q7Z406 topology). HPA rates the tissue profile Enhanced, with medium consistency between staining and RNA data and external verification pending (HPA: tissue IHC reliability).

What am I looking at on my slide?
Strong cytoplasmic and cell-border staining in colon, duodenum, rectum, or small-intestinal glandular cells.This matches the most abundant gastrointestinal pattern; score the named cells and their compartment, rather than treating every cell in the section as positive (HPA: tissue IHC).
Predominantly nuclear staining in a paraffin-section IHC positive control.Recheck the IHC result against cytoplasmic and membranous tissue staining before accepting it (HPA: tissue IHC). Nuclear staining cannot simply be dismissed as impossible: a separate ICC-IF antibody shows approved nucleoplasmic localisation (HPA: subcellular ICC-IF).
Strong staining of adipocytes, marrow hematopoietic cells, or lymph-node germinal-center cells.These named cell populations were not detected in HPA tissue IHC. Check for nonspecific antibody binding or endogenous detection activity before calling them MYH14 positive; the reference is cell-specific, not a whole-tissue negative claim (HPA: tissue IHC; general IHC practice).
Uniform colour over tissue and blank regions, obscuring cell boundaries.This does not resolve the reported cell-specific pattern. Assess background with an appropriate negative control, then review blocking, washing, antibody concentration, and chromogen development (HPA: tissue IHC; general IHC practice).
No staining in gastrointestinal glandular cells on the same run.First investigate the IHC run, because HPA reports High staining in these cells. Review tissue preservation, retrieval and detection conditions, and a known-positive control before interpreting an experimental specimen as negative (HPA: tissue IHC; general IHC practice).
💡Expected MYH14 appearanceCall a paraffin-section result consistent when gastrointestinal glandular cells show strong cytoplasmic and cell-border staining; colour confined to blank regions or unexpectedly strong in HPA-negative cell populations raises concern for a false positive (HPA: tissue IHC; general IHC practice).
How each factor affects the staining
Which compartment should guide IHC interpretation?HPA describes general cytoplasmic and membranous tissue staining. UniProt lists no transmembrane segment; border staining alone cannot establish membrane insertion (HPA: tissue IHC; UniProt Q7Z406 topology).
How strong is the tissue-pattern evidence?The HPA tissue profile is Enhanced, but its stated antibody-to-RNA consistency is medium and external verification is pending. HPA067889 has Enhanced IHC validation; HPA070260 has Approved IHC validation (HPA: tissue IHC; HPA: antibodies).
Do all MYH14 isoforms stain equally?UniProt lists five isoforms. The supplied record does not map these antibodies' epitopes to isoforms, so equal recognition cannot be inferred from a positive section (UniProt Q7Z406 isoforms; HPA: antibodies).
What should IF/ICC show?HPA reports approved nucleoplasmic ICC-IF localisation, with images from MCF-7, RT-4 and U2OS. That observation comes from an ICC-approved antibody and should be interpreted on its own guide page (HPA: subcellular ICC-IF; HPA: antibodies).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected gastrointestinal glands are faint or blank.A run-level staining problem is possible when a reported High cell population has no visible signal (HPA: tissue IHC; general IHC practice).Check a known-positive section and detection controls; review the antibody's IHC-P instructions and the run's retrieval, dilution, and chromogen steps. No MYH14-specific retrieval or fixation effect is established here (general IHC practice).
Only kidney tubules or other modestly stained cells are being used as the positive control.HPA lists kidney tubular cells as Low, making a weak result harder to judge than in High gastrointestinal glandular cells (HPA: tissue IHC).Use a section containing a reported High population, such as colon glandular cells, to assess whether the IHC run can show the expected pattern (HPA: tissue IHC; general IHC practice).
Brown signal appears broadly in HPA-negative cell populations.Nonspecific binding or endogenous detection activity can mimic staining in chromogenic IHC (general IHC practice).Compare with a no-primary control, assess endogenous enzyme blocking when relevant, and inspect whether signal remains restricted to defined cells (general IHC practice).
Tissue and blank areas both carry diffuse colour.Background may reflect inadequate washing, excessive antibody or detection reagent, or overdevelopment (general IHC practice).Use the negative control to identify the background source, then adjust washing, reagent concentration, or development according to the IHC reagents used (general IHC practice).
A nuclear signal is interpreted as proof that the tissue IHC pattern is wrong.The tissue IHC and ICC-IF localisation summaries differ, and their antibody validations are application-specific (HPA: tissue IHC; HPA: subcellular ICC-IF; HPA: antibodies).Judge paraffin IHC against its cytoplasmic and membranous tissue reference. Treat the approved nucleoplasmic ICC-IF observation as a separate application result (HPA: tissue IHC; HPA: subcellular ICC-IF).

Sample controls for MYH14 IHC & IF

🧪Run colon first: glandular cells should stain for MYH14 (HPA: High in colon glandular cells). Run adipose tissue as the negative comparator (HPA: Not detected in adipocytes); on the colon slide, use cells outside the glandular compartment as an internal background reference only if they show no specific staining.
Positive control tissue: Bronchus (Respiratory epithelial cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show MYH14 in MCF-7, RT-4, U2OS, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control (caption: rabbit anti-MYH14 primary). If available, use a MYH14 knockout specimen or an antigen-peptide block as a biological specificity control; quench endogenous peroxidase and check for nonspecific DAB signal in colon sections (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A04528-3 colon caption does not state a fixative (caption: fixative unreported). The reported paraffin-section procedure uses heat-mediated EDTA retrieval at pH 8.0; whether retrieval is required under other conditions is unreported (caption: EDTA retrieval). The evidence does not establish whether frozen sections or IF are easier; assess possible colonic endogenous peroxidase background with the no-primary control (standard IHC practice).

HPA tissue IHC evidence for MYH14

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Lung Alveolar cells High Protein (IHC) HPA →
Nasopharynx Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebral cortex Endothelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced MYH14 IHC Tips

Troubleshoot MYH14 staining in paraffin sections by checking retrieval, compartment, cell type, and controls before comparing signal intensity.

Which retrieval conditions should I try first for weak MYH14 staining?
Start with heat-mediated retrieval in EDTA at pH 8.0 for the catalog antibody (datasheet A04528-3). The selected paraffin-section image used that retrieval before overnight incubation with 2 μg/ml primary antibody at 4°C (caption A04528-3). If signal is weak, compare retrieved and unretrieved serial sections while holding antibody concentration, detection, and imaging conditions constant (standard IHC practice). Include colon glandular cells as a positive tissue reference, but score their staining separately from other cells because expression varies by cell type (HPA: High in colon glandular cells).
Could fixation explain weak or patchy MYH14 staining?
Target-specific fixation sensitivity is unknown because the selected paraffin-section caption does not state its fixative (caption A04528-3). Record the fixative, fixation duration, section thickness, and processing history for each block, then compare sections processed together before attributing differences to MYH14 abundance (standard IHC practice). Use the documented EDTA retrieval at pH 8.0 and a matched antibody concentration when comparing blocks (datasheet A04528-3; standard IHC practice). If staining remains patchy, inspect morphology and compare a positive reference section in the same run; neither tissue-expression patterns nor predicted protein features establish a MYH14-specific fixation effect (standard IHC practice).
Should MYH14 staining appear in cytoplasm, membranes, or nuclei?
Assess compartment and cell type together: tissue IHC describes general cytoplasmic and membranous staining, especially in gastrointestinal mucosa (HPA: tissue IHC profile). Cell-based ICC/IF instead lists nucleoplasm as its approved location, so a nuclear signal in a paraffin section warrants confirmation with controls and an independently assessed antibody (HPA: subcellular). MYH14 has no annotated transmembrane segment, and UniProt provides no subcellular-location annotation (UniProt Q7Z406: topology and subcellular record). In colon, compare glandular cells with adjacent cells on the same section and document whether staining is diffuse, peripheral, or nuclear before assigning a MYH14-specific pattern (HPA: High in colon glandular cells; standard IHC practice).
Can this antibody distinguish MYH14 isoforms or modified epitopes?
Do not assign an isoform from staining intensity alone: the record lists 5 MYH14 isoforms, while the selected caption does not specify the antibody epitope (UniProt Q7Z406: isoforms; caption A04528-3). MYH14 contains a motor domain at residues 105–800 and an IQ region at 803–832, but those coordinates do not identify this antibody’s binding site (UniProt Q7Z406: domains). Document the antibody’s mapped immunogen or epitope, if available, before comparing splice variants or predicting retrieval behavior (standard IHC practice). The recorded phosphorylation sites include residues 60 and 1980; their presence alone does not establish modification-sensitive staining (UniProt Q7Z406: modified residues).
How should I check a MYH14 pattern by multiplex IF?
Use IF as a separate validation experiment while interpreting this page’s paraffin-section chromogenic results; the selected caption documents IHC detection with DAB, not IF performance (caption A04528-3). Pair MYH14 with an epithelial lineage marker to identify glandular cells, which show high tissue IHC staining in colon, and include single-label controls for channel separation (HPA: High in colon glandular cells; standard IF practice). Choose a far-red fluorophore when tissue autofluorescence obscures shorter wavelengths, and inspect unstained tissue in every channel (standard IF practice). If testing an intracellular epitope, titrate permeabilisation and compare nuclear and cytoplasmic signal; the antibody’s epitope is unspecified, while MYH14 lacks a transmembrane segment (caption A04528-3; UniProt Q7Z406: topology; standard IF practice).
What should I adjust when DAB background obscures MYH14 staining?
First compare a no-primary control with the stained section to separate detection background from primary-antibody-associated signal (standard IHC practice). The selected colon image used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and a peroxidase-conjugated secondary for 30 minutes at 37°C (caption A04528-3). Apply an endogenous-peroxidase block, control DAB development time, and check wash steps as general chromogenic IHC measures (standard IHC practice). If background persists, titrate the primary antibody around the documented concentration and judge each condition against morphology and colon glandular-cell staining (caption A04528-3; HPA: High in colon glandular cells; standard IHC practice).
How can I quantify MYH14 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the compartment and cell population before scoring, since tissue IHC describes cytoplasmic and membranous expression and reports high staining in colon glandular cells (HPA: tissue IHC profile; HPA: High in colon glandular cells). For glandular-cell staining, report an H-score from 0–300 or the percentage of positive cells, using the same thresholds and DAB development conditions across sections (standard IHC practice). Normalise counts to the number of eligible glandular cells; for spatial density, report positive cells per mm² of viable, annotated tissue (standard IHC practice). Exclude folds, damaged edges, and necrotic regions from both numerator and denominator, and record whether nuclear signal was scored separately (standard IHC practice).
How do I distinguish genuine MYH14 staining from artefact?
Look for reproducible staining in the expected cell population: colon glandular cells are reported High, whereas adipocytes are Not detected in the tissue IHC reference (HPA: colon glandular cells; HPA: adipocytes). Treat a nuclear-only paraffin-section pattern cautiously because tissue IHC describes cytoplasmic and membranous expression, although cell-based ICC/IF lists nucleoplasm as an approved location (HPA: tissue IHC profile; HPA: subcellular). Signal confined to section edges, folds, or necrotic areas should prompt a morphology and processing check, while staining in a no-primary control suggests detection background (standard IHC practice). Use a same-run positive reference and an independently assessed antibody before interpreting an unexpected compartment or cell population as MYH14 (standard IHC practice).
Boster reagents

Best MYH14 / Myosin-14 IHC Antibodies

The IHC-validated anti-MYH14 antibody has real paraffin-section IHC data from human colon and colon cancer tissue (catalog IHC captions). Human, mouse and rat reactivity is listed (catalog applications/reactivity).

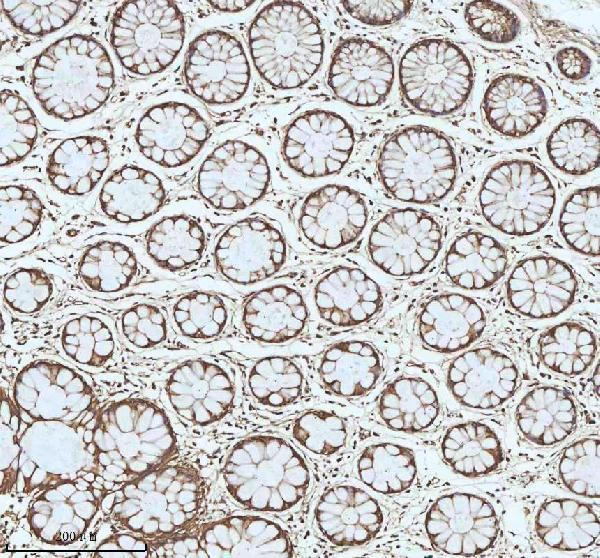
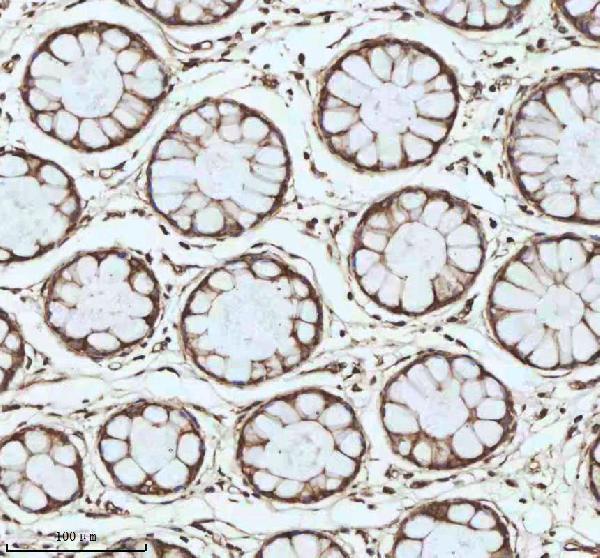
Real IHC data IHC analysis of MYH14 using anti-MYH14 antibody (A04528-3). MYH14 was detected in a paraffin-embedded section of human colon tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-MYH14 Antibody (A04528-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-MYH14 Antibody ®
Cat # A04528-3

A04528-3 is listed for IHC in human, mouse and rat samples (catalog applications/reactivity). Its IHC images show paraffin sections of human colon and colon cancer; no IF images are provided (catalog image captions).

Which to pick: Choose A04528-3 for chromogenic IHC on paraffin sections: its human colon images document EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody (A04528-3 IHC captions). The fixative is unreported (A04528-3 IHC captions). For IF/ICC, no validated SKU is listed (catalog applications/images); for mouse or rat IHC, A04528-3 lists reactivity, while its shown IHC data are human only (catalog applications/reactivity; A04528-3 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q7Z406 (MYH14_HUMAN, Myosin-14).
  2. Human Protein Atlas. MYH14 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. MYH14 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. MYH14 antibody validation summary (3 antibodies).
  5. The ESR1-MYH14 axis functions as a critical driver of cervical cancer progression and metastasis. Translational oncology 2026 — PMC13316688.
  6. Nonmuscle myosin 2 proteins encoded by Myh9, Myh10, and Myh14 are uniquely distributed in the tubular segments of murine kidney. Physiological reports 2017 — PMC5727274.
  7. Two novel/ancient myosins in mammalian skeletal muscles: MYH14/7b and MYH15 are expressed in extraocular muscles and muscle spindles. The Journal of physiology 2010 — PMC2821527.
  8. PubMed PMID:12909352 — UniProt-cited evidence.
  9. PubMed PMID:15057824 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.