NCF2 / Neutrophil cytosol factor 2 · IHC design guide

Design Immunohistochemistry for NCF2

Plan NCF2 paraffin-section IHC around expected cytoplasmic localization (UniProt) and staining in neutrophils and macrophages (HPA tissue IHC). Use the catalog antibody’s human tonsil example at 1 μg/ml (datasheet A02476-1), and control for endogenous peroxidase during DAB detection (standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NCF2 (IHC for NCF2): expected localisation Cytoplasm expected; tissue IHC compartment unresolved (UniProt; HPA tissue IHC), antibody A02476-1, validated IHC image, and IHC protocol steps
Printable NCF2 IHC protocol sheet — expected localisation Cytoplasm expected; tissue IHC compartment unresolved (UniProt; HPA tissue IHC), antibody A02476-1, controls and protocol steps. Open the full NCF2 IHC guide →

NCF2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasm expected; tissue IHC compartment unresolved (UniProt; HPA tissue IHC)
Staining pattern Neutrophils/macrophages: cytoplasmic signal expected (HPA tissue IHC; UniProt)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02476-1)
Positive control ⓘ Bone marrow+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A02476-1)
Caveat Endogenous peroxidase may confound DAB in marrow (HPA tissue IHC; standard IHC practice)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope 4 isoforms; epitope coverage cannot be resolved here (UniProt)
Section 1

Recommended NCF2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A02476-1) is followed by published NCF2 staining protocols for GBM, colon and rectal tissue, and HCC (PMC12936047; PMC12684989; PMC10134316).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human tonsil tissue; fixative not specified (datasheet A02476-1)
FixationImage fixative and duration unreported (datasheet A02476-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02476-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02476-1)
Primary antibodyRabbit anti-NCF2, 0.5-1μg/ml (datasheet A02476-1)
Primary incubationOvernight at 4 °C (datasheet A02476-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02476-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNCF2-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: High). HPA tissue profile: High expression in neutrophils and macrophages. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet A02476-1). Citrate at pH 6.0 is a published alternative for GBM sections (PMC12936047).
Section 2

What Is the Expected NCF2 Staining Pattern?

NCF2 should appear predominantly cytoplasmic in positive cells: UniProt places it in the cytoplasm and reports no transmembrane segment (UniProt P19878); HPA supports a cytosolic location (HPA: Cytosol, supported). Expect staining especially in neutrophils and macrophages (HPA: High expression). HPA rates tissue IHC reliability Enhanced, with medium consistency between staining and RNA data (HPA: tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining in inflammatory cells, including lung macrophages.This fits NCF2 localisation (UniProt P19878; HPA: Cytosol, supported). Lung macrophage staining is Medium in the HPA tissue IHC record; intensity need not match every positive tissue (HPA: Lung, macrophages, Medium).
Strong staining in bone marrow hematopoietic cells or splenic red-pulp cells.Both are High in HPA tissue IHC (HPA: Bone marrow, hematopoietic cells, High; Spleen, red-pulp cells, High). Assess which cells stain before calling an entire section uniformly positive.
Predominantly nuclear staining, or a sharp membrane-only outline in otherwise positive cells.This conflicts with the reported cytoplasmic and cytosolic locations (UniProt P19878; HPA: Cytosol, supported). Check morphology and controls, then consider staining artefact or antibody specificity before assigning NCF2 localisation.
Prominent signal in adipocytes or bronchial respiratory epithelium.Those cell types are Not detected in the listed HPA tissue IHC observations (HPA: Adipose tissue, adipocytes; Bronchus, respiratory epithelial cells). Review cell identification and controls; cross-reactivity or endogenous detection activity may explain discordant signal (general IHC practice).
Diffuse colour across cells and extracellular space, or no signal in a known-positive control.Diffuse deposition makes cell-specific localisation difficult to score (general IHC practice). An absent control signal prevents a negative test section from being interpreted confidently; check staining-run controls and detection steps (general IHC practice).
💡Expected NCF2 appearanceCall a result positive when appropriate cells show mainly cytoplasmic staining, with strong staining possible in bone marrow hematopoietic cells and medium staining in lung macrophages (HPA: tissue IHC; HPA: Cytosol, supported); dominant nuclear or broad cell-independent colour is suspect (general IHC practice).
How each factor affects the staining
Cell composition of the sectionHPA reports High expression in neutrophils and macrophages, while named tissue entries refer to specific cell populations (HPA: tissue IHC). Interpret the stained cells rather than treating a whole tissue as uniformly positive.
Location during oxidase assemblyNCF2 participates in a cytosolic regulatory complex that assembles with a membrane oxidase core upon activation (UniProt P19878). The reference location remains cytoplasmic/cytosolic; assembly alone does not establish a membrane-only IHC pattern.
Antibody evidenceThree listed antibodies have Enhanced IHC validation (HPA: HPA002327, HPA006040, CAB022160). That supports the reported tissue pattern but does not verify specificity for every specimen or staining condition (general IHC practice).
Isoforms and epitope uncertaintyUniProt lists 4 NCF2 isoforms and SH3 and PB1 domains (UniProt P19878). No epitope location is supplied here, so isoform coverage and domain-dependent staining cannot be inferred.
Phosphorylation and processingUniProt lists phosphothreonine 233 and phosphoserine 399, with no signal peptide or propeptide and one chain spanning residues 1–526 (UniProt P19878). These annotations do not establish a staining change under IHC conditions.
Chromogenic detectionEndogenous enzyme activity or nonspecific colour deposition can imitate cellular signal in chromogenic IHC (general IHC practice). Use suitable detection controls and assess whether colour follows plausible cell boundaries and cytoplasmic localisation.
IF/ICC Q&A: what location is expected?Predominantly cytosolic signal is the supported IF/ICC expectation (HPA: Cytosol, supported). HPA lists ICC-IF images in A-431, U-251MG and U2OS, but that record supplies no IF protocol here (HPA: subcellular).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in a bone marrow positive-control section.Bone marrow hematopoietic cells are High in HPA tissue IHC, so an entirely blank control raises a staining-run question (HPA: Bone marrow, hematopoietic cells, High; general IHC practice).Check that hematopoietic cells are present, then review primary-antibody application, detection reagents and control performance before interpreting test negatives (general IHC practice).
Lung macrophages stain less strongly than bone marrow cells.HPA records lung macrophages as Medium and bone marrow hematopoietic cells as High (HPA: tissue IHC). Different expected levels can produce different apparent intensities.Score the identifiable positive cell population and its cytoplasmic distribution within each tissue; retain a suitable positive control for the staining run (HPA: tissue IHC; general IHC practice).
Colour appears mainly in nuclei or as continuous membrane outlines.That distribution disagrees with NCF2 cytoplasm and supported cytosol localisation (UniProt P19878; HPA: Cytosol, supported). Background or off-target binding is possible (general IHC practice).Review the counterstain and cell boundaries, compare control sections, and verify that the primary antibody produces a plausible cytoplasmic pattern (general IHC practice).
Adipocytes or bronchial respiratory epithelial cells stain strongly.HPA lists these cell types as Not detected (HPA: Adipose tissue, adipocytes; Bronchus, respiratory epithelial cells). Misidentified cells or nonspecific detection could account for the discrepancy (general IHC practice).Recheck cell identity and compare a control lacking primary antibody; assess endogenous detection activity before assigning that colour to NCF2 (general IHC practice).
Diffuse colour obscures which cells are positive.Broad background can arise from nonspecific reagent binding or excess chromogenic deposition (general IHC practice). It cannot establish the cell-restricted HPA pattern (HPA: tissue IHC).Compare a control lacking primary antibody; review blocking, washes, antibody dilution and development time as general IHC variables, then rescore only clearly localised cellular signal (general IHC practice).
A negative test section is being called NCF2-negative after the positive control also failed.A failed positive control leaves assay performance unresolved (general IHC practice). The expected positive populations include bone marrow hematopoietic cells and splenic red-pulp cells (HPA: tissue IHC).Restore a positive-control signal and repeat the affected staining run before making a negative call; document the cell population and cytoplasmic pattern used for scoring (general IHC practice; HPA: Cytosol, supported).

Sample controls for NCF2 IHC & IF

🧪Run bone marrow first and look for staining in hematopoietic cells (HPA: High in bone marrow hematopoietic cells). Use adipose tissue adipocytes as the negative tissue (HPA: Not detected in adipocytes); nonhematopoietic cells on the bone marrow slide should show background-level staining, but require independent validation before treating them as a confirmed negative population.
Positive control tissue: Bone marrow (Hematopoietic cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
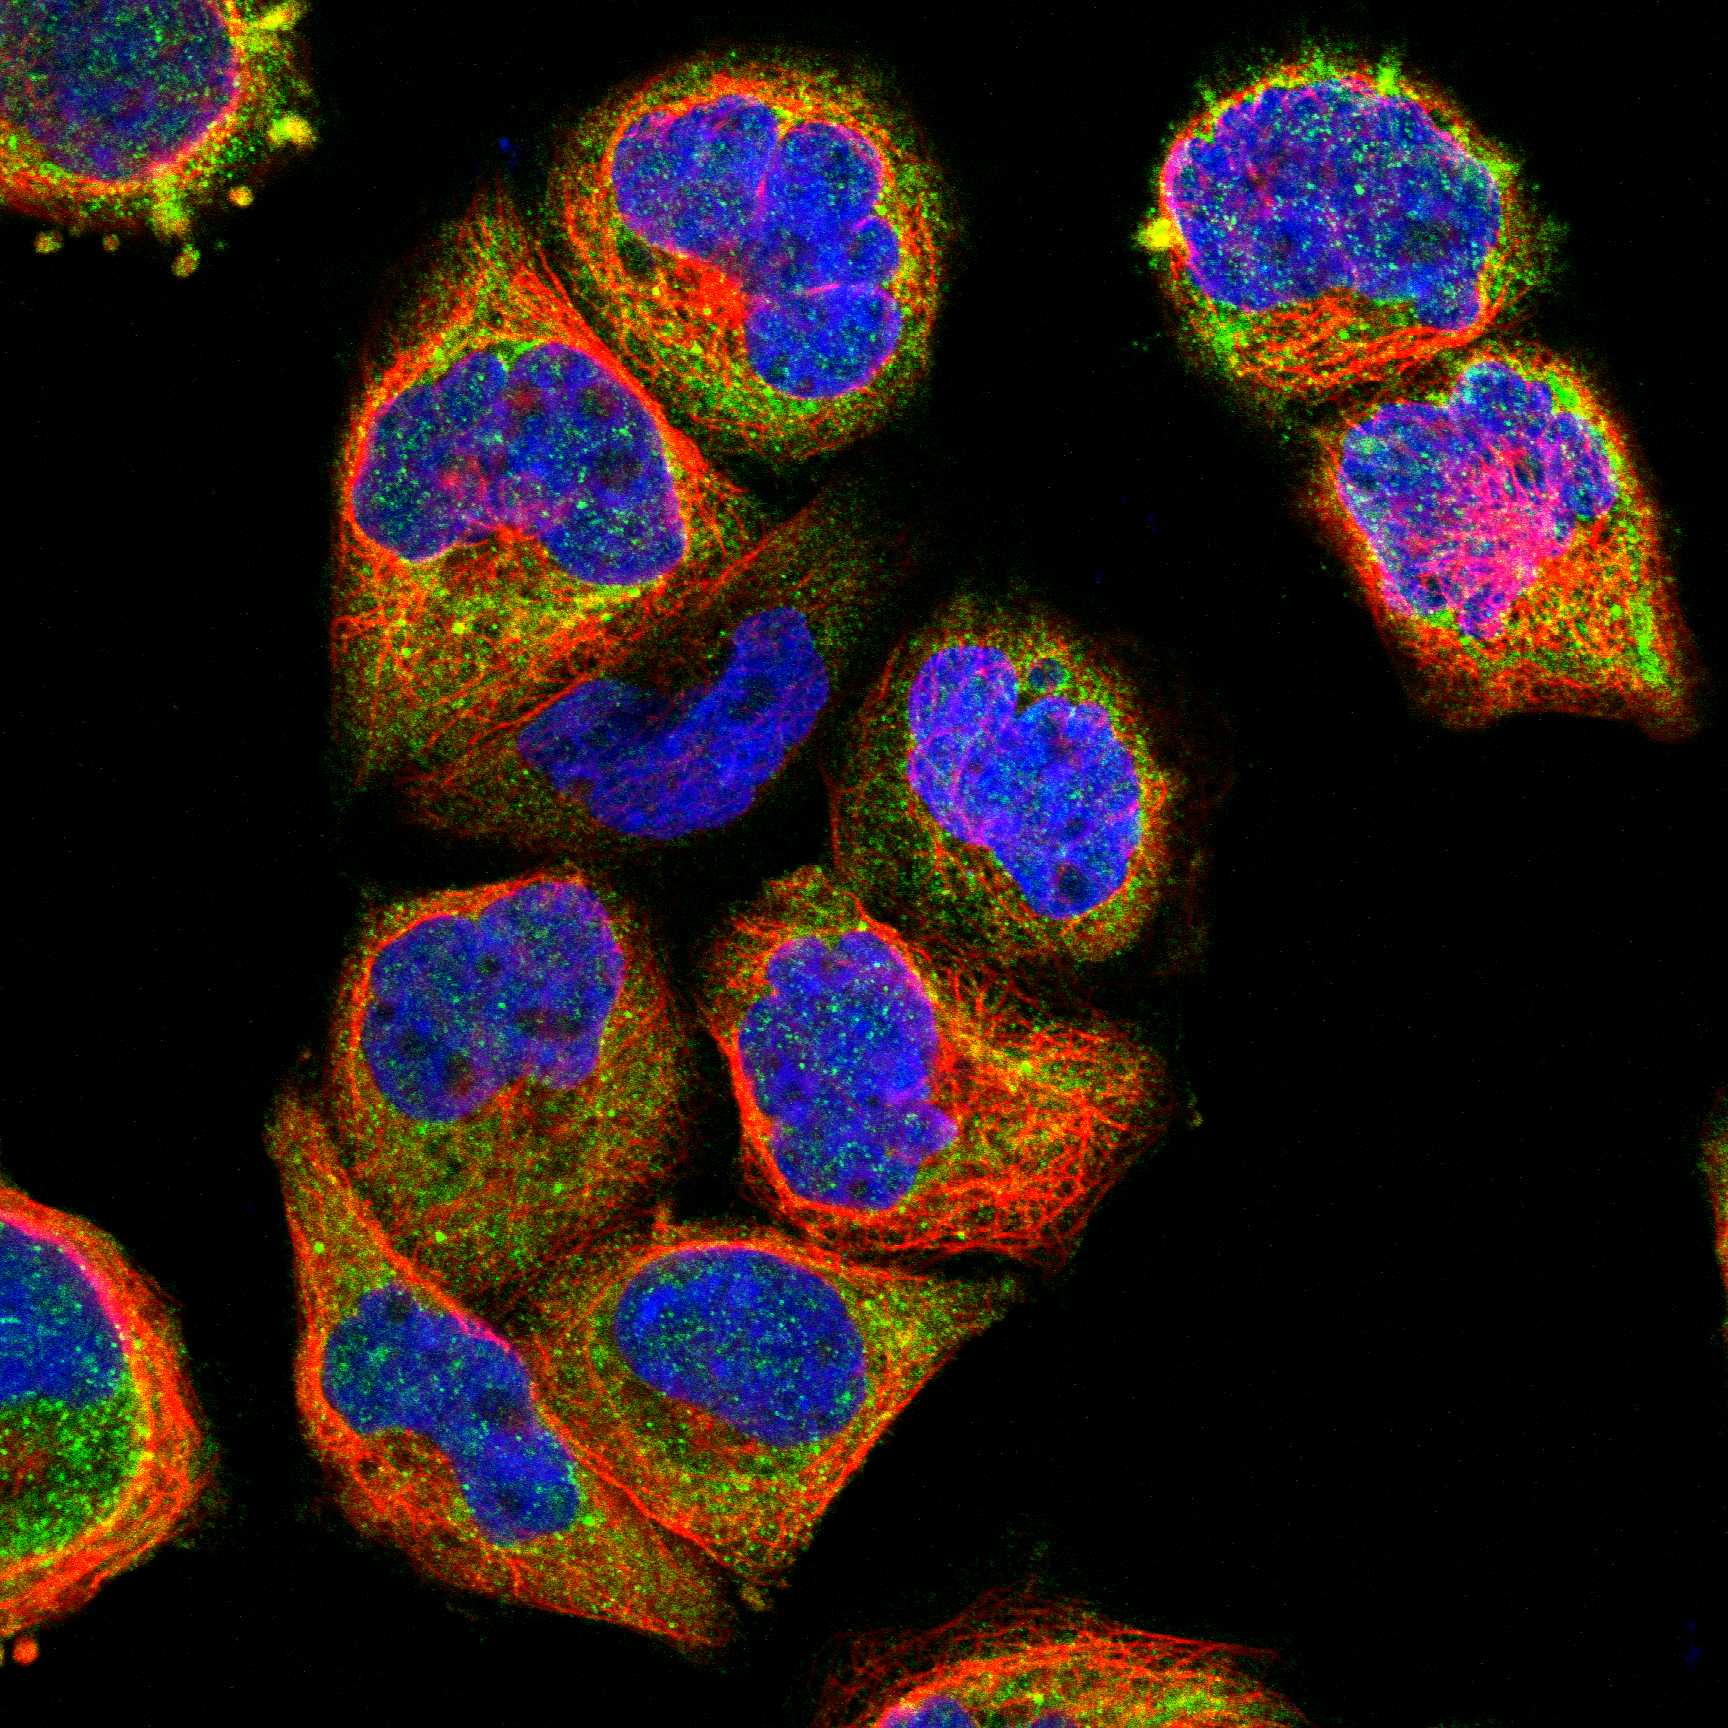
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show NCF2 in A-431, U-251MG, U2OS, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, host- and clonality-matched rabbit IgG isotype control, and an NCF2-knockout biological negative where available (caption: rabbit primary antibody; standard IHC control practice). Check endogenous peroxidase and biotin background in bone marrow because the selected IHC example uses biotin-based detection with DAB (caption: SABC with DAB; standard IHC control practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected paraffin-section caption does not state the fixative (caption: fixative unreported). The demonstrated IHC conditions use heat retrieval in EDTA at pH 8.0; whether retrieval is essential, or whether frozen sections or IF are easier, is unreported (caption: EDTA heat retrieval; HPA: cytosolic ICC-IF signal). In bone marrow, endogenous peroxidase or biotin can complicate chromogenic interpretation, so assess those backgrounds with the technical controls (standard IHC practice).

HPA tissue IHC evidence for NCF2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Endometrium Endothelial cells High Protein (IHC) HPA →
Spleen Cells in red pulp High Protein (IHC) HPA →
Lung Macrophages Medium Protein (IHC) HPA →
Lymph node Non-germinal center cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced NCF2 IHC Tips

Use cell type, cytosolic localisation and matched controls to troubleshoot NCF2 staining in paraffin sections (HPA tissue IHC; HPA subcellular; UniProt P19878 localisation).

What retrieval should I try when NCF2 staining is weak in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 (datasheet A02476-1). The catalog antibody's paraffin-section image used that condition before incubation at 1 µg/mL overnight at 4°C (caption A02476-1). If staining is weak, check that the section was fully dewaxed and that retrieval temperature, heating time and cooling were consistent across slides (standard IHC practice). Compare a retrieval time series using adjacent sections and the same detection settings, while watching for tissue loss or excessive background (standard IHC practice). Judge improvement in expected neutrophil or macrophage populations rather than by overall brown intensity (HPA tissue IHC profile; standard IHC practice).
Could fixation explain weak or patchy NCF2 staining?
Target-specific sensitivity to fixation is unknown from the supplied evidence; the catalog image identifies a paraffin section but does not report its fixative (caption A02476-1). Record the fixative and fixation duration for each specimen, then compare sections processed with the same retrieval, antibody incubation and detection conditions (standard IHC practice). For prospective samples, assess fixation conditions with matched tissue and a consistent processing schedule before attributing a staining difference to NCF2 abundance (standard IHC practice). Do not infer fixation tolerance from NCF2's cytoplasmic localisation or phosphorylation sites (UniProt P19878 localisation and modified residues). Review morphology and staining in expected myeloid cells alongside the processing record (HPA tissue IHC profile; standard IHC practice).
How should I evaluate punctate or membrane-adjacent NCF2 staining?
Expect predominantly cytoplasmic staining: NCF2 is annotated in the cytoplasm, and its supported subcellular location is the cytosol (UniProt P19878 localisation; HPA subcellular). It has no transmembrane segment, so an exclusively membrane-bound pattern merits scrutiny (UniProt P19878 topology). Activation assembles cytosolic oxidase subunits with the complex at the plasma or phagosomal membrane, making some membrane-adjacent signal biologically plausible (UniProt P19878 function). Examine high magnification fields to distinguish cytoplasmic granularity from precipitated chromogen, and compare serial sections with a no-primary control (standard IHC practice). Score cell type and compartment separately rather than treating every brown punctum as NCF2 (HPA tissue IHC profile; standard IHC practice).
Could NCF2 isoforms or epitope accessibility change the staining pattern?
NCF2 has four annotated isoforms, but the supplied product caption does not identify the antibody epitope (UniProt P19878 isoforms; caption A02476-1). Its SH3 domains span residues 240–299 and 457–516, and its PB1 domain spans 351–429; these locations alone do not establish antibody recognition (UniProt P19878 domains). Phosphothreonine 233 and phosphoserine 399 are annotated modifications, but no supplied evidence links either to this antibody's staining (UniProt P19878 modified residues; caption A02476-1). If specimens differ unexpectedly, check the antibody's documented immunogen or epitope before proposing an isoform explanation (standard antibody validation practice). Use matched retrieval and controls when comparing specimens so processing differences do not masquerade as epitope effects (standard IHC practice).
How can IF help resolve ambiguous NCF2 staining in tissue?
On a separate IF section, multiplex NCF2 with a validated neutrophil or macrophage marker to test whether signal belongs to an expected cell population (HPA tissue IHC profile; standard IF practice). Choose spectrally separated fluorophores and consider a far-red channel for the weaker signal after checking tissue autofluorescence in an unstained control (standard IF practice). Use a permeabilisation condition suitable for a cytosolic epitope, since NCF2 is cytosolic and lacks a transmembrane segment (HPA subcellular; UniProt P19878 topology; standard IF practice). Include single-label and no-primary controls to assess bleed-through and background (standard IF practice). Interpret IF as a localisation cross-check for chromogenic IHC, with antibody performance assessed in each application (standard antibody validation practice).
What should I change when NCF2 DAB staining is diffuse or widespread?
First compare the test section with a no-primary control and inspect whether brown signal follows tissue edges, folds or damaged areas (standard IHC practice). The catalog image used 10% goat serum blocking, 1 µg/mL primary antibody and overnight incubation at 4°C (caption A02476-1). If background persists, titrate primary antibody and detection exposure on adjacent sections while keeping retrieval at EDTA pH 8.0 initially (datasheet A02476-1; standard IHC practice). Apply an endogenous peroxidase block and control DAB development time as general chromogenic workflow steps (standard IHC practice). Compare the resulting pattern with expected myeloid staining before calling diffuse colour NCF2 positive (HPA tissue IHC profile; standard IHC practice).
How should I score NCF2 when myeloid cell abundance varies between sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the compartment and cell population before scoring, using cytoplasmic signal in morphologically identified cells as the readout (HPA subcellular; standard IHC practice). Report either an H-score from staining intensity and percentage of positive cells, or the percentage of positive cells within a defined population (standard IHC quantification practice). If spatial recruitment is the question, report positive-cell density per mm² of analysed viable tissue and state the region-selection rule (standard IHC quantification practice). Normalise cellular staining to the number of eligible cells, and density to analysed tissue area; document exclusions for folds and necrosis (standard IHC practice). Stratify relevant myeloid populations where possible because NCF2 is high in neutrophils and macrophages (HPA tissue IHC profile).
How do I distinguish true NCF2 positivity from IHC artefact?
Give greatest weight to cytoplasmic staining in expected neutrophils or macrophages, supported by appropriate positive and negative controls (HPA tissue IHC profile; HPA subcellular; standard IHC practice). An exclusively nuclear pattern is inconsistent with the supplied cytosolic localisation, while a strictly membrane-only pattern needs corroboration despite NCF2's role in oxidase assembly (HPA subcellular; UniProt P19878 function and topology). Discount colour concentrated at section edges, folds or necrotic regions, and investigate any staining retained in the no-primary control (standard IHC practice). Check endogenous peroxidase activity when interpreting DAB signal (standard IHC practice). Treat an unexpected cell type cautiously: HPA reports enhanced tissue-IHC reliability with medium RNA–staining consistency (HPA tissue IHC reliability).
Boster reagents

Best NCF2 / Neutrophil cytosol factor 2 IHC Antibodies

Both anti-NCF2 antibodies have paraffin-section IHC images from human tissue (catalog IHC captions); A02476-1 also has mouse and rat spleen images (catalog IHC captions), while M02476-1 lists ICC/IF without an IF figure (catalog applications/images).

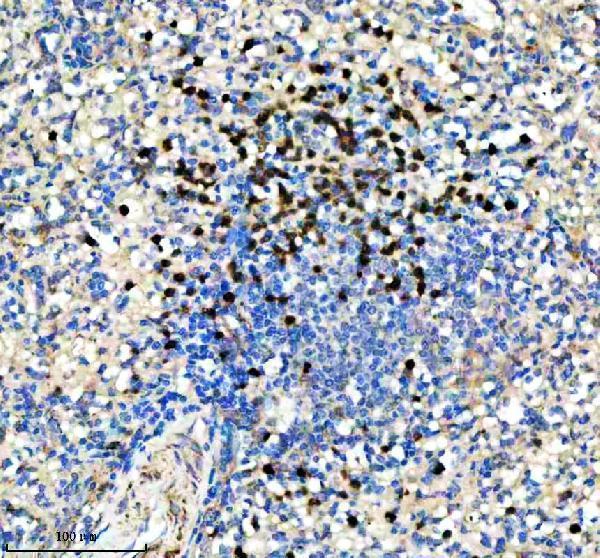
Real IHC data IHC analysis of NOXA2/p67phox/NCF2 using anti-NOXA2/p67phox/NCF2 antibody (A02476-1). NOXA2/p67phox/NCF2 was detected in paraffin-embedded section of human tonsil tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-NOXA2/p67phox/NCF2 Antibody (A02476-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-NOXA2/p67phox/NCF2 Antibody ®
Cat # A02476-1
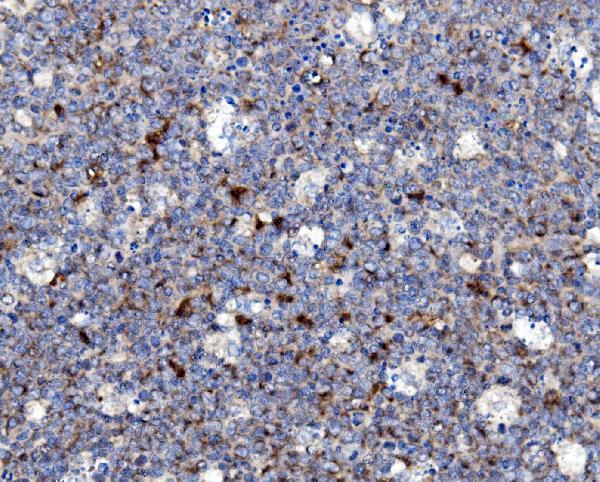
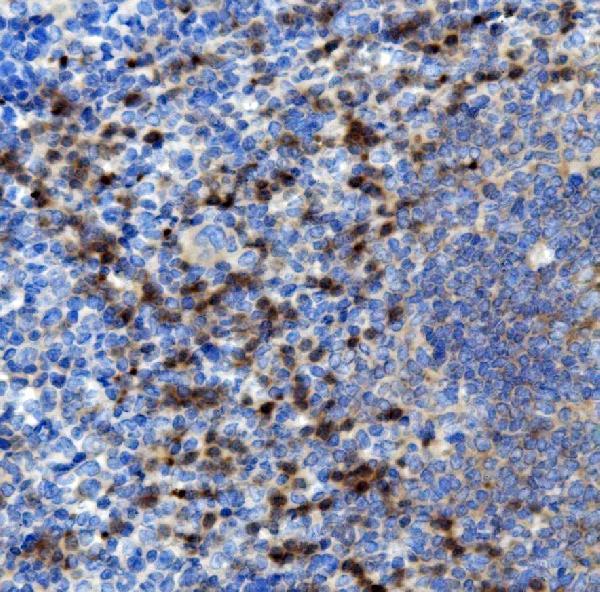
Real IHC data Figure 2. IHC analysis of NOXA2/p67phox/NCF2 using anti-NOXA2/p67phox/NCF2 antibody (M02476-1). NOXA2/p67phox/NCF2 was detected in a paraffin-embedded section of human spleen tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with a dilution of 1:100 rabbit anti-NOXA2/p67phox/NCF2 Antibody (M02476-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-NOXA2/p67phox Rabbit Monoclonal Antibody
Cat # M02476-1

A02476-1 lists IHC for human, mouse and rat, with images from human tonsil and mouse and rat spleen (catalog applications/reactivity; A02476-1 IHC captions). M02476-1 lists IHC and ICC/IF for human, mouse and rat, with IHC images from human spleen and tonsil (catalog applications/reactivity; M02476-1 IHC captions).

Which to pick: For tissue IHC across species, choose A02476-1: its own captions document paraffin sections from human tonsil and mouse and rat spleen (A02476-1 IHC captions). For human tissue IHC, M02476-1 offers a rabbit monoclonal antibody with paraffin-section images from spleen and tonsil; choose it for IF/ICC when that listed application is needed, although no IF image is supplied (catalog host/clone/applications/images; M02476-1 IHC captions). Both IHC captions specify paraffin sections and EDTA retrieval, but neither reports the fixative (A02476-1 and M02476-1 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P19878 (NCF2_HUMAN, Neutrophil cytosol factor 2).
  2. Human Protein Atlas. NCF2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. NCF2 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. NCF2 antibody validation summary (3 antibodies).
  5. NCF2 facilitates M2 macrophage polarization in glioblastoma through activation of the notch1-osteopontin axis. Frontiers in immunology 2026 — PMC12936047.
  6. NCF2 as a Novel Diagnostic Biomarker in Ulcerative Colitis: Linking Macrophage Infiltration to Immune Dysregulation via Multi-Omics Analysis. Journal of inflammation research 2025 — PMC12684989.
  7. Novel Diagnostic Biomarkers Related to Oxidative Stress and Macrophage Ferroptosis in Atherosclerosis. Oxidative medicine and cellular longevity 2022 — PMC9410850.
  8. Role of NCF2 as a potential prognostic factor and immune infiltration indicator in hepatocellular carcinoma. Cancer medicine 2023 — PMC10134316.
  9. PubMed PMID:1692159 — UniProt-cited evidence.
  10. PubMed PMID:7903171 — UniProt-cited evidence.
  11. PubMed PMID:12207919 — UniProt-cited evidence.