NFKBIE / NF-kappa-B inhibitor epsilon · IHC design guide

Design Immunohistochemistry for NFKBIE

Plan NFKBIE staining in paraffin sections using cytoplasmic localisation and the high signal reported in lymph node germinal center cells (HPA tissue IHC). Compare staining across consistently fixed sections and interpret intensity in light of the medium agreement between antibody staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NFKBIE (IHC for NFKBIE): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody M07073, validated IHC image, and IHC protocol steps
Printable NFKBIE IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody M07073, controls and protocol steps. Open the full NFKBIE IHC guide →

NFKBIE Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern High cytoplasmic staining in germinal center cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M07073)
Positive control ⓘ Bone marrow+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining has medium agreement with RNA expression (HPA tissue IHC)
Regulation No stimulus-linked expression specified (UniProt)
Isoform / epitope No annotated isoforms; full-length chain 1–500 (UniProt)
Section 1

Recommended NFKBIE IHC & IF Protocols

The catalog antibody uses EDTA pH 8.0 retrieval (datasheet: M07073). Three published IHC protocols provide sample-specific conditions (PMC12502231; PMC11332585; PMC12553587).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse spleen tissue; fixative not specified (datasheet M07073)
FixationImage fixative and duration unreported (datasheet M07073); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M07073); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M07073)
Primary antibodyRabbit monoclonal (clone ADCF-14) anti-NFKBIE, 1:50 (datasheet M07073)
Primary incubationOvernight at 4 °C (datasheet M07073)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M07073)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNFKBIE-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression with high levels in lymphoid tissue. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet: M07073); citrate retrieval is a published alternative for mouse xenograft sections (PMC12502231).
Section 2

What Is the Expected NFKBIE Staining Pattern?

NFKBIE is a cytoplasmic protein with no transmembrane segment (UniProt O00221). In paraffin-section IHC, expect cytoplasmic staining across many cell types, with prominent staining in lymphoid tissue and hematopoietic cells (HPA: ubiquitous cytoplasmic expression; high in bone-marrow hematopoietic cells). HPA rates the tissue pattern Supported, with medium agreement between staining and RNA data and external verification pending (HPA: tissue IHC reliability).

What am I looking at on my slide?
Clear cytoplasmic staining in lymph-node germinal-center cells or bone-marrow hematopoietic cells (HPA: High in both).This fits the reported IHC distribution (HPA: ubiquitous cytoplasmic expression, high in lymphoid tissue). Compare staining with neighboring cells and a matched negative control before scoring intensity (general IHC practice).
Strong nuclear-only or membrane-rim staining dominates a paraffin section (HPA: tissue IHC profile is cytoplasmic).This is discordant with the expected tissue pattern and warrants an artefact check (HPA: tissue IHC profile; UniProt O00221: cytoplasm, no transmembrane segment). Nuclear staining alone is inconclusive: HPA separately reports nucleolar and nucleoplasmic ICC-IF signal (HPA: subcellular ICC-IF).
Staining is strongest in smooth-muscle cells, myocytes, fibroblasts or adipocytes while an expected high-staining population is faint (HPA: Low in those cell types).The reversed intensity pattern raises concern for cross-reactivity or endogenous detection activity; it does not establish either cause (HPA: tissue IHC levels; general IHC practice). These low-staining cells are not validated negatives (HPA: no negative tissues listed).
Color spreads evenly across tissue, including spaces or structures without a clear cellular pattern (general IHC practice).Diffuse background limits interpretation of NFKBIE localization; assess reagent-only and tissue controls before assigning the color to target protein (general IHC practice). A genuine tissue pattern should be predominantly cytoplasmic (HPA: tissue IHC profile).
No signal appears in lymph-node germinal-center cells or bone-marrow hematopoietic cells (HPA: High in both).The result conflicts with HPA's observed high staining, but one blank section does not prove biological absence (HPA: tissue IHC; general IHC practice). Check section quality and assay controls, then repeat with an IHC-validated antibody if needed (general IHC practice).
💡Expected NFKBIE appearanceCall a convincing positive when cellular cytoplasm stains clearly in an HPA high-staining population, such as lymph-node germinal-center cells, while controls remain clean; diffuse color or a dominant membrane rim is suspect (HPA: tissue IHC; UniProt O00221 topology; general IHC practice).
How each factor affects the staining
Tissue distribution (HPA: tissue IHC)HPA reports ubiquitous cytoplasmic staining with high levels in lymphoid tissue; its listed low-staining cell types are comparisons, not validated negatives (HPA: tissue IHC).
Evidence strength (HPA: tissue IHC reliability)The pattern is Supported, with medium staining–RNA agreement and external verification pending; use it as an expected pattern, not an absolute pass/fail rule (HPA: tissue IHC reliability).
Cellular topology (UniProt O00221)NFKBIE is cytoplasmic and has no transmembrane segment; a dominant membrane outline needs scrutiny in tissue IHC (UniProt O00221; HPA: tissue IHC profile).
Antibody validation (HPA: antibody records)HPA lists IHC as Supported for HPA002692, HPA005941 and CAB010272; this supports the reported pattern but does not validate an unlisted reagent (HPA: antibody records).
IF/ICC pattern? (HPA: subcellular ICC-IF)HPA reports mainly nucleoli fibrillar-center signal, plus nucleoplasm and cytosol, in ICC-IF. Treat this as a separate assay observation when judging paraffin-section IHC (HPA: subcellular ICC-IF; HPA: tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
High-staining lymphoid cells show no chromogenic signal (HPA: High in lymph-node germinal-center cells).Assay failure or weak target detection is possible; absence in one section is not proof of absent NFKBIE (general IHC practice).Confirm tissue preservation, detection controls and the catalog antibody's IHC-P instructions; repeat with an HPA high-staining tissue for comparison (general IHC practice; HPA: tissue IHC).
A strong membrane rim replaces the expected cytoplasmic pattern (HPA: tissue IHC profile).A dominant membrane pattern conflicts with the reported cytoplasmic localization and lack of a transmembrane segment (HPA: tissue IHC; UniProt O00221).Compare with a clean negative control and examine whether signal follows cell boundaries rather than cytoplasm; reassess specificity before scoring (general IHC practice).
Color is strongest in low-staining fibroblasts or smooth-muscle cells (HPA: Low in both).Cross-reactivity or endogenous detection activity could contribute, particularly if an expected high-staining cell population is weak (HPA: tissue IHC; general IHC practice).Check reagent-only controls and endogenous-enzyme blocking for the chromogenic system; compare with an HPA high-staining cell population (general IHC practice; HPA: tissue IHC).
Diffuse color obscures cellular boundaries (general IHC practice).Nonspecific reagent binding or incomplete washing can produce background in chromogenic IHC (general IHC practice).Review blocking, antibody dilution and wash conditions against the catalog IHC-P protocol; use controls to determine whether a cytoplasmic pattern remains interpretable (general IHC practice).
A nuclear-only result appears in tissue despite cytoplasmic staining expected by IHC (HPA: tissue IHC profile).The assays differ: HPA reports nucleolar and nucleoplasmic signal in ICC-IF, alongside cytosol, while its tissue IHC profile is cytoplasmic (HPA: subcellular ICC-IF; tissue IHC).Record the compartment and assay separately. Check IHC controls and morphology before calling nuclear-only tissue staining either specific or artefactual (general IHC practice; HPA: tissue IHC).
Two paraffin sections differ sharply in staining intensity (general IHC practice).Unequal section quality or assay conditions may affect comparison; HPA supplies no target-specific fixation-sensitivity finding for NFKBIE (general IHC practice; HPA: supplied tissue IHC evidence).Compare matched controls and processing records, then score the same cell population under comparable staining conditions (general IHC practice).

Sample controls for NFKBIE IHC & IF

🧪Run lymph node first and check that germinal center cells stain (HPA: High in lymph node germinal center cells). HPA detects NFKBIE in all 45 scored tissues, so use no-primary and isotype controls for the negative comparison; any cells on the positive slide without specific staining should show counterstain only, but they are not validated biological negatives (HPA: no negative tissue rows; standard IHC practice).
Positive control tissue: Bone marrow (Hematopoietic cells, HPA High)
Negative control tissue: None in HPA: NFKBIE is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show NFKBIE in A-431, U-251MG, U2OS, with annotated localisation: Nucleoli fibrillar center (supported) (HPA subcellular).
Technical controls: Include a secondary-only slide and an isotype control matched to the primary antibody’s host species, immunoglobulin class and clonality; a NFKBIE knockout specimen, if available, provides a biological specificity control (standard IHC practice). Quench endogenous peroxidase and check for residual chromogen signal in lymph node immune cells when using HRP/DAB detection (standard IHC practice; selected M07073 caption: HRP/DAB).
⚠️Feasibility: The selected M07073 caption demonstrates staining in a paraffin-embedded mouse spleen section after heat retrieval in EDTA at pH 8.0, but reports no fixative (selected M07073 tissue-IHC caption). A target-specific fixation window and fixation effect are unreported, and the supplied evidence does not establish whether frozen sections or IF would be easier (selected M07073 tissue-IHC caption; HPA: ICC-IF localization images). In lymph node, endogenous peroxidase in immune cells can complicate HRP/DAB interpretation, so assess background on the secondary-only slide (standard IHC practice).

HPA tissue IHC evidence for NFKBIE

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Fallopian tube Glandular cells High Protein (IHC) HPA →
Lymph node Germinal center cells High Protein (IHC) HPA →
Nasopharynx Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: NFKBIE is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced NFKBIE IHC Tips

Troubleshoot NFKBIE staining by comparing signal strength, cell type and compartment across matched paraffin sections and controls (datasheet M07073; HPA tissue IHC; UniProt O00221).

How should I optimize retrieval when NFKBIE staining is weak?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet M07073). The catalog antibody produced a mouse spleen IHC image after this retrieval and overnight incubation at 4°C at 1:50 (datasheet M07073). If staining is weak, compare retrieval heating and cooling conditions across adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Include a matched section without primary antibody to distinguish recovered signal from retrieval-related background (standard IHC practice). Treat any alternative buffer or pH as a fallback requiring its own comparison, because the supplied image documents EDTA at pH 8.0 (datasheet M07073).
Could fixation explain inconsistent NFKBIE staining between paraffin blocks?
Target-specific NFKBIE fixation sensitivity is unknown: the selected image identifies a paraffin section but does not report its fixative (datasheet M07073). Record each block’s fixative and fixation duration, then compare similarly processed sections under identical retrieval, antibody incubation and DAB development conditions (standard IHC practice). Excessive or inconsistent fixation can alter epitope accessibility in IHC, but this remains a general possibility rather than a demonstrated NFKBIE effect (standard IHC practice). Use a section with established staining in the same run to monitor processing and detection performance (standard IHC practice). Do not infer fixation tolerance from the tissue staining profile or protein sequence (HPA tissue IHC; UniProt O00221).
Where should convincing NFKBIE chromogenic signal appear?
Expect a cytoplasmic component because NFKBIE is described as cytoplasmic and sequesters NF-kappa-B complexes there (UniProt O00221). Tissue IHC describes broadly cytoplasmic staining, with higher levels in lymphoid tissue (HPA tissue IHC). Assess signal within identified cells rather than treating diffuse DAB over connective tissue or section edges as cellular localisation (standard IHC practice). Nuclear staining deserves separate scrutiny: cell imaging reports nucleolar fibrillar center, nucleoplasmic and cytosolic localisation, but those observations do not establish the pattern for this antibody in paraffin IHC (HPA subcellular; datasheet M07073). Compare compartments against counterstained morphology and a no-primary control before assigning a nuclear pattern to NFKBIE (standard IHC practice).
Could an isoform or modified epitope account for patchy staining?
The supplied UniProt record annotates no isoforms and lists a single 1–500 chain, so it provides no isoform-specific staining prediction (UniProt O00221). It lists phosphoserines at residues 157, 161 and 183, without establishing whether the catalog antibody recognizes a phosphorylation-sensitive epitope (UniProt O00221; datasheet M07073). The antibody’s epitope is not specified in the supplied caption, so patchiness alone cannot identify epitope masking or modification as the cause (datasheet M07073). Compare adjacent sections processed together and inspect whether staining follows cell morphology or processing boundaries (standard IHC practice). If evaluating another antibody, check its documented immunogen and IHC validation before interpreting discordant patterns (standard IHC practice).
How can I investigate NFKBIE localisation with multiplex IF?
For a separate IF experiment, pair NFKBIE with a validated marker for the cell population under study; macrophages are among the reported expressing cells (UniProt O00221; standard IF practice). Choose spectrally separated fluorophores and consider a far-red channel when tissue autofluorescence overlaps shorter-wavelength signal (standard IF practice). NFKBIE has no transmembrane segment and is reported in cytosol and nuclear compartments, so evaluate permeabilisation that allows antibody access to those intracellular sites (UniProt O00221; HPA subcellular; standard IF practice). Include single-stain and no-primary controls to check bleed-through and background (standard IF practice). The supplied catalog image documents chromogenic paraffin IHC, so establish this antibody’s IF performance independently (datasheet M07073).
How do I reduce diffuse DAB or nonspecific cellular staining?
First compare the stained section with a no-primary control to identify detection-system or tissue background (standard IHC practice). The selected image used 10% goat serum block, a 1:50 rabbit primary overnight at 4°C, and a peroxidase-linked secondary (datasheet M07073). Apply a peroxidase block before HRP detection and keep DAB development consistent across comparison sections (standard IHC practice). If background persists, titrate the primary and secondary separately and review washing, serum blocking and reagent compatibility (standard IHC practice). Judge any loss of background against retained intracellular staining in plausible positive cells, including lymphoid populations (HPA tissue IHC; standard IHC practice).
What is a defensible way to score NFKBIE IHC across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because tissue IHC reports widespread cytoplasmic expression with higher levels in lymphoid tissue (HPA tissue IHC). Within matched regions, report an H-score based on intensity and percentage of positive cells, or report percentage positive with an explicit threshold (standard IHC practice). For spatial comparisons, count positive cells per mm² of evaluable tissue and state the sampled area (standard IHC practice). Normalize cell counts to the relevant cell population or evaluable tissue area, using the same rule across sections (standard IHC practice). Keep retrieval, staining, counterstaining and image analysis settings consistent, and exclude folds or necrotic areas by predefined criteria (standard IHC practice).
How can I distinguish true NFKBIE staining from artefact?
Give greatest weight to cellular staining in plausible compartments: NFKBIE is cytoplasmic by UniProt annotation, while tissue IHC reports cytoplasmic expression (UniProt O00221; HPA tissue IHC). Compare cell identity with the expected context, including lymphoid tissue enrichment and reported expression in granulocytes and macrophages (HPA tissue IHC; UniProt O00221). Treat staining restricted to cut edges, folds or necrotic areas as suspect and inspect a no-primary section for matching signal (standard IHC practice). Check whether an apparent brown deposit persists after peroxidase blocking before attributing it to NFKBIE (standard IHC practice). Nuclear-only signal warrants independent validation because cell imaging reports nuclear sites, whereas the supplied tissue IHC profile emphasizes cytoplasm (HPA subcellular; HPA tissue IHC).
Boster reagents

Best NFKBIE / NF-kappa-B inhibitor epsilon IHC Antibodies

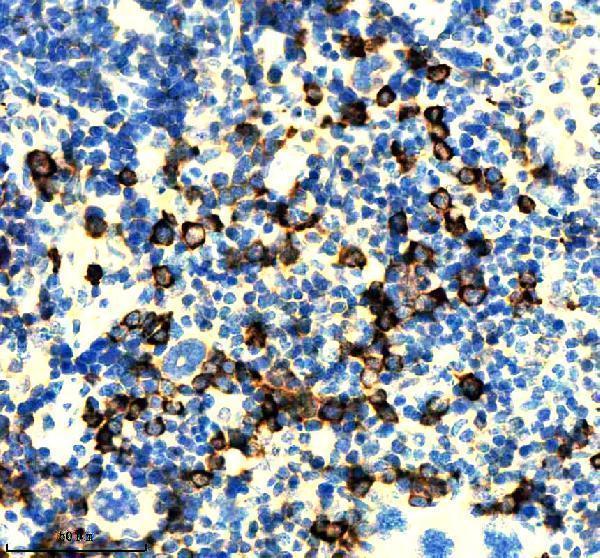
Two anti-NFKBIE antibodies list Human reactivity and IHC/IF/ICC applications (catalog); M07073 has a paraffin-section mouse spleen IHC image, while neither has an IF image (catalog).

Real IHC data IHC analysis of NFKBIE using anti-NFKBIE antibody (M07073). NFKBIE was detected in a paraffin-embedded section of mouse spleen tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-NFKBIE Antibody (M07073) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-IKB epsilon NFKBIE Monoclonal Antibody
Cat # M07073

M07073 lists Human reactivity and IHC/IF/ICC applications; its IHC image shows a paraffin-embedded mouse spleen section (catalog; M07073 image caption). M07073-3 lists Human reactivity and IHC/IF/ICC applications, with no IHC or IF image supplied (catalog).

Which to pick: Choose M07073 for paraffin-section chromogenic IHC: its caption documents EDTA pH 8.0 retrieval, 1:50 primary antibody and DAB detection; the fixative is unreported (M07073 image caption). For IF/ICC, both rabbit monoclonals list those applications and Human reactivity, but neither has an IF image (catalog). Cross-species reactivity is unestablished: both list Human reactivity, although M07073’s IHC caption depicts mouse spleen (catalog; M07073 image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O00221 (IKBE_HUMAN, NF-kappa-B inhibitor epsilon).
  2. Human Protein Atlas. NFKBIE tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. NFKBIE subcellular location (ICC-IF): Mainly localized to the nucleoli fibrillar center. In addition localized to the nucleoplasm and cytosol..
  4. Human Protein Atlas. NFKBIE antibody validation summary (3 antibodies).
  5. NFKBIE as a prognostic biomarker and therapeutic target for GBM: role in Hedgehog signaling activation. BMC cancer 2025 — PMC12502231.
  6. NFKBIE is a predictive factor of survival and is correlated with immune infiltration and antigen processing and presentation in hepatocellular carcinoma. Oncology letters 2024 — PMC11332585.
  7. FTO promotes the progression of triple-negative breast cancer by regulating the m6A methylation of NFKBIE. Clinical and experimental medicine 2025 — PMC12553587.
  8. Discovery of Novel Recurrent Mutations and Clinically Meaningful Subgroups in Nodal Marginal Zone Lymphoma. Cancers 2020 — PMC7352856.
  9. PubMed PMID:9135156 — UniProt-cited evidence.
  10. PubMed PMID:14574404 — UniProt-cited evidence.
  11. PubMed PMID:9315679 — UniProt-cited evidence.