NKX2-1 / Homeobox protein Nkx-2.1 · IHC design guide

Design Immunohistochemistry for NKX2-1

Plan chromogenic IHC for NKX2-1 around nuclear staining in thyroid glandular and lung alveolar type I cells (HPA tissue IHC). Use adrenal glandular cells, where staining was not detected, as a comparison and keep fixation consistent across sections (HPA tissue IHC; standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NKX2-1 (IHC for NKX2-1): expected localisation Nuclear staining in thyroid and lung (HPA tissue IHC), antibody M01322-3, validated IHC image, and IHC protocol steps
Printable NKX2-1 IHC protocol sheet — expected localisation Nuclear staining in thyroid and lung (HPA tissue IHC), antibody M01322-3, controls and protocol steps. Open the full NKX2-1 IHC guide →

NKX2-1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in thyroid and lung (HPA tissue IHC)
Staining pattern Strong nuclear staining in thyroid glandular and lung alveolar type I cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M01322-3)
Positive control ⓘ Lung+3 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Bronchial and nasopharyngeal epithelium also stains (HPA tissue IHC)
Regulation Thyroid and lung enriched expression (HPA tissue IHC)
Isoform / epitope 2 isoforms; antibody epitope coverage is unknown (UniProt)
Section 1

Recommended NKX2-1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: M01322-3) is followed by four published NKX2-1 chromogenic IHC protocols (PMC2950211; PMC6541221; PMC2705775; PMC6138525).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human thyroid cancer tissue; fixative not specified (datasheet M01322-3)
FixationImage fixative and duration unreported (datasheet M01322-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M01322-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M01322-3)
Primary antibodyRabbit monoclonal (clone 27N58) anti-NKX2-1, 1:50-1:200 (datasheet M01322-3)
Primary incubationOvernight at 4 °C (datasheet M01322-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M01322-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNKX2-1-positive staining in alveolar cells type I of lung (HPA tissue IHC: High). HPA tissue profile: Selective nuclear expression in thyroid and lung. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet: M01322-3). For mouse thyroid sections, a published alternative uses citrate at pH 7.0 (PMC6138525).
Section 2

What Is the Expected NKX2-1 Staining Pattern?

NKX2-1 is a nuclear transcription factor with no transmembrane segment (UniProt P43699: localization, topology). In paraffin-section IHC, expect selective nuclear staining in thyroid glandular cells and lung alveolar type I cells, with weaker staining in respiratory epithelium of bronchus and nasopharynx (HPA tissue IHC: high in thyroid and lung; medium in bronchus and nasopharynx). HPA rates its tissue pattern Enhanced, reflecting high consistency between staining and RNA expression (HPA tissue IHC: reliability).

What am I looking at on my slide?
Strong, discrete nuclear chromogen in thyroid glandular cells or lung alveolar type I cells.This matches the reported high-staining populations and nuclear pattern (HPA tissue IHC: thyroid and lung high, selective nuclear expression). Judge the cells and their nuclei, rather than treating any brown tissue area as a positive result (standard IHC practice).
Predominantly cytoplasmic, membranous, or diffuse extracellular color, with little nuclear signal.This conflicts with the expected nuclear location and absence of a transmembrane segment (UniProt P43699: localization, topology). Treat it as suspect staining; examine background and controls before assigning it to NKX2-1 (standard IHC practice).
Prominent staining in adipocytes or adrenal glandular cells, especially outside nuclei.HPA reports NKX2-1 as not detected in these populations (HPA tissue IHC: adipose tissue and adrenal gland). Consider cross-reactivity or endogenous chromogenic activity, then check whether the same staining appears in a no-primary control (standard IHC practice).
A general haze or widespread brown color obscures cell boundaries and nuclei.This cannot establish the selective nuclear pattern reported by HPA (HPA tissue IHC: profile). Nonspecific reagent binding, residual detection activity, or insufficient washing can produce background; compare the negative control and inspect whether the signal is confined to nuclei (standard IHC practice).
No nuclear signal in thyroid glandular cells or lung alveolar type I cells.A blank known-positive population conflicts with HPA's high staining observations (HPA tissue IHC: thyroid and lung high). First verify tissue identity and an intact staining run; then review retrieval, primary antibody use, and detection steps as general IHC checks (standard IHC practice).
💡Expected NKX2-1 appearanceCall the IHC result positive when high chromogenic signal is confined to nuclei of thyroid glandular cells or lung alveolar type I cells; prominent cytoplasmic color or staining of HPA-negative cells is suspect (HPA tissue IHC: nuclear profile, high and not-detected populations; UniProt P43699: nucleus).
How each factor affects the staining
Tissue and cell selectionThyroid glandular cells and lung alveolar type I cells provide HPA-reported high examples; bronchial and nasopharyngeal respiratory epithelial cells are medium (HPA tissue IHC). Interpret a weaker respiratory epithelial result against its own reported level, rather than expecting every positive site to match thyroid or lung (HPA tissue IHC: positive populations).
Antibody evidence for IHCHPA lists CAB000078 and CAB053633 as IHC Enhanced; that designation reflects reproduced staining by independent antibodies or orthogonal data (HPA antibodies: IHC validation). It supports use of the reported tissue pattern as a benchmark, while slide-level controls remain necessary to assess a particular staining run (standard IHC practice).
Isoforms and epitope coverageUniProt lists two NKX2-1 isoforms, 1 and 3 (UniProt P43699: isoforms). The supplied record gives no antibody epitope or isoform recognition data, so a difference between specimens cannot be assigned to isoform coverage from these sources alone (UniProt P43699: isoforms; HPA antibodies: validation fields).
Antigen retrieval, as a general IHC variableIf a known-positive paraffin section is blank, review the retrieval step alongside the primary and detection steps (standard IHC practice). The supplied HPA tissue pattern and UniProt record do not establish an NKX2-1-specific retrieval requirement or a fixation effect (HPA tissue IHC: scope; UniProt P43699: record).
IF/ICC: should the same compartment be expected?For this IHC guide, use the selective nuclear tissue pattern (HPA tissue IHC: profile; UniProt P43699: nucleus). HPA's separate ICC-IF entry reports Golgi apparatus and vesicles as uncertain in its imaged cell lines (HPA subcellular: uncertain locations, HEK293, U-251MG, U2OS). That entry does not override the tissue IHC benchmark (HPA tissue IHC: profile).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive thyroid or lung section is blank.The observed result conflicts with HPA-reported high staining; the source does not identify a specific failed step (HPA tissue IHC: thyroid and lung high).Confirm the scored cell population, then check retrieval, primary antibody, chromogen, and run controls in sequence (standard IHC practice).
Color is mainly cytoplasmic or membranous.That compartment conflicts with NKX2-1's nuclear annotation and lack of a transmembrane segment (UniProt P43699: localization, topology).Inspect nuclear counterstain and a no-primary control; review blocking, washing, and detection if extranuclear color persists (standard IHC practice).
Adipocytes or adrenal glandular cells appear strongly positive.HPA reports NKX2-1 as not detected in those cells; cross-reactivity or endogenous detection activity is possible (HPA tissue IHC: negative populations; standard IHC practice).Compare a no-primary control and reassess whether signal is nuclear; investigate detection background before scoring it as NKX2-1 (standard IHC practice).
Diffuse brown background makes nuclei hard to distinguish.Background can arise from nonspecific binding or residual chromogenic activity (standard IHC practice). It obscures HPA's selective nuclear pattern (HPA tissue IHC: profile).Check the negative control, blocking, washes, and chromogen development; rescore only where individual nuclei are clearly resolved (standard IHC practice).
Bronchial or nasopharyngeal epithelium stains less intensely than thyroid.HPA rates those respiratory epithelial populations medium, versus high thyroid glandular staining (HPA tissue IHC: positive populations).Judge localization and the appropriate tissue reference before changing conditions solely to equalize intensity (HPA tissue IHC: nuclear profile and levels; standard IHC practice).
An ICC-IF image suggests Golgi or vesicle signal while the IHC slide is nuclear.HPA marks those ICC-IF locations uncertain, while tissue IHC shows selective nuclear expression (HPA subcellular: uncertainty; HPA tissue IHC: profile).Interpret the paraffin-section result against tissue IHC and its controls; consult the separate IF/ICC guide for that application's images (HPA tissue IHC: profile; HPA subcellular: ICC-IF).

Sample controls for NKX2-1 IHC & IF

🧪Run thyroid gland first; glandular cells should show nuclear staining (HPA: High in thyroid gland glandular cells; UniProt P43699: nucleus). Use adipose tissue adipocytes as the negative tissue (HPA: Not detected in adipocytes), and assess nonglandular cells on the thyroid slide for background rather than counting their staining as target positive (HPA: High in thyroid gland glandular cells).
Positive control tissue: Lung (Alveolar cells type I, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show NKX2-1 in HEK293, U-251MG, U2OS, with annotated localisation: Golgi apparatus (uncertain), Vesicles (uncertain) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; an IgG control matched to the primary antibody’s host species and, if applicable, monoclonal subclass; and NKX2-1 knockout tissue as a biological negative (standard IHC practice). Block endogenous peroxidase in the thyroid section before HRP/DAB detection (selected-SKU caption: HRP/DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative not stated). The demonstrated IHC procedure uses heat retrieval in EDTA at pH 8.0, but the evidence does not establish that retrieval is required for every specimen (selected-SKU caption: EDTA retrieval, pH 8.0). There is no matched evidence that frozen sections or IF are easier; interpret IF localisation cautiously because the uncertain Golgi and vesicle annotation differs from the nuclear UniProt annotation (HPA: uncertain Golgi apparatus and vesicles; UniProt P43699: nucleus).

HPA tissue IHC evidence for NKX2-1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Lung Alveolar cells type I High Protein (IHC) HPA →
Thyroid gland Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Nasopharynx Respiratory epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced NKX2-1 IHC Tips

Troubleshoot NKX2-1 staining in paraffin sections by checking retrieval, nuclear localisation, cell identity and controls (UniProt P43699; HPA tissue IHC).

How should I troubleshoot weak NKX2-1 staining after antigen retrieval?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet M01322-3). The selected image used this retrieval before overnight incubation at 4°C with antibody diluted 1:50 (datasheet M01322-3). If nuclear staining is weak, compare controlled heating durations while holding antibody dilution, detection and section thickness constant (standard IHC practice). Include thyroid glandular cells as a positive reference and adipocytes as a negative reference (HPA tissue IHC). Score nuclear signal and tissue damage together; stronger DAB alone does not establish improved NKX2-1 detection (UniProt P43699 localisation; standard IHC practice).
Could fixation explain inconsistent nuclear staining between paraffin sections?
The selected paraffin-section caption does not state a fixative, so target-specific NKX2-1 sensitivity to fixation is unknown (datasheet M01322-3). Record the fixative, fixation interval, processing schedule and section age for each specimen before comparing staining (standard IHC practice). To investigate an inconsistent result, process matched samples under defined fixation conditions and apply the same EDTA pH 8.0 retrieval and 1:50 primary dilution (datasheet M01322-3; standard IHC practice). Compare nuclear signal in the same cell population and assess morphology alongside intensity (UniProt P43699 localisation; standard IHC practice). Do not infer a preferred fixation condition from tissue-expression patterns (HPA tissue IHC).
Should cytoplasmic or punctate staining count as NKX2-1 positive?
For chromogenic tissue IHC, score convincing nuclear staining: NKX2-1 is a nuclear transcription factor, and tissue staining is selectively nuclear in thyroid and lung (UniProt P43699; HPA tissue IHC). Thyroid glandular cells and lung alveolar type I cells provide expected positive populations (HPA tissue IHC). Golgi and vesicle locations appear in an ICC/IF summary, but both assignments are marked uncertain (HPA subcellular). Therefore, record isolated cytoplasmic or punctate DAB separately and check it against a no-primary control before calling cells positive (HPA subcellular; standard IHC practice). Keep counterstain light enough to resolve individual nuclei (standard IHC practice).
Could isoforms or epitope accessibility cause discordant nuclear IHC results?
NKX2-1 has 2 listed isoforms, numbered 1 and 3, and a reported phosphoserine at residue 254 (UniProt P43699). Its annotated chain spans residues 1–371, with no transmembrane segment or signal peptide (UniProt P43699). The supplied caption does not identify the antibody epitope, so neither isoform coverage nor modification sensitivity can be assigned to M01322-3 (datasheet M01322-3; UniProt P43699). If validated assays disagree, obtain the immunogen or epitope information and compare it with isoform sequences before attributing the difference to expression (standard IHC practice). First check retrieval, nuclear localisation and positive controls on adjacent sections (datasheet M01322-3; HPA tissue IHC).
How can I assess NKX2-1 in a multiplex IF experiment?
For the separate IF/ICC workflow, pair NKX2-1 with a validated marker identifying thyroid glandular cells or lung alveolar type I cells (HPA tissue IHC; standard IF practice). Assign the dimmer target a bright, spectrally separated fluorophore, and check tissue autofluorescence and single-stain controls before interpreting overlap (standard IF practice). Because the expected signal is nuclear and NKX2-1 lacks a transmembrane segment, choose permeabilisation that allows nuclear antibody access, then optimise it against cell morphology (UniProt P43699; standard IF practice). Confirm the chosen antibody and fixation method for IF independently; the paraffin-section caption supplies no IF fixation evidence (datasheet M01322-3). Treat punctate Golgi or vesicle signal cautiously because those ICC/IF locations are uncertain (HPA subcellular).
What should I check when DAB background obscures NKX2-1 nuclei?
The selected paraffin-section example used 10% goat serum blocking, 1:50 primary antibody overnight at 4°C, and peroxidase-conjugated secondary antibody for 30 minutes at 37°C (datasheet M01322-3). It then used DAB development (datasheet M01322-3). If staining is diffuse, run no-primary and secondary-only controls, check washes, and compare a shorter chromogen development time (standard IHC practice). Include a general endogenous-peroxidase blocking step when appropriate for the specimen; it is a workflow control, not NKX2-1-specific evidence (standard IHC practice). Judge background against nuclear staining in expected cells and a negative tissue population such as adipocytes (HPA tissue IHC; UniProt P43699 localisation).
How should I quantify NKX2-1 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define positive staining as nuclear DAB in the cell population selected for analysis, and keep counterstain and image settings consistent (UniProt P43699 localisation; standard IHC practice). Report the percentage of positive nuclei and, when intensity matters, an H-score from 0–300 using intensity categories 0–3 (standard IHC practice). Normalise positive counts to all evaluable nuclei in that cell population, rather than to total tissue area containing stroma or empty space (standard IHC practice). Record how many fields and cells were scored, and exclude folds, necrosis and damaged edges using preset criteria (standard IHC practice). Use matched positive thyroid or lung material to monitor staining consistency between runs (HPA tissue IHC; standard IHC practice).
How do I distinguish true NKX2-1 staining from section artefacts?
A convincing positive pattern is nuclear staining in an expected population, including thyroid glandular cells or lung alveolar type I cells (UniProt P43699 localisation; HPA tissue IHC). Check whether the signal persists away from section edges and necrotic areas, where uneven staining can mislead interpretation (standard IHC practice). Cytoplasmic deposits or strong staining in an unexpected cell population warrant review of morphology, retrieval and no-primary controls before scoring (HPA tissue IHC; standard IHC practice). Investigate widespread DAB signal with an endogenous-peroxidase control and review chromogen development (standard IHC practice). Interpret a negative section alongside a functioning positive control, because failed detection cannot establish absent protein (standard IHC practice).
Boster reagents

Best NKX2-1 / Homeobox protein Nkx-2.1 IHC Antibodies

IHC images cover human lung and thyroid tissue (catalog image captions); IF images cover human lung tissue and HeLa cells (catalog image captions). All three antibodies list human, mouse and rat reactivity (catalog applications/reactivity).

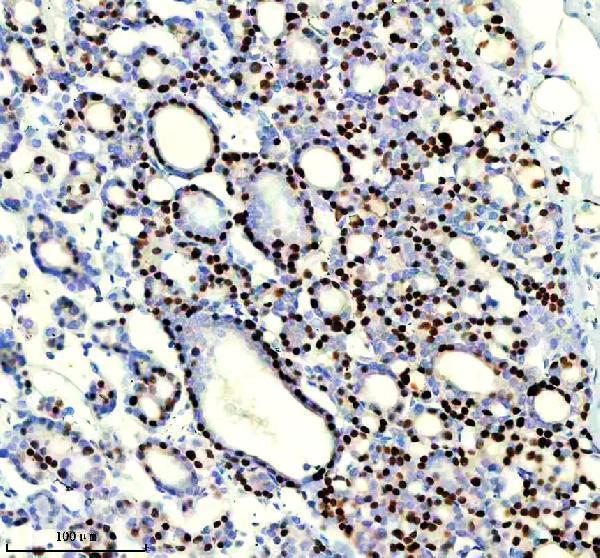
Real IHC data IHC analysis of TTF-1 using anti-TTF-1 antibody (M01322-3). TTF-1 was detected in a paraffin-embedded section of human thyroid cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-TTF-1 Antibody (M01322-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-TTF1 Rabbit Monoclonal Antibody
Cat # M01322-3
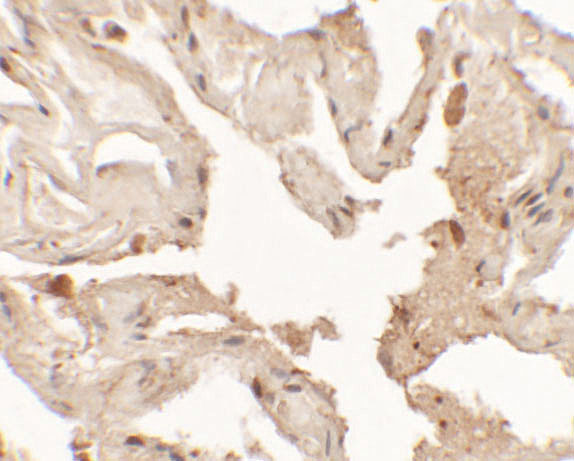
Real IHC data Immunohistochemistry of NKX2-1 in human lung tissue with NKX2-1 antibody at 2.5 μg/mL.
Anti-Homeobox protein Nkx-2.1 NKX2-1 Antibody
Cat # A01322
Real IHC data Immunohistochemical analysis of paraffin-embedded human thyroid, using TTF1 Antibody.
Anti-TTF1 NKX2-1 Rabbit Monoclonal Antibody
Cat # M01322-1

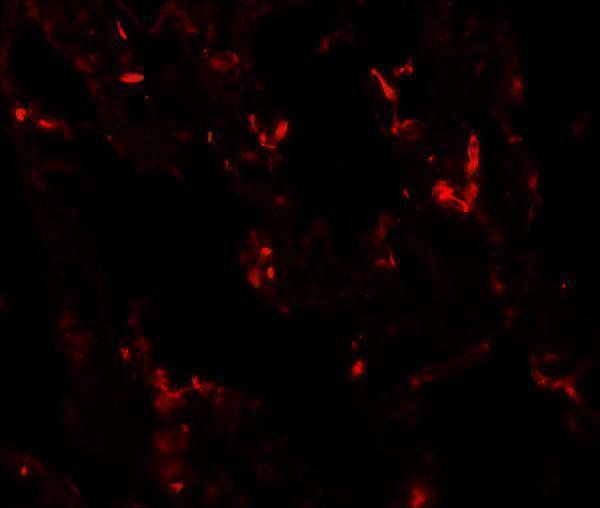
M01322-3 shows IHC in paraffin-embedded human thyroid cancer tissue, with EDTA retrieval at pH 8.0 (M01322-3 image caption). A01322 shows IHC and IF in human lung tissue (A01322 image captions), while M01322-1 shows IHC in paraffin-embedded human thyroid and IF in HeLa cells (M01322-1 image captions).

Which to pick: For paraffin-section IHC, choose M01322-3 when its documented EDTA retrieval workflow fits: its caption reports 1:50 primary antibody and DAB detection; the fixative is unreported (M01322-3 image caption). For IF/ICC, choose M01322-1, a rabbit monoclonal with IF and ICC listed and an IF image in HeLa cells (M01322-1 catalog applications; M01322-1 IF image caption). For work across human, mouse and rat, all three list reactivity with those species; their supplied IHC images show human samples, so verify staining in the intended species (catalog reactivity; catalog IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P43699 (NKX21_HUMAN, Homeobox protein Nkx-2.1).
  2. Human Protein Atlas. NKX2-1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. NKX2-1 subcellular location (ICC-IF): Localized to the Golgi apparatus and vesicles..
  4. Human Protein Atlas. NKX2-1 antibody validation summary (3 antibodies).
  5. Secretoglobin 3A2/uteroglobin-related protein 1 is a novel marker for pulmonary carcinoma in mice and humans. Lung cancer (Amsterdam, Netherlands) 2011 — PMC2950211.
  6. Tumor Suppressor Activity of Selenbp1, a Direct Nkx2-1 Target, in Lung Adenocarcinoma. Molecular cancer research : MCR 2018 — PMC6541221.
  7. Early thyroid development requires a Tbx1-Fgf8 pathway. Developmental biology 2009 — PMC2705775.
  8. An in vivo model for thyroid regeneration and folliculogenesis. Laboratory investigation; a journal of technical methods and pathology 2018 — PMC6138525.
  9. PubMed PMID:7711079 — UniProt-cited evidence.
  10. PubMed PMID:7711080 — UniProt-cited evidence.
  11. PubMed PMID:7713914 — UniProt-cited evidence.