NMNAT1 / Nicotinamide/nicotinic acid mononucleotide adenylyltransferase 1 · IHC design guide

Design Immunohistochemistry for NMNAT1

Plan NMNAT1 chromogenic IHC on paraffin sections around the nuclear staining reported in most tissues (HPA tissue IHC). Use the documented antibody conditions and compare stained cells with appropriate controls, especially where tissue expression evidence differs (datasheet A03221-1; HPA tissue IHC; UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NMNAT1 (IHC for NMNAT1): expected localisation Nuclear in most tissues (HPA tissue IHC), antibody A03221-1, validated IHC image, and IHC protocol steps
Printable NMNAT1 IHC protocol sheet — expected localisation Nuclear in most tissues (HPA tissue IHC), antibody A03221-1, controls and protocol steps. Open the full NMNAT1 IHC guide →

NMNAT1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear in most tissues (HPA tissue IHC)
Staining pattern Nuclear staining in most tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03221-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Skeletal myocytes are unstained despite reported muscle expression (HPA tissue IHC; UniProt)
Regulation Broad expression; no inducer reported (UniProt)
Isoform / epitope No annotated isoforms; one 1–279 chain (UniProt)
Section 1

Recommended NMNAT1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A03221-1) is accompanied by published colorectal, glioma, and liver IHC methods (PMC11954486; PMC12048879; PMC12204165).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human renal cancer tissue; fixative not specified (datasheet A03221-1)
FixationImage fixative and duration unreported (datasheet A03221-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03221-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03221-1)
Primary antibodyRabbit anti-NMNAT1, 2-5 μg/ml (datasheet A03221-1)
Primary incubationOvernight at 4 °C (datasheet A03221-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03221-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNMNAT1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Nuclear expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet A03221-1); the cited articles do not specify a retrieval buffer.
Section 2

What Is the Expected NMNAT1 Staining Pattern?

NMNAT1 is a nuclear protein without a transmembrane segment (UniProt Q9HAN9). In paraffin section IHC, expect nuclear staining in many tissues, including colon glandular cells and cerebral cortex neurons, where HPA reports medium staining (HPA tissue IHC). HPA describes nuclear expression in most tissues, but its IHC reliability is Approved with only medium consistency between antibody staining and RNA data (HPA tissue IHC).

What am I looking at on my slide?
Distinct nuclear chromogen in colon glandular cells or cerebral cortex neurons, with little staining outside nuclei (HPA tissue IHC).This matches the reported medium staining in those cells and NMNAT1’s nuclear location (HPA tissue IHC; UniProt Q9HAN9). Compare intensity within the same run; HPA’s categories are tissue observations, not a universal scoring threshold (HPA tissue IHC).
Predominantly cytoplasmic or membrane staining, without convincing nuclear staining.That compartment does not match the expected nuclear pattern (UniProt Q9HAN9; HPA tissue IHC). Treat it as possible nonspecific staining or a detection artefact; review controls and staining conditions before assigning it to NMNAT1 (general IHC practice).
Strong staining in adipocytes or skeletal muscle myocytes, where HPA reports NMNAT1 as not detected (HPA tissue IHC).Investigate antibody cross-reactivity or endogenous detection activity (general IHC practice). A discrepant result is not proof of either cause: HPA’s IHC assessment has only medium consistency with RNA data (HPA tissue IHC).
Diffuse chromogen across tissue, including areas without a clear nuclear pattern.Background can obscure the compartment needed to interpret NMNAT1 IHC (UniProt Q9HAN9; HPA tissue IHC). Assess a negative reagent control and review blocking, washes and detection chemistry before scoring positive cells (general IHC practice).
No nuclear signal in colon glandular cells despite intact tissue and visible counterstained nuclei (HPA tissue IHC).This misses an HPA-reported medium-staining cell population (HPA tissue IHC). Check antibody and detection performance, antigen retrieval and run controls before calling the sample negative (general IHC practice); no NMNAT1-specific retrieval requirement is supplied.
💡Expected NMNAT1 appearanceCall a positive result when chromogen is concentrated in nuclei of an HPA-reported cell population, such as colon glandular cells or cerebral cortex neurons at medium intensity; diffuse or predominantly extranuclear staining warrants investigation (HPA tissue IHC; UniProt Q9HAN9).
How each factor affects the staining
Nuclear localisation and topology (UniProt Q9HAN9).NMNAT1 is annotated in the nucleus and has no transmembrane segment (UniProt Q9HAN9). Score nuclear staining first; membrane-dominant staining does not fit that annotation, although morphology alone cannot establish antibody specificity (general IHC practice).
Tissue and cell variation (HPA tissue IHC; UniProt Q9HAN9).HPA reports medium nuclear staining in several epithelial and neuronal populations, but no detection in adipocytes or skeletal muscle myocytes (HPA tissue IHC). UniProt reports high expression in skeletal muscle (UniProt Q9HAN9); do not equate that expression statement with a positive myocyte IHC result.
IHC evidence strength (HPA tissue IHC; HPA antibodies).HPA rates tissue IHC Approved, describes medium agreement with RNA, and lists HPA059447 as IHC Approved (HPA tissue IHC; HPA antibodies). Use the reported pattern as a reference, while checking unexpected staining with appropriate controls (general IHC practice).
IF/ICC: what localisation is expected? (HPA subcellular ICC-IF).HPA supports nucleoplasmic and nuclear-body localisation in ICC-IF (HPA subcellular ICC-IF). That observation helps interpret compartment, but this IHC guide supplies no IF/ICC protocol or basis for expecting visible nuclear bodies in every paraffin section.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected nuclei remain unstained in colon glands or cerebral cortex neurons (HPA tissue IHC).A weak run, detection failure or unsuitable general IHC conditions may suppress visible signal (general IHC practice); the payload establishes no NMNAT1-specific fixation or retrieval sensitivity.Check a run control, antibody dilution, retrieval execution and detection reagents before interpreting the specimen as negative (general IHC practice).
Chromogen appears mainly outside nuclei.The pattern conflicts with UniProt’s nuclear annotation and HPA’s nuclear tissue profile (UniProt Q9HAN9; HPA tissue IHC); nonspecific binding or detection background is possible (general IHC practice).Compare with a negative reagent control, inspect nuclear counterstain and reduce background using validated general IHC adjustments (general IHC practice).
Adipocytes or skeletal muscle myocytes stain strongly (HPA tissue IHC).HPA reports these cells as not detected (HPA tissue IHC). Cross-reactivity or endogenous chromogenic activity is possible, although the staining alone cannot identify which mechanism applies (general IHC practice).Compare a negative reagent control and an HPA-reported medium-positive cell population in the same run before assigning specificity (HPA tissue IHC; general IHC practice).
Diffuse background prevents nuclear scoring.Excess nonspecific signal or endogenous detection activity can mask compartment boundaries in chromogenic IHC (general IHC practice).Inspect reagent controls; review blocking, washes, chromogen development and counterstain so nuclear staining can be distinguished from background (general IHC practice).
Skeletal muscle is selected as the sole positive control because UniProt reports high expression (UniProt Q9HAN9).HPA reports skeletal muscle myocytes as not detected by tissue IHC (HPA tissue IHC), so this control may give a misleading assessment of the staining run.Use an HPA-reported medium-staining population, such as colon glandular cells, to assess the IHC run; interpret the muscle result separately (HPA tissue IHC).

Sample controls for NMNAT1 IHC & IF

🧪Run cervix first: squamous epithelial cells should show NMNAT1 staining (HPA: Medium in cervix squamous epithelial cells). Use oral mucosa squamous epithelial cells as the negative tissue (HPA: Not detected in oral mucosa squamous epithelial cells); on the cervix slide, use only visibly unstained stromal cells as an internal background reference, without assuming all stromal cells are NMNAT1-negative (UniProt Q9HAN9: widely expressed).
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show NMNAT1 in BJ [Human fibroblast], PC-3, U2OS, with annotated localisation: Nucleoplasm (supported), Nuclear bodies (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit isotype control alongside a validated NMNAT1 knockout or peptide-block control (caption: rabbit anti-NMNAT1 antibody A03221-1; standard IHC practice). For chromogenic detection, block endogenous peroxidase and check whether any brown signal in the cervix persists in the no-primary control (caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: The selected paraffin-section caption reports heat retrieval in EDTA at pH 8.0, but reports no fixative; a target-specific fixation window and fixation effect are unreported, and retrieval dependence cannot be established from that single condition (caption: A03221-1). Frozen sections cannot be ranked as easier from the supplied evidence (caption: paraffin-section IHC only). IF/ICC Q&A: Is localisation assessable by IF? Yes—use nuclear counterstaining and assess nucleoplasmic and nuclear-body signal, while checking tissue autofluorescence with a no-primary control (HPA subcellular: supported nucleoplasm and nuclear bodies; standard IF practice).

HPA tissue IHC evidence for NMNAT1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →
Caudate Neuronal cells Medium Protein (IHC) HPA →
Cerebral cortex Neuronal cells Medium Protein (IHC) HPA →
Cervix Squamous epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Lymph node Germinal center cells Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Spleen Cells in red pulp Not detected Protein (IHC) HPA →
Section 3

Advanced NMNAT1 IHC Tips

Troubleshoot NMNAT1 staining by checking nuclear localisation, section processing, detection controls and cell-specific scoring (UniProt Q9HAN9; HPA tissue IHC).

Which retrieval conditions should I start with for NMNAT1 paraffin-section IHC?
Start with heat-mediated retrieval in EDTA at pH 8.0 for NMNAT1 paraffin-section IHC (datasheet A03221-1). The selected tissue image used this retrieval before overnight primary-antibody incubation at 4°C, so keep that sequence when reproducing its conditions (datasheet A03221-1). If nuclear staining is weak, check heating consistency, section adhesion and whether the retrieval buffer retained its intended pH before increasing antibody concentration (standard IHC practice; HPA: nuclear expression in most tissues). Compare retrieval changes on adjacent sections with identical detection and counterstaining, because an apparent gain can reflect increased background rather than improved nuclear signal (standard IHC practice).
How should I assess fixation when NMNAT1 nuclear staining is weak?
The selected NMNAT1 image identifies a paraffin-embedded section but does not state its fixative, so target-specific fixation sensitivity is unknown (datasheet A03221-1). Record the fixative, fixation duration and tissue thickness for each specimen, then compare similarly processed sections before attributing weak nuclear signal to NMNAT1 abundance (standard IHC practice; HPA: nuclear expression in most tissues). Include a section processed alongside the test material that shows interpretable nuclear staining, and check that morphology remains intact after retrieval (standard IHC practice). Do not infer a preferred fixative from NMNAT1's nuclear localisation or its annotated phosphorylation sites at residues 117 and 119 (UniProt Q9HAN9).
What staining pattern should count as convincing NMNAT1 localisation?
Prioritise nuclear chromogenic signal when assessing NMNAT1, because UniProt assigns it to the nucleus and HPA reports nuclear expression in most tissues (UniProt Q9HAN9; HPA tissue IHC). HPA subcellular imaging further supports nucleoplasmic and nuclear-body localisation, although that imaging comes from ICC/IF rather than the selected tissue section (HPA subcellular; datasheet A03221-1). Compare brown signal with a nuclear counterstain at the same magnification, and score cells whose nuclei are morphologically intact (standard IHC practice). Diffuse cytoplasmic staining without a nuclear component warrants checks of background, retrieval and detection before it is interpreted as NMNAT1 localisation (UniProt Q9HAN9; standard IHC practice).
Could isoforms or epitope accessibility explain discordant NMNAT1 staining?
The supplied UniProt record lists 0 isoforms and one chain spanning residues 1–279, so it provides no annotated isoform explanation for different IHC patterns (UniProt Q9HAN9). NMNAT1 has no annotated transmembrane segment, signal peptide or glycosylation sites; these annotations alone do not identify the antibody epitope or predict retrieval sensitivity (UniProt Q9HAN9). Confirm the catalog antibody's stated immunogen or epitope before making claims about recognition of particular residues or phosphorylation states (standard antibody-validation practice; UniProt Q9HAN9: phosphoserine 117 and phosphothreonine 119). For discordant sections, compare nuclear signal under matched retrieval and detection conditions, and seek an independent specificity control where available (standard IHC practice).
How can I adapt the localisation check to multiplex IF?
Use the separate IF/ICC workflow to assess NMNAT1 fluorescence, because the selected antibody evidence here describes chromogenic staining of a paraffin section (datasheet A03221-1). Pair NMNAT1 with a marker for the cell population being examined and a nuclear stain, then check whether its signal occupies nuclei within the marked cells (HPA: nuclear expression in most tissues; standard IF practice). Choose spectrally separated fluorophores and favour a red or far-red NMNAT1 channel when shorter-wavelength tissue autofluorescence interferes (standard IF practice). Because NMNAT1 lacks a transmembrane segment and is nuclear, optimise permeabilisation for nuclear epitope access while monitoring cell integrity; the antibody's exact epitope is unspecified here (UniProt Q9HAN9; standard IF practice).
What should I check when DAB obscures NMNAT1 nuclear staining?
The selected NMNAT1 tissue image used a peroxidase-conjugated secondary antibody and DAB, making nonspecific brown deposits relevant to this chromogenic workflow (datasheet A03221-1). Include a no-primary control, block endogenous peroxidase and compare background in nuclei, cytoplasm and tissue edges before adjusting the primary antibody (standard IHC practice). Its image used 10% goat serum blocking and 2 μg/ml primary antibody overnight at 4°C; these are documented starting conditions for that image (datasheet A03221-1). If background persists, inspect washing, secondary-antibody binding and DAB development time while retaining a positive comparison section in the same run (standard IHC practice).
How should I score NMNAT1 across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score NMNAT1 in morphologically intact nuclei within a predefined cell population, consistent with its nuclear assignment and the HPA tissue profile (UniProt Q9HAN9; HPA tissue IHC). Report either the percentage of positive nuclei or an H-score from 0–300 based on nuclear intensity and the percentage of cells at each intensity (standard IHC scoring practice). Normalise positive counts to all evaluable nuclei in that same population, and keep tissue area or cells per mm² explicit when reporting density (standard quantitative pathology practice). Apply one threshold, exposure-free brightfield imaging setup and sampling rule across sections; record excluded folds, edges and necrotic regions (standard IHC practice).
How do I distinguish true NMNAT1 signal from tissue artefact?
Treat crisp nuclear staining in intact cells as more consistent with NMNAT1 than isolated cytoplasmic deposits, because UniProt and HPA describe predominantly nuclear localisation (UniProt Q9HAN9; HPA tissue IHC). Compare the stained cell type with the tissue context: HPA reports medium signal in cerebral-cortex neuronal cells but no detected signal in skeletal-muscle myocytes, despite broad UniProt tissue-expression annotation (HPA tissue IHC; UniProt Q9HAN9). Discount staining confined to section edges, folds or necrotic areas, and check a no-primary section for endogenous peroxidase-associated DAB signal (standard IHC practice). Interpret differences cautiously because HPA labels tissue staining approved with only medium consistency against RNA expression (HPA tissue IHC).
Boster reagents

Best NMNAT1 / Nicotinamide/nicotinic acid mononucleotide adenylyltransferase 1 IHC Antibodies

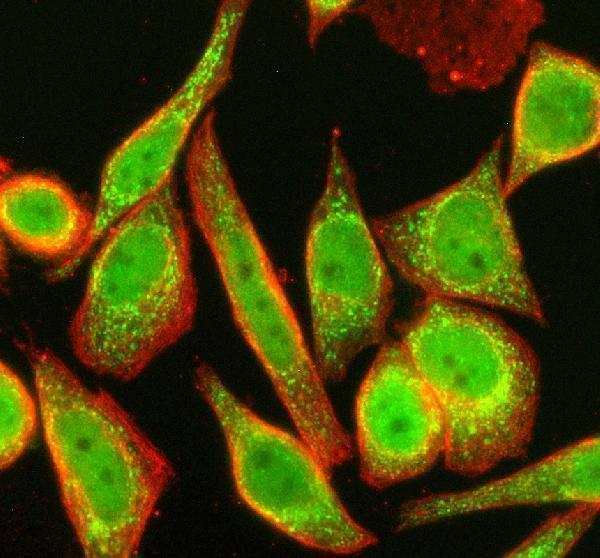
Anti-NMNAT1 A03221-1 has IHC data from human renal cancer paraffin sections and IF/ICC data from rat brain sections and SIHA cells (catalog image captions).

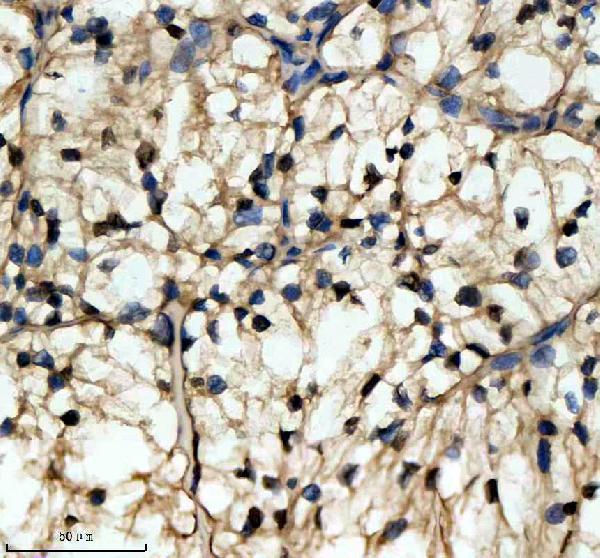
Real IHC data IHC analysis of NMNAT1 using anti-NMNAT1 antibody (A03221-1). NMNAT1 was detected in a paraffin-embedded section of human renal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-NMNAT1 Antibody (A03221-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-NMNAT1 Antibody ®
Cat # A03221-1

A03221-1 has an IHC image from a human renal cancer paraffin section and is listed for IHC (catalog image caption; catalog applications). The same SKU has IF images from rat brain and human renal cancer paraffin sections and an ICC image from SIHA cells (catalog image captions).

Which to pick: Choose A03221-1 for paraffin-section IHC: its image caption documents EDTA retrieval at pH 8.0 and 2 μg/ml antibody in a human renal cancer section; the fixative is unreported (catalog IHC image caption). Choose the same SKU for IF/ICC based on its tissue and cell images, or for work involving human, mouse, and rat based on its listed reactivity; the image captions show human and rat examples (catalog IF image captions; catalog reactivity).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9HAN9 (NMNA1_HUMAN, Nicotinamide/nicotinic acid mononucleotide adenylyltransferase 1).
  2. Human Protein Atlas. NMNAT1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. NMNAT1 subcellular location (ICC-IF): Localized to the nucleoplasm and nuclear bodies..
  4. Human Protein Atlas. NMNAT1 antibody validation summary (1 antibodies).
  5. Prognostic and Immunological Significance of NMNAT1 in Colorectal and Pan-Cancer Contexts. OncoTargets and therapy 2025 — PMC11954486.
  6. Nuclear NAD(+) synthase nicotinamide mononucleotide adenylyltransferase 1 contributes to nuclear atypia and promotes glioma growth. Neuro-oncology advances 2025 — PMC12048879.
  7. Hepatic NMNAT1 is required to defend against alcohol-associated fatty liver disease. Science advances 2025 — PMC12204165.
  8. SARM1 depletion rescues NMNAT1-dependent photoreceptor cell death and retinal degeneration. eLife 2020 — PMC7591247.
  9. PubMed PMID:11248244 — UniProt-cited evidence.
  10. PubMed PMID:11027696 — UniProt-cited evidence.
  11. PubMed PMID:11891043 — UniProt-cited evidence.