NT5C1A / Cytosolic 5'-nucleotidase 1A · IHC design guide

Design Immunohistochemistry for NT5C1A

Plan chromogenic NT5C1A IHC in paraffin sections using skeletal muscle as a high-staining control (HPA tissue IHC). Assess cytoplasmic staining by cell type, since only a subset of renal tubules is positive (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NT5C1A (IHC for NT5C1A): expected localisation Cytoplasm in muscle and some renal tubules (HPA tissue IHC), antibody A12036-2, validated IHC image, and IHC protocol steps
Printable NT5C1A IHC protocol sheet — expected localisation Cytoplasm in muscle and some renal tubules (HPA tissue IHC), antibody A12036-2, controls and protocol steps. Open the full NT5C1A IHC guide →

NT5C1A Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasm in muscle and some renal tubules (HPA tissue IHC)
Staining pattern Cytoplasmic stain in myocytes and a subset of renal tubules (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A12036-2)
Positive control ⓘ Heart muscle+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Only a subset of renal tubules stains (HPA tissue IHC)
Regulation High expression in skeletal muscle (UniProt)
Isoform / epitope No annotated isoforms; one 1–368 chain (UniProt)
Section 1

Recommended NT5C1A IHC & IF Protocols

The catalog antibody has an IHC-P protocol (datasheet A12036-2). Two published NT5C1A IHC studies provide pancreatic cancer tissue protocols (PMC6413477; PMC11109879).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human skeletal muscle tissue; fixative not specified (datasheet A12036-2)
FixationImage fixative and duration unreported (datasheet A12036-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A12036-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A12036-2)
Primary antibodyRabbit anti-NT5C1A, 2-5 μg/ml (datasheet A12036-2)
Primary incubationOvernight at 4 °C (datasheet A12036-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A12036-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNT5C1A-positive staining in cardiomyocytes of heart muscle (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression mainly in a subset of renal tubules and striated muscle. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 for the catalog antibody (datasheet A12036-2). The published microarrays used different retrieval conditions with other antibodies (PMC6413477).
Section 2

What Is the Expected NT5C1A Staining Pattern?

NT5C1A is a cytoplasmic protein with no transmembrane segment (UniProt Q9BXI3: subcellular location and topology). In paraffin-section IHC, expect cytoplasmic staining in striated muscle cells and a subset of renal tubules (HPA: tissue IHC profile). HPA rates the tissue pattern Supported, with medium consistency between staining and RNA expression and external verification pending (HPA: reliability). Read staining by cell type and compartment together, rather than treating any colored area as a positive result.

What am I looking at on my slide?
Clear cytoplasmic staining in skeletal myocytes or cardiomyocytes, with preserved cell outlines.This fits the expected compartment and high-staining cell types (UniProt Q9BXI3: cytoplasm; HPA: High in skeletal myocytes and cardiomyocytes). A subset of renal tubules can also stain (HPA: tissue IHC profile). Compare cells within the same section before assigning an intensity score.
Predominantly nuclear or sharply membrane-restricted staining, without convincing cytoplasmic signal.That pattern conflicts with the recorded cytoplasmic location and absence of a transmembrane segment (UniProt Q9BXI3: subcellular location and topology). Treat it as questionable IHC signal; inspect morphology, counterstain and detection controls before interpreting it as NT5C1A.
Strong staining in cells listed as not detected, such as adipocytes or bone-marrow hematopoietic cells.This differs from the HPA tissue observations (HPA: Not detected in adipocytes and bone-marrow hematopoietic cells). Consider antibody cross-reactivity or detection-related signal, and compare with a known-positive section. An HPA 'Not detected' entry is an observed result, not proof that every specimen must be negative.
Diffuse color across tissue, stroma or empty areas, with little cell-specific contrast.Uniform background cannot establish a cytoplasmic NT5C1A pattern (UniProt Q9BXI3: cytoplasm). Check the no-primary control, blocking, washes and chromogen development as general IHC checks. Score only signal that can be assigned to intact cells in the expected compartment.
No discernible cytoplasmic signal in a well-preserved skeletal- or heart-muscle section.This conflicts with the reported high staining in myocytes or cardiomyocytes (HPA: High in skeletal and heart muscle). First check whether the assay worked using a validated positive control; then review antibody dilution, retrieval conditions and detection steps as general IHC variables. Absence of signal alone does not establish absent protein.
💡Expected NT5C1A appearanceCall a section positive when cytoplasmic staining is clear in skeletal myocytes or cardiomyocytes, where HPA reports High staining; isolated nuclear, membrane-only or cell-independent color is suspect (HPA: tissue IHC; UniProt Q9BXI3: cytoplasm and topology).
How each factor affects the staining
Cellular compartmentNT5C1A is annotated as cytoplasmic and has no transmembrane segment (UniProt Q9BXI3: subcellular location and topology). Use cytoplasmic distribution as an interpretation criterion; a membrane-only pattern needs independent checking.
Tissue and cell-type contrastHPA reports High staining in skeletal myocytes and cardiomyocytes, Medium staining in several listed epithelial or neuronal populations, and Not detected in specified other cells (HPA: tissue IHC). Choose controls by the named cell population, rather than by tissue name alone.
Strength of IHC evidenceThe tissue profile is Supported, with medium staining–RNA consistency and external verification pending (HPA: reliability). Two listed rabbit polyclonal antibodies, HPA050283 and HPA054158, each have Supported IHC status (HPA: antibodies). These labels warrant measured interpretation of unexpected patterns.
IF/ICC interpretationWhat IF pattern is established? No ICC-IF image-bearing cell lines or main subcellular location are supplied (HPA: subcellular record), and the listed antibodies have no ICC status (HPA: antibodies). Cytoplasmic location is the UniProt expectation; an IF-specific staining pattern remains unverified here (UniProt Q9BXI3: cytoplasm).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive muscle control is blank.The assay may have lost detectable signal; high muscle-cell staining is expected from the reference observations (HPA: High in skeletal myocytes and cardiomyocytes).Confirm control morphology and reagent activity, then review primary dilution, retrieval, incubation and chromogenic detection as general IHC workflow checks. Do not infer a target-specific fixation effect from this result.
Staining appears mainly nuclear.The observed compartment conflicts with the cytoplasmic annotation (UniProt Q9BXI3: subcellular location). Counterstain overlap or nonspecific detection may complicate the reading (general IHC practice).Inspect the primary-free control and cytoplasmic detail at higher magnification; repeat with the IHC-validated antibody under its documented conditions if the compartment remains unclear (general IHC practice).
Strong color appears in adipocytes or marrow hematopoietic cells.Those cell types are listed as Not detected (HPA: tissue IHC). Cross-reactivity or a detection artifact is possible; the mismatch alone does not identify its cause.Compare a muscle-positive control and a no-primary control in the same run. Recheck cell identity and scoring boundaries before reporting unexpected cell-type expression (general IHC practice).
Color is diffuse or pools around tissue edges.Cell-independent color does not match the reported cytoplasmic pattern (HPA: tissue IHC profile; UniProt Q9BXI3: cytoplasm). Background can arise during blocking, washing or chromogen development (general IHC practice).Review the no-primary control, blocking, wash steps and development time; exclude edge deposits from cell-level scoring (general IHC practice).
Only membrane outlines seem positive.A membrane-only result is discordant with cytoplasmic localization and the lack of a transmembrane segment (UniProt Q9BXI3: location and topology).Check whether cytoplasm is also stained in known-positive myocytes. If it is not, review controls and repeat the IHC assessment before assigning the outline to NT5C1A (general IHC practice).
IF/ICC shows a pattern that differs from the IHC slide.The supplied HPA record has no ICC-IF image-bearing cell lines or assigned main IF location, and neither listed antibody has ICC status (HPA: subcellular record; HPA: antibodies).Treat the IF result as unverified by these records. Evaluate its own controls and cellular morphology; use cytoplasmic localization as a reference expectation, not as IF validation (UniProt Q9BXI3: cytoplasm).

Sample controls for NT5C1A IHC & IF

🧪Run skeletal muscle first; myocytes should show strong staining (HPA: High in skeletal-muscle myocytes). Use adipose tissue as the negative tissue; adipocytes should show no specific staining (HPA: Not detected in adipocytes). On the positive slide, nuclei should show counterstain without specific NT5C1A signal, while cells other than myocytes should be judged against background rather than assumed negative (UniProt Q9BXI3: Cytoplasm).
Positive control tissue: Heart muscle (Cardiomyocytes, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for NT5C1A; derive a cell-line control from the positive tissue's cell type (Cardiomyocytes) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control appropriate to the primary antibody’s clonality (selected-SKU caption: rabbit anti-NT5C1A); use NT5C1A knockout material as a biological specificity control if available. Quench endogenous peroxidase and check for background DAB staining in skeletal muscle (selected-SKU caption: peroxidase detection with DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU tissue-IHC caption does not state the fixative (selected-SKU caption: fixative not stated). The demonstrated paraffin-section workflow used heat retrieval in EDTA at pH 8.0, so retrieval should be kept consistent when comparing slides (selected-SKU caption: heat-mediated EDTA retrieval). The supplied evidence does not establish whether frozen sections or IF are easier for NT5C1A; for skeletal-muscle IHC, monitor endogenous peroxidase background alongside the expected cytoplasmic signal (HPA: High in skeletal-muscle myocytes; UniProt Q9BXI3: Cytoplasm; selected-SKU caption: DAB detection).

HPA tissue IHC evidence for NT5C1A

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes High Protein (IHC) HPA →
Skeletal muscle Myocytes High Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →
Cerebellum GLUC cells - cytoplasm/membrane Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Fallopian tube Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced NT5C1A IHC Tips

Use the catalog antibody’s paraffin section example and the expected cytoplasmic pattern to troubleshoot NT5C1A staining, then confirm conclusions with matched controls.

Which retrieval condition should I start with for weak NT5C1A staining?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A12036-2). The catalog antibody’s skeletal muscle example then used 2 μg/ml primary antibody overnight at 4°C, providing a documented starting point when comparing runs (datasheet A12036-2). If staining remains weak, compare a modest change in heating time on serial sections while holding antibody concentration and detection constant (standard IHC practice). Include a skeletal muscle positive control and inspect tissue morphology after heating; excessive retrieval can obscure whether stronger DAB reflects improved antigen access or tissue damage (HPA: High in skeletal myocytes; standard IHC practice).
Could fixation explain absent cytoplasmic staining in my paraffin sections?
The catalog image identifies paraffin-embedded human skeletal muscle but does not report its fixative, so NT5C1A-specific fixation sensitivity is unknown (datasheet A12036-2). Record the fixative, fixation duration and processing history for each specimen before comparing staining intensity (standard IHC practice). Run a matched positive control through the same processing conditions, then use EDTA retrieval at pH 8.0 and the documented 2 μg/ml primary concentration as initial conditions (datasheet A12036-2; standard IHC practice). If the control stains and the test section does not, examine preservation and tissue identity before assigning the difference to NT5C1A biology (standard IHC practice).
Where should convincing NT5C1A staining appear in tissue?
Score a predominantly cytoplasmic signal in the relevant cells, consistent with NT5C1A’s reported cytoplasmic location and absence of a transmembrane segment (UniProt Q9BXI3 subcellular location and topology). Skeletal myocytes and cardiomyocytes are useful positive compartments because their HPA tissue staining is High (HPA: High in skeletal myocytes and cardiomyocytes). HPA also describes cytoplasmic expression mainly in striated muscle and a subset of renal tubules, so assess individual cell populations instead of averaging whole sections (HPA: tissue IHC profile). Predominantly nuclear or sharply membrane-restricted DAB should prompt review of counterstain, section edges and no-primary controls before it is scored as specific (UniProt Q9BXI3 subcellular location; standard IHC practice).
Can isoforms or processing account for discordant NT5C1A staining?
The supplied UniProt record lists 0 isoforms and one chain spanning residues 1–368, with no signal peptide or propeptide (UniProt Q9BXI3 processing and isoforms). It also lists 0 glycosylation sites and 0 modified residues, so those annotations provide no specific explanation for a staining difference (UniProt Q9BXI3 PTMs). The antibody epitope is not supplied; do not assign a failed section to a particular epitope or claim that retrieval exposes one region preferentially (datasheet A12036-2: epitope not stated). Compare serial sections under the documented EDTA pH 8.0 retrieval condition and check a skeletal muscle control before investigating antibody specificity further (datasheet A12036-2; HPA: High in skeletal myocytes).
How should I adapt the tissue pattern for a multiplex IF experiment?
For an IF study, pair NT5C1A with a marker identifying skeletal myocytes or cardiomyocytes and look for cytoplasmic signal within the marker-defined cells (HPA: High in skeletal myocytes and cardiomyocytes; UniProt Q9BXI3 subcellular location). Because NT5C1A is cytoplasmic and has no transmembrane segment, include a controlled permeabilisation step in the IF workflow to give antibody access to the intracellular target (UniProt Q9BXI3 subcellular location and topology; standard IF practice). Choose a spectrally separated, preferably far-red channel after measuring tissue autofluorescence, and include single-stain and no-primary controls (standard IF practice). The paraffin section caption documents chromogenic IHC conditions; it supplies no IF fixation or dilution setting to transfer directly (datasheet A12036-2).
How can I reduce diffuse DAB staining without losing true cytoplasmic signal?
First compare the section with a no-primary control and check whether DAB accumulates at tissue edges or across cells lacking the expected cytoplasmic pattern (standard IHC practice; UniProt Q9BXI3 subcellular location). The catalog example used 10% goat serum blocking, 2 μg/ml primary overnight at 4°C, and a peroxidase-linked secondary for 30 minutes at 37°C (datasheet A12036-2). Include an endogenous peroxidase blocking step before HRP–DAB detection and keep DAB development time matched across slides (standard IHC practice). If background persists, titrate primary antibody and detection time on adjacent sections while retaining a skeletal muscle positive control (standard IHC practice; HPA: High in skeletal myocytes).
How should I quantify NT5C1A staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region of interest before scoring, then record cytoplasmic intensity and the percentage of positive cells separately (UniProt Q9BXI3 subcellular location; standard IHC practice). For a semiquantitative result, calculate an H-score from the percentages at intensity levels 0–3, giving a possible range of 0–300 (standard IHC practice). Normalise cell counts or stained area to the number of eligible cells or measured tissue area, and report the denominator for each region (standard IHC practice). Use matched processing, retrieval and DAB development, since staining intensity depends on those conditions; score renal tubule subsets separately from surrounding cells (standard IHC practice; HPA: cytoplasmic expression in a subset of renal tubules).
What distinguishes a true NT5C1A-positive cell from staining artefact?
A credible positive shows cytoplasmic staining in an identified cell population, with skeletal myocytes and cardiomyocytes providing strong tissue references (UniProt Q9BXI3 subcellular location; HPA: High in skeletal myocytes and cardiomyocytes). Treat nuclear-only, sharply membrane-restricted or edge-concentrated DAB cautiously, and exclude necrotic regions from scoring (UniProt Q9BXI3 subcellular location and topology; standard IHC practice). Compare no-primary and endogenous peroxidase controls when staining appears widespread, since HRP–DAB signal can arise outside antibody-specific detection (standard IHC practice). HPA rates its tissue profile Supported with medium staining–RNA consistency and pending external verification, so use concordant controls and cell-level morphology when interpreting unexpected positives (HPA: reliability description; standard IHC practice).
Boster reagents

Best NT5C1A / Cytosolic 5'-nucleotidase 1A IHC Antibodies

Anti-NT5C1A antibodies have IHC data from human skeletal muscle paraffin sections and IF data from A549 cells (catalog image captions); listed reactivity covers human and mouse (catalog reactivity).

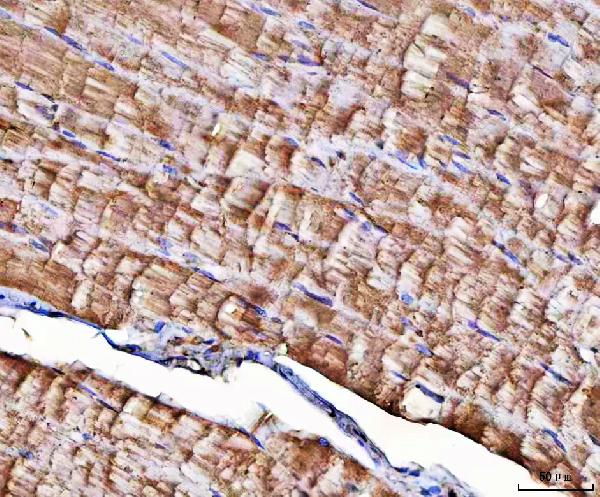
Real IHC data IHC analysis of NT5C1A using anti-NT5C1A antibody (A12036-2). NT5C1A was detected in a paraffin-embedded section of human skeletal muscle tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-NT5C1A Antibody (A12036-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-NT5C1A Antibody ®
Cat # A12036-2
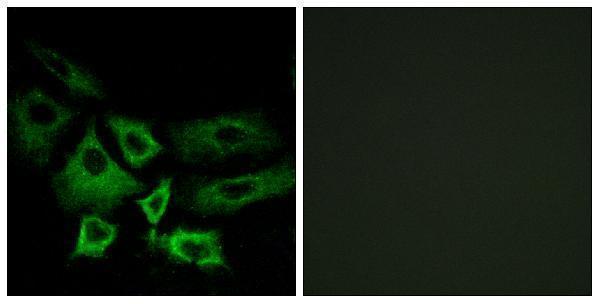
Real IF data Immunofluorescence analysis of A549 cells, using NT5C1A Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-Cytosolic 5'-nucleotidase 1A NT5C1A Antibody
Cat # A30631

A12036-2 has IHC data from a human skeletal muscle paraffin section (A12036-2 image caption). A30631 has IF data from A549 cells with a peptide-blocked comparison image; its listed reactivity is human and mouse (A30631 image caption; catalog reactivity).

Which to pick: Choose A12036-2 for chromogenic IHC on human paraffin sections: it is a rabbit polyclonal antibody listed for IHC, and its own image caption documents EDTA retrieval at pH 8.0, 2 μg/ml primary antibody and DAB detection (catalog applications; A12036-2 image caption). The caption does not report the fixative (A12036-2 image caption). Choose A30631 for IF/ICC or planned human and mouse work: it is a rabbit polyclonal antibody listed for IF/ICC and for human and mouse reactivity, while A12036-2 lists human reactivity only (catalog applications and reactivity); A30631 has no listed IHC validation (catalog applications).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9BXI3 (5NT1A_HUMAN, Cytosolic 5'-nucleotidase 1A).
  2. Human Protein Atlas. NT5C1A tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. NT5C1A subcellular location (ICC-IF): Highest expression in SH-SY5Y: 16.2 nTPM.
  4. Human Protein Atlas. NT5C1A antibody validation summary (2 antibodies).
  5. Cytosolic 5'-nucleotidase 1A is overexpressed in pancreatic cancer and mediates gemcitabine resistance by reducing intracellular gemcitabine metabolites. EBioMedicine 2019 — PMC6413477.
  6. Expression of gemcitabine metabolizing enzymes and stromal components reveal complexities of preclinical pancreatic cancer models for therapeutic testing. Neoplasia (New York, N.Y.) 2024 — PMC11109879.
  7. PubMed PMID:11133996 — UniProt-cited evidence.
  8. PubMed PMID:16710414 — UniProt-cited evidence.
  9. PubMed PMID:15489334 — UniProt-cited evidence.