This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan NUDT21 paraffin-section IHC around the reported cytoplasmic tissue pattern, with high staining in kidney tubule cells and parathyroid and stomach glandular cells (HPA tissue IHC). The catalog antibody lists an IHC dilution range of 1:50–1:200 (datasheet A09247); score intensity and compartment against matched controls (standard IHC practice).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic tissue staining (HPA tissue IHC); nuclear location (UniProt) | |
| Staining pattern | Broad cytoplasmic staining across tissues (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, heat-mediated (datasheet A09247) | |
| Positive control | Kidney+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific) | |
| Caveat | Staining reliability is uncertain; verify locally (HPA tissue IHC) | |
| Regulation | Low tissue RNA specificity (HPA tissue RNA) | |
| Isoform / epitope | 0 isoforms; no extracellular epitope domain (UniProt) |
Start with the catalog antibody’s IHC-P protocol (datasheet A09247), then compare the published breast tissue protocol (PMC7200255).
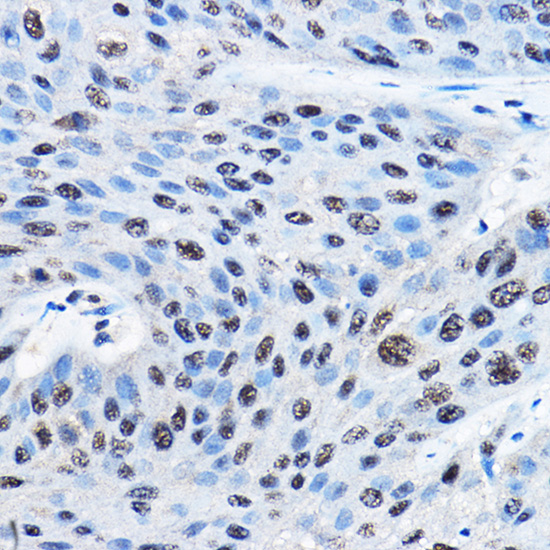
| Sample | Paraffin-embedded human esophageal cancer tissue; fixative not specified (datasheet A09247) |
| Fixation | Image fixative and duration unreported (datasheet A09247); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Citrate pH 6.0 (datasheet A09247); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-NUDT21, 1:50-1:200 (datasheet A09247) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | NUDT21-positive staining in cells in tubules of kidney (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control. |
NUDT21 is found in the nucleus and cytoplasm and has no transmembrane segment (UniProt O43809). In paraffin-section IHC, HPA describes a ubiquitous cytoplasmic pattern, with high staining in kidney tubule cells and parathyroid and stomach glandular cells (HPA tissue IHC). Interpret that pattern cautiously: HPA rates its tissue IHC reliability uncertain, citing medium agreement with RNA expression and pending external verification (HPA tissue IHC).
| Cell-associated cytoplasmic staining in kidney tubules or parathyroid or stomach glands, with clear tissue structure. | This matches HPA's high cell-specific IHC observations and its broad cytoplasmic profile (HPA tissue IHC). Compare intensity within a run rather than treating every cell as equally positive: HPA also reports medium, low and undetected cell populations (HPA tissue IHC). |
| Strong staining confined to cell membranes, luminal deposits or extracellular material. | This compartment does not match UniProt's nucleus/cytoplasm assignment or its lack of a transmembrane segment (UniProt O43809 topology). Treat it as a possible staining artefact and examine morphology and controls before scoring; nuclear staining alone is not a mismatch because nuclear localization is reported (UniProt O43809). |
| Strong signal in adipocytes or ovarian stromal cells, while expected positive cells are weak. | HPA reports NUDT21 as not detected in those cell populations (HPA tissue IHC). Unexpected staining raises cross-reactivity or endogenous detection activity as possibilities (standard IHC practice); it does not prove either, especially given HPA's uncertain tissue IHC reliability (HPA tissue IHC). |
| Brown signal spreads across stroma, empty spaces and many cell types without crisp cell boundaries. | Diffuse, noncellular signal is more consistent with background than a scorable intracellular pattern (standard chromogenic IHC practice; UniProt O43809 localization). Check a no-primary control and assess blocking, washing and detection conditions (standard IHC practice). HPA's broad expression alone cannot establish that diffuse staining is specific (HPA tissue IHC). |
| No signal in kidney tubule cells or parathyroid or stomach glandular cells. | These are reported high IHC populations, so an absent result warrants a run-level check (HPA tissue IHC). Confirm tissue preservation and the assay's positive control, then review antibody dilution, retrieval and detection as general IHC variables (standard IHC practice). HPA provides no NUDT21-specific retrieval or fixation rule. |
| Compartment reported by each method | HPA tissue IHC describes ubiquitous cytoplasmic expression, whereas UniProt lists nucleus and cytoplasm and describes shuttling (HPA tissue IHC; UniProt O43809). Score cytoplasmic IHC against the tissue profile without declaring nuclear signal biologically impossible. |
| IF/ICC Q: where should puncta appear? | A: HPA supports nuclear bodies as the main IF/ICC location; its additional centriolar-satellite assignment is uncertain (HPA subcellular ICC-IF). UniProt reports punctate subnuclear paraspeckles (UniProt O43809). Do not require individually resolved puncta in chromogenic tissue IHC. |
| Tissue and cell selection | Kidney tubules, parathyroid glands and stomach glands are reported high; adipocytes and ovarian stromal cells are reported not detected (HPA tissue IHC). Use cell identity within the section when assessing a result, since HPA's overall profile is broad (HPA tissue IHC). |
| Antibody-level validation | HPA019863 has an uncertain IHC assessment, while HPA074228 has supported ICC assessment and no listed IHC assessment (HPA antibodies). An IF validation label should not be carried over to paraffin-section IHC. |
| Topology and processing | UniProt reports no transmembrane segment or signal peptide and lists a chain spanning residues 2–227 (UniProt O43809 topology/processing). That record supports an intracellular expectation; it supplies no basis for a shed or secreted staining pattern. |
| Fixation sensitivity | A target-specific fixation effect is unreported in the supplied UniProt and HPA records. Assess retrieval and tissue processing through ordinary IHC controls (standard IHC practice); do not infer a NUDT21-specific fixation response from topology, modifications or tissue intensity. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive cells are blank across the run. | A staining-run failure is possible; HPA reports high signal in kidney tubules and parathyroid and stomach glandular cells (HPA tissue IHC). | Check an appropriate positive control, tissue integrity, primary-antibody application and detection reagents; review retrieval and dilution as general IHC variables (standard IHC practice). |
| Positive cells stain weakly but background is low. | The assay may be underdeveloped, or the sampled population may normally stain less strongly: HPA records medium and low populations alongside high ones (HPA tissue IHC). | Confirm the cell type first, then compare a reported high population in the same run; adjust detection or antibody conditions only against controls (HPA tissue IHC; standard IHC practice). |
| Diffuse brown haze obscures cell boundaries. | Nonspecific antibody binding, insufficient washing or endogenous detection activity can produce background (standard chromogenic IHC practice). | Inspect no-primary and detection controls; review blocking and washes before interpreting intensity (standard IHC practice). Do not score haze as HPA's cytoplasmic pattern (HPA tissue IHC). |
| Signal is concentrated at membranes or outside cells. | The location conflicts with reported nuclear/cytoplasmic localization and absence of a transmembrane segment (UniProt O43809). | Check morphology and controls, and compare another section or validated antibody when available (standard IHC practice). Record the compartment discrepancy before calling the section NUDT21-positive. |
| A reported negative population stains as strongly as the positive control. | Cross-reactivity or endogenous detection activity is possible (standard IHC practice); HPA's negative-cell calls carry the same uncertain tissue IHC reliability caveat (HPA tissue IHC). | Verify cell identity and no-primary control, then compare antibody-independent controls if available (standard IHC practice). Report the discordance rather than treating one HPA call as definitive. |
| IF/ICC shows nuclear puncta but tissue IHC looks mostly cytoplasmic. | The methods have different reported observations: HPA supports nuclear bodies in ICC-IF and describes cytoplasmic tissue IHC (HPA subcellular ICC-IF; HPA tissue IHC). | Interpret each image against its own method and antibody validation status; do not use puncta as a required chromogenic IHC scoring feature (HPA antibodies; standard IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Kidney | Cells in tubules | High | Protein (IHC) | HPA → |
| Parathyroid gland | Glandular cells | High | Protein (IHC) | HPA → |
| Stomach | Glandular cells | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Ovary | Ovarian stroma cells | Not detected | Protein (IHC) | HPA → |
| Soft tissue | Fibroblasts | Not detected | Protein (IHC) | HPA → |
| Vagina | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot NUDT21 staining in paraffin sections by checking retrieval, compartment, tissue context and controls before comparing chromogenic scores.
The IHC-validated antibody has an image from a human esophageal cancer paraffin section; the catalog also lists human, mouse, and rat reactivity and IF/ICC applications for another SKU (catalog applications; A09247 IHC image caption).
A09247 will render with its IHC image from a human esophageal cancer paraffin section (A09247 IHC image caption). A09247-1 is listed for IHC and IF/ICC in human, mouse, and rat, but has no supplied IHC or IF image and will not render as a card (catalog applications, reactivity, and image captions).
Which to pick: Choose A09247 for paraffin-section tissue IHC because its own image shows that use with citrate pH 6.0 retrieval; the fixative is unreported (A09247 IHC image caption). For IF/ICC, consider A09247-1 because those applications are listed, although no IF image is supplied (catalog applications and image captions). Both rabbit polyclonal antibodies list human, mouse, and rat reactivity, but the supplied tissue image documents human IHC only (catalog host, clone, and reactivity; A09247 IHC image caption).