NUP50 / Nuclear pore complex protein Nup50 · IHC design guide

Design Immunohistochemistry for NUP50

Plan chromogenic IHC for NUP50 using its ubiquitous nuclear tissue staining as the expected pattern (HPA tissue IHC). Compare sections with consistent fixation and account for changes in nuclear pore association during mitosis (standard IHC practice; UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for NUP50 (IHC for NUP50): expected localisation Nuclear staining (HPA tissue IHC); NPC association (UniProt), antibody A06152-1, validated IHC image, and IHC protocol steps
Printable NUP50 IHC protocol sheet — expected localisation Nuclear staining (HPA tissue IHC); NPC association (UniProt), antibody A06152-1, controls and protocol steps. Open the full NUP50 IHC guide →

NUP50 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining (HPA tissue IHC); NPC association (UniProt)
Staining pattern Nuclei across many cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A06152-1)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat NPC association changes during mitosis (UniProt)
Regulation Highest in testis and leukocytes (UniProt)
Isoform / epitope 2 isoforms; check epitope coverage (UniProt)
Section 1

Recommended NUP50 IHC & IF Protocols

The catalog antibody protocol is paired with published NUP50 IHC methods for sarcoma and lung adenocarcinoma tissue sections (PMC7573283; PMC13279022).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat testis tissue; fixative not specified (datasheet A06152-1)
FixationImage fixative and duration unreported (datasheet A06152-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A06152-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A06152-1)
Primary antibodyRabbit anti-NUP50, 2-5 μg/ml (datasheet A06152-1)
Primary incubationOvernight at 4 °C (datasheet A06152-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A06152-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultNUP50-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet A06152-1); the lung adenocarcinoma method also specifies EDTA, without a pH (PMC13279022).
Section 2

What Is the Expected NUP50 Staining Pattern?

In paraffin-section IHC, expect predominantly nuclear NUP50 staining across many cell types (HPA: ubiquitous nuclear expression; reliability Enhanced, with medium consistency between staining and RNA data). Nuclear membrane and nucleoplasmic localization are consistent with the protein record (UniProt Q9UKX7: nuclear pore complex and nucleus membrane; no transmembrane segment). Interpret intensity by cell type: HPA reports high staining in several epithelial and neuronal populations, and low staining in selected muscle cells and cholangiocytes (HPA: tissue IHC).

What am I looking at on my slide?
Nuclear staining in glandular cells of appendix, breast, cervix or colon, or in bronchial respiratory epithelium.This matches reported high staining in these cells (HPA: tissue IHC). Judge chromogenic signal within nuclei against the counterstain and neighboring background (general IHC practice). Nuclear signal is consistent with NUP50 localization (UniProt Q9UKX7: nucleus and nuclear pore complex).
Nuclear staining in caudate or cerebral cortex neurons, or cerebellar Purkinje cells.These are additional reported high-staining populations (HPA: tissue IHC). A nuclear pattern supports the expected localization (UniProt Q9UKX7: nucleus and nuclear pore complex). High describes HPA observations; it does not set a universal intensity threshold for every section (HPA: tissue IHC; general IHC practice).
Strong, predominantly cytoplasmic or extracellular deposit with little convincing nuclear staining.That distribution conflicts with the reported nuclear pattern (HPA: ubiquitous nuclear expression; UniProt Q9UKX7: nuclear pore localization). Treat it as possible nonspecific staining or detection artifact and assess controls before assigning it to NUP50 (general IHC practice).
An unexpected cell population stains strongly while nearby expected nuclei remain weak, or color extends beyond cell boundaries.Check cell identity and section morphology before calling the population truly positive (general IHC practice). HPA reports widespread expression, so an unlisted cell type alone does not prove cross-reactivity (HPA: ubiquitous nuclear expression). Antibody cross-reactivity or endogenous detection activity remains possible when controls show the same deposit (general IHC practice).
Diffuse color obscures nuclei, or no nuclear signal appears in a reported high-staining tissue.Diffuse background makes compartment assignment unreliable (general IHC practice). An absent signal in a reported high-staining cell population calls for review of the stain and controls before a biological negative call (HPA: tissue IHC; general IHC practice). HPA reliability is Enhanced, with medium staining–RNA consistency (HPA: tissue IHC).
💡Expected NUP50 appearanceCall a result positive when chromogenic signal is clearly nuclear in the relevant cells, with strong examples in HPA-listed glandular, respiratory epithelial or neuronal populations (HPA: tissue IHC); broad cytoplasmic or extracellular color without nuclear definition is suspect (HPA: ubiquitous nuclear expression; general IHC practice).
How each factor affects the staining
Cell type and tissueHPA reports high staining in listed glandular, respiratory epithelial and neuronal cells, but low staining in liver cholangiocytes, cardiomyocytes and skeletal myocytes (HPA: tissue IHC). Low-staining populations are weak comparators, not established negative controls (HPA: tissue IHC; general IHC practice).
Subcellular distributionNUP50 is assigned to the nucleus, nuclear pore complex and nucleus membrane; it has no transmembrane segment (UniProt Q9UKX7: subcellular location and topology). Evaluate a nuclear compartment pattern rather than expecting a cell-surface outline (UniProt Q9UKX7: localization; general IHC practice).
Antibody evidenceHPA047162 has Enhanced IHC validation; HPA048328 has Enhanced ICC validation but no IHC status in this payload (HPA: antibody validation). Validation supports interpretation of the reported application and does not establish identical performance for another antibody (HPA: antibody validation; general IHC practice).
Isoforms and processingUniProt lists 2 isoforms and a single 1–468 protein chain, with no signal peptide or propeptide (UniProt Q9UKX7: isoforms and processing). Without an antibody epitope, these facts cannot establish which isoform a stain detects (UniProt Q9UKX7: isoforms; general IHC practice).
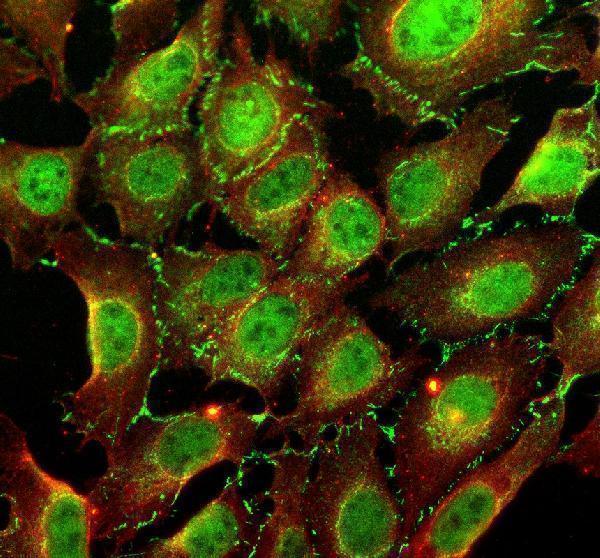
IF/ICC Q&A: what pattern should be expected?Nucleoplasm and nuclear membrane are both Enhanced HPA ICC-IF locations; images are listed for MCF-7, PC-3, U2OS and HEK293 (HPA: subcellular ICC-IF). This supports a localization check, while IF/ICC setup belongs to its separate guide (HPA: subcellular ICC-IF).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A reported high-staining glandular or neuronal population has no nuclear color.A failed stain or detection step is possible; one negative section cannot override the reported high pattern (HPA: tissue IHC; general IHC practice).Review a same-run positive tissue control, antibody application, retrieval conditions and detection reagents; then repeat the stain if the control failed (general IHC practice).
Only cytoplasm stains strongly while nuclei remain clear.The compartment conflicts with NUP50 localization (UniProt Q9UKX7: nucleus and nuclear pore complex; HPA: ubiquitous nuclear expression).Compare a known high-staining tissue and a no-primary control, and reassess antibody specificity before scoring that color as NUP50 (HPA: tissue IHC; general IHC practice).
A no-primary control develops color in the same unexpected cells.Endogenous detection activity or nonspecific detection chemistry is possible (general IHC practice).Check the control, endogenous-activity blocking and detection reagents before interpreting the test section (general IHC practice).
Diffuse color or precipitate masks nuclear boundaries.Background staining or deposited chromogen can prevent reliable localization (general IHC practice).Inspect the no-primary control and staining run; optimize blocking, washing or detection development according to the assay controls (general IHC practice).
Cholangiocytes, cardiomyocytes or skeletal myocytes stain faintly.Low staining is reported for these populations (HPA: tissue IHC). Faint nuclear signal alone need not indicate assay failure (HPA: tissue IHC; general IHC practice).Assess their nuclei alongside a reported high-staining population in the same run; avoid treating these low-staining cells as absolute negatives (HPA: tissue IHC; general IHC practice).
An antibody shows a pattern different from the reported HPA IHC pattern.The listed Enhanced IHC status applies to HPA047162; HPA048328 has no IHC status in the supplied record (HPA: antibody validation).Confirm the antibody's IHC validation, examine positive and no-primary controls, and score only convincing cellular and nuclear signal (HPA: antibody validation; general IHC practice).

Sample controls for NUP50 IHC & IF

🧪Run appendix first and assess its glandular cells for NUP50 staining (HPA: High in appendix glandular cells). HPA detects NUP50 in all 45 scored tissues, so there is no HPA-supported negative tissue; use no-primary and isotype controls, and expect any locally unstained cells on the positive slide to retain counterstain without nuclear DAB signal rather than treating them as validated negative cells (HPA: no negative tissue rows).
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: None in HPA: NUP50 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show NUP50 in MCF-7, PC-3, U2OS, HEK293, with annotated localisation: Nucleoplasm (enhanced), Nuclear membrane (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a concentration-matched rabbit IgG isotype control, and a matched NUP50 knockout specimen if available (selected-SKU caption: rabbit primary antibody). In appendix sections, quench endogenous peroxidase and check that blood or inflammatory-cell background does not mimic DAB staining (HPA: appendix glandular cells High; selected-SKU caption: HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative unreported). That caption documents heat retrieval in EDTA at pH 8.0, providing a starting condition without establishing that retrieval is required (selected-SKU caption: EDTA retrieval, pH 8.0). IF/ICC images support evaluating nucleoplasmic and nuclear-membrane localization on its own guide page, but the supplied evidence does not show that IF or frozen sections are easier than paraffin IHC (HPA subcellular: nucleoplasm and nuclear membrane; selected-SKU caption: paraffin-section IHC).

HPA tissue IHC evidence for NUP50

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: NUP50 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced NUP50 IHC Tips

Troubleshoot NUP50 chromogenic IHC by checking retrieval, nuclear localization, and controls before comparing staining across sections.

Which retrieval conditions should I try when nuclear NUP50 staining is weak?
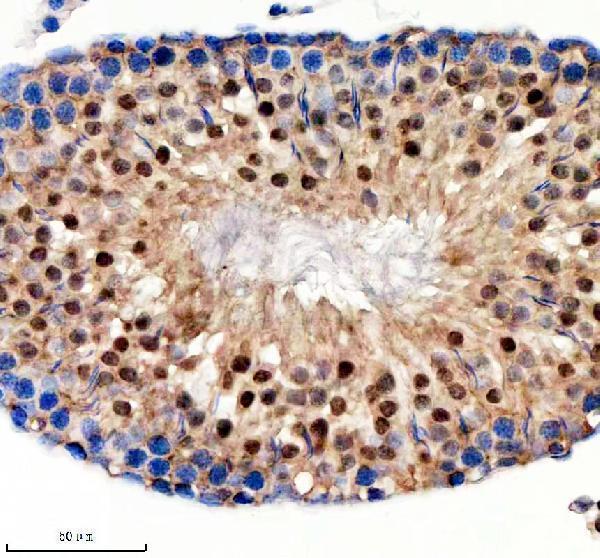
Start with heat-mediated retrieval in EDTA, pH 8.0, for paraffin sections (datasheet A06152-1). The selected rat testis image used that retrieval, followed by 10% goat-serum block and 2 μg/ml antibody overnight at 4°C (caption A06152-1). If staining remains weak, vary heating duration in a small, matched section series before considering another buffer as a fallback (general IHC practice). Keep detection exposure and DAB development identical across sections, then judge nuclear signal against a no-primary control and intact tissue morphology (general IHC practice; HPA: ubiquitous nuclear expression). Include an unstained serial section to assess intrinsic pigment before changing retrieval conditions (general IHC practice).
How should I troubleshoot fixation-related loss of NUP50 staining in paraffin sections?
The selected paraffin-section caption does not state its fixative, so NUP50-specific fixation sensitivity is unknown (caption A06152-1). For a controlled pilot, process matched tissue pieces with documented fixation intervals, such as 6 h and 24 h in neutral-buffered formalin, while holding embedding and section thickness constant (general IHC practice). Apply the same EDTA, pH 8.0 heat retrieval and antibody conditions to both groups (datasheet A06152-1; general IHC practice). Compare nuclear staining with morphology and no-primary controls; a difference identifies a preparation-dependent effect in that pilot, not an established property of NUP50 (general IHC practice).
Does diffuse nuclear staining contradict NUP50's nuclear-pore assignment?
No: chromogenic NUP50 signal can be assessed at the nuclear rim and within nuclei, since the record places it at the nuclear pore and HPA also reports nucleoplasm and nuclear membrane (UniProt Q9UKX7 subcellular; HPA subcellular). In testis, reported localization shifts from nuclear surface in spermatocytes to nuclear interior in spermatids and back at the spermatozoon nuclear surface (UniProt Q9UKX7, by similarity). Score these compartments separately in intact cells, using a 2 μg/ml overnight stain as the selected image's starting condition (caption A06152-1). Treat isolated cytoplasmic DAB without matching nuclear signal cautiously and check the no-primary section (HPA: ubiquitous nuclear expression; general IHC practice).
Could isoforms or epitope masking explain discordant NUP50 staining?
NUP50 has 2 recorded isoforms and multiple modified residues, including phosphoserines at positions 52 and 208 (UniProt Q9UKX7 isoforms and modified residues). An antibody's ability to distinguish those isoforms or modifications cannot be inferred without its epitope map (general IHC interpretation). First repeat the catalog antibody's EDTA, pH 8.0 heat retrieval on matched sections and compare nuclear compartments under identical DAB development (datasheet A06152-1; general IHC practice). If staining remains discordant, use an independently validated antibody with a documented, distinct epitope and compare staining patterns, without claiming isoform-specific expression from one chromogenic reagent (general IHC practice).
How can parallel IF help assess NUP50 staining seen by chromogenic IHC?
Use IF/ICC as a parallel localization check: HPA reports enhanced nucleoplasmic and nuclear-membrane localization in cell images, including MCF-7, PC-3, U2OS and HEK293 (HPA subcellular). For tissue multiplexing, pair NUP50 with a validated marker of the expected cell type, such as a glandular-cell marker where glandular staining is expected (HPA: high in appendix glandular cells; general IF practice). Select a far-red fluorophore when shorter-wavelength tissue autofluorescence interferes, and include single-stain and no-primary controls (general IF practice). Permeabilise sufficiently for nucleoplasmic epitopes while preserving the nuclear rim; NUP50 has no transmembrane segment or assigned luminal side (UniProt Q9UKX7 topology; general IF practice).
What should I check if DAB obscures NUP50 nuclear staining?
Inspect a no-primary section for nonspecific secondary or detection chemistry and a peroxidase-block control for endogenous enzyme signal (general chromogenic IHC practice). In the selected rat testis image, the antibody was applied at 2 μg/ml overnight at 4°C, followed by peroxidase-linked detection and DAB (caption A06152-1). Titrate primary concentration and shorten DAB development in matched sections if broad brown deposition masks nuclear detail, keeping retrieval at EDTA, pH 8.0 initially (datasheet A06152-1; general IHC practice). Compare nuclear signal with the no-primary section and morphology; edge-concentrated or necrotic staining alone does not establish NUP50 localization (HPA: ubiquitous nuclear expression; general IHC practice).
How should I score NUP50 when nuclear rim and nucleoplasm both stain? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scoring unit as morphologically intact, identified cells and record nuclear-rim and nucleoplasmic DAB separately when resolution permits (HPA subcellular; general IHC practice). For each compartment, report the percentage of positive cells and an H-score from 0–300 using intensity grades 0–3, with the threshold set from control sections (general IHC practice). Normalize positive-cell counts to the number of eligible cells in each annotated cell population, or report positive-cell density per mm² of viable tissue (general IHC practice). Keep retrieval at EDTA, pH 8.0 and DAB exposure consistent across compared slides, since processing shifts alter apparent intensity (datasheet A06152-1; general IHC practice).
Which staining patterns support true NUP50 positivity rather than artefact?
Give greatest weight to reproducible nuclear-rim or nucleoplasmic DAB in intact cells, because NUP50 is assigned to nuclear pores and HPA reports both nuclear compartments (UniProt Q9UKX7 subcellular; HPA subcellular). High signal in glandular cells can support expected distribution, while low signal in cholangiocytes, cardiomyocytes or myocytes is not automatically assay failure (HPA tissue IHC). Check a no-primary and peroxidase-block section, and discount isolated necrotic, tissue-edge or diffuse cytoplasmic pigment (general IHC practice). Finally, compare matched sections retrieved in EDTA, pH 8.0; HPA's tissue reliability is Enhanced with medium staining–RNA consistency, so concordance alone is insufficient validation (datasheet A06152-1; HPA tissue IHC).
Boster reagents

Best NUP50 / Nuclear pore complex protein Nup50 IHC Antibodies

NUP50 has paraffin-section IHC data in rat testis and IF data in rat testis and U2OS cells (A06152-1 image captions); catalog reactivity includes human, mouse, and rat (catalog reactivity).

Real IHC data IHC analysis of NUP50 using anti-NUP50 antibody (A06152-1). NUP50 was detected in a paraffin-embedded section of rat testis tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-NUP50 Antibody (A06152-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-NUP50 Antibody ®
Cat # A06152-1

A06152-1 has IHC and IF images from rat testis paraffin sections and an IF image from U2OS cells (A06152-1 image captions); M06152 lists IF/ICC, with no supplied staining image (M06152 catalog applications and image captions). M06152-1 lists IHC and IF/ICC for human, mouse, and rat, with no supplied staining image (M06152-1 catalog applications, reactivity, and image captions).

Which to pick: Choose A06152-1 for tissue IHC: its rat testis image documents a paraffin section with EDTA retrieval at pH 8.0 and primary antibody at 2 μg/ml; the fixative is unreported (A06152-1 IHC caption). For IF/ICC, A06152-1 has images from U2OS cells and rat testis, while monoclonal M06152 and M06152-1 list IF/ICC without supplied images (A06152-1 IF captions; M06152 and M06152-1 catalog applications and image captions). All three list human, mouse, and rat reactivity, but the supplied IHC image documents rat tissue only (catalog reactivity; A06152-1 IHC caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9UKX7 (NUP50_HUMAN, Nuclear pore complex protein Nup50).
  2. Human Protein Atlas. NUP50 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. NUP50 subcellular location (ICC-IF): Localized to the nucleoplasm and nuclear membrane..
  4. Human Protein Atlas. NUP50 antibody validation summary (2 antibodies).
  5. Identification of Subtype-Specific Metastasis-Related Genetic Signatures in Sarcoma. Frontiers in oncology 2020 — PMC7573283.
  6. Nuclear pore pathology underlying multisystem proteinopathy type 3-related inclusion body myopathy. Annals of clinical and translational neurology 2024 — PMC10963302.
  7. Role and insights of human papillomavirus E5 oncoprotein in cervical carcinogenesis. Experimental and therapeutic medicine 2026 — PMC13389621.
  8. GALNT7-induced O-glycosylation of NUP50 activates fatty acid β-oxidation to promote lung adenocarcinoma metastasis. The Journal of biological chemistry 2026 — PMC13279022.
  9. PubMed PMID:10449902 — UniProt-cited evidence.
  10. PubMed PMID:15461802 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.