ORC2 / Origin recognition complex subunit 2 · IHC design guide

Design Immunohistochemistry for ORC2

Plan chromogenic ORC2 IHC in paraffin sections using pachytene spermatocyte nuclei as a positive reference (HPA tissue IHC). Start with the catalog antibody at 2–5 μg/ml (datasheet A04350-1) and keep fixation consistent across sections (standard IHC practice).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ORC2 (IHC for ORC2): expected localisation Nuclear staining in seminiferous duct cells (HPA tissue IHC), antibody A04350-1, validated IHC image, and IHC protocol steps
Printable ORC2 IHC protocol sheet — expected localisation Nuclear staining in seminiferous duct cells (HPA tissue IHC), antibody A04350-1, controls and protocol steps. Open the full ORC2 IHC guide →

ORC2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in seminiferous duct cells (HPA tissue IHC)
Staining pattern High nuclear staining in pachytene spermatocytes (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A04350-1)
Positive control ⓘ Testis
Negative control ⓘ Adrenal gland+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining has medium consistency with RNA expression (HPA tissue IHC)
Regulation Expression regulation is unreported (UniProt)
Isoform / epitope 0 isoforms; no annotated processing that shifts epitopes (UniProt)
Section 1

Recommended ORC2 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: A04350-1) is accompanied by two published ORC2 IHC protocols for paraffin sections (PMC12048666; PMC9972100).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded diffuse large B-cell lymphoma of human intestine tissue; fixative not specified (datasheet A04350-1)
FixationImage fixative and duration unreported (datasheet A04350-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A04350-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A04350-1)
Primary antibodyRabbit anti-ORC2, 2-5 μg/ml (datasheet A04350-1)
Primary incubationOvernight at 4 °C (datasheet A04350-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A04350-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultORC2-positive staining in pachytene spermatocytes of testis (HPA tissue IHC: High). HPA tissue profile: High nuclear expression in cells of seminiferous ducts. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet: A04350-1); the published citric acid pH 6.0 method used a different antibody (PMC9972100).
Section 2

What Is the Expected ORC2 Staining Pattern?

ORC2 should show predominantly nuclear staining in pachytene spermatocytes within testicular seminiferous ducts (HPA: high nuclear expression in these cells). UniProt places ORC2 in the nucleus and reports no transmembrane segment (UniProt Q13416: subcellular location and topology). The HPA tissue IHC assessment is Enhanced, with medium consistency between antibody staining and RNA expression (HPA: reliability).

What am I looking at on my slide?
Strong nuclear staining in pachytene spermatocytes, with nuclei identifiable by counterstain.This matches the reported high signal in these testicular cells and the nuclear tissue pattern (HPA: testis IHC). Compare cells within the seminiferous ducts before scoring a section as positive; staining elsewhere does not substitute for this reference pattern (HPA: testis IHC).
Predominantly membrane or extracellular staining, with little nuclear signal.This is discordant with the nuclear IHC pattern (HPA: tissue IHC) and with ORC2's nuclear location and lack of a transmembrane segment (UniProt Q13416). Review staining and detection controls before interpreting it as ORC2; compartment mismatch alone does not identify the source of the signal (general IHC practice).
Strong staining in adrenal glandular or bronchial respiratory epithelial cells.HPA reports ORC2 as not detected in these cell populations (HPA: adrenal gland and bronchus IHC). If staining persists, investigate antibody cross-reactivity or endogenous detection activity using appropriate controls; a single discordant section cannot distinguish those causes (general IHC practice).
Uniform haze over nuclei, cytoplasm, and tissue-free areas.A diffuse field lacks the cell-restricted nuclear pattern reported in testis (HPA: testis IHC). Excess background from staining or detection can obscure a specific signal; inspect the omitted-primary control and assess washing and reagent concentration (general IHC practice).
No nuclear signal in morphologically identifiable pachytene spermatocytes.This conflicts with the reported high staining of those cells (HPA: testis IHC), but does not by itself show that ORC2 is absent. Check whether a positive control stained and whether the section contains the relevant cell population before interpreting the result (general IHC practice).
💡Expected ORC2 appearanceCall the result consistent with ORC2 when staining is high and nuclear in pachytene spermatocytes (HPA: testis IHC); dominant membrane staining or uniform haze is discordant with that pattern (HPA: tissue IHC; UniProt Q13416 topology).
How each factor affects the staining
Cell population and tissueHPA reports high staining in testicular pachytene spermatocytes, low staining in several other listed cell types, and no detection in others (HPA: tissue IHC). Score the identified population; a whole-section average can hide this difference (general IHC practice).
CompartmentNuclear tissue staining agrees with UniProt's nuclear location (HPA: tissue IHC; UniProt Q13416). ORC2 has no annotated transmembrane segment, so dominant membrane staining warrants scrutiny (UniProt Q13416 topology).
Antibody validationThe tissue IHC assessment is Enhanced, yet staining has only medium consistency with RNA expression (HPA: tissue IHC reliability). CAB003693 has Enhanced IHC validation; HPA073881 has no listed IHC validation status (HPA: antibody validation). Apply those qualifications to antibody-specific conclusions.
Biological contextORC2 is part of the origin recognition complex involved in replication initiation, whose assembly is cell-cycle dependent (UniProt Q13416). This supports attention to cell identity, but supplies no IHC intensity threshold for a cell-cycle stage (UniProt Q13416; HPA: testis IHC).
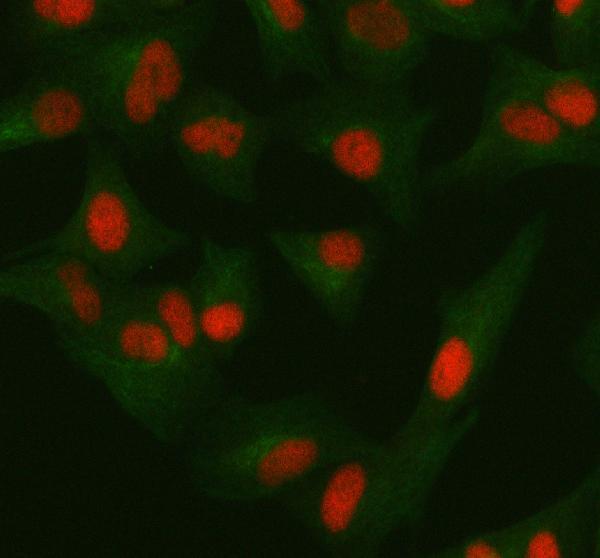
IF/ICC question: where should signal appear?Mainly in nucleoplasm, with an additional approved cytosolic location (HPA: subcellular ICC-IF). This answers the compartment question for IF/ICC; the primary slide interpretation here uses the nuclear tissue IHC pattern (HPA: testis IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Testis section has no convincing nuclear staining.The sampled area may lack identifiable pachytene spermatocytes, or the staining run may have failed (HPA: testis IHC; general IHC practice).Locate the relevant cells by morphology and counterstain, then compare with a positive-control section processed in the same run (general IHC practice).
All nuclei are dark, including cells outside the expected pattern.Overdeveloped detection or excess nonspecific staining can conceal cell-level differences (general IHC practice); HPA reports its strongest testicular signal in pachytene spermatocytes (HPA: testis IHC).Review detection time and primary-antibody concentration using the chosen IHC protocol, then compare an omitted-primary control (general IHC practice).
Adrenal glandular cells stain strongly.The result conflicts with HPA's not-detected observation for that cell type (HPA: adrenal gland IHC); cross-reactivity or endogenous detection activity is possible (general IHC practice).Run omitted-primary and relevant detection controls; check whether staining is nuclear and reproducible before assigning it to ORC2 (general IHC practice).
Staining is strongest at membranes or tissue edges.That distribution conflicts with nuclear tissue staining and ORC2's lack of a transmembrane segment (HPA: tissue IHC; UniProt Q13416 topology). Edge-localized signal can arise during staining (general IHC practice).Inspect an omitted-primary control and interior tissue; reassess blocking, washing, and detection conditions if the edge pattern persists (general IHC practice).
A negative reference section stains faintly.Some listed cell populations have low staining, while others are not detected (HPA: tissue IHC); faint signal alone cannot establish a false positive.Identify and score the exact cell population against its HPA category, then compare compartment and control-slide background (HPA: tissue IHC; general IHC practice).
IF/ICC shows cytosolic signal alongside nucleoplasmic signal.HPA lists nucleoplasm as the main supported location and cytosol as an additional approved location in ICC-IF (HPA: subcellular ICC-IF).Interpret the IF/ICC image using those compartment annotations; evaluate paraffin-section IHC against the reported nuclear tissue pattern (HPA: subcellular ICC-IF; HPA: tissue IHC).

Sample controls for ORC2 IHC & IF

🧪Run testis first and score pachytene spermatocytes for nuclear staining; HPA reports High ORC2 in these cells (HPA: High in testis pachytene spermatocytes; UniProt Q13416: nucleus). Use adrenal gland glandular cells as the negative tissue (HPA: Not detected in adrenal gland glandular cells); on the testis slide, treat cells without nuclear signal as internal negative cells only after confirming their background matches the controls.
Positive control tissue: Testis (Pachytene spermatocytes, HPA High)
Negative control tissue: Adrenal gland (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ORC2 in A-431, U-251MG, U2OS, HEK293, Hep-G2, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control alongside an ORC2-knockout biological negative (selected-SKU caption: rabbit primary antibody; standard IHC controls). For DAB detection, quench endogenous peroxidase and assess background in the testis section (selected-SKU caption: peroxidase detection with DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact A04350-1 tissue-IHC caption does not state a fixative (selected-SKU caption: fixative not stated). The reported paraffin-section staining used heat retrieval in EDTA at pH 8.0; this shows a workable retrieval condition, but does not establish that retrieval is required (selected-SKU caption: EDTA retrieval at pH 8.0). The evidence does not establish whether frozen sections or IF/ICC are easier; in testis, score the densely packed germ-cell nuclei by cell type and compare nuclear signal with background controls (HPA: High in pachytene spermatocytes; standard IHC practice).

HPA tissue IHC evidence for ORC2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Testis Pachytene spermatocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced ORC2 IHC Tips

ORC2 is a nuclear replication complex component (UniProt Q13416). Use compartment, tissue controls, and matched processing to troubleshoot chromogenic IHC.

How should I retrieve ORC2 in paraffin sections when nuclear staining is weak?
Start with heat-mediated retrieval in EDTA pH 8.0 (datasheet A04350-1). The catalog antibody detected ORC2 in a paraffin section of diffuse large B-cell lymphoma of human intestine after that retrieval, with 2 μg/ml primary antibody overnight at 4°C (datasheet A04350-1). If nuclear staining remains weak, check heating consistency and section adhesion before comparing an alternative retrieval condition on adjacent sections (standard IHC practice). Keep detection and exposure conditions matched during that comparison so a change in nuclear signal can be attributed to retrieval (standard IHC practice). Judge improvement against nuclear, rather than diffuse cytoplasmic, staining because ORC2 is nuclear (UniProt Q13416).
Could fixation explain weak ORC2 staining in my paraffin sections?
ORC2-specific sensitivity to fixation is unknown: the selected tissue-IHC caption calls the section paraffin-embedded but does not state its fixative (datasheet A04350-1). Record the fixative and processing history for each specimen, and compare sections processed together when investigating weak nuclear staining (standard IHC practice). Start with the documented EDTA pH 8.0 retrieval and 2 μg/ml primary antibody overnight at 4°C before changing one preparation variable at a time (datasheet A04350-1; standard IHC practice). Include a tissue control with expected nuclear signal in each run, since loss of staining across specimens can indicate a shared processing or detection problem (HPA tissue IHC; standard IHC practice).
Should I accept cytoplasmic ORC2 staining as a positive IHC result?
Prioritise nuclear staining: ORC2 is assigned to the nucleus (UniProt Q13416), and tissue IHC reports high nuclear expression in pachytene spermatocytes (HPA tissue IHC). Cell-based imaging places ORC2 mainly in the nucleoplasm and additionally in the cytosol (HPA subcellular). A cytoplasmic IHC signal therefore needs separate validation; compare its distribution with nuclear signal, a no-primary control, and similarly processed sections (HPA subcellular; standard IHC practice). Score nuclear and cytoplasmic compartments separately instead of combining them into one positive call (standard IHC practice). ORC2 has no annotated transmembrane segment, so a crisp membrane-only pattern warrants investigation (UniProt Q13416).
How can I distinguish epitope loss from an ORC2 isoform effect?
The record annotates 0 isoforms and one chain spanning residues 1–577; it does not establish the catalog antibody’s epitope (UniProt Q13416; datasheet A04350-1). ORC2 has annotated phosphorylation sites, including residues 116, 122, and 138, but their effect on this antibody’s staining is unknown (UniProt Q13416). First repeat the documented EDTA pH 8.0 retrieval on a matched positive control, then compare any alternative retrieval on adjacent sections (datasheet A04350-1; standard IHC practice). Avoid attributing a changed signal to a particular isoform or modification without epitope mapping or independent validation (standard IHC practice).
How should I adapt ORC2 localisation checks to multiplex IF?
In IF, pair ORC2 with a validated marker for the expected cell type, such as a pachytene spermatocyte marker when examining testis, and include a nuclear counterstain (HPA tissue IHC; standard IF practice). Assign ORC2 and the cell marker spectrally distinct fluorophores; consider a far-red ORC2 channel if the specimen shows shorter-wavelength autofluorescence (standard IF practice). Permeabilise sufficiently for antibody access to the nucleoplasm, since ORC2 is mainly nucleoplasmic and has no annotated transmembrane segment (HPA subcellular; UniProt Q13416; standard IF practice). Check single-stain and no-primary controls before calling colocalisation, and assess any cytosolic ORC2 signal separately (HPA subcellular; standard IF practice).
What should I check when ORC2 DAB staining is diffuse or granular?
Compare the stained section with a no-primary control to assess secondary reagent and chromogen background (standard IHC practice). For peroxidase detection, include an endogenous peroxidase block and inspect whether DAB appears outside cell nuclei; these are general chromogenic workflow checks (standard IHC practice). The catalog example used a peroxidase-conjugated secondary for 30 minutes at 37°C and DAB development after 2 μg/ml primary antibody overnight at 4°C (datasheet A04350-1). Review blocking, washing, and development consistency across adjacent sections before interpreting diffuse staining as ORC2, whose tissue signal is expected to be nuclear (UniProt Q13416; HPA tissue IHC; standard IHC practice).
How should I score variable ORC2 nuclear staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and score the percentage of ORC2-positive nuclei, with intensity recorded separately or combined as a nuclear H-score (standard IHC practice). Normalise counts or positive-cell density per mm² to viable tissue area or to the number of evaluable nuclei, and apply the same threshold across sections (standard IHC practice). Exclude folds, necrotic areas, and poorly preserved edges before scoring, using matched staining and imaging settings for comparisons (standard IHC practice). Report nuclear and cytoplasmic measurements separately because ORC2 is nuclear in the protein record, while cell-based imaging also supports some cytosolic localisation (UniProt Q13416; HPA subcellular).
When is an apparent ORC2-positive cell likely to be artefact?
A convincing result shows cellular nuclear staining in an appropriate compartment, consistent with ORC2’s nuclear assignment and high nuclear signal in pachytene spermatocytes (UniProt Q13416; HPA tissue IHC). Compare suspect cells with adjacent viable tissue and a no-primary control before accepting isolated DAB deposits (standard IHC practice). Staining confined to section edges, necrotic regions, or sites with endogenous peroxidase activity warrants repeat assessment after checking blocking and section quality (standard IHC practice). Membrane-only staining is discordant with ORC2’s lack of an annotated transmembrane segment, while cytoplasmic staining requires separate assessment because cytosolic localisation has been observed in cell-based imaging (UniProt Q13416; HPA subcellular).
Boster reagents

Best ORC2 / Origin recognition complex subunit 2 IHC Antibodies

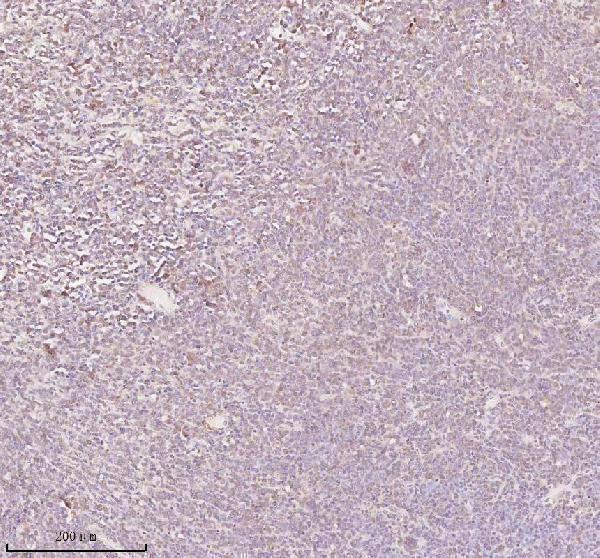
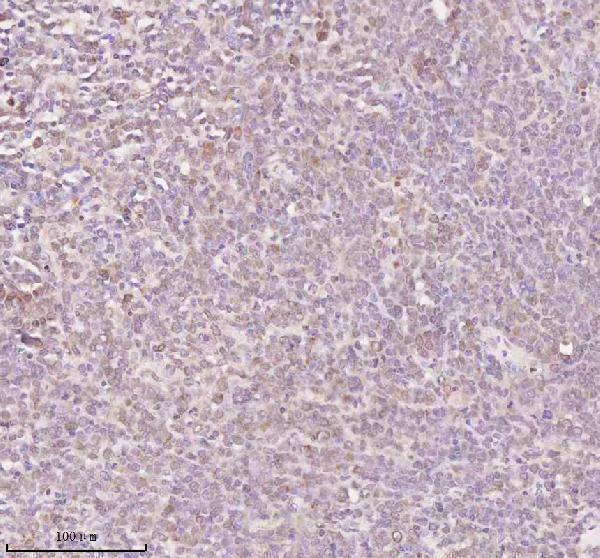
A04350-1 has IHC images from human paraffin sections and an IF image from A549 cells; its listed reactivity includes human, mouse and rat (catalog applications/reactivity; image captions).

Real IHC data IHC analysis of ORC2 using anti-ORC2 antibody (A04350-1). ORC2 was detected in a paraffin-embedded section of diffuse large B-cell lymphoma of human intestine tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-ORC2 Antibody (A04350-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-ORC2 Antibody ®
Cat # A04350-1

A04350-1 will render with its IHC figure from a paraffin-embedded section of human intestinal diffuse large B-cell lymphoma (A04350-1 IHC caption). The catalog also documents IHC in human prostate adenocarcinoma sections and IF/ICC in A549 cells (A04350-1 image captions).

Which to pick: Choose A04350-1 for paraffin-section IHC: its own caption documents EDTA retrieval at pH 8.0 and primary antibody at 2 μg/ml; the fixative is unreported (A04350-1 IHC caption). Choose the same SKU for IF/ICC because its own IF caption shows staining in A549 cells at 5 μg/ml (A04350-1 IF caption). Human, mouse and rat reactivity is listed, but the supplied IHC captions document human tissue only; clonality is unreported (catalog reactivity; A04350-1 IHC captions; catalog clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q13416 (ORC2_HUMAN, Origin recognition complex subunit 2).
  2. Human Protein Atlas. ORC2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. ORC2 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol..
  4. Human Protein Atlas. ORC2 antibody validation summary (2 antibodies).
  5. Anlotinib enhances the efficacy of KRAS-G12C inhibitors through c-Myc/ORC2 axis inhibition in non-small cell lung cancer. Cell death & disease 2025 — PMC12048666.
  6. Systemic analysis of the DNA replication regulator origin recognition complex in lung adenocarcinomas identifies prognostic and expression significance. Cancer medicine 2023 — PMC9972100.
  7. Integrated PPI- and WGCNA-Retrieval of Hub Gene Signatures Shared Between Barrett's Esophagus and Esophageal Adenocarcinoma. Frontiers in pharmacology 2020 — PMC7438937.
  8. PubMed PMID:7502077 — UniProt-cited evidence.
  9. PubMed PMID:8808289 — UniProt-cited evidence.
  10. PubMed PMID:15815621 — UniProt-cited evidence.