PAPSS2 / Bifunctional 3'-phosphoadenosine 5'-phosphosulfate synthase 2 · IHC design guide

Design Immunohistochemistry for PAPSS2

Use adrenal glandular cells and cartilage chondrocytes as high-staining reference populations for PAPSS2 paraffin IHC (HPA tissue IHC). This guide pairs their observed nuclear pattern with the catalog antibody’s paraffin-section staining conditions (HPA tissue IHC; datasheet A05684-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PAPSS2 (IHC for PAPSS2): expected localisation Nuclear staining in several tissues (HPA tissue IHC), antibody A05684-1, validated IHC image, and IHC protocol steps
Printable PAPSS2 IHC protocol sheet — expected localisation Nuclear staining in several tissues (HPA tissue IHC), antibody A05684-1, controls and protocol steps. Open the full PAPSS2 IHC guide →

PAPSS2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in several tissues (HPA tissue IHC)
Staining pattern Nuclear signal in adrenal glandular cells and chondrocytes (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A05684-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent (standard IHC practice; not target-specific)
Caveat Only medium RNA–staining concordance (HPA tissue IHC)
Regulation Adrenal gland–enhanced RNA (HPA tissue RNA)
Isoform / epitope 2 isoforms (A, B); verify epitope coverage (UniProt)
Section 1

Recommended PAPSS2 IHC & IF Protocols

The catalog antibody protocol and 3 published PAPSS2 IHC protocols cover colon and cartilage sections (datasheet A05684-1; PMC11285290; PMC6256856; PMC10935170).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human adrenocortical adenoma tissue; fixative not specified (datasheet A05684-1)
FixationImage fixative and duration unreported (datasheet A05684-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A05684-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A05684-1)
Primary antibodyRabbit anti-PAPSS2, 2-5 μg/ml (datasheet A05684-1)
Primary incubationOvernight at 4 °C (datasheet A05684-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A05684-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
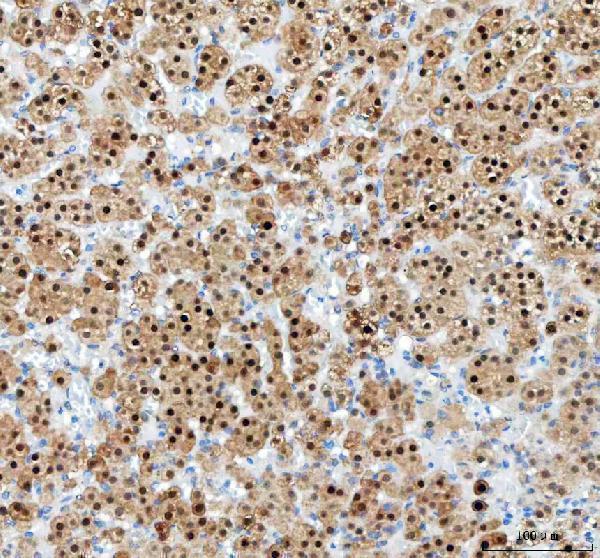
Expected resultPAPSS2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in several tissues, including adrenal gland and cartilage. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA, pH 8.0, for the catalog antibody (datasheet A05684-1). For cartilage, the published protocol instead uses hyaluronidase pretreatment (PMC6256856).
Section 2

What Is the Expected PAPSS2 Staining Pattern?

In paraffin tissue sections, expect PAPSS2 mainly in nuclei across several tissues, with high staining in adrenal glandular cells and cartilage chondrocytes (HPA tissue IHC: Enhanced reliability; High in both cell types). UniProt lists no subcellular location and no transmembrane segment (UniProt O95340 topology). ICC-IF instead reports mainly mitochondrial localization (HPA subcellular: approved); assess that result in its separate assay context.

What am I looking at on my slide?
Distinct nuclear staining in adrenal glandular cells or cartilage chondrocytes.This matches the tissue IHC profile and provides a useful positive reference (HPA tissue IHC: nuclear expression; High in both cell types). Compare staining within the named cells rather than treating every cell in the section as an expected positive.
Predominantly cytoplasmic or punctate staining, with little nuclear signal, in a paraffin section.This differs from the reported tissue IHC pattern (HPA tissue IHC: nuclear expression). Check antibody identity and staining controls before assigning a compartment. Mitochondrial localization comes from ICC-IF images, a different preparation and antibody assessment (HPA subcellular: approved; HPA antibodies).
Strong staining in cells listed as undetected, such as adipocytes or bone marrow hematopoietic cells.These cells are poor expected positives (HPA tissue IHC: Not detected). Consider cross-reactivity or endogenous chromogenic activity and inspect a no-primary control (general IHC practice). A single discordant section does not establish a new PAPSS2 expression pattern.
Haze across cells, stroma, or the whole section obscures nuclear boundaries.The result cannot be scored confidently against the reported nuclear profile (HPA tissue IHC: nuclear expression). Review blocking, washes, detector background, and counterstain intensity with appropriate controls (general IHC practice).
No visible signal in adrenal glandular cells or cartilage chondrocytes.This conflicts with reported high staining in those cell types (HPA tissue IHC: High). Confirm the expected cells are present, then review the catalog antibody's IHC-P conditions, detection reagents, and positive-control performance (general IHC practice).
💡Expected PAPSS2 appearanceCall a section positive when nuclear signal is clear in the relevant adrenal glandular cells or chondrocytes, with strong staining plausible there (HPA tissue IHC: nuclear; High); widespread staining of listed undetected cells or diffuse haze warrants investigation (HPA tissue IHC: Not detected; general IHC practice).
How each factor affects the staining
Tissue and cell selectionAdrenal glandular cells and cartilage chondrocytes are high-staining references; colon enterocytes and kidney distal tubules are medium (HPA tissue IHC). Use the named cell population when judging a section because the listed levels are cell-specific.
IHC evidence strengthThe tissue profile has Enhanced reliability, with medium antibody–RNA consistency and supporting external characterization (HPA tissue IHC). HPA075267 has Enhanced IHC validation (HPA antibodies); these labels support interpretation but do not make every stained cell specific.
IF/ICC: where should PAPSS2 appear?Mainly in mitochondria in the reported ICC-IF assessment (HPA subcellular: approved). HPA071224 is ICC Approved, while HPA075267 is IHC Enhanced (HPA antibodies). Treat the different compartment reports as assay-specific observations; this section supplies no IF/ICC protocol.
Protein features and coverageUniProt records two isoforms, A and B, one chain spanning residues 1–614, and no signal peptide, propeptide, transmembrane segment, or annotated glycosylation sites (UniProt O95340). Epitope placement and isoform coverage are unreported here, so the features alone cannot predict staining differences.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive tissue is blank.The run may have failed, or the expected cells may be absent from the viewed area (general IHC practice).Locate adrenal glandular cells or cartilage chondrocytes, both reported High (HPA tissue IHC); verify positive-control staining and the catalog antibody's IHC-P conditions (general IHC practice).
Signal appears mainly outside nuclei.The compartment disagrees with the tissue IHC profile (HPA tissue IHC: nuclear expression).Check antibody identity, positive control, and section morphology before scoring (general IHC practice). Do not substitute the mitochondrial ICC-IF report for the tissue IHC expectation (HPA subcellular: approved).
Cells expected to be undetected stain strongly.Cross-reactivity or endogenous detection activity may contribute (general IHC practice); the HPA cell-level result is Not detected.Compare a no-primary control and review blocking of endogenous chromogenic activity (general IHC practice). Reassess against the specific cell listing (HPA tissue IHC: Not detected).
Background obscures cell boundaries.Non-specific antibody or detector signal, or heavy counterstain, can obscure localization (general IHC practice).Inspect no-primary and positive controls; review blocking, washes, detection, and counterstain so nuclear staining can be assessed (general IHC practice; HPA tissue IHC: nuclear expression).
A medium-staining tissue appears weaker than adrenal gland.The reported cell-level staining differs: colon enterocytes and kidney distal tubules are Medium, while adrenal glandular cells are High (HPA tissue IHC).Score each named cell population against its own reported level, with a same-run positive reference to check assay performance (HPA tissue IHC; general IHC practice).
Two PAPSS2 antibodies give different compartment patterns.Their supplied validation covers different applications: HPA075267 is IHC Enhanced and HPA071224 is ICC Approved (HPA antibodies).Record antibody and assay for each image; judge paraffin sections against the nuclear tissue IHC profile and ICC-IF against its mitochondrial report (HPA tissue IHC; HPA subcellular).

Sample controls for PAPSS2 IHC & IF

🧪Run adrenal gland first: glandular cells should stain (HPA: High in adrenal gland glandular cells). Use adipose tissue adipocytes as the negative comparison (HPA: Not detected in adipose tissue adipocytes); on the adrenal slide, morphologically identified nonglandular cells should show no convincing signal above background, but their PAPSS2 status is not established by the supplied HPA row.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PAPSS2 in BJ [Human fibroblast], SiHa, U2OS, with annotated localisation: Mitochondria (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a concentration-matched rabbit IgG isotype control matched to the primary antibody’s clonality, and a PAPSS2 knockout or validated peptide-block control (caption: rabbit anti-PAPSS2 A05684-1). Block endogenous peroxidase for HRP/DAB detection and compare any adrenal pigment with the no-primary slide (caption: HRP/DAB detection).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A05684-1 paraffin-section caption does not state a fixative. Start with heat-mediated EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody overnight at 4°C (caption: A05684-1 tissue IHC); whether retrieval is essential remains unreported. The supplied evidence does not establish that frozen sections or IF are easier; adrenal pigment may complicate chromogenic scoring and should be checked against the no-primary control.

HPA tissue IHC evidence for PAPSS2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. External characterization data supports antibody staining.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Cartilage Chondrocytes High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Placenta Decidual cells High Protein (IHC) HPA →
Rectum Enterocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Section 3

Advanced PAPSS2 IHC Tips

Troubleshoot PAPSS2 chromogenic IHC by checking retrieval, compartment, cell identity and controls before comparing staining across sections.

Which retrieval conditions should I start with for PAPSS2 in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 (datasheet A05684-1). The selected paraffin-section image used that retrieval before incubation with the catalog antibody at 2 μg/ml overnight at 4°C (datasheet A05684-1). If staining is weak, compare retrieval heating times on adjacent sections while holding antibody concentration and detection conditions constant (standard IHC practice). Include a documented positive tissue, such as adrenal gland, and a no-primary control in each comparison (HPA: high staining in adrenal gland glandular cells; standard IHC practice). Excessive tissue damage or diffuse staining after heating suggests that retrieval conditions need adjustment (standard IHC practice).
How should I troubleshoot weak staining when fixation details are unavailable?
The selected PAPSS2 image documents a paraffin section, but its fixative is unreported (datasheet A05684-1). Target-specific fixation sensitivity is therefore unknown; record fixation conditions for each specimen before comparing staining (datasheet A05684-1; standard IHC practice). On matched sections, keep EDTA retrieval at pH 8.0 and the primary incubation at 2 μg/ml overnight at 4°C while assessing whether the recorded processing histories track with signal (datasheet A05684-1; standard IHC practice). Compare tissue integrity and counterstain quality alongside PAPSS2 staining, because damaged sections can make weak signal difficult to interpret (standard IHC practice). Include a no-primary control to reveal detection background (standard IHC practice).
How should I resolve conflicting nuclear and mitochondrial PAPSS2 patterns?
Do not assign a single established compartment from the available evidence: tissue IHC describes nuclear expression, whereas cellular IF identifies mitochondria as the main location (HPA: tissue profile; HPA: subcellular, approved). Score nuclear and cytoplasmic staining separately in the chromogenic sections, using a consistent hematoxylin counterstain to define nuclei (standard IHC practice). Check whether each pattern repeats in matched sections and in the documented positive cell populations, including adrenal gland glandular cells and cartilage chondrocytes (HPA: high in both; standard IHC practice). A mitochondrial assignment from diffuse DAB staining alone is unsupported without a suitable orthogonal localization assay (HPA: subcellular; standard IHC practice).
Can this stain distinguish PAPSS2 isoforms or reveal epitope masking?
PAPSS2 has 2 recorded isoforms, A and B, but the supplied antibody caption does not identify the recognized epitope (UniProt O95340: isoforms; datasheet A05684-1). Treat chromogenic signal as PAPSS2 staining without claiming isoform specificity unless epitope mapping or isoform-specific validation is available (standard IHC practice). The recorded chain spans residues 1–614, has no signal peptide or transmembrane segment, and has no annotated glycosylation sites or modified residues (UniProt O95340: processing, topology, PTMs). Those annotations do not establish how fixation or retrieval exposes the antibody epitope (standard IHC practice). If signal changes after retrieval adjustments, compare matched positive and negative controls before attributing the change to an isoform (standard IHC practice).
How can IF help investigate an ambiguous PAPSS2 IHC pattern?
Use IF as a separate localization check when chromogenic sections cannot resolve nuclear from punctate cytoplasmic signal (HPA: nuclear tissue-IHC profile; HPA: mitochondrial IF location). Multiplex PAPSS2 with a marker for the expected cell type, such as a chondrocyte marker in cartilage, and assess signal within identified cells (HPA: high in cartilage chondrocytes; standard IF practice). Select fluorophores after inspecting unstained tissue in each channel, so tissue autofluorescence does not mimic puncta (standard IF practice). Because PAPSS2 has no transmembrane segment and IF reports mitochondrial localization, optimize permeabilization for access to intracellular epitopes, without assuming which side of a mitochondrial membrane contains this antibody’s epitope (UniProt O95340: topology; HPA: subcellular; standard IF practice).
What controls distinguish PAPSS2 staining from chromogenic background?
The selected image used 10% goat serum blocking, a peroxidase-conjugated secondary antibody, and DAB development (datasheet A05684-1). Include a no-primary section to identify secondary or detection background, and use a peroxidase-blocking step as a general chromogenic IHC control (standard IHC practice). If diffuse DAB persists, inspect whether it appears in the no-primary section and adjust blocking, washing, or detection exposure one variable at a time (standard IHC practice). Compare suspected signal with cell-resolved positive references, including adrenal gland glandular cells, rather than treating uniform tissue color as PAPSS2 expression (HPA: high in adrenal gland glandular cells; standard IHC practice).
How should I score PAPSS2 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because the tissue IHC profile reports nuclear expression while cellular IF reports mitochondrial localization (HPA: tissue profile; HPA: subcellular). For chromogenic sections, record the percentage of positive cells and staining intensity, then calculate an H-score using the same thresholds across cases (standard IHC practice). Where cell number varies, report positive-cell density per mm² of viable, analyzable tissue and normalize counts to the relevant cell population (standard IHC practice). Exclude folds, damaged edges, and necrotic areas using a prespecified rule, and keep retrieval, development, and imaging conditions comparable (standard IHC practice).
When is a PAPSS2-positive IHC result convincing rather than artefactual?
A convincing result is reproducible in the expected cells, including adrenal gland glandular cells or cartilage chondrocytes, with low signal in the no-primary control (HPA: high in both cell populations; standard IHC practice). Evaluate nuclear staining explicitly because HPA describes nuclear expression in several tissues, while recognizing that its cellular IF data mainly place PAPSS2 in mitochondria (HPA: tissue profile; HPA: subcellular). Recheck staining restricted to section edges or necrotic regions, and investigate diffuse DAB that persists without primary antibody as possible detection artefact (standard IHC practice). Interpret the pattern alongside tissue morphology and matched controls; PAPSS2’s sulfate-activation function alone cannot establish the identity of a stained cell (UniProt O95340: function; standard IHC practice).
Boster reagents

Best PAPSS2 / Bifunctional 3'-phosphoadenosine 5'-phosphosulfate synthase 2 IHC Antibodies

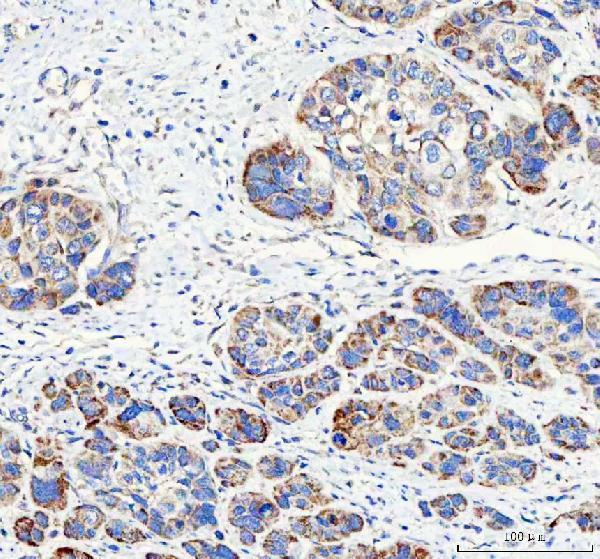
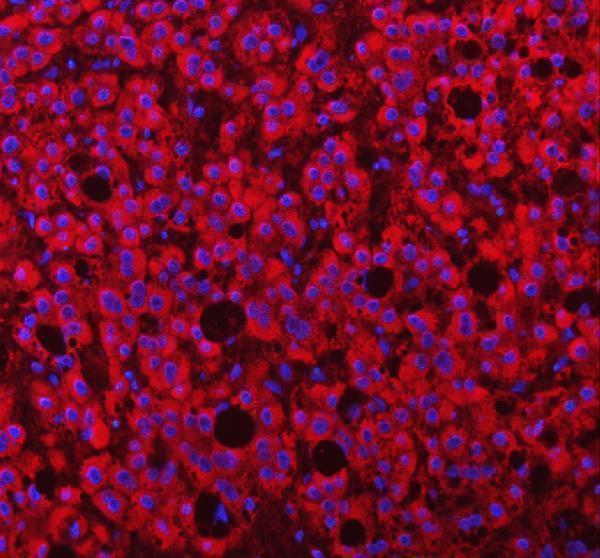
The IHC-validated antibody A05684-1 has paraffin-section IHC images from human tissues and IF images from human paraffin sections (catalog image captions); listed reactivity includes human, mouse and rat (catalog reactivity).

Real IHC data IHC analysis of PAPSS2 using anti-PAPSS2 antibody (A05684-1). PAPSS2 was detected in a paraffin-embedded section of human adrenocortical adenoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-PAPSS2 Antibody (A05684-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-PAPSS2 Antibody ®
Cat # A05684-1

A05684-1 will render with its human adrenocortical adenoma paraffin-section IHC figure; additional IHC captions show human laryngeal squamous cell carcinoma, liver cancer and lung cancer (catalog IHC image captions). Its IF captions show human liver cancer and lung adenocarcinoma paraffin sections (catalog IF image captions).

Which to pick: Choose A05684-1 for chromogenic tissue IHC on paraffin sections: its own caption reports EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody (A05684-1 IHC image caption); the fixative is unreported (A05684-1 IHC image caption). The same SKU is listed for IF, with human paraffin-section IF images, but ICC validation is unreported (catalog applications; A05684-1 IF image captions). For cross-species planning, A05684-1 lists human, mouse and rat reactivity, while the supplied IHC and IF images show human tissue only; its host is rabbit and clonality is unreported (catalog reactivity, host and image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O95340 (PAPS2_HUMAN, Bifunctional 3'-phosphoadenosine 5'-phosphosulfate synthase 2).
  2. Human Protein Atlas. PAPSS2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. PAPSS2 subcellular location (ICC-IF): Mainly localized to the mitochondria..
  4. Human Protein Atlas. PAPSS2 antibody validation summary (2 antibodies).
  5. Food-grade TiO(2) impairs intestinal mucus barrier via disrupting the gut microbiota-ILA-mucin sulfation axis: novel insights and dietary intervention strategies. Journal of nanobiotechnology 2026 — PMC13495178.
  6. Gut microbiota metabolite indole-3-acetic acid maintains intestinal epithelial homeostasis through mucin sulfation. Gut microbes 2024 — PMC11285290.
  7. The osteoarthritis-associated gene PAPSS2 promotes differentiation and matrix formation in ATDC5 chondrogenic cells. Experimental and therapeutic medicine 2018 — PMC6256856.
  8. Sulfation of chondroitin and bile acids converges to antagonize Wnt/β-catenin signaling and inhibit APC deficiency-induced gut tumorigenesis. Acta pharmaceutica Sinica. B 2024 — PMC10935170.
  9. PubMed PMID:9771708 — UniProt-cited evidence.
  10. PubMed PMID:10679223 — UniProt-cited evidence.
  11. PubMed PMID:10559207 — UniProt-cited evidence.