This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan PCCB chromogenic IHC on paraffin sections using the granular cytoplasmic pattern and high hepatocyte staining as references (HPA tissue IHC). Start the catalog antibody at 2–5 μg/ml (datasheet A04326-1), then assess staining against tissue controls.

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Granular cytoplasm observed; matrix expected (HPA tissue IHC; UniProt) | |
| Staining pattern | Granular hepatocyte cytoplasm; variable across tissues (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A04326-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Bone marrow+4 more · see all |
| Fixation | Keep paraffin-section fixation consistent (standard IHC practice; not target-specific) | |
| Caveat | Liver peroxidase may increase chromogenic background (HPA tissue IHC; standard IHC practice) | |
| Regulation | Tissue-enhanced RNA in liver (HPA RNA specificity) | |
| Isoform / epitope | 2 isoforms; mature chain starts at residue 29; epitope map unknown (UniProt) |
The catalog antibody’s IHC-P protocol uses EDTA pH 8.0 retrieval (datasheet A04326-1); the published osteosarcoma protocol below uses sodium citrate retrieval (PMC9751795).
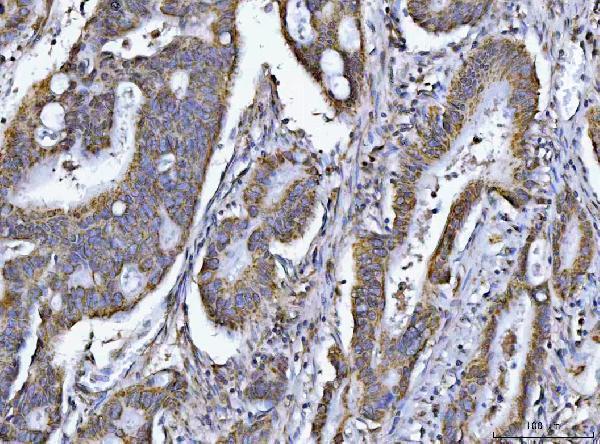
| Sample | Paraffin-embedded human colon adenocarcinoma tissue; fixative not specified (datasheet A04326-1) |
| Fixation | Image fixative and duration unreported (datasheet A04326-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A04326-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A04326-1) |
| Primary antibody | Rabbit anti-PCCB, 2-5 μg/ml (datasheet A04326-1) |
| Primary incubation | Overnight at 4 °C (datasheet A04326-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A04326-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PCCB-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Granular cytoplasmic expression at variable levels in most tissues. No signal in the no-primary control. |
PCCB is a mitochondrial matrix protein with no transmembrane segment (UniProt P05166: subcellular location and topology). In paraffin IHC, expect granular cytoplasmic staining rather than a resolved view of the matrix (HPA: tissue IHC profile; general IHC interpretation). Hepatocytes and several glandular cell populations stain strongly, while expression varies across tissues (HPA: High in hepatocytes and listed glandular cells; HPA: Enhanced reliability, based on antibody staining and RNA consistency).
| Granular cytoplasmic stain in hepatocytes or listed glandular cells. | This matches the observed PCCB tissue profile (HPA: High in liver hepatocytes and adrenal, appendix, colon, duodenum, gallbladder, and parathyroid glandular cells). Granules are compatible with mitochondrial localisation, although chromogenic IHC alone does not resolve the matrix (UniProt P05166: mitochondrion matrix; general IHC interpretation). |
| Predominantly nuclear, surface-membrane, or extracellular stain. | These compartments conflict with the expected mitochondrial matrix location and granular cytoplasmic IHC profile (UniProt P05166: subcellular location and topology; HPA: tissue IHC profile). Treat an isolated compartment shift as suspect; review morphology and detection controls before assigning it to PCCB (general IHC practice). |
| Strong stain in a cell population reported as not detected. | For example, strong hematopoietic-cell staining in bone marrow differs from the HPA observation (HPA: Not detected in bone marrow hematopoietic cells). Cross-reactivity or endogenous detection activity is possible (general IHC practice). Check a no-primary control and compare the same cell population with a positive tissue; HPA's result does not prove biological absence. |
| Broad, diffuse colour obscures cell boundaries and granules. | A diffuse field cannot be scored confidently against the reported granular cytoplasmic profile (HPA: tissue IHC profile). Background may arise from detection reagents or insufficient washing (general IHC practice). Compare a no-primary control and examine whether the colour tracks tissue structures rather than the expected cell populations. |
| No convincing stain in a known-positive tissue. | Absent hepatocyte staining conflicts with the HPA High observation for liver (HPA: High in hepatocytes). First check whether the section and chromogenic detection worked, then review the antibody's IHC-P conditions (general IHC practice). A failed run cannot establish that PCCB is absent from the specimen. |
| Location and topology | PCCB resides in the mitochondrial matrix and has no transmembrane segment (UniProt P05166: subcellular location and topology). Interpret chromogenic granules within cytoplasm as compatible with that location; do not infer matrix resolution from an IHC section (HPA: granular cytoplasmic profile; general IHC interpretation). |
| Tissue and cell selection | Liver hepatocytes provide a documented High-staining comparator; bone marrow hematopoietic cells are reported Not detected (HPA: liver and bone marrow tissue IHC). Use the named cell populations when comparing slides, because HPA describes variable staining across most tissues (HPA: tissue IHC profile). |
| Antibody evidence | Two listed rabbit polyclonal antibodies, HPA036939 and HPA036940, have Enhanced IHC validation (HPA: antibody validation). Enhanced supports confidence in the reported tissue pattern; it does not validate a different antibody, staining run, or specimen automatically (HPA: validation description; general IHC interpretation). |
| Processing and isoforms | UniProt lists a 29–539 mature chain and two isoforms (UniProt P05166: processing and isoforms). The supplied evidence does not map the catalog antibody's epitope or show isoform-specific tissue staining; interpret a discrepant pattern against tissue controls rather than assigning it to processing or one isoform. |
| IF/ICC Q&A: what localisation is supported? | Mitochondrial matrix localisation is annotated for PCCB (UniProt P05166: subcellular location). HPA supplies no ICC-IF images or main ICC-IF location, so its tissue IHC pattern cannot serve as direct evidence of an IF image pattern (HPA: subcellular ICC-IF record). |
| Situation | Likely cause | Next action |
|---|---|---|
| Liver control has no hepatocyte signal. | This disagrees with a documented High population (HPA: liver hepatocytes); the staining run may have failed (general IHC practice). | Check section integrity and chromogenic detection with run controls, then review the IHC-validated antibody's supplied IHC-P conditions before interpreting study tissues (general IHC practice). |
| Expected cells stain weakly, but controls develop. | Intensity varies across tissues (HPA: variable tissue IHC profile); a weak field may also be difficult to separate from background (general IHC interpretation). | Compare the named cell population with a documented High control, such as hepatocytes, on the same run; score only signal distinguishable from the no-primary control (HPA: High in hepatocytes; general IHC practice). |
| Diffuse colour appears across positive and negative regions. | Non-specific background or endogenous detection activity can obscure the reported granular pattern (general IHC practice; HPA: granular cytoplasmic tissue profile). | Inspect a no-primary control, review blocking and washing, and assess whether discrete cytoplasmic granules remain above background (general IHC practice). |
| Staining is mainly nuclear or along cell borders. | That distribution disagrees with mitochondrial matrix localisation and the tissue IHC profile (UniProt P05166: subcellular location; HPA: granular cytoplasmic profile). | Check compartment calls against the counterstain and cell morphology; repeat with appropriate run controls before scoring it as PCCB (general IHC practice). |
| A reported negative cell population stains strongly. | The result conflicts with the specified HPA observation; cross-reactivity or detection background is possible (HPA: Not detected populations; general IHC practice). | Confirm the exact cell type, compare a no-primary control, and check a documented High population in the same run before treating the signal as specific (HPA: High and Not detected populations; general IHC practice). |
| Two antibodies give conflicting cell patterns. | Both listed antibodies have Enhanced IHC status, but validation does not establish that every run will agree (HPA: HPA036939 and HPA036940 validation; general IHC interpretation). | Compare matched positive and negative cell populations, morphology, and run controls; report the discrepancy rather than combining discordant signals into one PCCB score (HPA: tissue IHC; general IHC practice). |
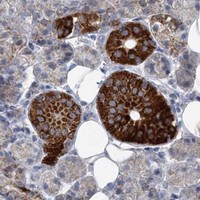
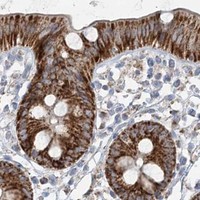

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Oral mucosa | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Ovary | Ovarian stroma cells | Not detected | Protein (IHC) | HPA → |
| Skeletal muscle | Myocytes | Not detected | Protein (IHC) | HPA → |
| Smooth muscle | Smooth muscle cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot chromogenic PCCB staining in paraffin sections using the catalog antibody’s tissue example, expected mitochondrial localisation, and cell-level controls.
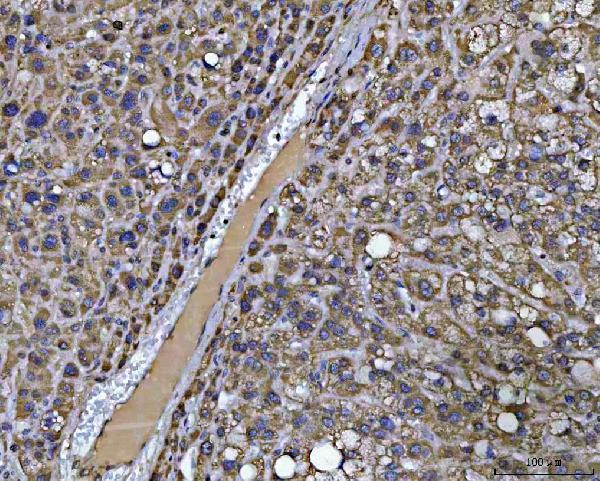
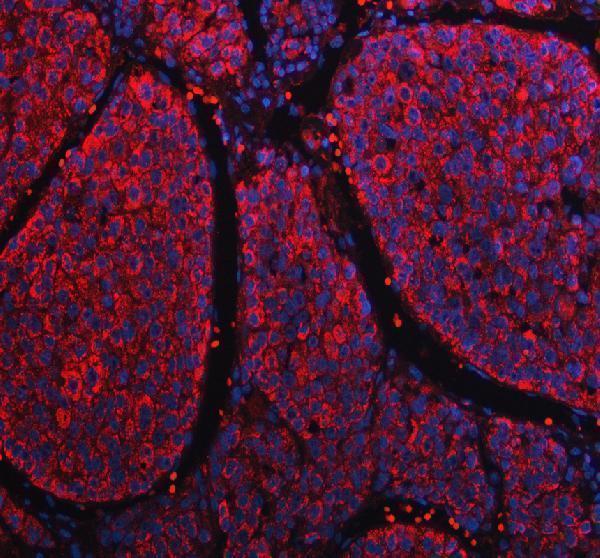
A04326-1 has IHC images from paraffin-embedded human colon adenocarcinoma and liver cancer sections and an IF image from paraffin-embedded human liver cancer tissue (catalog image captions).
A04326-1 has documented IHC staining in paraffin-embedded human colon adenocarcinoma and liver cancer sections (catalog IHC captions). The same SKU has documented IF staining in a paraffin-embedded human liver cancer section and stated human, mouse, and rat reactivity (catalog IF caption; catalog reactivity).
Which to pick: For tissue IHC, choose A04326-1: its own captions document paraffin-section staining with EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (catalog IHC captions). For IF, the same SKU has a paraffin-section image at 5 μg/ml, while ICC validation and clonality are unreported (catalog IF caption; catalog applications and product details). For cross-species planning, it lists human, mouse, and rat reactivity, but the supplied IHC and IF tissue images show human samples only (catalog reactivity; catalog image captions).