PFN1 / Profilin-1 · IHC design guide

Design Immunohistochemistry for PFN1

Plan PFN1 staining in paraffin sections using the catalog antibody’s IHC protocol. Interpret cytoplasmic staining against the strong signal reported in subsets of immune cells (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PFN1 (IHC for PFN1): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody PB9313, validated IHC image, and IHC protocol steps
Printable PFN1 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody PB9313, controls and protocol steps. Open the full PFN1 IHC guide →

PFN1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Cytoplasmic, strongest in immune-cell subsets (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB9313)
Positive control ⓘ Lung+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image PB9313)
Caveat Immune-cell-rich areas may dominate staining (HPA tissue IHC)
Regulation No specific regulator reported (UniProt)
Isoform / epitope No annotated isoforms; the chain spans residues 2–140 (UniProt)
Section 1

Recommended PFN1 IHC & IF Protocols

The catalog antibody has a datasheet IHC-P protocol (datasheet: PB9313). The published options below cover oral tissue, spinal cord and cortex, breast tissue, and bladder specimens (PMC5422140; PMC3923463; PMC3834125; PMC5342587).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet PB9313)
FixationImage fixative and duration unreported (datasheet PB9313); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB9313); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9313)
Primary antibodyRabbit anti-PFN1, 0.5-1μg/ml (datasheet PB9313)
Primary incubationOvernight at 4 °C (datasheet PB9313)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9313)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPFN1-positive staining in alveolar cells type II of lung (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression, most abundant in subsets of immune cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: PB9313). Citrate pH 6.0 is a published alternative with a different PFN1 antibody (PMC3834125).
Section 2

What Is the Expected PFN1 Staining Pattern?

PFN1 should appear predominantly in the cytoplasm, consistent with its cytoskeletal association and lack of a transmembrane segment (UniProt P07737). In paraffin-section IHC, staining is broadly distributed, with particularly strong signal in subsets of immune cells (HPA tissue IHC). HPA rates the tissue pattern Enhanced, while reporting medium agreement with RNA data and pending external verification (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining is strong in lymph-node germinal center cells or spleen red-pulp cells (HPA tissue IHC).This fits two HPA High cell populations and the expected cytoplasmic location (HPA tissue IHC; UniProt P07737). Judge the named cells and compartment, since the HPA profile describes broadly distributed expression with variation among cell types (HPA tissue IHC).
Staining is predominantly nuclear or sharply restricted to cell membranes.Treat this as a localisation mismatch requiring investigation: UniProt places PFN1 in the cytoplasm and cytoskeleton, and HPA describes cytoplasmic tissue staining (UniProt P07737; HPA tissue IHC). Check morphology and controls before interpreting it as PFN1.
A low-staining reference population shows intense signal, such as caudate glial cells (HPA tissue IHC).Cross-reactivity or endogenous detection activity is possible (general IHC practice). HPA lists caudate glial cells as Low, but its tissue profile is broadly positive; unexpected intensity alone does not prove nonspecific binding (HPA tissue IHC).
Chromogen colours tissue broadly, including areas without a clear cellular pattern.This is diffuse background rather than a convincing cytoplasmic cell pattern (general IHC practice; HPA tissue IHC). Compare a matched detection-only control and review blocking, washes, and detection chemistry (general IHC practice).
The named cells in a known-positive section show no detectable staining.First check the assay with an HPA High population, such as lung alveolar type II cells or lymph-node germinal center cells (HPA tissue IHC). An absent signal there can reflect an assay problem; one negative section cannot establish absent PFN1 expression (general IHC practice).
💡Expected PFN1 appearanceA convincing positive result is cellular cytoplasmic staining, including High signal in HPA-listed populations such as lymph-node germinal center cells, whereas dominant nuclear staining or widespread cell-free colour is suspect (HPA tissue IHC; UniProt P07737; general IHC practice).
How each factor affects the staining
Compartment and topology (UniProt P07737)PFN1 is assigned to the cytoplasm and cytoskeleton and has no transmembrane segment (UniProt P07737). Score cytoplasmic staining within identifiable cells; membrane-only staining needs investigation.
Cell-population choice (HPA tissue IHC)HPA calls lung alveolar type II cells, lymph-node germinal center cells, spleen red-pulp cells, and tonsil non-germinal center cells High (HPA tissue IHC). It lists several other populations as Medium or Low, so compare the specified cells.
Strength of IHC evidence (HPA antibodies; HPA tissue IHC)CAB037134 and CAB037140 each have Enhanced IHC status (HPA antibodies). HPA also notes medium staining–RNA consistency and pending external verification, so corroborate unexpected patterns rather than treating validation as certainty (HPA tissue IHC).
Processing and variants (UniProt P07737)UniProt records no signal peptide, propeptide, or annotated isoforms; the listed chain spans residues 2–140 (UniProt P07737). These annotations provide no basis for predicting a distinct secreted or membrane staining pattern.
Detection chemistry (general IHC practice)Endogenous enzyme activity can contribute colour when the matching enzyme-based detection system is used (general IHC practice). Interpret a suspicious signal against a detection-only control; this is a general assay consideration, not a reported PFN1-specific effect.
IF/ICC Q&A (HPA subcellular; HPA antibodies)Where should PFN1 appear in IF/ICC? HPA approves a cytosolic location and lists images from A-431 and U-251MG cells (HPA subcellular). CAB037140 has Uncertain ICC status; its Enhanced rating applies to IHC (HPA antibodies).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive-control cells remain unstained (HPA tissue IHC).The IHC assay may not be generating detectable signal (general IHC practice); the section alone cannot identify which step failed.Confirm the named HPA High cells are present, then review antibody identity and dilution, antigen retrieval, and detection reagents against the catalog antibody’s IHC-P instructions (HPA tissue IHC; general IHC practice).
Signal is nuclear with little cytoplasmic colour.The compartment conflicts with PFN1’s annotated cytoplasmic location and HPA’s tissue profile (UniProt P07737; HPA tissue IHC). Nonspecific staining is one possibility (general IHC practice).Verify cell boundaries and counterstain, examine a known-positive population, and compare an appropriate staining control before scoring the nuclear signal (general IHC practice; HPA tissue IHC).
Most of the section has a uniform brown haze.Diffuse background may reflect detection chemistry, inadequate blocking, or insufficient washing (general IHC practice); it does not reproduce HPA’s cellular cytoplasmic profile (HPA tissue IHC).Inspect a detection-only control, then check blocking and wash steps and the detection system used (general IHC practice). Assess PFN1 only where cell outlines and cytoplasm remain interpretable.
A Low HPA population appears as intense as an HPA High population (HPA tissue IHC).Cell identification, background, or antibody cross-reactivity may contribute (general IHC practice). HPA levels are observations for named cell populations, not an absolute intensity cutoff (HPA tissue IHC).Recheck the cell types and compare compartments and controls across the same run; avoid calling the Low population a true negative solely from its HPA label (HPA tissue IHC; general IHC practice).
Two IHC antibodies give different tissue patterns.Enhanced status for both CAB037134 and CAB037140 does not guarantee identical results in every section; HPA reports medium consistency with RNA and pending external verification (HPA antibodies; HPA tissue IHC).Compare the same named HPA High cells, section morphology, and staining controls, then report the disagreement rather than choosing a pattern from intensity alone (HPA tissue IHC; general IHC practice).
An IF/ICC image seems to contradict the IHC slide.HPA’s approved cytosolic IF/ICC location and tissue IHC levels describe different preparations; CAB037140 is rated Uncertain for ICC but Enhanced for IHC (HPA subcellular; HPA antibodies).Interpret the paraffin-section result against HPA tissue cells and cytoplasmic location; assess the IF/ICC result under its separate guide and antibody validation (HPA tissue IHC; HPA subcellular; HPA antibodies).

Sample controls for PFN1 IHC & IF

🧪Run lung first and confirm staining in alveolar type II cells (HPA: High in lung alveolar cells type II). HPA detects PFN1 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and do not treat other cells on the lung slide as confirmed PFN1-negative cells (HPA tissue data).
Positive control tissue: Lung (Alveolar cells type II, HPA High)
Negative control tissue: None in HPA: PFN1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PFN1 in A-431, U-251MG, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a nonimmune rabbit IgG isotype control matched to the primary antibody’s clonality where known; the PB9313 caption identifies a rabbit primary but does not state its clonality (PB9313 caption). A PFN1 knockout sample or validated peptide block can test target specificity; for the caption’s SABC/DAB detection, quench endogenous peroxidase and check for endogenous biotin in lung tissue (PB9313 caption; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected PB9313 paraffin-section caption does not report the fixative (PB9313 caption). That caption uses heat retrieval in EDTA at pH 8.0, but one example does not establish that retrieval is required (PB9313 caption). The supplied evidence does not establish whether frozen sections or IF are easier; lung pigment can complicate interpretation of brown DAB staining (standard IHC practice).

HPA tissue IHC evidence for PFN1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Lung Alveolar cells type II High Protein (IHC) HPA →
Lymph node Germinal center cells High Protein (IHC) HPA →
Spleen Cells in red pulp High Protein (IHC) HPA →
Tonsil Non-germinal center cells High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: PFN1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced PFN1 IHC Tips

Troubleshoot PFN1 staining in paraffin section chromogenic IHC, with one guide to interpreting IF results.

Which retrieval conditions should I start with for PFN1 paraffin sections?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for PB9313 paraffin sections (datasheet PB9313). The selected image used this retrieval before an overnight incubation with 1 μg/mL primary antibody at 4°C (PB9313 tissue-IHC caption). If cytoplasmic staining is weak, compare retrieval durations on matched sections while keeping antibody concentration and detection conditions constant (standard IHC practice). Assess tissue preservation alongside signal, because excessive heating can damage section morphology and complicate cell-level scoring (standard IHC practice). Include a no-primary control to distinguish retrieval-related tissue background from antibody-dependent staining (standard IHC practice).
Could fixation explain weak or uneven PFN1 staining?
The PB9313 tissue-IHC caption identifies a paraffin section but does not report its fixative, so PFN1-specific fixation sensitivity is unknown (PB9313 tissue-IHC caption). Record fixation method and duration for each specimen, then compare similarly processed sections before attributing a signal difference to PFN1 biology (standard IHC practice). On matched sections, check whether weak cytoplasmic staining tracks with poor morphology, detached tissue, or uneven processing (standard IHC practice; UniProt P07737 localisation). Keep retrieval at EDTA pH 8.0 and the primary incubation at 1 μg/mL overnight at 4°C during that comparison (datasheet PB9313; PB9313 tissue-IHC caption).
Where should convincing PFN1 staining appear in tissue?
Look primarily for cytoplasmic staining: PFN1 is assigned to the cytoplasm and cytoskeleton, and tissue IHC reports ubiquitous cytoplasmic expression (UniProt P07737 localisation; HPA tissue IHC). Assess signal within identifiable cells rather than treating diffuse color across a section as localisation evidence (standard IHC practice). High staining is reported in lung alveolar type II cells, lymph node germinal center cells, and spleen red pulp cells, which can provide contextual comparisons when those cells are present (HPA tissue IHC). Predominantly nuclear or luminal staining warrants review of morphology, no-primary controls, and detection background before being scored as PFN1 (UniProt P07737 localisation; standard IHC practice).
How should an unknown epitope affect troubleshooting?
The supplied record annotates 0 isoforms and no protein domain, but it does not identify the PB9313 binding epitope (UniProt P07737 record; PB9313 tissue-IHC caption). PFN1 has no annotated transmembrane segment, signal peptide, or glycosylation sites; these facts support a cytoplasmic staining expectation without establishing epitope accessibility after processing (UniProt P07737 topology and processing; UniProt P07737 localisation). Annotated modifications include phosphorylation at residues 28, 57, and 85, but the payload does not link them to antibody recognition (UniProt P07737 modified residues). If staining changes with retrieval, compare matched sections and seek epitope documentation before assigning a modification-specific cause (standard IHC practice).
How can IF help assess the cell distribution seen by IHC?
For IF, pair PFN1 with a marker that identifies the cell population being assessed, then compare signal within segmented cells rather than across the whole field (standard IF practice). For example, a marker identifying alveolar type II cells can help examine a population reported to stain strongly in lung IHC (HPA tissue IHC). Select a fluorophore channel with low tissue autofluorescence and include single-stain controls when multiplexing (standard IF practice). PFN1 is cytosolic and has no annotated transmembrane segment, so permeabilisation should permit access to an intracellular epitope, although this antibody’s epitope is unspecified (HPA subcellular; UniProt P07737 topology; standard IF practice). The PB9313 paraffin-section caption does not establish an IF fixation condition (PB9313 tissue-IHC caption).
What should I check when DAB obscures cytoplasmic PFN1 staining?
The selected PB9313 paraffin-section image used 10% goat serum blocking, a biotinylated goat anti-rabbit secondary, streptavidin-biotin detection, and DAB (PB9313 tissue-IHC caption). Start by comparing no-primary and secondary-only controls with the stained section to locate antibody-independent or detection-dependent color (standard IHC practice). Check peroxidase blocking and, with a biotin-based detection system, assess endogenous biotin contribution in the specimen (standard IHC practice; PB9313 tissue-IHC caption). If background remains high, titrate the primary around the reported 1 μg/mL condition and keep DAB development consistent across controls and samples (PB9313 tissue-IHC caption; standard IHC practice).
How should I score PFN1 across sections with different cell populations? ⚠ ANSWER MARKED FOR VERIFICATION
Score cytoplasmic PFN1 within predefined, morphologically identified cell populations, because tissue IHC reports widespread expression with particularly high staining in subsets of immune cells (HPA tissue IHC). An H-score can combine the percentage of cells at each staining intensity; alternatively, report percent positive cells when intensity grading is unreliable (standard IHC practice). For dispersed positive cells, report density per mm² of evaluable tissue and state the cell-identification rule (standard IHC practice). Normalize comparisons to the same cell population and evaluable tissue area, excluding folds and necrotic regions by a prespecified rule (standard IHC practice). Apply identical imaging and DAB scoring criteria across sections (standard IHC practice).
How can I distinguish a PFN1-positive cell from staining artefact?
A plausible positive cell has interpretable cytoplasmic signal in intact tissue, consistent with PFN1’s cytoplasmic and cytoskeletal assignment (UniProt P07737 localisation; HPA tissue IHC). Check the cell identity: high staining is documented in subsets of immune cells and in lung alveolar type II cells, so nearby positive cells should not automatically be assigned to the cell population of interest (HPA tissue IHC). Discount staining concentrated at section edges or in necrotic areas until it is reproduced in well-preserved tissue (standard IHC practice). Review no-primary and peroxidase-block controls when diffuse DAB color or endogenous enzyme activity could explain the result (standard IHC practice). HPA labels its tissue IHC reliability “Enhanced” while noting pending external verification, so treat it as supporting context rather than definitive validation of this specimen (HPA tissue IHC).
Boster reagents

Best PFN1 / Profilin-1 IHC Antibodies

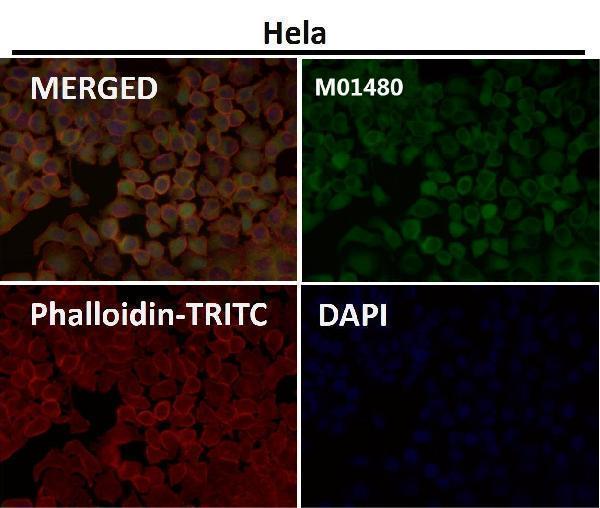
The catalog lists human, mouse and rat reactivity for both antibodies (catalog: reactivity). The supplied figures show paraffin-section IHC for PB9313 and IF for M01480 (PB9313 IHC captions; M01480 IF caption).

Real IHC data IHC analysis of Profilin 1 using anti-Profilin 1 antibody (PB9313). Profilin 1 was detected in paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-Profilin 1 Antibody (PB9313) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-Profilin 1/PFN1 Antibody ®
Cat # PB9313
Real IF data Immunofluorescent analysis using the Antibody at 1:50 dilution.
Anti-Profilin1 PFN1 Rabbit Monoclonal Antibody
Cat # M01480

PB9313 will render with IHC data from human lung cancer paraffin sections; its catalog also lists IF/ICC (PB9313 IHC caption; PB9313 applications). M01480 will render with an IF image at 1:50; its catalog lists IHC and IF/ICC, but the IF caption does not identify a specimen (M01480 IF caption; M01480 applications).

Which to pick: For tissue IHC, choose PB9313: its image captions document human lung and intestinal cancer paraffin sections with EDTA retrieval at pH 8.0 and antibody at 1 μg/ml; the fixative is unreported (PB9313 IHC captions). For IF/ICC, M01480 is a rabbit monoclonal with an IF image at 1:50, although its caption leaves the specimen unspecified (M01480 catalog; M01480 IF caption). Both SKUs list human, mouse and rat reactivity, but the supplied PB9313 tissue images document human samples only (catalog: reactivity; PB9313 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P07737 (PROF1_HUMAN, Profilin-1).
  2. Human Protein Atlas. PFN1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. PFN1 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. PFN1 antibody validation summary (2 antibodies).
  5. A loss of profilin-1 in late-stage oral squamous cell carcinoma. Journal of oral pathology & medicine : official publication of the International Association of Oral Pathologists and the American Academy of Oral Pathology 2017 — PMC5422140.
  6. Profilin-1 mutations are rare in patients with amyotrophic lateral sclerosis and frontotemporal dementia. Amyotrophic lateral sclerosis & frontotemporal degeneration 2013 — PMC3923463.
  7. Profilin-1 downregulation has contrasting effects on early vs late steps of breast cancer metastasis. Oncogene 2014 — PMC3834125.
  8. Silencing of Profilin-1 suppresses cell adhesion and tumor growth via predicted alterations in integrin and Ca2+ signaling in T24M-based bladder cancer models. Oncotarget 2016 — PMC5342587.
  9. PubMed PMID:3356709 — UniProt-cited evidence.
  10. PubMed PMID:20736409 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.