PFN2 / Profilin-2 · IHC design guide

Design Immunohistochemistry for PFN2

Plan PFN2 chromogenic IHC in paraffin sections using cytoplasmic staining and high CNS signal as reference patterns (HPA tissue IHC). This guide covers fixation consistency, tissue controls and interpretation of the 2 annotated isoforms (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PFN2 (IHC for PFN2): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A06663, validated IHC image, and IHC protocol steps
Printable PFN2 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A06663, controls and protocol steps. Open the full PFN2 IHC guide →

PFN2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Variable cytoplasmic staining; high in CNS neurons and neuropil (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A06663)
Positive control ⓘ Caudate+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA have medium consistency (HPA tissue IHC)
Regulation Brain-high tissue expression (UniProt)
Isoform / epitope 2 isoforms, IIa and IIb; epitope coverage unknown (UniProt)
Section 1

Recommended PFN2 IHC & IF Protocols

The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet A06663). Three published PFN2 IHC protocols provide tissue-specific alternatives (PMC9005514; PMC6065425; PMC4870769).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat brain tissue; fixative not specified (datasheet A06663)
FixationImage fixative and duration unreported (datasheet A06663); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A06663); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A06663)
Primary antibodyRabbit anti-PFN2, 2-5μg/ml (datasheet A06663)
Primary incubationOvernight at 4 °C (datasheet A06663)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A06663)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPFN2-positive staining in neuronal cells of caudate (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissue types at variable levels, high in CNS. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 for the catalog antibody (datasheet A06663); evaluate citrate retrieval when adapting the colorectal or esophageal protocols (PMC6065425; PMC4870769).
Section 2

What Is the Expected PFN2 Staining Pattern?

PFN2 is a cytoplasmic, cytoskeleton-associated protein with no transmembrane segment (UniProt P35080). In paraffin-section IHC, expect variable cytoplasmic staining across tissues, with strong signal in selected CNS cells and neuropil (HPA tissue IHC). HPA rates its tissue IHC reliability Enhanced, while reporting medium consistency between staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Strong cytoplasmic staining in caudate or hippocampal neuronal cells, or cerebral cortex neuropil (HPA tissue IHC).This matches HPA's High observations in those sites and UniProt's cytoplasmic, cytoskeleton-associated location (HPA tissue IHC; UniProt P35080). Judge the stained cell or structure, not the whole section: HPA reports variable levels across tissues (HPA tissue IHC).
Staining confined to nuclei, with little cytoplasmic signal.A nuclear-only pattern falls outside the reported cytoplasmic tissue profile and UniProt location (HPA tissue IHC; UniProt P35080). Check the counterstain and detection controls before interpreting it as PFN2; the supplied sources do not establish nuclear localisation (general IHC practice; UniProt P35080).
Strong staining in a cell population HPA lists as Not detected, such as adipocytes or bone-marrow hematopoietic cells (HPA tissue IHC).Treat this as unexpected for that sampled cell population (HPA tissue IHC). Possible causes include antibody cross-reactivity or endogenous chromogenic detection activity; compare a known-positive control and a no-primary control before assigning the signal to PFN2 (general IHC practice).
Broad colour over tissue and empty areas, with no clear cellular pattern.Diffuse background cannot establish the HPA cell-specific pattern (HPA tissue IHC). Examine the no-primary control, blocking, washes and detection exposure; background from the staining workflow can obscure a genuine cytoplasmic signal (general IHC practice).
No staining in caudate neuronal cells or kidney collecting ducts selected as positive controls (HPA tissue IHC).Both are reported High by HPA, so an absent control signal makes a negative study section difficult to interpret (HPA tissue IHC; general IHC practice). Check section integrity, antibody and detection reagents, and retrieval conditions before calling the study tissue negative (general IHC practice).
💡Expected PFN2 appearanceCall a result consistent with PFN2 when cytoplasmic staining is strong in HPA High populations such as caudate neuronal cells or kidney collecting ducts; isolated nuclear colour or widespread cell-independent colour is suspect (HPA tissue IHC; UniProt P35080; general IHC practice).
How each factor affects the staining
Tissue and cell selectionHPA reports High staining in caudate neuronal cells, cerebral cortex neuropil, hippocampal neuronal cells, epididymal glandular cells and kidney collecting ducts; liver hepatocytes are Low (HPA tissue IHC). Use the named cell population when comparing intensity.
IHC evidence strengthHPA rates tissue IHC reliability Enhanced but describes only medium staining-to-RNA consistency; both listed rabbit pAbs, HPA035611 and CAB037073, have Enhanced IHC validation (HPA tissue IHC; HPA antibodies). These ratings support the observed pattern without making every tissue a positive control.
Compartment and isoformsUniProt places PFN2 in cytoplasm and cytoskeleton, records no transmembrane segment, and lists isoforms IIa and IIb (UniProt P35080). The supplied record gives no antibody epitope or isoform-specific staining data, so do not attribute a tissue pattern to one isoform.
IF/ICC Q&A: Is membrane staining an established expectation?HPA's ICC-IF summary says Membrane, but supplies no main location or cell-line images (HPA subcellular). UniProt reports cytoplasm and cytoskeleton with no transmembrane segment (UniProt P35080). Treat membrane-only IF as unresolved here, not as the IHC-P scoring pattern.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The known-positive control is blank.A staining-step failure is possible when a population HPA rates High gives no signal (HPA tissue IHC; general IHC practice).Verify the selected control cell population, antibody preparation, retrieval run and chromogenic detection with controls before interpreting study sections (general IHC practice).
A study section is negative but its positive control stains.PFN2 varies by tissue and cell type; HPA lists several populations as Low or Not detected (HPA tissue IHC).Score the relevant cell population against its HPA reference level. Report a negative result for that population without extending it to all cells in the tissue (HPA tissue IHC; general IHC practice).
Colour appears in a HPA Not detected population.The signal may reflect cross-reactivity or endogenous detection activity; the HPA entry alone cannot identify its cause (HPA tissue IHC; general IHC practice).Review a no-primary control and the assay's endogenous-activity blocking step; compare localisation with a HPA High control (general IHC practice; HPA tissue IHC).
Staining is nuclear-only.That distribution conflicts with the reported cytoplasmic tissue profile and UniProt location (HPA tissue IHC; UniProt P35080).Check counterstain interpretation and detection controls, then reassess whether cytoplasmic signal is present before scoring PFN2 (general IHC practice).
The slide has diffuse background.Background can mask the cellular pattern needed for comparison with HPA observations (general IHC practice; HPA tissue IHC).Compare a no-primary control; review blocking, washes and chromogen development, then score only distinguishable cellular staining (general IHC practice).
Strong signal appears outside CNS tissue.High staining is also reported in epididymal glandular cells and kidney collecting ducts (HPA tissue IHC).Identify the stained cell population before treating a non-CNS positive as unexpected; compare its compartment and intensity with the HPA entry (HPA tissue IHC; UniProt P35080).

Sample controls for PFN2 IHC & IF

🧪Run caudate first and require staining in neuronal cells (HPA: High in caudate neuronal cells). Use adipose tissue adipocytes as the negative comparator (HPA: Not detected in adipose tissue adipocytes); on the caudate slide, treat unstained non-neuronal profiles as candidate internal negatives only after confirming their identity and background-level signal (HPA: High is assigned to neuronal cells).
Positive control tissue: Caudate (Neuronal cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for PFN2; derive a cell-line control from the positive tissue's cell type (Neuronal cells) and confirm it by RNA or western blot first.
Technical controls: Include no-primary (secondary-only) and matched rabbit IgG isotype controls, plus a PFN2 knockout specimen or peptide-block control if available (caption: rabbit anti-PFN2 primary; standard IHC practice). For chromogenic detection, quench endogenous peroxidase and check for endogenous biotin before interpreting signal (caption: biotinylated secondary, streptavidin–biotin complex and DAB; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected A06663 paraffin-section caption does not state the fixative (caption: fixative unreported). The caption uses heat-mediated EDTA retrieval at pH 8.0, but does not establish whether retrieval is required; the evidence also does not establish that frozen sections or IF are easier (caption: heat-mediated EDTA retrieval; standard IHC interpretation). In brain, pigment can complicate DAB interpretation, so compare cellular signal with the control slide (standard IHC practice).

HPA tissue IHC evidence for PFN2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebral cortex Neuropil High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →
Hippocampus Neuronal cells High Protein (IHC) HPA →
Kidney Collecting ducts High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Esophagus Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced PFN2 IHC Tips

Use the paraffin-section protocol for the catalog antibody as the starting point, then assess signal against PFN2’s reported tissue and cellular distribution.

What retrieval should I use when PFN2 staining is weak in paraffin sections?
Start with heat-mediated retrieval in EDTA, pH 8.0, for paraffin sections (datasheet A06663). The catalog antibody’s rat brain image used this retrieval before incubation at 2 µg/mL overnight at 4°C (datasheet A06663). If signal remains weak, compare retrieval heating and cooling conditions on adjacent sections while keeping antibody concentration and detection constant; excessive heating can damage morphology (standard IHC practice). Judge any improvement in neuronal cells and neuropil, where strong staining is reported, alongside a no-primary control so stronger background is not mistaken for recovered antigen (HPA: neuronal cells and neuropil High; standard IHC practice).
How should I assess whether fixation is limiting PFN2 detection?
The catalog image identifies paraffin-embedded rat brain sections but does not state their fixative or fixation duration (datasheet A06663). Target-specific sensitivity to fixation is therefore unknown; tissue staining patterns and protein features cannot establish it (HPA: tissue IHC profile; UniProt P35080). If section preparation records are available, compare matched samples with documented fixation histories using the same EDTA, pH 8.0 retrieval and 2 µg/mL primary concentration (datasheet A06663; standard IHC practice). Review morphology and no-primary controls alongside PFN2 signal, because fixation-related tissue damage or nonspecific staining can complicate interpretation of weak chromogenic labeling (standard IHC practice).
Where should convincing PFN2 staining appear within a positive tissue?
Prioritize cytoplasmic labeling: PFN2 is annotated in the cytoplasm and cytoskeleton, without a transmembrane segment (UniProt P35080). Tissue IHC reports variable cytoplasmic expression, with high signal in caudate neuronal cells, cerebral cortex neuropil, and kidney collecting ducts (HPA: tissue IHC). The HPA subcellular summary says “Membrane,” but supplies no ICC/IF images here; treat a membrane-only DAB pattern cautiously rather than assigning it as the expected paraffin-section pattern (HPA: subcellular summary; HPA: tissue IHC). Compare stained cells with adjacent morphology and a no-primary control, particularly where cytoplasmic DAB could obscure cell boundaries (standard IHC practice).
Can this IHC stain distinguish PFN2 isoforms or reveal an inaccessible epitope?
PFN2 has 2 annotated isoforms, IIa and IIb, while the supplied antibody caption gives no epitope or isoform-specific reactivity (UniProt P35080; datasheet A06663). Consequently, assign positive DAB staining to PFN2 immunoreactivity without attributing it to either isoform (UniProt P35080; datasheet A06663). PFN2 has no annotated transmembrane segment, glycosylation sites, or signal peptide, and includes an N-acetylalanine at position 2; these annotations do not establish which residues the antibody recognizes (UniProt P35080). If an isoform-specific conclusion matters, obtain epitope and cross-reactivity documentation or use a separately validated isoform-discriminating assay (standard IHC practice).
How can I check the IHC pattern with multiplex IF?
Use multiplex IF as a separate validation experiment: the supplied catalog example establishes paraffin-section chromogenic IHC, while no IF result is provided for that antibody (datasheet A06663). In brain sections, pair PFN2 with a neuronal cell marker and assess the neuronal cells or neuropil reported as high in tissue IHC (HPA: neuronal cells and neuropil High). Choose fluorophores after measuring tissue autofluorescence in each detection channel, and include single-stain controls to identify bleed-through (standard IF practice). PFN2 has no transmembrane segment and is annotated in the cytoplasm and cytoskeleton, so test gentle permeabilisation for access to intracellular epitopes without assuming the undisclosed antibody epitope (UniProt P35080; standard IF practice).
What should I change if DAB staining spreads across the section?
First compare a no-primary section with the complete stain to separate detection-system background from primary-antibody signal (standard IHC practice). The catalog example used 10% goat serum, 2 µg/mL primary antibody overnight at 4°C, a biotinylated secondary for 30 minutes at 37°C, and a streptavidin–biotin system with DAB (datasheet A06663). If diffuse staining persists, check blocking, washes, primary concentration, and DAB development consistently across adjacent sections; peroxidase blocking is a general chromogenic IHC step (standard IHC practice). Evaluate endogenous biotin when using the documented biotin-based detection system, using appropriate detection controls before calling widespread cytoplasmic color PFN2 (datasheet A06663; standard IHC practice).
How should I score PFN2 IHC across regions with different cell populations? ⚠ ANSWER MARKED FOR VERIFICATION
Define regions and cell populations before scoring, because PFN2 tissue IHC varies across cell types and reports high signal in caudate neuronal cells, cerebral cortex neuropil, and kidney collecting ducts (HPA: tissue IHC). For identifiable cells, record percent positive and staining intensity as an H-score; for neuropil, measure DAB-positive area or optical density per mm² using a fixed threshold (standard IHC practice). Normalize cellular scores to the relevant counted cells and neuropil measurements to the annotated neuropil area, while applying identical acquisition and color-deconvolution settings across sections (standard IHC practice). Report background-subtracted results, section counts, region definitions, and the no-primary threshold so changes in tissue composition are distinguishable from staining changes (standard IHC practice).
How do I distinguish true PFN2 signal from section artefact?
Look for cytoplasmic labeling in plausible cells and neuropil, consistent with PFN2’s cytoplasm and cytoskeleton annotation and the reported high brain tissue IHC pattern (UniProt P35080; HPA: tissue IHC). Strong color confined to section edges, necrotic areas, or a no-primary control needs investigation as an artefact or detection background (standard IHC practice). Likewise, question a membrane-only pattern or staining assigned to the wrong cell population before interpreting it as PFN2 expression (UniProt P35080; HPA: tissue IHC; standard IHC practice). Endogenous enzyme activity can also produce misleading chromogenic signal, so verify peroxidase blocking and compare controls; HPA rates tissue reliability “Enhanced” while reporting only medium agreement between staining and RNA data (standard IHC practice; HPA: reliability).
Boster reagents

Best PFN2 / Profilin-2 IHC Antibodies

Anti-PFN2 catalog antibodies have paraffin-section IHC images from human, mouse, and rat tissues, plus an IF/ICC image from SH-SY5Y cells (catalog image captions).

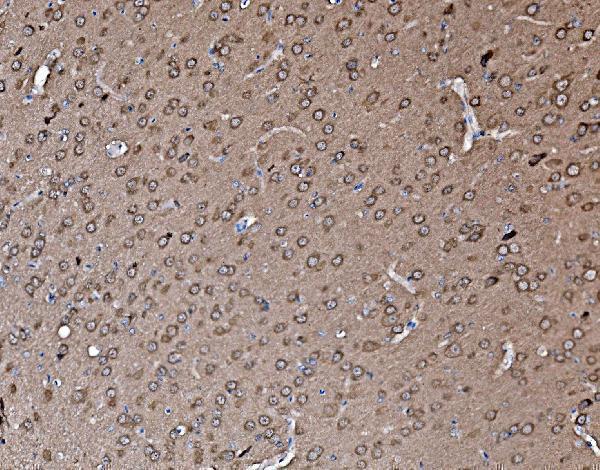
Real IHC data IHC analysis of Profilin 2/PFN2 using anti-Profilin 2/PFN2 antibody (A06663). Profilin 2/PFN2 was detected in paraffin-embedded section of rat brain tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml rabbit anti-Profilin 2/PFN2 Antibody (A06663) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-Profilin 2/PFN2 Antibody ®
Cat # A06663

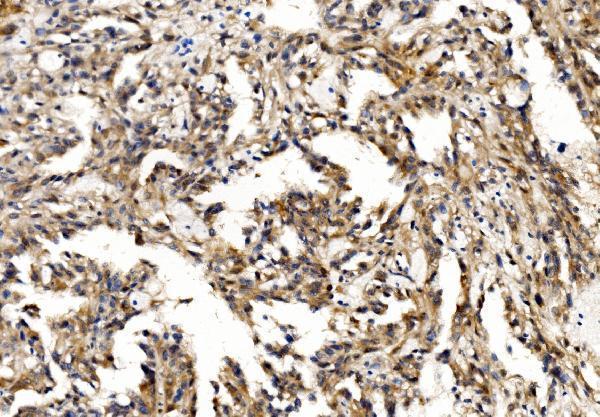
The rendered A06663 card shows paraffin-section IHC in rat brain; its additional captions show mouse brain and human renal cancer (A06663 image captions). PA2162 has paraffin-section IHC images from human tonsil and intestinal cancer, plus an IF/ICC image from SH-SY5Y cells (PA2162 image captions).

Which to pick: For tissue IHC, choose A06663 when its rat or mouse brain or human renal cancer examples match your sample; its captions use EDTA retrieval at pH 8 and 2 μg/ml primary antibody (A06663 image captions). For IF/ICC, choose PA2162, which lists both applications and shows SH-SY5Y cell staining at 5 μg/ml (PA2162 applications and IF caption). Both list human, mouse, and rat reactivity for cross-species work; their IHC captions establish paraffin sections but do not report the fixative, and clonality is unreported (catalog reactivity, IHC captions, and clone fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P35080 (PROF2_HUMAN, Profilin-2).
  2. Human Protein Atlas. PFN2 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. PFN2 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. PFN2 antibody validation summary (2 antibodies).
  5. OCT1-target neural gene PFN2 promotes tumor growth in androgen receptor-negative prostate cancer. Scientific reports 2022 — PMC9005514.
  6. Loss of profilin 2 contributes to enhanced epithelial-mesenchymal transition and metastasis of colorectal cancer. International journal of oncology 2018 — PMC6065425.
  7. The novelty of profilin 2 in regulating pyruvate kinase M2 nuclear translocation and promoting tumor angiogenesis in lung adenocarcinoma. Respiratory research 2025 — PMC12123718.
  8. PFN2, a novel marker of unfavorable prognosis, is a potential therapeutic target involved in esophageal squamous cell carcinoma. Journal of translational medicine 2016 — PMC4870769.
  9. PubMed PMID:8365484 — UniProt-cited evidence.
  10. PubMed PMID:11027290 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.