PHLDA3 / Pleckstrin homology-like domain family A member 3 · IHC design guide

Design Immunohistochemistry for PHLDA3

Plan PHLDA3 paraffin IHC with the catalog antibody at 1:100–1:300 (datasheet: IHC). Use cytoplasmic staining as the tissue reference pattern while accounting for low consistency between antibody staining and RNA expression (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PHLDA3 (IHC for PHLDA3): expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody A09241, validated IHC image, and IHC protocol steps
Printable PHLDA3 IHC protocol sheet — expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody A09241, controls and protocol steps. Open the full PHLDA3 IHC guide →

PHLDA3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC)
Staining pattern Cytoplasmic staining in glandular and other tissue cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent (standard IHC practice; not target-specific)
Caveat Antibody staining and RNA show low consistency (HPA tissue IHC)
Regulation p53-regulated expression (UniProt)
Isoform / epitope No annotated isoforms or processing; no TM segment (UniProt)
Section 1

Recommended PHLDA3 IHC & IF Protocols

Compare the catalog antibody’s paraffin-section IHC protocol (datasheet) with published PHLDA3 protocols for brain tissue, porcine ovary, and thoracic tumors (PMC12646473; PMC7432752; PMC7947487).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast carcinoma tissue; fixative not specified (datasheet A09241)
FixationImage fixative and duration unreported (datasheet A09241); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-PHLDA3, 1:100-1:300 (datasheet A09241)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPHLDA3-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval); the published frozen-section protocol used sub-boiling citrate for 10 min (PMC7432752).
Section 2

What Is the Expected PHLDA3 Staining Pattern?

PHLDA3 should show predominantly cytoplasmic staining in many tissues, with possible membrane-associated signal (HPA: cytoplasmic expression in most tissues; UniProt Q9Y5J5: cytoplasm and membrane, no transmembrane segment). Medium staining is reported in selected glandular, respiratory epithelial, hematopoietic, neuronal, and endothelial cells (HPA tissue IHC). HPA rates the tissue staining Approved but reports low consistency with RNA expression; interpret intensity alongside cell identity and controls (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic signal in adrenal or breast glandular cells, bronchial respiratory epithelial cells, or marrow hematopoietic cells.These are plausible positives: HPA reports Medium staining in those cell types and cytoplasmic expression across most tissues (HPA tissue IHC). Compare the named cells with nearby tissue structures when scoring; widespread color alone does not identify the positive population.
Cytoplasmic signal with a membrane-associated rim in the expected cells.The cytoplasmic component matches the HPA tissue profile; membrane association is compatible with UniProt localisation and a PH domain spanning residues 8–127 (HPA tissue IHC; UniProt Q9Y5J5). A membrane rim is not required for a positive IHC result because HPA describes the observed tissue pattern as cytoplasmic.
Strong, predominantly nuclear staining with little cytoplasmic signal.Treat this as a compartment mismatch requiring review, since the supplied localisation is cytoplasm and membrane, with no nuclear location reported (HPA tissue IHC; UniProt Q9Y5J5). Check the counterstain and staining controls before assigning the nuclear color to PHLDA3.
Intense color in a cell population outside the reported positive populations, especially if it also appears in a negative control.The cell identity is discordant with the cited HPA examples (HPA tissue IHC). Cross-reactivity or endogenous chromogenic detection activity is possible in IHC; a reagent-omission control and appropriate blocking help distinguish those possibilities (standard IHC practice).
Diffuse color over cells and tissue spaces, or no signal in a section expected to stain.Diffuse color without cell boundaries is difficult to score as specific PHLDA3 (standard IHC practice). An unstained HPA Medium reference tissue warrants a check of tissue preservation, retrieval, antibody use, and detection controls; HPA's Approved rating has low RNA–staining consistency (HPA tissue IHC).
💡Expected PHLDA3 appearanceCall a result positive when discernible, mainly cytoplasmic color marks an HPA-reported cell population at an intensity consistent with its reference category—such as Medium in adrenal glandular cells—while diffuse background or isolated strong nuclear color prompts review (HPA tissue IHC; UniProt Q9Y5J5).
How each factor affects the staining
Cell population and tissue choiceHPA reports Medium staining in adrenal, appendix, and breast glandular cells; bronchial respiratory epithelial cells; marrow hematopoietic cells; and selected neural or endothelial cells (HPA tissue IHC). Match the scored cell population, since adjacent cells in one section need not share the reported level.
Lower-signal reference tissueHPA reports Low staining in hepatocytes and splenic red-pulp cells, and Not detected in adipocytes (HPA tissue IHC). UniProt describes broad expression with its lowest expression in liver and spleen (UniProt Q9Y5J5). These are less useful as sole positive controls than an HPA Medium population.
Intracellular localisationUniProt places PHLDA3 in cytoplasm and membrane and reports no transmembrane segment (UniProt Q9Y5J5). HPA tissue IHC describes a cytoplasmic pattern (HPA tissue IHC). Interpret an apparent membrane rim in that context; the record does not establish a required membrane-to-cytoplasm ratio.
Strength of validation evidenceHPA lists antibody HPA027601 as IHC Approved, yet flags low consistency between antibody staining and RNA expression (HPA antibody validation; HPA tissue IHC). Approved should therefore be read with that stated caveat, rather than as proof that every colored cell is target-specific.
ICC/IF evidence boundaryHPA supplies no main subcellular location or cell lines with ICC/IF images, and lists no ICC validation for HPA027601 (HPA subcellular; HPA antibody validation). The tissue IHC pattern can guide what to inspect in IF, but does not validate an IF staining pattern.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
An HPA Medium reference cell population shows no chromogenic signal.The expected population may be absent from the section, or an IHC workflow component may have failed; HPA reports Medium staining for the specified cells (HPA tissue IHC).Verify the cell population on the counterstained section, then check the primary-antibody step, retrieval conditions, detection reagents, and a working positive control (standard IHC practice). No PHLDA3-specific retrieval condition is established here.
The whole section is pale brown, including spaces between cells.Diffuse background can result from insufficient washing, excess reagent, or nonspecific chromogen deposition (standard chromogenic IHC practice). It does not resemble HPA's cellular cytoplasmic profile (HPA tissue IHC).Inspect reagent-omission controls, washing, and detection conditions; score only signal that can be assigned to cells after background is controlled (standard IHC practice).
A strongly stained cell type disagrees with the HPA pattern.Cross-reactivity or endogenous detection activity may contribute, particularly if a control without primary antibody also develops color (standard IHC practice). HPA reports distinct staining levels by cell type (HPA tissue IHC).Identify the cells histologically, compare the matching HPA tissue entry, and inspect reagent-omission and endogenous-activity controls before calling them PHLDA3-positive (HPA tissue IHC; standard IHC practice).
Nuclear color dominates the slide.Predominantly nuclear staining conflicts with the supplied cytoplasm-and-membrane localisation (UniProt Q9Y5J5; HPA tissue IHC). Counterstain or nonspecific detection can complicate visual assignment (standard IHC practice).Review the chromogen and counterstain separately, compare a negative staining control, and require a credible cellular cytoplasmic component before accepting the pattern (standard IHC practice; HPA tissue IHC).
Adipocytes are negative while nearby cells stain.HPA reports adipocytes as Not detected; staining in another cell population does not change that adipocyte reference level (HPA tissue IHC).Score adipocytes separately from neighboring cells. Use an HPA Medium population as the positive reference if assay performance needs checking (HPA tissue IHC).
Can the IHC result establish the expected IF/ICC pattern?HPA provides no ICC/IF image-bearing cell line, no main ICC/IF location, and no ICC validation for the listed antibody (HPA subcellular; HPA antibody validation).Treat cytoplasmic and possible membrane signal as a localisation hypothesis from HPA tissue IHC and UniProt Q9Y5J5; use the separate IF/ICC guide for assay design and controls.

Sample controls for PHLDA3 IHC & IF

🧪Run breast first: glandular cells should show medium staining (HPA: Medium in breast glandular cells; selected A09241 caption: paraffin-embedded breast carcinoma). Run adipose tissue as the negative: adipocytes are not detected (HPA: Not detected in adipocytes); on the breast slide, use unstained adjacent nonglandular cells as a background reference only after confirming they are unstained, rather than assuming they are PHLDA3-negative (HPA: breast glandular-cell annotation only).
Positive control tissue: Adrenal gland (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for PHLDA3; derive a cell-line control from the positive tissue's cell type (Glandular cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control and an isotype control matched to the primary antibody’s host species and clonality (standard IHC practice). Use a PHLDA3 knockout specimen or peptide competition as a biological specificity control (standard IHC practice; selected A09241 caption: peptide-blocked breast carcinoma image), and quench endogenous peroxidase before chromogenic detection (standard IHC practice).
⚠️Feasibility: A target-specific fixation window and antigen-retrieval dependence are unreported; the selected A09241 caption describes a paraffin-embedded breast carcinoma section but does not report its fixative (selected A09241 caption). The supplied evidence does not establish whether frozen sections or IF are easier; HPA lists no ICC-IF images for PHLDA3 (HPA subcellular record). No breast-specific staining artefact is reported in the supplied evidence; interpret cytoplasmic and membrane staining in light of the annotated localisation (UniProt Q9Y5J5: Cytoplasm; Membrane).

HPA tissue IHC evidence for PHLDA3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bone marrow Hematopoietic cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced PHLDA3 IHC Tips

Troubleshoot PHLDA3 chromogenic IHC by checking retrieval, staining compartment, controls and cell-specific scoring before interpreting signal.

How should I retrieve PHLDA3 in paraffin sections when staining is weak?
Start with citrate pH 6.0 heat-induced antigen retrieval at 95–98 °C for 20 min (page retrieval rule: cytoplasmic/membrane antigen). Keep section thickness, heating vessel and cooling procedure consistent across the comparison set so retrieval is the variable under test (standard IHC practice). If staining remains weak, compare a modestly longer heating time on adjacent sections while monitoring tissue damage and background (standard IHC practice). Include a known staining reference and a no-primary control in the same run (standard IHC practice). The selected A09241 image documents staining in paraffin-embedded breast carcinoma, but its caption does not report a retrieval method or fixative (A09241 caption).
Can I adjust fixation to improve PHLDA3 staining?
Target-specific sensitivity to fixation is unknown from the supplied evidence (A09241 caption: fixative unreported). Record the actual fixative, fixation duration and processing history for each specimen before comparing PHLDA3 staining (standard IHC practice). On matched material, compare routine fixation conditions while keeping citrate pH 6.0 retrieval at 95–98 °C for 20 min and detection settings constant (page retrieval rule; standard IHC practice). Use tissue preservation and staining in an internal reference cell population to judge each condition (standard IHC practice). Neither the reported tissue staining pattern nor the absence of annotated glycosylation establishes a PHLDA3-specific fixation effect (HPA tissue IHC; UniProt Q9Y5J5 record).
Where should convincing PHLDA3 chromogenic signal appear?
Assess cytoplasmic staining first: HPA reports cytoplasmic expression in most tissues, while UniProt also lists a membrane location (HPA tissue IHC; UniProt Q9Y5J5 localisation). A membrane-associated component is plausible, but PHLDA3 has no annotated transmembrane segment, so a sharply exclusive membrane rim needs additional validation (UniProt Q9Y5J5 topology; standard IHC interpretation). Compare the pattern with cell morphology and a no-primary control under identical chromogen exposure (standard IHC practice). HPA reports medium staining in breast glandular cells and no detected staining in adipocytes, which can guide examination of suitable sections (HPA tissue IHC). Treat isolated nuclear-only signal as discordant with the supplied localisation evidence until independently confirmed (UniProt Q9Y5J5 localisation).
How can I assess whether the antibody recognises the intended PHLDA3 epitope?
Map the antibody immunogen to the 127-aa PHLDA3 sequence and its annotated PH domain at residues 8–127, if the immunogen sequence is available (UniProt Q9Y5J5 record; standard IHC practice). The supplied record lists one chain and no annotated isoforms, glycosylation sites or modified residues; those annotations do not establish where this antibody binds (UniProt Q9Y5J5 record). The A09241 caption reports that synthesized peptide blocked the breast carcinoma IHC image, supporting peptide-competitive staining in that image (A09241 caption). Compare adjacent sections with and without the competing peptide under identical detection settings (standard IHC practice). Competition alone cannot exclude recognition of another tissue antigen bearing a similar epitope (standard IHC interpretation).
What should I check before comparing PHLDA3 IHC with multiplex IF?
Treat IF as a separate validation experiment because the supplied A09241 evidence describes paraffin-section chromogenic IHC, with no IF result or stated fixative (A09241 caption). Multiplex PHLDA3 with a validated marker for the cell type being evaluated, and confirm each channel using single-stain controls (standard IF practice). Choose fluorophores after inspecting unstained tissue autofluorescence, favoring a spectrally distinct channel with adequate signal (standard IF practice). For an intracellular epitope, titrate permeabilisation to permit access while retaining morphology; membrane association alone does not establish an extracellular epitope (UniProt Q9Y5J5 localisation and topology; standard IF practice). Compare IF distribution with the expected cytoplasmic IHC pattern, without treating agreement as antibody specificity proof (HPA tissue IHC; standard IHC/IF interpretation).
How do I reduce diffuse brown background without losing PHLDA3 signal?
Run no-primary and detection-only controls to identify staining from the detection system before changing antibody conditions (standard IHC practice). Block endogenous peroxidase for the chromogenic workflow, then check whether pigment, tissue edges or necrotic areas retain colour in the controls (standard IHC practice). If background persists, titrate primary antibody and incubation time on adjacent sections while holding citrate pH 6.0 retrieval at 95–98 °C for 20 min constant (page retrieval rule; standard IHC practice). Use an appropriate protein block and sufficient washes, documenting each change alongside tissue preservation (standard IHC practice). Judge improvement by cleaner cellular cytoplasmic staining rather than a lower whole-slide brown signal alone (HPA tissue IHC; standard IHC interpretation).
How should I quantify heterogeneous PHLDA3 staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the tissue compartment and eligible cells before scoring, then exclude folds, necrosis and section edges by the same rule for every slide (standard IHC practice). An H-score combines the percentage of cells at each intensity level, commonly 0–3, into a 0–300 score; report the scoring scheme explicitly (standard IHC practice). Alternatively, report percentage-positive cells or positive-cell density per mm² when cell counts and sampled area are reliable (standard IHC practice). Normalise counts to eligible cells or tissue area within the same annotated compartment, and use matched processing and chromogen exposure across groups (standard IHC practice). Report cytoplasmic and membrane-associated signal separately if both are scored (UniProt Q9Y5J5 localisation; standard IHC practice).
What distinguishes convincing PHLDA3 staining from an artefact?
Look for reproducible cytoplasmic staining in intact, identifiable cells; HPA reports cytoplasmic expression in most tissues but notes low consistency between antibody staining and RNA expression (HPA tissue IHC). A membrane-associated component is compatible with the UniProt location annotation, whereas nuclear-only staining calls for independent confirmation (UniProt Q9Y5J5 localisation; standard IHC interpretation). Check cell identity against the section: HPA reports medium staining in breast glandular cells and no detected staining in adipocytes (HPA tissue IHC). Disregard signal confined to edges, necrotic regions or endogenous-enzyme-positive controls until the artefact is resolved (standard IHC practice). The peptide-blocked A09241 image supports competition in that specimen, not universal staining specificity (A09241 caption; standard IHC interpretation).
Boster reagents

Best PHLDA3 / Pleckstrin homology-like domain family A member 3 IHC Antibodies

A09241 has human paraffin-section IHC imagery (catalog IHC image caption) and listed IF use (catalog applications). Human, mouse, and rat reactivity is listed (catalog reactivity); no IF image is supplied (catalog IF images).

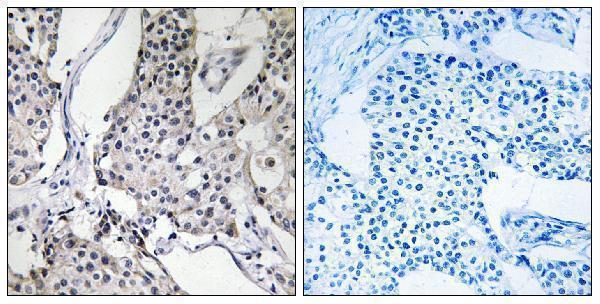
Real IHC data Immunohistochemistry analysis of paraffin-embedded human breast carcinoma tissue, using PHLDA3 Antibody. The picture on the right is blocked with the synthesized peptide.
Anti-PHLDA3 Antibody
Cat # A09241

A09241 will render with an IHC image of paraffin-embedded human breast carcinoma tissue and a peptide-blocked companion image (catalog IHC image caption). It lists IHC and IF applications and human, mouse, and rat reactivity (catalog applications; catalog reactivity).

Which to pick: Choose A09241 for tissue IHC because its own image shows a human paraffin section (catalog IHC image caption); the fixative is unreported (catalog IHC image caption). For IF, A09241 lists a 1:50 dilution (catalog IF dilution), but supplies no IF image or ICC application claim (catalog IF images; catalog applications). For cross-species studies, A09241 lists human, mouse, and rat reactivity (catalog reactivity); its host is rabbit, and clonality is unreported (catalog host; catalog clone).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9Y5J5 (PHLA3_HUMAN, Pleckstrin homology-like domain family A member 3).
  2. Human Protein Atlas. PHLDA3 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. PHLDA3 subcellular location (ICC-IF): Highest expression in RT-4: 187.0 nTPM.
  4. Human Protein Atlas. PHLDA3 antibody validation summary (1 antibodies).
  5. Quantitative proteomic analysis reveals key proteins involved in radiation-induced brain injury. PloS one 2025 — PMC12646473.
  6. Cross-talk among MEN1, p53 and Notch regulates the proliferation of pancreatic neuroendocrine tumor cells by modulating INSM1 expression and subcellular localization. Neoplasia (New York, N.Y.) 2021 — PMC8350333.
  7. Characteristics of Circular RNA Expression Profiles of Porcine Granulosa Cells in Healthy and Atretic Antral Follicles. International journal of molecular sciences 2020 — PMC7432752.
  8. The expression patterns and prognostic significance of pleckstrin homology-like domain family A (PHLDA) in lung cancer and malignant mesothelioma. Journal of thoracic disease 2021 — PMC7947487.
  9. PubMed PMID:10594239 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.